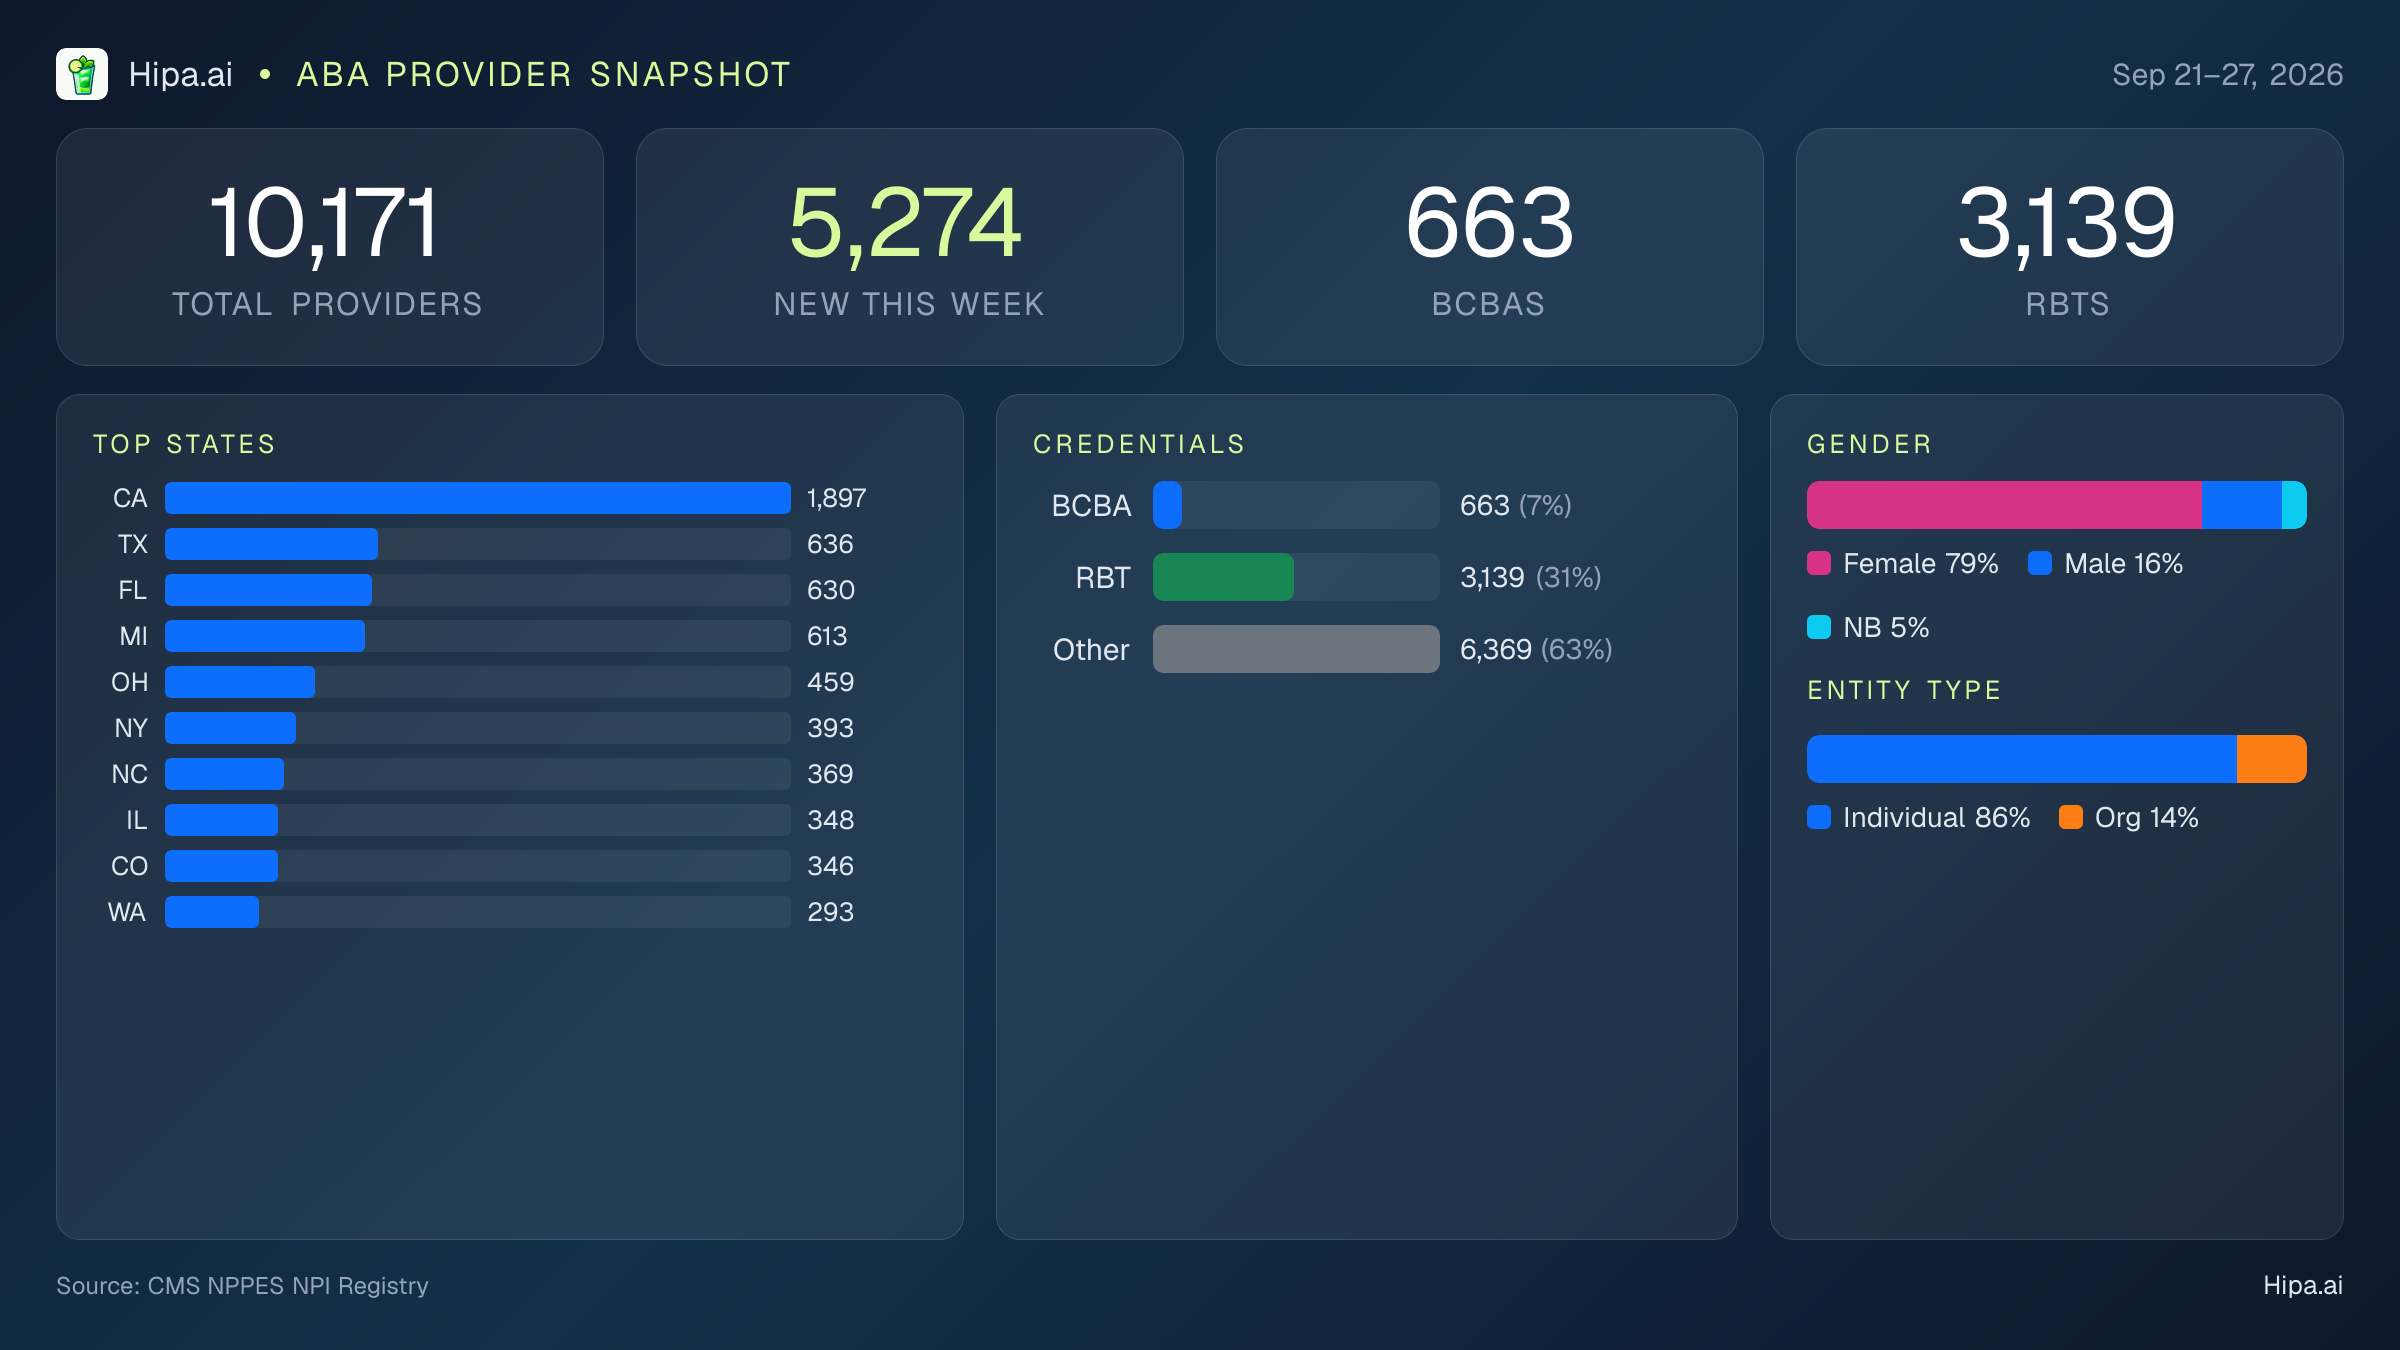
| 1213 S CHAMPION AVE LLCORG | COLUMBUS, OH | - | BCBA | 09/25/2026 |
| 180 DEGREE SUPPORT SERVICES LLCORG | RICHMOND, VA | - | Case Management Agency | 04/20/2016 |
| 1ST MERIDIAN PLACEMENT SERVICES, INCORG | SAN DIEGO, CA | - | Case Management Agency | 09/21/2026 |
| 2301 THERAPY LLCORG | BROOKLYN, NY | - | BCBA | 09/21/2026 |
| 240 SCHUNNEMUNK REALTY LLCORG | MONROE, NY | - | Case Management Agency | 09/22/2026 |
| 3-KEYS CHARITIES INCORG | NORTH LAS VEGAS, NV | - | Case Management Agency | 09/23/2026 |
| 3:16 BEHAVIORAL HEALTH & WELLNESS, PLLCORG | MULESHOE, TX | - | Mental Health Counselor | 04/30/2026 |
| 360 SUPPORT SERVICES, LLCORG | WAUWATOSA, WI | - | Mental Health Counselor | 09/22/2026 |
| 4EVERBLAZIN ENT LLCORG | ROCHESTER, NY | - | Case Manager/Care Coordinator | 07/22/2026 |
| 8A BEHAVIOR CONSULTANTS LLCORG | NORWALK, CA | - | Community/Behavioral Health Agency | 09/24/2026 |
| 913 ENTERPRISES LLCORG | RUTHER GLEN, VA | - | Case Manager/Care Coordinator | 06/29/2026 |
| A BETTER DAY COUNSELING LLCORG | DULUTH, GA | - | Professional Counselor | 02/16/2016 |
| A BLY TBI NHTD LLCORG | MELROSE, NY | - | Counselor | 09/22/2026 |
| A DASH OF MINDFULNESS PSYCHOTHERAPYORG | RICHMOND, VA | - | Clinical Social Worker | 11/18/2020 |
| A NEW DAY MANAGEMENT LLCORG | SALISBURY, MD | - | Mental Health Counselor | 09/23/2026 |
| A TRUE PATH CARE GROUPORG | KATY, TX | - | Case Management Agency | 09/21/2026 |
| A VOICE HAS WEIGHT LLCORG | LAWRENCEVILLE, VA | - | Case Management Agency | 09/21/2026 |
| A'NEW CHILD AND FAMILY GUIDANCE CENTER PLLCORG | FORT BELVOIR, VA | - | Mental Health Counselor | 09/21/2026 |
| AB SOLUTIONS LLCORG | SAN ANTONIO, TX | - | BCBA | 08/28/2020 |
| ABA ACHIEVE PLLCORG | FRISCO, TX | - | BCBA | 09/23/2026 |
| ABA ADVANTAGE LLCORG | CHANDLER, AZ | - | BCBA | 05/05/2023 |
| ABA PUZZLE LLCORG | MIAMI, FL | - | Speech-Language Pathologist | 01/09/2025 |
| ABA THERAPY TITAN, LLCORG | ORANGE PARK, FL | - | BCBA | 09/25/2026 |
| ABATZIS, EMELIA | LEXINGTON, NC | - | Counselor | 09/23/2026 |
| ABBOOD, SAFAA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| ABBOTT, LINDSAY | WAKE FOREST, NC | - | Mental Health Counselor | 09/24/2026 |
| ABC CARE LICENSED BEHAVIOR ANALYST PLLCORG | FALLSBURG, NY | - | BCBA | 09/22/2026 |
| ABDI, FATUMA | SAVAGE, MN | - | RBT | 09/23/2026 |
| ABDI, ZAKARIYE | ROSEVILLE, MN | - | RBT | 09/22/2026 |
| ABDON, MICHAEL | TACOMA, WA | LMHC | Mental Health Counselor | 11/01/2024 |
| ABDUL, AVIA | WEST PALM BEACH, FL | - | RBT | 09/22/2026 |
| ABDULAALI, AMINA | BURNSVILLE, MN | - | RBT | 09/22/2026 |
| ABDULELAH, FURKAN | WOODBURY, MN | - | RBT | 09/25/2026 |
| ABDULLAHI, ABSHIR | BROOKLYN CENTER, MN | - | RBT | 09/23/2026 |
| ABEDI, ROSEMON | GRANDVILLE, MI | - | RBT | 09/22/2026 |
| ABEGGLEN, OLIVIA | DE PERE, WI | BCBA | RBT | 04/08/2022 |
| ABENROTH, MARIE-ANNE | CANISTOTA, SD | LPC; LAC; NCC | Mental Health Counselor | 04/24/2019 |
| ABERGER, JOHANN | CARBONDALE, CO | LPCC | Counselor | 09/25/2026 |
| ABERNATHY, BREANNA | FAIRFAX, VA | - | RBT | 09/21/2026 |
| ABH PENNSYLVANIA CHILDRENS SERVICES INCORG | MALVERN, PA | - | Community/Behavioral Health Agency | 07/11/2023 |
| ABH PENNSYLVANIA CHILDRENS SERVICES INCORG | MALVERN, PA | - | Community/Behavioral Health Agency | 07/14/2023 |
| ABIDAKUN, OREOLUWA | HOUSTON, TX | MS | Clinical Social Worker | 09/25/2026 |
| ABNER, DERIONAH | PRINCESS ANNE, MD | LGPC | Counselor | 09/17/2026 |
| ABNEY, ERIC | MOUNTAIN BRK, AL | LICSW | Clinical Social Worker | 02/21/2025 |
| ABO BEHAVIORAL HEALTH LLCORG | FORT WASHINGTON, PA | - | BCBA | 02/16/2026 |
| ABQ WELLNESS PCORG | ALBUQUERQUE, NM | - | Clinical Social Worker | 07/02/2025 |
| ABRAHAM, JORDYN | LONGVIEW, WA | CPSS, SUDPT | Counselor | 12/18/2023 |
| ABRAHAM, SARAH | NORTH CHESTERFIELD, VA | - | Mental Health Counselor | 09/22/2026 |
| ABRAM, PATRICIA | HOUSTON, TX | - | RBT | 09/21/2026 |
| ABREGO, BRITNEE | COLUMBIA, MD | - | RBT | 09/26/2026 |
| ABSHER, CONNIE | NEWPORT, OR | - | Mental Health Counselor | 09/19/2022 |
| ABU SAMAHA, LINA | CAMPBELL, CA | - | BCBA | 05/03/2022 |
| ABUBAKAR, KHADIJAT | BALTIMORE, MD | - | RBT | 09/24/2026 |
| ABUDU, IBILAYO | COLUMBIA, MD | - | RBT | 09/21/2026 |
| ABUKAR, MUHANNAD | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| ABUNDANT FAMILY PRACTICE PLLCORG | MIDLAND, TX | - | Clinic/Center | 09/14/2026 |
| ABUNDANTLY YOU COUNSELING SERVICES, LLCORG | PITTSFIELD, MA | - | Community/Behavioral Health Agency | 09/23/2026 |
| ACAB, CHALE'T | HERNDON, VA | - | BCBA | 09/15/2020 |
| ACADIAN HEALTH ALLIANCEORG | LAFAYETTE, LA | - | Mental Health Counselor | 09/21/2026 |
| ACEVEDO MENA, JESSICA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ACEVEDO, LISSETT | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| ACEVES, EMMA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| ACEVES, KAYLA | SAN BERNARDINO, CA | - | RBT | 09/24/2026 |
| ACHA, CEPHAS | WASHINGTON, DC | - | Case Manager/Care Coordinator | 01/22/2024 |
| ACHIEVE WNCORG | ASHEVILLE, NC | - | Community/Behavioral Health Agency | 06/07/2017 |
| ACHIEVEMENT AUTISM SERVICES IL LLCORG | CHICAGO, IL | - | BCBA | 09/23/2026 |
| ACHIEVEMENT AUTISM SERVICES TX LLCORG | FORT WORTH, TX | - | BCBA | 09/23/2026 |
| ACHIEVEMENTS UNLIMITED CLINICAL PSYCHOLOGY SERVICES, INC.ORG | VISALIA, CA | - | Community/Behavioral Health Agency | 06/21/2016 |
| ACORN ABA LLCORG | NASHUA, NH | - | BCBA | 09/23/2026 |
| ACORN HEALTHORG | FORT CAMPBELL, KY | - | BCBA | 09/21/2026 |
| ACORN TO OAK PLAY THERAPY LLCORG | ALTOONA, IA | - | Clinical Social Worker | 09/23/2026 |
| ACOSTA MENA, RACHEL | MIAMI, FL | - | BCBA | 11/01/2018 |
| ACOSTA MONTOYA, YOLANDA | TORRANCE, CA | LCSW | Clinical Social Worker | 06/17/2021 |
| ACOSTA-SEGURA, ISABELLA | RANCHO CUCAMONGA, CA | MSW | Clinical Social Worker | 06/16/2022 |
| ACOSTA, ALBERTO | FORT RILEY, KS | - | Mental Health Counselor | 12/11/2020 |
| ACOSTA, KAYLA | VAN NUYS, CA | - | RBT | 09/22/2026 |
| ACTION BEHAVIOR CENTERS, LLCORG | AUSTIN, TX | - | BCBA | 04/13/2016 |
| ACTION RECOVERY COUNSELING LLCORG | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 11/10/2025 |
| ACTON, BRIEANNA | WEST JORDAN, UT | - | RBT | 09/22/2026 |
| ACTSS A COMMON THREAD SUPPORTIVE SERVICESORG | FORT SMITH, AR | - | Addiction (Substance Use Disorder) Counselor | 02/19/2020 |
| ADAIR COUNTY AMBULANCE DISTRICTORG | KIRKSVILLE, MO | - | Community/Behavioral Health Agency | 09/25/2026 |
| ADAM THIBODEAU PLLCORG | ARLINGTON, VA | - | Clinical Social Worker | 09/21/2026 |
| ADAME, MIKEL | KENT, WA | - | Counselor | 03/03/2025 |
| ADAME, SAMANTHA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| ADAMS HOUSE OF HEALINGORG | ABSECON, NJ | - | Professional Counselor | 08/10/2026 |
| ADAMS, CHARLES | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| ADAMS, DARREN | BOISE, ID | LCPC | Mental Health Counselor | 06/21/2017 |
| ADAMS, DESTINY | BENTONVILLE, AR | LCSW | Case Manager/Care Coordinator | 08/23/2022 |
| ADAMS, HONEY | IRVINE, CA | - | RBT | 09/21/2026 |
| ADAMS, ISABELLA | ALBUQUERQUE, NM | LMSW | Clinical Social Worker | 09/24/2026 |
| ADAMS, KATHERINE | ORLANDO, FL | LMHC | Mental Health Counselor | 07/02/2022 |
| ADAMS, KIANNA | DALTON, GA | - | Professional Counselor | 09/23/2026 |
| ADAMS, KYLELYNNE | CARLSBAD, CA | - | RBT | 09/23/2026 |
| ADAMS, SARAH | APPLE VALLEY, MN | M.S., CCC-SLP | Speech-Language Pathologist | 09/23/2014 |
| ADAMS, TATIANNA | HENDERSONVILLE, NC | LCSW-A | Clinical Social Worker | 12/02/2020 |
| ADDIS, GORDON | PORTLAND, OR | CADCI | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| ADDISON, MAISIE | GRAND FORKS, ND | - | RBT | 09/22/2026 |
| ADEDAPO, AYOMIDE | LUTHERVILLE, MD | - | Clinical Social Worker | 02/06/2022 |
| ADEN, AMIRA | MINNEAPOLIS, MN | - | RBT | 09/21/2026 |
| ADEN, FARDOWSA | BUFFALO, NY | - | Counselor | 01/08/2019 |
| ADETUNJI, FOLASHADE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/25/2026 |
| ADEWOLE, ARAMIDE | ELKRIDGE, MD | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| ADHD ALLIANCE OF MN PLLCORG | EDINA, MN | - | Clinic/Center | 11/14/2025 |
| ADKHAMOVA, ODINAKHON | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/24/2026 |
| ADKINS, JASON | DANVILLE, VA | LPC | Mental Health Counselor | 09/24/2026 |
| ADKINS, PAIGE | GLENDALE, AZ | - | RBT | 09/23/2026 |
| ADONETTI, ANITA | TYLER, TX | LCDC | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| ADU, ESTHER | FRAMINGHAM, MA | - | Clinical Social Worker | 11/11/2024 |
| ADVANCE COUNSELING SERVICE LLCORG | HEWITT, TX | - | Mental Health Counselor | 08/18/2026 |
| ADVANCED UROLOGY INSTITUTE OF GEORGIA, LLCORG | MARIETTA, GA | - | Clinic/Center | 08/20/2019 |
| ADWELL, ALYSSA | SEATTLE, WA | MSW | Clinical Social Worker | 05/13/2019 |
| AEA, ZACHARY | CHARLOTTE, NC | - | Mental Health Counselor | 09/22/2026 |
| AEAD, DANIELLE | QUINCY, MA | - | RBT | 09/22/2026 |
| AEGIS GROUP PRACTICE LLCORG | SAINT PETER, MN | - | Speech-Language Pathologist | 09/21/2026 |
| AEGIS GROUP PRACTICE LLCORG | NORTH MANKATO, MN | - | Speech-Language Pathologist | 09/21/2026 |
| AEGIS GROUP PRACTICE LLCORG | LE SUEUR, MN | - | Speech-Language Pathologist | 09/21/2026 |
| AFFINITY COMMUNITY DEVELOPMENT, INC.ORG | SILVER SPRING, MD | - | Counselor | 10/25/2025 |
| AFFINITY HEALTH PARTNERS INCORG | GRAND RAPIDS, MI | - | Community/Behavioral Health Agency | 12/09/2025 |
| AFFINITY PSYCHOTHERAPY LCSW PLLCORG | NEW YORK, NY | - | Clinical Social Worker | 11/21/2019 |
| AGANZE, ESTELLA | FAIRFAX, VA | - | RBT | 11/22/2022 |
| AGAPE ALLIANCE GROUP, LLCORG | LOS ANGELES, CA | - | Counselor | 09/24/2026 |
| AGAPE TELEHEALTH COUNSELING LLCORG | PROVO, UT | - | Mental Health Counselor | 09/24/2026 |
| AGARWAL, SAANVI | EMERYVILLE, CA | - | RBT | 08/11/2025 |
| AGI MEDICAL PLLCORG | BROOKLYN, NY | - | Specialist | 04/08/2009 |
| AGIM, PRISCILLA | WORCESTER, MA | - | RBT | 09/22/2026 |
| AGNEW, HANNAH | PHOENIX, AZ | LCSW | Clinical Social Worker | 03/27/2026 |
| AGUILAR-HERNANDEZ, DEANNA | CARMEL, IN | - | RBT | 09/24/2026 |
| AGUILAR, ANDREA | TORRANCE, CA | - | RBT | 09/21/2026 |
| AGUILAR, BIANCA RENEE | RIVERSIDE, CA | - | RBT | 09/25/2026 |
| AGUILAR, CINDY | SAN MARCOS, CA | - | Clinical Social Worker | 07/27/2026 |
| AGUILAR, MAXWELL | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| AGUILAR, TORI | PHILLIPSBURG, NJ | - | BCBA | 08/07/2023 |
| AGUILAR, WALTER | WAUKEGAN, IL | - | Case Manager/Care Coordinator | 09/21/2026 |
| AGUILERA, KIMBERLY | PALMDALE, CA | - | Day Training/Habilitation Specialist | 03/14/2019 |
| AGUILERA, SHARON | BELTON, TX | LPC | Professional Counselor | 05/23/2018 |
| AGUIRRE, JADYN | TULSA, OK | - | RBT | 09/21/2026 |
| AGUNDEZ, CINTHYA | LAS VEGAS, NV | - | BCBA | 06/14/2019 |
| AGYEMANG-KOEHLER, STEPHEN | RIVERDALE, GA | - | RBT | 09/22/2025 |
| AHAUS, CAMPBELL | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| AHEAD & BEYOND LLCORG | NORTH BERGEN, NJ | - | BCBA | 09/24/2026 |
| AHMED, FARHANA | UPLAND, CA | - | Assistant Behavior Analyst | 09/21/2026 |
| AHMED, HUDA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| AHMED, MUNMUN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| AHMED, SARAH | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| AHUMADA, CARLA | EL CENTRO, CA | - | Assistant Behavior Analyst | 09/21/2026 |
| AHWAH, ZULEIKA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| AIKEN, BRITTANY | BEAUFORT, SC | - | Mental Health Counselor | 09/05/2022 |
| AIMEE RUST, LCPC, LMFT, LLCORG | BILLINGS, MT | - | Mental Health Counselor | 09/23/2026 |
| AIRBORNE ABA SUNRISE NM LLCORG | ALBUQUERQUE, NM | - | BCBA | 03/13/2026 |
| AIT MANSOUR, FATIMA | NILES, IL | - | RBT | 09/21/2026 |
| AJAEO HEALTHCARE SERVICES LLCORG | RANDALLSTOWN, MD | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| AKANA, SAVIAN | WAIPAHU, HI | - | RBT | 09/22/2026 |
| AKEM, JOHN PAUL JAM | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/24/2026 |
| AKIHARY, MARISSA | STANFORD, KY | - | Speech-Language Pathologist | 09/29/2022 |
| AKINS, JANEEN | OAKWOOD VILLAGE, OH | LISW | Clinical Social Worker | 09/21/2026 |
| AKPOR, BENETTE | FREDERICK, MD | - | Mental Health Counselor | 07/07/2025 |
| AKTAR, ZAHANARA | GAITHERSBURG, MD | LCSW | Clinical Social Worker | 02/20/2023 |
| AKWUE, OJORE | OMAHA, NE | LGPC | Mental Health Counselor | 09/26/2026 |
| AL-KAZAK, SHAWNA | SACATON, AZ | LAC | Mental Health Counselor | 08/18/2022 |
| ALASALY, TALA | BLAINE, MN | - | RBT | 09/24/2026 |
| ALASKAR, JENNA | CHICAGO, IL | LPC | Professional Counselor | 09/25/2026 |
| ALBA, SEBASTIAN | VAN NUYS, CA | - | RBT | 09/24/2026 |
| ALBARRAN, YESENIA | YAKIMA, WA | CMA | Addiction (Substance Use Disorder) Counselor | 02/03/2017 |
| ALBERS, AUDREY | CENTERVILLE, OH | - | RBT | 09/24/2026 |
| ALBERTI, LORNA | LINCOLN PARK, NJ | - | BCBA | 09/21/2026 |
| ALBERTY, MONICA | SHAWNEE, KS | - | RBT | 09/22/2026 |
| ALBIN, GARRETT | EUGENE, OR | REGISTERED ASSOCIATE | Professional Counselor | 03/09/2023 |
| ALBUERNE BATISTA, YOSLAYDA | MIAMI, FL | - | Speech-Language Pathologist | 01/18/2021 |
| ALBUQUERQUE INDIAN HEALTH CENTERORG | ALBUQUERQUE, NM | - | Clinic/Center | 11/01/2006 |
| ALCALA RAMOS, VANESSA | VAN NUYS, CA | - | RBT | 09/24/2026 |
| ALCANTAR, ALEJANDRA | MOBILE, AL | BCABA | Assistant Behavior Analyst | 10/25/2022 |
| ALCANTAR, CLAUDIA | CALHOUN, TN | - | RBT | 09/26/2026 |
| ALCANTAR, VICTORIA | COVINA, CA | - | Assistant Behavior Analyst | 12/17/2025 |
| ALCARAZ, DAISY | TORRANCE, CA | - | RBT | 09/21/2026 |
| ALDARONDO HERNANDEZ, ARIADNA | BEDFORD, NH | PHD | Psychologist | 09/12/2018 |
| ALDDELL, LYNN | OREM, UT | - | Clinical Social Worker | 04/14/2022 |
| ALDERN, EZRA | DENVER, CO | LCSW | Clinical Social Worker | 09/22/2026 |
| ALDRETE, DAISY | NAMPA, ID | - | RBT | 09/21/2026 |
| ALEGRIA, KATARINA | ORANGE, CA | - | RBT | 09/24/2026 |
| ALEGRIA, SANDY | OAKLAND, CA | - | Clinical Social Worker | 12/14/2020 |
| ALEISA, PAULETTA | LOWMANSVILLE, KY | - | Mental Health Counselor | 04/23/2012 |
| ALEMAN, ALLISYN | ABINGDON, VA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| ALETHEIA BEHAVIOR SERVICES, LLCORG | WASILLA, AK | - | BCBA | 09/23/2026 |
| ALEX WALLACE COUNSELING LLCORG | LUDLOW FALLS, OH | - | Mental Health Counselor | 09/23/2026 |
| ALEXANDER HEALTHCARE SERVICES INCORG | MINT HILL, NC | - | Case Management Agency | 09/24/2026 |
| ALEXANDER, ALAYNA | HUNTERSVILLE, NC | - | RBT | 09/22/2026 |
| ALEXANDER, ALEXUS | EDMOND, OK | MA, LPC CANDIDATE | Counselor | 09/26/2026 |
| ALEXANDER, ALYSSA | GRAND ISLAND, NE | LICSW | Mental Health Counselor | 02/28/2018 |
| ALEXANDER, JERVONI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| ALEXANDER, MATTHEW | TUMWATER, WA | - | Counselor | 09/25/2026 |
| ALFANO, HEATHER | HENDERSONVILLE, NC | LCSW, LCAS, RYT | Addiction (Substance Use Disorder) Counselor | 01/03/2008 |
| ALFARO, BRIAN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ALFARO, BRIANNA | KINGWOOD, TX | - | RBT | 09/23/2026 |
| ALFARO, MELANIE | COVINA, CA | - | RBT | 06/01/2022 |
| ALFARO, NATALIE | NEWPORT BEACH, CA | - | RBT | 09/25/2026 |
| ALFARO, PATRICIA | SANTA MARIA, CA | - | Addiction (Substance Use Disorder) Counselor | 12/07/2021 |
| ALFIERI, MONICA | NEWTOWN, PA | - | Counselor | 09/22/2026 |
| ALGOVER, CLAUDIA | SAN DIEGO, CA | - | Mental Health Counselor | 09/21/2026 |
| ALHARBY, MONA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| ALI KHALIL, MOUSTAFA | ANN ARBOR, MI | LLMSW | Clinical Social Worker | 09/21/2026 |
| ALI, AARALYN | RIVERSIDE, CA | - | RBT | 09/25/2026 |
| ALI, HUSSAIN | GASTONIA, NC | - | Assistant Behavior Analyst | 09/24/2026 |
| ALI, RUMANA | SYOSSET, NY | - | Mental Health Counselor | 09/21/2026 |
| ALI, SALEEMA | LODI, CA | AMFT, APCC | Mental Health Counselor | 02/14/2024 |
| ALI, SUMAYA | EL SEGUNDO, CA | - | RBT | 10/27/2025 |
| ALIGN SERVICES OF WYOMING, INC.ORG | LARAMIE, WY | - | Case Manager/Care Coordinator | 05/28/2026 |
| ALIGN YOUR MIND COUNSELINGORG | LA MARQUE, TX | - | Mental Health Counselor | 06/09/2025 |
| ALIGNED MINDS THERAPY GROUPORG | MANAHAWKIN, NJ | - | Professional Counselor | 06/11/2026 |
| ALINSUNURIN, LIEZL | KANEOHE, HI | - | RBT | 09/22/2026 |
| ALIVE ABA THERAPY KS LLCORG | BROOKLYN, NY | - | BCBA | 09/23/2026 |
| ALIVE ABA THERAPY MO LLCORG | BROOKLYN, NY | - | BCBA | 09/23/2026 |
| ALIVE ABA THERAPY NM LLCORG | BROOKLYN, NY | - | BCBA | 09/23/2026 |
| ALJARDAT, PAIGE | SAINT PAUL, MN | MSW | Clinical Social Worker | 06/22/2021 |
| ALJELAIHAWI, ALIAA | MARYSVILLE, WA | BT | RBT | 09/21/2026 |
| ALKUS, HULYA | ALHAMBRA, CA | - | RBT | 09/22/2026 |
| ALLARAKHIA PCORG | TROY, MI | - | Clinic/Center | 09/14/2026 |
| ALLCARE MEDICAL & PSYCHIATRIC SERVICES PLLCORG | HOUSTON, TX | - | Clinic/Center | 09/25/2026 |
| ALLEGRETTI, SHANNON | NAPERVILLE, IL | PSY.D. | Psychologist | 03/13/2007 |
| ALLEGUE, JANETTE | MIAMI, FL | - | RBT | 03/29/2019 |
| ALLEMAN, MORGAN | YOUNGSVILLE, LA | - | Speech-Language Pathologist | 08/20/2020 |
| ALLEN-WALKER, CHRISTINA | COLUMBIA, MO | LPCC | Mental Health Counselor | 08/17/2015 |
| ALLEN, AALIYAH | CHATTANOOGA, TN | BEHAVIOR TECHNICIAN | RBT | 09/21/2026 |
| ALLEN, CHANDLER | AUSTIN, TX | LPC-A | Mental Health Counselor | 09/22/2026 |
| ALLEN, EMILY | GREENSBORO, NC | - | Clinical Social Worker | 09/23/2026 |
| ALLEN, HOLLY | GRANDVILLE, MI | LLMSW | Clinical Social Worker | 09/21/2026 |
| ALLEN, KARRIE | COLUMBIA, SC | LPC | Addiction (Substance Use Disorder) Counselor | 11/12/2017 |
| ALLEN, KODI | OVERLAND PARK, KS | LMLP | Professional Counselor | 09/09/2024 |
| ALLEN, MICHAEL | DES MOINES, IA | - | Mental Health Counselor | 09/23/2026 |
| ALLEN, PATRICK | SPOKANE, WA | LICSW-A | Clinical Social Worker | 09/23/2026 |
| ALLEN, REBECCA | PROVO, UT | - | Clinical Social Worker | 08/04/2022 |
| ALLEN, REGINARDO | WEST DUNDEE, IL | - | Counselor | 09/24/2026 |
| ALLEN, SAMUEL | FAIRFIELD, CA | MS | RBT | 10/09/2023 |
| ALLEN, SHARON | HILLSBORO, OR | LPC | Professional Counselor | 05/16/2014 |
| ALLEN, TALEHA | WINTER PARK, FL | - | Mental Health Counselor | 05/19/2021 |
| ALLEN, VICTORIA | CHESTER, VA | LPC | Professional Counselor | 10/24/2019 |
| ALLENCOMPASS LLCORG | HOUSTON, TX | - | Professional Counselor | 02/16/2024 |
| ALLEVA, KRISTIE | WASILLA, AK | MS, LPC | Mental Health Counselor | 10/15/2008 |
| ALLEY, CHRISTINA | MOUNT AIRY, NC | - | Clinical Social Worker | 09/23/2026 |
| ALLEY, KATHARINE | MANHATTAN BEACH, CA | LCSW | Clinical Social Worker | 11/05/2014 |
| ALLIANCE FOR WELLNESS, INC.ORG | VICTORVILLE, CA | - | Community/Behavioral Health Agency | 08/28/2026 |
| ALLINGTON COUNSELING, LLCORG | ALAMOSA, CO | - | Counselor | 09/26/2026 |
| ALLINGTON, CHRISTOPHER | ALAMOSA, CO | LPC, LAC | Counselor | 08/21/2013 |
| ALLISON LONG, PLLCORG | VANCOUVER, WA | - | Mental Health Counselor | 09/21/2026 |
| ALLMON, SIMONE | ALPHARETTA, GA | MA, MS, LPC | Professional Counselor | 05/04/2017 |
| ALMADA PEREZ, IGNACIO LORENZO | ANDERSON, SC | - | Mental Health Counselor | 08/06/2025 |
| ALMANZA, KATARINA | KATY, TX | MS, LPC | Professional Counselor | 09/22/2026 |
| ALMANZA, SASHARY | VERNON HILLS, IL | - | Counselor | 09/25/2026 |
| ALMANZAR, RAIZA | DANBURY, CT | - | Speech-Language Pathologist | 09/21/2026 |
| ALMEIDA, ASHLEY | PROVIDENCE, RI | LMHC | Mental Health Counselor | 06/07/2016 |
| ALMEIDA, CASSANDRA | PROVIDENCE, RI | LCSW | Clinical Social Worker | 09/23/2026 |
| ALMODOVAR, BEYONCE | MELBOURNE, FL | - | RBT | 09/26/2026 |
| ALMOND, JAMIE | RAMSEUR, NC | - | Mental Health Counselor | 09/24/2026 |
| ALMONTE, MARIA | MIDDLE VILLAGE, NY | LMHC | Mental Health Counselor | 08/31/2021 |
| ALNAMES, SALSABIL | DETROIT, MI | - | RBT | 09/25/2026 |
| ALOMARI, NAWAL | ORLAND PARK, IL | M.A. LPC | Professional Counselor | 08/17/2016 |
| ALONSO HERNANDEZ, ADRIANA | FARMINGTON HILLS, MI | - | RBT | 06/07/2024 |
| ALONSO SALCEDA, KEREN | HIALEAH, FL | - | BCBA | 06/28/2023 |
| ALONSO, ARRIANNA | BAKERSFIELD, CA | - | Day Training/Habilitation Specialist | 10/12/2022 |
| ALONSO, SONIA | MIAMI, FL | - | RBT | 09/23/2026 |
| ALPER, BRANDON | SACRAMENTO, CA | - | Day Training/Habilitation Specialist | 09/09/2024 |
| ALSALMANI, ALIAA | GARDEN CITY, MI | - | RBT | 09/25/2026 |
| ALSTON, JASMINE | PITTSBURGH, PA | - | RBT | 09/23/2026 |
| ALSTON, TAMIRA | PALM COAST, FL | LMHC | Mental Health Counselor | 09/29/2017 |
| ALSULTANI, ZANEP | GARDEN CITY, MI | - | RBT | 09/23/2026 |
| ALTAMIRA, MILDRED | ESPANOLA, NM | LCSW | Clinical Social Worker | 02/04/2020 |
| ALTIER, JAMIE | WHITE BEAR LAKE, MN | - | RBT | 09/21/2026 |
| ALTRUISTIC HOME CARE AGENCY LLCORG | SHELBY, NC | - | Case Management Agency | 04/08/2024 |
| ALTSCHULD, ANDREW | CONCORD, CA | - | BCBA | 06/26/2020 |
| ALUCCE, JONEL | CENTENNIAL, CO | - | RBT | 09/21/2026 |
| ALUNA WELLNESSORG | BURBANK, CA | - | Mental Health Counselor | 09/09/2026 |
| ALVARADO ESPINOZA, MARILYN | TORRANCE, CA | - | RBT | 09/21/2026 |
| ALVARADO, KARISSA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ALVARADO, LETICIA | POMONA, CA | - | Case Manager/Care Coordinator | 03/07/2007 |
| ALVARADO, ROSALIE | LA HABRA, CA | - | RBT | 09/21/2026 |
| ALVARADO, VICTORIA | TAMPA, FL | - | RBT | 09/21/2026 |
| ALVARADO, VIOLETA | CYPRESS, TX | - | Speech-Language Pathologist | 09/03/2026 |
| ALVARENGA QUIROZ, KAREN | SAN MARCOS, CA | - | RBT | 09/21/2026 |
| ALVAREZ BORGES, ARIEL | MIAMI, FL | - | RBT | 09/21/2026 |
| ALVAREZ CABEZOLA, NEIVYS | DORAL, FL | - | RBT | 04/15/2024 |
| ALVAREZ COLUMBIE, GEORGEA | MIAMI, FL | - | RBT | 09/27/2017 |
| ALVAREZ-GIBSON, FOLASADE | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| ALVAREZ-MESA, LUIS | PORT ST LUCIE, FL | - | RBT | 09/23/2026 |
| ALVAREZ, ALIYAH | MARTINEZ, CA | - | RBT | 12/18/2020 |
| ALVAREZ, ASHLEY | MINNEAPOLIS, MN | LICSW | Counselor | 07/19/2017 |
| ALVAREZ, CHARLIE | YAKIMA, WA | - | Case Manager/Care Coordinator | 09/22/2026 |
| ALVAREZ, ERICA | SAN BERNARDINO, CA | N/A | Assistant Behavior Analyst | 09/21/2026 |
| ALVAREZ, IBANOE | ORLAND PARK, IL | - | RBT | 09/23/2026 |
| ALVAREZ, KINMBERLY | MEDFORD, OR | - | Mental Health Counselor | 09/21/2026 |
| ALVAREZ, MARIA | PERRYSBURG, OH | - | Professional Counselor | 09/05/2024 |
| ALVAREZ, OLICIA | FRISCO, TX | MA | Professional Counselor | 09/23/2026 |
| ALVERSON, SAGE | CONCORD, CA | - | RBT | 09/25/2026 |
| ALVIAR, ELISABETH | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/25/2026 |
| ALWAN, IMAN | TORRANCE, CA | - | RBT | 09/21/2026 |
| ALYAMANI, DHUHA | HAMTRAMCK, MI | - | RBT | 09/24/2026 |
| AMACKER, REBECCA | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| AMANA, ANGELA | GREENSBORO, NC | SLP | Speech-Language Pathologist | 05/13/2011 |
| AMANDA PARISH, MENTAL HEALTH COUNSELING, PLLCORG | PORT JERVIS, NY | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| AMANTE, WENDOLIN | SANTA ANA, CA | - | Case Manager/Care Coordinator | 09/24/2026 |
| AMARAL, PAUL | NEW BEDFORD, MA | - | RBT | 09/22/2026 |
| AMATO, JOHN | VANCOUVER, WA | - | Counselor | 08/19/2021 |
| AMATO, RICHARD | LOXAHATCHEE, FL | - | Mental Health Counselor | 12/12/2023 |
| AMAYA SAAVEDRA, DENISSE | WALNUT CREEK, CA | - | Specialist | 09/25/2026 |
| AMAYA, ALEXIS | BLOOMINGTON, MN | LPCC | Professional Counselor | 03/10/2020 |
| AMBATI, KOMAL | FEDERAL WAY, WA | - | Mental Health Counselor | 09/24/2026 |
| AMBOOKEN, ISABEL | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| AMBROSE, EDEN | MANKATO, MN | MA, LPCC | Professional Counselor | 04/24/2023 |
| AMBROSIA PSYCHOLOGY INCORG | SANTA MONICA, CA | - | Mental Health Counselor | 11/04/2025 |
| AMBROSIA, ELISABETTA | SANTA MONICA, CA | PSY.D. | Psychologist | 04/16/2020 |
| AMBROSIO, BEATRIZ | WHITTIER, CA | - | RBT | 09/21/2026 |
| AMDUKA, ZEMZEM | VOORHEES, NJ | - | RBT | 09/25/2026 |
| AMELINE, CAROL | FT LEONARD WOOD, MO | LCSW | Clinical Social Worker | 04/18/2013 |
| AMERSON, MADISON | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| AMIRI, SABA | AMES, IA | - | RBT | 09/23/2026 |
| AMOS, ASHTON | JENKS, OK | ST | Speech-Language Pathologist | 07/23/2020 |
| AMS IMPACT GROUP, LLCORG | TEMPE, AZ | - | Speech-Language Pathologist | 09/25/2026 |
| ANCHEYTA-ABELAR, YOTZIL | ELKHART, IN | - | RBT | 09/22/2026 |
| ANCHONDO, TAWNY | EVERETT, WA | - | Counselor | 09/21/2026 |
| ANCHOR POINT THERAPY SERVICES LLCORG | ORLANDO, FL | - | BCBA | 09/24/2026 |
| ANCHORED IN ATTUNEMENTORG | BETHLEHEM, PA | - | Mental Health Counselor | 09/26/2026 |
| ANCHORED MIND COUNSELINGORG | INDIANA, PA | - | Professional Counselor | 02/23/2026 |
| ANDALON, KASSANDRA | SAN JOSE, CA | - | RBT | 09/21/2026 |
| ANDALUZ, VICTORIA | WEST MELBOURNE, FL | - | Mental Health Counselor | 09/25/2026 |
| ANDERLOHR, CATHLEEN | GRAND RAPIDS, MI | - | RBT | 09/25/2026 |
| ANDERS, CRYSTAL | LEXINGTON, KY | - | Case Manager/Care Coordinator | 09/24/2026 |
| ANDERSEN, FRANCES | PITTSFIELD, MA | - | Mental Health Counselor | 09/16/2026 |
| ANDERSON-KIRKLAND, DARLENE | DETROIT, MI | L.M.S.W. | Case Manager/Care Coordinator | 12/21/2012 |
| ANDERSON-PACE, LISA | TROY, MI | LMSW | Clinical Social Worker | 11/29/2017 |
| ANDERSON, ALEXANDRA | MARQUETTE, MI | - | Speech-Language Pathologist | 09/21/2026 |
| ANDERSON, AMY | WASHINGTON, DC | - | Clinical Social Worker | 03/01/2023 |
| ANDERSON, AUTUMN | ROSEMOUNT, MN | CCC-SLP | Speech-Language Pathologist | 08/24/2020 |
| ANDERSON, DEONTA | FARMINGTON HILLS, MI | - | RBT | 10/29/2025 |
| ANDERSON, EMILY | CINCINNATI, OH | - | Mental Health Counselor | 07/06/2023 |
| ANDERSON, EMILY | SALT LAKE CITY, UT | - | RBT | 09/24/2026 |
| ANDERSON, ERIN | VAN NUYS, CA | - | Mental Health Counselor | 09/22/2026 |
| ANDERSON, GLINDA | CORAL GABLES, FL | - | RBT | 09/21/2026 |
| ANDERSON, ISABELLA | BRIGHTON, MI | - | RBT | 07/30/2025 |
| ANDERSON, JESSICA | ANN ARBOR, MI | - | Speech-Language Pathologist | 09/24/2026 |
| ANDERSON, KELLI | VIRGINIA BEACH, VA | - | RBT | 09/24/2026 |
| ANDERSON, MARYANNE | LATHAM, NY | - | Speech-Language Pathologist | 09/23/2026 |
| ANDERSON, MICAH | TULSA, OK | - | Speech-Language Pathologist | 06/21/2023 |
| ANDERSON, MICHELLE | CHARLESTON, WV | BSN, RN, MC | Counselor | 10/23/2025 |
| ANDERSON, MICHELLE | CENTENNIAL, CO | LPC | Professional Counselor | 10/09/2019 |
| ANDERSON, MIRANDA | DALLAS, GA | LPC | Mental Health Counselor | 05/08/2026 |
| ANDERSON, SHAWN | SANTA MONICA, CA | LCSW | Clinical Social Worker | 08/22/2026 |
| ANDERSON, SHEILA | PHILADELPHIA, PA | - | BCBA | 12/28/2015 |
| ANDERSON, TANIA | CANTON, OH | - | Case Manager/Care Coordinator | 05/29/2026 |
| ANDERSON, TRAVIS | MILTON, WA | AAC | Mental Health Counselor | 09/22/2026 |
| ANDERSON, TYLER | SALT POINT, NY | - | Mental Health Counselor | 10/05/2023 |
| ANDINO, CAROLIN | MIAMI GARDENS, FL | - | RBT | 09/22/2026 |
| ANDRADE, EDIR | WORCESTER, MA | - | RBT | 09/22/2026 |
| ANDRADE, EMILY | ORANGE, CA | - | RBT | 09/22/2026 |
| ANDRADE, RACHEL | NORTH LAS VEGAS, NV | - | RBT | 03/26/2019 |
| ANDRE, JESSICA | BEAVERTON, OR | LCSW | Clinical Social Worker | 12/07/2022 |
| ANDREA LIVERMAN, LLCORG | SAVANNAH, GA | - | Professional Counselor | 06/18/2014 |
| ANDREA MCGUIRE LLCORG | EAST LANSING, MI | - | Clinical Social Worker | 05/12/2025 |
| ANDREWS-WALKER, NOELL | ATLANTA, GA | LCSW | Clinical Social Worker | 08/29/2022 |
| ANDREWS, ABIGAIL | GUILDERLAND, NY | LMHC | Mental Health Counselor | 01/17/2025 |
| ANDREWS, JENNIFER | BEND, OR | MS, CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| ANDREWS, MAXWELL | MADISON, WI | - | Clinical Social Worker | 09/21/2026 |
| ANDREWS, PATANISHA | SPOKANE, WA | MS, MHP, CDPT | Addiction (Substance Use Disorder) Counselor | 08/24/2016 |
| ANDREWS, RETHA | ARDMORE, OK | - | RBT | 10/21/2020 |
| ANDREWS, SIMONE | NEW YORK, NY | PSY.D | Psychologist | 10/04/2016 |
| ANDREWS, SIYANNISAPHIRA | DURHAM, NC | - | RBT | 06/19/2026 |
| ANDRUS-BRYANT, TAYIA | AKRON, OH | - | Case Manager/Care Coordinator | 11/28/2022 |
| ANESTHESIA ASSOCIATES, PLLCORG | MAPLE GROVE, MN | - | Specialist | 09/16/2012 |
| ANEW COUNSELING SOLUTIONSORG | MONROVIA, IN | - | Clinical Social Worker | 04/01/2026 |
| ANGEL, TANIA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| ANGELA K CLAUSIUSORG | DERBY, KS | - | Clinical Social Worker | 06/08/2026 |
| ANGER, EMILY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| ANGLUM, JOHN | MELVILLE, NY | - | RBT | 09/21/2026 |
| ANGU TUMASANG, EDMOND CHE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 04/26/2024 |
| ANKERKRONE CALDAS, HENRIQUE | BOSTON, MA | - | Counselor | 01/26/2026 |
| ANN'S SUNSHINE FAMILY SERVICESORG | WEATHERFORD, TX | - | Case Management Agency | 09/02/2026 |
| ANNAGRACE CENTER FOR BEHAVIORAL HEALTH LLCORG | BOWIE, MD | - | Mental Health Counselor | 09/21/2026 |
| ANNAS, SYDNEY | DENVER, CO | - | Professional Counselor | 09/23/2026 |
| ANNERINO, KRISTINA | CHICAGO, IL | - | Addiction (Substance Use Disorder) Counselor | 07/28/2014 |
| ANNUNZIATO, JESSICA | PLANO, TX | BCBA | BCBA | 02/01/2019 |
| ANSHUR, ABDULQADIR | FRIDLEY, MN | - | RBT | 09/21/2026 |
| ANSTETT-KASPARI, CHARITY | SUPERIOR, WI | LCSW, LICSW | Clinical Social Worker | 05/14/2024 |
| ANT BEHAVIOR SOLUTIONS LLCORG | LAFAYETTE, CA | - | BCBA | 02/21/2024 |
| ANTCZAK, JONATHAN | MENIFEE, CA | CADC III | Case Manager/Care Coordinator | 08/19/2024 |
| ANTESODA, KRISTINE | BAKERSFIELD, CA | - | Clinical Social Worker | 02/24/2025 |
| ANTHONY, KATHERINE | BILLINGS, MT | BCBA | BCBA | 07/26/2023 |
| ANTON, BRIDGET | RIDGEWOOD, NJ | PHD | Psychologist | 01/07/2021 |
| ANTONE, ALBANA | WINCHESTER, ID | LPC | Professional Counselor | 12/04/2024 |
| ANTONELLI, JENNIFER | LAKE ORION, MI | MACCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| ANTTILA, SAMANTHA | BROOKLYN CENTER, MN | - | RBT | 09/23/2026 |
| ANTWI, LEAH | PHILADELPHIA, PA | - | BCBA | 09/21/2026 |
| ANUNKOR, OGECHI | BROOKLYN, NY | - | Specialist | 09/23/2026 |
| ANWELL, ARAMI | DENVER, CO | LPCC | Mental Health Counselor | 09/22/2026 |
| ANYANWU, DANIELS | KATY, TX | - | RBT | 09/21/2026 |
| ANZOLA, JASMYN | BLOOMINGTON, IN | - | Speech-Language Pathologist | 09/21/2026 |
| APALACHEE CENTER, INC.ORG | QUINCY, FL | - | Community/Behavioral Health Agency | 09/15/2006 |
| APHEALTH PBCORG | LONG BEACH, CA | - | Case Management Agency | 09/24/2026 |
| APONTE, DESIREE | FRISCO, TX | - | Professional Counselor | 07/16/2024 |
| APOTSOS, ANASTASIA | FUQUAY VARINA, NC | - | Speech-Language Pathologist | 04/19/2022 |
| APPELQUIST, TISHA | BURNSVILLE, MN | - | RBT | 09/21/2026 |
| APPLETON, GRACE | IRVINE, CA | - | RBT | 09/21/2026 |
| APUZZIE, ASHELY | FALL RIVER, MA | - | RBT | 09/22/2026 |
| AQA, KAMILAH | MODESTO, CA | ASW | Professional Counselor | 01/27/2017 |
| AQUINO GONZALEZ, LILIAN | PORTLAND, OR | - | Mental Health Counselor | 09/21/2026 |
| AQUINO, KARINA | ASTORIA, NY | LMHC | Mental Health Counselor | 12/06/2023 |
| ARAGON, TIMOTHY | DRAPER, UT | - | Clinical Social Worker | 01/28/2019 |
| ARAIZA RENDON, JORGE | CAMARILLO, CA | - | Day Training/Habilitation Specialist | 12/18/2023 |
| ARANDA, CARMEN | PHILADELPHIA, PA | LPC | Professional Counselor | 09/02/2026 |
| ARBERTHA, MARVIN | OKLAHOMA CITY, OK | BHRS | Mental Health Counselor | 04/19/2012 |
| ARBIT COUNSELINGORG | WASHINGTON, DC | - | Mental Health Counselor | 09/22/2026 |
| ARBUCKLE, DAVID | PARKERSBURG, WV | - | BCBA | 07/20/2023 |
| ARC BROWARD, INC.ORG | SUNRISE, FL | - | Speech-Language Pathologist | 02/21/2008 |
| ARC REGEN LLCORG | LAS VEGAS, NV | - | Community/Behavioral Health Agency | 07/09/2025 |
| ARCE, GIOVANA | MONROVIA, CA | - | RBT | 06/08/2022 |
| ARCH PSYCHOLOGICAL, PCORG | MOUNT KISCO, NY | - | Psychologist | 11/29/2011 |
| ARCHER, AARON | KALISPELL, MT | LAC, PCLC | Addiction (Substance Use Disorder) Counselor | 12/01/2025 |
| ARCHER, DANIEL | LEESBURG, FL | - | Mental Health Counselor | 09/24/2026 |
| ARCHULETA, NATASHA | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| ARCHWAY COUNSELING SERVICES LLCORG | WESTMINSTER, MD | - | Mental Health Counselor | 01/20/2023 |
| ARCILA, LESLEY | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| ARCONTI, PAIGE | FAIRLAWN, OH | - | Speech-Language Pathologist | 09/21/2026 |
| ARECHIGA, ALEXIA | GARDENA, CA | - | RBT | 09/24/2026 |
| AREL, HEATHER | GREENFIELD, NH | - | BCBA | 07/30/2026 |
| ARELLANO, BRENDA | EL CENTRO, CA | - | Day Training/Habilitation Specialist | 07/16/2015 |
| ARELLANO, JANESSA | COVINA, CA | - | RBT | 09/23/2026 |
| ARELLANO, KAILYE | SANTA FE, NM | - | RBT | 09/24/2026 |
| ARENAS, CLAUDIA | ROSEVILLE, CA | - | RBT | 04/15/2026 |
| ARENAS, MONICA | KATY, TX | - | Mental Health Counselor | 09/25/2026 |
| AREND COUNSELING LLCORG | PITTSBURGH, PA | - | Mental Health Counselor | 06/15/2026 |
| AREVALO, MELISSA | VIENNA, VA | - | RBT | 09/22/2026 |
| AREVALO, ZULMA | ALHAMBRA, CA | - | RBT | 01/29/2026 |
| ARIAS GARCIA, JESSE | NORTH HILLS, CA | - | RBT | 09/25/2026 |
| ARIAS LOPEZ, YADIRA | MIAMI, FL | - | BCBA | 05/07/2024 |
| ARIAS, MELISSA | MIAMI, FL | RBT | RBT | 09/28/2023 |
| ARIAS, RACHEL | WILMINGTON, MA | - | RBT | 09/22/2026 |
| ARIAS, YADIRA | REDONDO BEACH, CA | M.S | BCBA | 06/08/2022 |
| ARISE COUNSELING PLLCORG | GRAND RAPIDS, MI | - | Mental Health Counselor | 09/24/2026 |
| ARISE RECOVERY, LLCORG | HOUSTON, TX | - | Case Management Agency | 02/26/2026 |
| ARISTIZABAL, NICOLE | HOLLY RIDGE, NC | - | Speech-Language Pathologist | 08/27/2026 |
| ARISTOR, CARMY | BROOKLYN, NY | - | Mental Health Counselor | 06/22/2016 |
| ARMADA, CAMILLE | ORLANDO, FL | - | Speech-Language Pathologist | 09/23/2026 |
| ARMAS MENDEZ, YEUDIET | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| ARMAS, ARTURO | FARMINGTON HILLS, MI | - | RBT | 03/29/2021 |
| ARMENTA, KATLYNE | LOS ANGELES, CA | - | Counselor | 06/20/2024 |
| ARMENTA, SAMARAH | RIO RANCHO, NM | - | RBT | 09/22/2026 |
| ARMIJO ELISOFF, BISHOP | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| ARMSTRONG, JAYLYN | WORCESTER, MA | - | RBT | 09/23/2026 |
| ARMSTRONG, MELODY | LAKEVIEW, OR | - | Addiction (Substance Use Disorder) Counselor | 11/23/2021 |
| ARNOLD, KRYSTINA | SPRING, TX | - | RBT | 09/23/2026 |
| ARNOLD, MAHALIA | ORLAND PARK, IL | - | RBT | 09/25/2026 |
| ARNONE, TIMOTHY | MONROE, CT | LPC | Mental Health Counselor | 09/23/2026 |
| ARNZEN, ROSS | FALL RIVER, MA | - | Clinical Social Worker | 09/23/2026 |
| AROCHA SOSA, ANA MARGARITA | HIALEAH, FL | - | RBT | 09/25/2026 |
| ARPIN, KATHRYN | LYNNWOOD, WA | SUDPT | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| ARRA, STEPHANIE | MASSAPEQUA, NY | LMHC, M.S. ED., NCC | Mental Health Counselor | 08/28/2020 |
| ARRINGTON, ALICIA | DECATUR, GA | - | RBT | 09/25/2026 |
| ARROYO, DIANA | DEERFIELD BCH, FL | - | RBT | 09/23/2026 |
| ARSHAD, ZESHAN | DEARBORN, MI | - | RBT | 09/22/2026 |
| ARTHUR, TANESHA | VALLEY STREAM, NY | - | Specialist | 06/08/2012 |
| ARTURI, JILL | KENOSHA, WI | - | Speech-Language Pathologist | 09/21/2026 |
| ARUCAN, ARICA | STOCKTON, CA | MSW | Clinical Social Worker | 06/14/2010 |
| ARVANITIS, AVA | WESTCHESTER, IL | C-SLPA | Speech-Language Pathologist | 09/22/2026 |
| AS YOU ARE COUNSELING PLLCORG | FORT WORTH, TX | - | Professional Counselor | 09/21/2026 |
| ASAD, YASMEEN | EL CAJON, CA | - | Mental Health Counselor | 09/21/2026 |
| ASANTEWAA, BERNICE | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ASATO-SUAREZ, DARIO | PORTLAND, OR | - | Case Manager/Care Coordinator | 09/23/2026 |
| ASCENCIO, MELISSA | WALNUT CREEK, CA | - | RBT | 05/15/2025 |
| ASCEND COUNSELING AND THERAPY SERVICES, LLCORG | JOHNS CREEK, GA | - | Professional Counselor | 09/24/2026 |
| ASCENDANCY MENTAL AND BEHAVIORAL HEALTH SERVICES, LLC.ORG | SCOTTSBLUFF, NE | - | Mental Health Counselor | 06/04/2024 |
| ASCH, JACOB | JACKSONVILLE, FL | BCABA | Assistant Behavior Analyst | 08/16/2017 |
| ASHBY, QUINTIN | VICTORVILLE, CA | - | RBT | 09/22/2026 |
| ASHCRAFT, VICTORIA | TUSCALOOSA, AL | ALC | Mental Health Counselor | 09/24/2026 |
| ASHLEY EIKENBERRY, PLLCORG | GRAND JUNCTION, CO | - | Professional Counselor | 09/26/2026 |
| ASHLEY, COLIN | BENTON HARBOR, MI | - | RBT | 09/21/2026 |
| ASKREN-GONZALEZ, ESTRELLA | CHICAGO, IL | LPC, NCC | Professional Counselor | 07/05/2022 |
| ASLAM, QUDSIA | WESTERVILLE, OH | - | RBT | 09/17/2026 |
| ASMUSSEN, MICHELLE | MECHANICSVILLE, MD | HRS,RPS,CCJP,CS,RCPF | Community/Behavioral Health Agency | 09/25/2026 |
| ASP, LEAH | ROSEMOUNT, MN | MA, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| ASPIRUS MEDICAL GROUP, INC.ORG | WAUSAU, WI | - | Clinic/Center | 11/02/2006 |
| ASTER VALE BEHAVIORAL HEALTH & CONSULTING, PLLCORG | RICHMOND, VA | - | Clinical Social Worker | 09/24/2026 |
| ASTRICK THERAPY SOLUTIONSORG | MARIETTA, GA | - | Professional Counselor | 08/14/2026 |
| AT EASE WELLNESS COLLECTIVE LLCORG | DOVER, DE | - | Mental Health Counselor | 09/25/2026 |
| AT HOME CARE COMMUNITY OUTREACHORG | PORT GIBSON, MS | - | Community/Behavioral Health Agency | 01/09/2018 |
| AT YOUR DOOR PHYSICIAN CAREORG | CHICAGO, IL | - | Clinic/Center | 04/08/2021 |
| ATIK, REEM | LONG BEACH, CA | - | Clinical Social Worker | 12/16/2018 |
| ATIVIE, BLESSING | COLORADO SPRINGS, CO | LCSW | Clinical Social Worker | 06/13/2013 |
| ATKINS, CYNTHIA | POUGHKEEPSIE, NY | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| ATKINS, GAIL | ALPENA, MI | LPC | Professional Counselor | 10/21/2016 |
| ATKINSON, JOVONNA | LEXINGTON, KY | - | Clinical Social Worker | 09/21/2026 |
| ATLAS BEHAVIORAL HEALTH PLLCORG | CHICAGO, IL | - | Psychologist | 03/23/2020 |
| ATOLAGBE, TAWAKALITU | BOWIE, MD | - | Mental Health Counselor | 09/21/2026 |
| ATTIA, MIA | SUGAR LAND, TX | - | RBT | 05/12/2025 |
| ATWOOD, ANNETTE | PINELLAS PARK, FL | - | Clinical Social Worker | 09/21/2026 |
| ATWOOD, JANIE | SALEM, OR | - | Mental Health Counselor | 09/24/2026 |
| AUBREE DOSPOY PSYCHOTHERAPYORG | KALAMAZOO, MI | - | Clinical Social Worker | 09/25/2026 |
| AUDELO, DANIEL | VICTORVILLE, CA | - | RBT | 09/24/2026 |
| AUDREY LIPSKEY COUNSELINGORG | REDMOND, OR | - | Clinical Social Worker | 06/07/2021 |
| AUGUSTINE, AMANDA | SHELBYVILLE, KY | - | RBT | 09/21/2026 |
| AUMACK, KATEARIE | LARAMIE, WY | PPC | Counselor | 09/25/2026 |
| AURA MENTAL WELLNESSORG | SUN CITY CENTER, FL | - | Mental Health Counselor | 08/13/2026 |
| AURELL, ANGELA | SEATTLE, WA | SUDP | Addiction (Substance Use Disorder) Counselor | 09/20/2019 |
| AUREUM HEALTH HEALTH, LLCORG | NORTH HAVEN, CT | - | Community/Behavioral Health Agency | 09/24/2026 |
| AUREVIA CENTER LLCORG | MIAMI, FL | - | BCBA | 09/22/2026 |
| AURORA COUNSELING, LLCORG | FAIRBANKS, AK | - | Mental Health Counselor | 03/31/2022 |
| AUSTIN, ANDREW | NEW YORK, NY | LMHC | Mental Health Counselor | 09/25/2023 |
| AUSTIN, SHANNON | EAST LANSING, MI | - | Speech-Language Pathologist | 09/25/2026 |
| AUSTIN, STEFANIE | FRISCO, TX | MBA, CMPE, CSPPM | Case Manager/Care Coordinator | 09/23/2026 |
| AUTISM BEHAVIORAL INSTITUTE, LLC DBA ALREADY AUTISM HEALTHORG | SAVANNAH, GA | - | BCBA | 08/27/2019 |
| AUTMAN, TOREE | KANKAKEE, IL | - | RBT | 09/22/2026 |
| AUZ, ALEXANDRA | HUNTINGTON STATION, NY | MA, CCC-SLP | Speech-Language Pathologist | 05/15/2019 |
| AVALOS GONZALEZ, LIZBETH | LAS VEGAS, NV | - | BCBA | 07/05/2022 |
| AVALOS VEGA, DANIEL | SAN FRANCISCO, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| AVALOS, ARGELIA | MENIFEE, CA | - | RBT | 09/21/2026 |
| AVALOS, BRENDA | GARDEN GROVE, CA | - | RBT | 09/25/2026 |
| AVELAR RAMIREZ, OSCAR | AGOURA HILLS, CA | - | RBT | 09/22/2026 |
| AVELLO, ANA | MIAMI, FL | - | RBT | 11/10/2020 |
| AVENTRA MEDICAL LLCORG | HOUSTON, TX | - | Clinic/Center | 07/09/2026 |
| AVERETT, EDEN | ST GEORGE, UT | - | RBT | 09/23/2026 |
| AVERY, ZACHARY | SAN DIEGO, CA | LCSW, BC-TMH, TIYT | Clinical Social Worker | 11/04/2022 |
| AVILA, ESMERALDA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| AVILA, YANET | DORAL, FL | - | RBT | 10/07/2020 |
| AVILES AVINA, NYREL | SOMERSET, KY | - | Speech-Language Pathologist | 09/24/2026 |
| AVILES, JODIE | SOMERSWORTH, NH | - | RBT | 09/22/2026 |
| AVILEZ, ESTRELLA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| AWEH, PROMISE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 10/06/2025 |
| AYALA, BEATRIZ R | GREENACRES, FL | - | Clinical Social Worker | 06/05/2015 |
| AYALA, CELESTE | LOS ANGELES, CA | - | RBT | 09/21/2026 |
| AYALA, JANNETTE | DALLAS, TX | - | RBT | 09/22/2026 |
| AYALA, JAQUELINE | LOS ANGELES, CA | - | RBT | 09/24/2026 |
| AYALA, JESUS | CONCORD, CA | - | RBT | 01/05/2021 |
| AYALA, KAITLYN | SCHAUMBURG, IL | LCPC, NCSP | Professional Counselor | 10/11/2018 |
| AYALA, LARISSA | FAIRFIELD, CA | - | Day Training/Habilitation Specialist | 12/26/2025 |
| AYALA, SUMMER | RIVERBANK, CA | - | RBT | 09/21/2026 |
| AYERS, CAMRYN | COLUMBUS, GA | - | RBT | 09/24/2026 |
| AYESH, YOUSEF | IRVINE, CA | - | RBT | 09/21/2026 |
| AYILOGE, KEMISOLA | MARTINEZ, CA | LCSW-C | Clinical Social Worker | 10/22/2020 |
| AYON, MANUEL | WOODLAND, CA | - | Clinical Social Worker | 03/25/2013 |
| AZALEA BEHAVIORAL CONSULTING SERVICES, LLCORG | MERIDIANVILLE, AL | - | BCBA | 09/25/2026 |
| AZAMI, NOOSHIN | CHULA VISTA, CA | - | BCBA | 07/27/2021 |
| AZIZ, AWEEN | VAN NUYS, CA | - | Day Training/Habilitation Specialist | 08/03/2026 |
| AZULAY, ADAM | POMONA, CA | - | Mental Health Counselor | 09/22/2026 |
| AZZI, CHRISTIE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| B & H CSSP OPERATIONS HARRISON B LLCORG | HARRISON, AR | - | Community/Behavioral Health Agency | 09/24/2026 |
| B&R THERAPY LLCORG | PRESCOTT, AZ | - | Clinical Social Worker | 09/25/2026 |
| BAADE, SAVANNAH | JUDA, WI | - | Speech-Language Pathologist | 06/23/2021 |
| BABAJKO, ALEXIS | CARLSBAD, CA | BCBA | BCBA | 04/03/2019 |
| BABCOCK, KYLE | MIDLAND, MI | - | Mental Health Counselor | 05/08/2023 |
| BABERS, TIANA | SPOKANE, WA | - | Clinical Social Worker | 10/31/2023 |
| BABU, MEGHNA | JOHNSTOWN, PA | - | Psychologist | 08/07/2023 |
| BABU, NIDHIYA | SACRAMENTO, CA | - | Speech-Language Pathologist | 09/23/2026 |
| BACA, MIRANDA | ALBUQUERQUE, NM | - | Case Manager/Care Coordinator | 05/18/2026 |
| BACHMAN, ALEX | WESTFIELD, NJ | LCSW, LCADC | Clinical Social Worker | 09/24/2026 |
| BACHTIGER, TRESTIN | CHICAGO, IL | - | RBT | 09/22/2026 |
| BACKSTROM, KIARALYN | YAKIMA, WA | - | Counselor | 09/21/2026 |
| BACON, BETHANY | CHICAGO, IL | LCSW | Clinical Social Worker | 02/06/2020 |
| BACON, TIERRA | CHARLOTTE, NC | SWT BA | Clinical Social Worker | 08/22/2019 |
| BADDELEY, GARY | BEACHWOOD, OH | - | Addiction (Substance Use Disorder) Counselor | 03/22/2022 |
| BADDR, AHMAD MURTAZA | WOODBRIDGE, VA | RBT | RBT | 08/07/2025 |
| BADEL, JENNA | CLARKSTON, MI | - | Clinical Social Worker | 09/24/2026 |
| BADGLEY, MACKENZIE | BUFFALO, NY | SLP | Speech-Language Pathologist | 05/28/2025 |
| BADOLATO, ROSALIA | BETHLEHEM, PA | MS, LAPC | Mental Health Counselor | 09/21/2026 |
| BAE, YEONG | FORT WASHINGTON, PA | LCSW, M.DIV | Clinical Social Worker | 10/01/2024 |
| BAER, BRADYLEE | KNOXVILLE, TN | - | RBT | 09/25/2026 |
| BAEZ, MARILIN | ORLANDO, FL | - | RBT | 02/17/2015 |
| BAGG, ASHLEE | DUNMORE, PA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| BAGGESE, STEVEN | ELK GROVE, CA | BCBA | BCBA | 02/23/2015 |
| BAGLEY, JULIE | SHELTON, WA | LMHCA | Mental Health Counselor | 09/21/2026 |
| BAHNICK, JACOB | EVERETT, WA | - | Counselor | 01/07/2026 |
| BAHNUB, RILEIGH | FARRAGUT, TN | LPC | Professional Counselor | 05/05/2022 |
| BAHSAINE, IHSSANE | ADAMS, MA | - | RBT | 09/22/2026 |
| BAILEY, CHARITY | PRINCETON, WV | MS, LPC | Mental Health Counselor | 09/23/2026 |
| BAILEY, CHAZZ | MCHENRY, IL | - | Professional Counselor | 02/25/2025 |
| BAILEY, JENNIFER | ROSEMOUNT, MN | MACCCSLP | Speech-Language Pathologist | 02/06/2007 |
| BAILEY, KRISTEN | GERMANTOWN, MD | MS | Mental Health Counselor | 06/08/2020 |
| BAILEY, MARY ANNE | MURFREESBORO, TN | MS | Mental Health Counselor | 05/07/2010 |
| BAILEY, RANDI | ANDALUSIA, AL | LICSW | Clinical Social Worker | 09/24/2026 |
| BAILEY, ROBYN | CUMMING, GA | - | Mental Health Counselor | 09/26/2026 |
| BAILEY, SAMEAH | RICHMOND, TX | - | RBT | 09/24/2026 |
| BAILIFF, EMILY | ROCK SPRINGS, WY | - | Clinical Social Worker | 09/10/2015 |
| BAINBRIDGE THERAPYORG | SUQUAMISH, WA | - | Counselor | 09/21/2026 |
| BAINES, CHRISTINA | COPPERAS COVE, TX | LMHC, LPC | Professional Counselor | 03/22/2024 |
| BAIRD, JESSICA | WILMINGTON, NC | - | Clinical Social Worker | 05/18/2021 |
| BAIRD, RACHEL | WEST JORDAN, UT | - | RBT | 09/25/2026 |
| BAKARDIEVA RAMOS DA SILVA, BIANCA | MINNETRISTA, MN | MA, LPCC, LADC | Professional Counselor | 09/21/2026 |
| BAKER, EMMA | QUEEN CREEK, AZ | - | RBT | 09/25/2026 |
| BAKER, HANNAH | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BAKER, JESSIE | JACKSONVILLE, FL | LCSW | Clinical Social Worker | 09/25/2026 |
| BAKER, PATRICK | CHELSEA, MA | - | Mental Health Counselor | 09/21/2026 |
| BAKER, PATTY | LITTLESTOWN, PA | CDMS CCM QRP | Case Manager/Care Coordinator | 01/18/2010 |
| BAKER, ROBERT | VIRGINIA, MN | - | Clinical Social Worker | 10/19/2022 |
| BAKER, SHERI | NORFOLK, VA | LPC | Mental Health Counselor | 01/02/2020 |
| BAKER, SYNNE | LOS ANGELES, CA | - | Psychologist | 06/14/2018 |
| BAKER, TREVOR | DENVER, CO | - | RBT | 09/21/2026 |
| BALANCIO, ELIJAH | CLEVELAND, OH | - | RBT | 03/04/2024 |
| BALAREZO, DANIELA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| BALASUBRAMANIAM, MATHURAM (MADHU) | WHEATON, IL | LCPC | Mental Health Counselor | 09/24/2026 |
| BALDERAS ACEVES, ASHLEY | CENTENNIAL, CO | - | RBT | 09/01/2026 |
| BALDERAS-JOHNSON, PATRICIA | SAINT PETER, MN | - | Clinical Social Worker | 09/21/2026 |
| BALDOVINES, ALEXA | CERRITOS, CA | - | RBT | 09/21/2026 |
| BALDRIDGE, SAVANNAH | WASHINGTON, UT | - | RBT | 09/25/2026 |
| BALDWIN, KAYLA | COLUMBIA, MD | - | Mental Health Counselor | 09/22/2026 |
| BALESTINO, ANNA | RANDOLPH, MA | - | RBT | 09/21/2026 |
| BALIDOY, CIARA | CONCORD, CA | - | RBT | 09/24/2026 |
| BALINT, HEATHER | SOUTHFIELD, MI | - | RBT | 09/24/2026 |
| BALL, LINDSEY | WICHITA, KS | - | Professional Counselor | 01/11/2024 |
| BALLARD, CAITLYN | GARLAND, TX | LPC-A, ASOTP | Counselor | 09/24/2026 |
| BALLARD, ELEANA | SAINT CLOUD, MN | LADC | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BALLARD, LYDIA | ROSWELL, NM | - | RBT | 12/25/2025 |
| BALROOP, NIRVANA | PLANTATION, FL | M.S, SLP | Speech-Language Pathologist | 02/02/2009 |
| BALUCH, SARAH | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BAMFIELD, TAYLOR | TUCSON, AZ | - | Mental Health Counselor | 12/12/2022 |
| BANA, ABDINASIR | MINNETONKA, MN | - | RBT | 11/14/2023 |
| BANAGHAN, HALIE | NEW SMYRNA, FL | MA | Mental Health Counselor | 12/09/2025 |
| BANDA BERRY HEALTH SERVICES, PROFESSIONAL CORPORATIONORG | PASADENA, CA | - | Mental Health Counselor | 09/22/2026 |
| BANG, ALINA | MISSION VIEJO, CA | M.S., CCC-SLP | Speech-Language Pathologist | 09/24/2026 |
| BANIPALSIN, ADONIS | NORTHRIDGE, CA | - | RBT | 09/23/2026 |
| BANKS, MICAH | SOUTHFIELD, MI | - | RBT | 09/25/2026 |
| BANKS, PAULISHA | GARDENA, CA | - | BCBA | 09/20/2020 |
| BANKSTON, ALLISON | DELAND, FL | MS, LMHC | Mental Health Counselor | 08/27/2019 |
| BANNISH, JOSEPH | ABERDEEN, WA | - | Addiction (Substance Use Disorder) Counselor | 08/28/2021 |
| BANNUR, NIDHI | MADISON, WI | - | RBT | 09/23/2026 |
| BANUELOS, RICARDO | DUARTE, CA | - | Clinical Social Worker | 07/27/2021 |
| BANYAN TREE THERAPY LLCORG | BRIGHTON, MA | - | Clinical Social Worker | 09/29/2025 |
| BAPTIST HEALTH MEDICAL GROUPORG | LOUISVILLE, KY | - | Speech-Language Pathologist | 01/16/2026 |
| BAQUERO, PIERRE | MURRIETA, CA | - | RBT | 03/22/2025 |
| BARAHONA, ANA | GLENDALE, CA | - | RBT | 09/25/2026 |
| BARAJAS, ARACELI | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 02/03/2021 |
| BARBEAU PROFESSIONAL SERVICES PLLCORG | WHEELING, WV | - | Clinical Social Worker | 09/25/2026 |
| BARBER, KATELYNN | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| BARBER, VICTORIA | TAYLOR MILL, KY | RBT | RBT | 09/24/2026 |
| BARBERENA, JESSENIA | TORRANCE, CA | - | RBT | 09/22/2026 |
| BARBERY, KIANA | ATLANTA, GA | - | BCBA | 09/23/2026 |
| BARCLAY, REBECCA | CARLISLE, PA | LPC | Mental Health Counselor | 06/18/2017 |
| BARDONNER, RICHARD | CERES, CA | SUDRC | Addiction (Substance Use Disorder) Counselor | 05/02/2025 |
| BARDOORIAN, ELLA | WASHINGTON COURT HOUSE, OH | - | Clinical Social Worker | 09/21/2026 |
| BARDWELL, RONNESHIA | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| BARE, THOMAS | PLYMOUTH, MN | - | RBT | 09/24/2026 |
| BARGER, KENSINGTON | KNOXVILLE, TN | - | RBT | 09/23/2026 |
| BARILLAS, KATIE | ALPHARETTA, GA | LPC, NCC, MS | Mental Health Counselor | 03/20/2024 |
| BARKATAKI DO PCORG | VALENCIA, CA | - | Clinic/Center | 06/17/2022 |
| BARKSDALE, KENDRA | MACEDONIA, OH | - | Case Manager/Care Coordinator | 06/09/2023 |
| BARLINDAL, STEVEN | SAN FRANCISCO, CA | C.A.T.C. | Addiction (Substance Use Disorder) Counselor | 08/23/2013 |
| BARLOW, MEGAN | ATTLEBORO, MA | - | Clinical Social Worker | 09/25/2026 |
| BARLOW, SARAH | COLUMBIA, SC | RBT | RBT | 09/21/2026 |
| BARLOW, TONYA | JACKSON, OH | - | Case Manager/Care Coordinator | 09/18/2026 |
| BARNARD, RHONDA | WINDCREST, TX | LPC | Mental Health Counselor | 02/23/2023 |
| BARNES, ASHLEY | EASTHAMPTON, MA | MA | Counselor | 10/06/2023 |
| BARNES, DELISSIA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BARNES, KIMBERLEE | VAN BUREN, MO | PSY.D., L.P.C. | Psychologist | 07/18/2007 |
| BARNES, SIERRA | GREENWOOD VILLAGE, CO | MA, LPC | Professional Counselor | 01/28/2020 |
| BARNES, SOPHIE | DOVER, DE | LCSW | Clinical Social Worker | 09/21/2026 |
| BARNETT, KEITH | RED BLUFF, CA | LCSW | Clinical Social Worker | 06/24/2008 |
| BARNHART, LAUREN | KENOSHA, WI | LPC | Professional Counselor | 11/10/2015 |
| BARONE, JAMES | STAMFORD, CT | - | Counselor | 09/23/2026 |
| BAROSKO, GLORIA | MESA, AZ | MA, BCBA, LBA | BCBA | 09/21/2026 |
| BARREIRO, NYDIA | ORANGE PARK, FL | LPC | Professional Counselor | 02/07/2023 |
| BARRERA, LAURA | CORPUS CHRISTI, TX | LPC | Mental Health Counselor | 06/17/2024 |
| BARRERA, STEPHANIE | SEVIERVILLE, TN | M.S., CCC-SLP | Speech-Language Pathologist | 03/05/2019 |
| BARRETO, ALEJANDRO | SAN JUAN, PR | - | Clinical Social Worker | 09/23/2026 |
| BARRETT, JENICA | SEATTLE, WA | - | Speech-Language Pathologist | 08/30/2016 |
| BARRETT, NATAJAH | PORT SAINT LUCIE, FL | EKG | RBT | 11/27/2023 |
| BARRETT, TAYLOR | MODESTO, CA | - | Professional Counselor | 05/15/2025 |
| BARRIENTOS, KARLA | SAN ANTONIO, TX | - | RBT | 09/24/2026 |
| BARRO SORIA, MARISELA | MIAMI, FL | - | RBT | 09/25/2026 |
| BARRON, RILEY | COLUMBIA, SC | RBT | RBT | 09/24/2026 |
| BARRY, ELLA | WOODBINE, NJ | - | Mental Health Counselor | 09/24/2026 |
| BARRY, JUSTUS | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| BARRY, REBECCA | LOUISVILLE, CO | MA, LPC | Professional Counselor | 01/23/2018 |
| BARTHELEMY, ROSE | BROOMALL, PA | - | RBT | 09/23/2026 |
| BARTHOLME, JACQUELINE | SAN MARCOS, CA | MS, CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| BARTHOLOMAY, MAX | FARMINGTON, CT | - | BCBA | 09/21/2026 |
| BARTLEY, MONICA | CORTLAND, OH | SWT | Clinical Social Worker | 11/06/2020 |
| BARTON, BRIANNA | FAYETTEVILLE, NC | - | RBT | 09/23/2026 |
| BARTON, KADISON | RICHFIELD, UT | LCSW | Clinical Social Worker | 09/24/2026 |
| BARTON, STACY | DONIPHAN, MO | LPC | Professional Counselor | 11/13/2020 |
| BARTSCH, CHRISTINA | WHITE PLAINS, NY | M.S., CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| BARUA, RIMKI | MISSION, KS | - | RBT | 09/23/2026 |
| BASDEKIS, NICHOLAS | WORCESTER, MA | - | Mental Health Counselor | 09/24/2026 |
| BASISTA, BARBORA | ALBUQUERQUE, NM | - | Speech-Language Pathologist | 09/24/2026 |
| BASKIN, AARON | HINGHAM, MA | LMHC | Mental Health Counselor | 03/22/2023 |
| BASKIN, ABBIE | VALDOSTA, GA | - | BCBA | 09/30/2024 |
| BASSETT, GRACIE | EAST LANSING, MI | - | RBT | 09/24/2026 |
| BASSIMAKOPOLOS, AMANDA | TURNERSVILLE, NJ | LCSW | Clinical Social Worker | 09/22/2026 |
| BASTIEN, LAENS | MILLERSVILLE, MD | RBT | RBT | 09/21/2026 |
| BATEMAN, NICOLE | CHICAGO, IL | LCSW | Clinical Social Worker | 09/22/2026 |
| BATEMAN, NIKIA | FRESNO, CA | LCSW | Clinical Social Worker | 01/11/2022 |
| BATES, ANGELA | OLYMPIA, WA | LMHCA | Mental Health Counselor | 09/09/2024 |
| BATES, JAMIE | AKRON, OH | LPC | Addiction (Substance Use Disorder) Counselor | 06/18/2021 |
| BATES, MIRACLE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| BATES, SAMANTHA | GLADSTONE, MO | - | RBT | 09/24/2026 |
| BATISTA, ESTELA | WORCESTER, MA | LMHC | Mental Health Counselor | 02/08/2022 |
| BATO, RACHEL | PORTLAND, OR | - | Case Manager/Care Coordinator | 09/24/2026 |
| BATRICE, DENA | DALLAS, TX | - | Clinical Social Worker | 08/25/2026 |
| BATSON, MACKENZIE | AURORA, CO | MA, LPC | Mental Health Counselor | 10/05/2022 |
| BATTAGLIESE, LAURA | SACRAMENTO, CA | M.A. | Speech-Language Pathologist | 06/19/2014 |
| BATTAIA, CHASE | LITTLETON, CO | - | Clinical Social Worker | 09/24/2026 |
| BAUDENDISTEL, CORTNEY | GREENSBURG, IN | LCSW | Clinical Social Worker | 09/25/2026 |
| BAUER, ELAYNA | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| BAUER, STACIE | BAY CITY, MI | - | BCBA | 05/01/2019 |
| BAUM, JESSICA | PARK RAPIDS, MN | MA LPCC | Mental Health Counselor | 03/20/2019 |
| BAUM, PHOEBE | PHILADELPHIA, PA | - | Clinical Social Worker | 09/24/2026 |
| BAUSCH, MELISSA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BAUTISTA-MOORE, CANDICE | HAYWARD, CA | - | RBT | 09/21/2026 |
| BAUTISTA, JOAN | CHULA VISTA, CA | LCSW | Clinical Social Worker | 09/22/2026 |
| BAUTISTA, JOSEPH | UPLAND, CA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| BAUTISTA, LITZY | SAN JOSE, CA | - | RBT | 09/24/2026 |
| BAUTISTA, LIZBETH | DUARTE, CA | BACHELORS OF ARTS | Case Manager/Care Coordinator | 05/20/2021 |
| BAVIS, KIMBERLY | VICTOR, NY | - | Specialist | 09/25/2026 |
| BAVOSA, RENE | ANNANDALE, NJ | - | Professional Counselor | 12/18/2023 |
| BAXTER, CECILIA | OREFIELD, PA | LPC | Mental Health Counselor | 06/17/2026 |
| BAXTER, HAYLEY | BLUE ASH, OH | LISW-SUPV | Clinical Social Worker | 08/08/2018 |
| BAXTER, LINDSAY | RICHMOND, VA | - | Clinical Social Worker | 09/21/2026 |
| BAXTER, MADISON | CRESTVIEW, FL | - | BCBA | 09/22/2026 |
| BAXTER, NICOLE | CHICAGO, IL | LCSW | Clinical Social Worker | 08/03/2016 |
| BAXTER, STEPHANIE | LONGVIEW, WA | - | Clinical Social Worker | 04/23/2019 |
| BAY VALLEY MARRIAGE & FAMILY COUNSELING GROUP, INC.ORG | VACAVILLE, CA | - | Counselor | 09/24/2026 |
| BAYER, MICHELE | WEST SACRAMENTO, CA | MHRS | Case Manager/Care Coordinator | 09/28/2020 |
| BAYHA, JENNY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| BAYLEY, KELLY | METAMORA, MI | - | Speech-Language Pathologist | 09/22/2026 |
| BAYSIDE DYSPHAGIA DIAGNOSTICSORG | HYANNIS, MA | - | Speech-Language Pathologist | 07/15/2026 |
| BCS MANAGEMENT LLCORG | IRVING, TX | - | Clinic/Center | 05/21/2019 |
| BE PARTICULAR PEER SUPPORT EDUCATION & NAVIGATION SERVICES INCORG | LOS ANGELES, CA | - | Mental Health Counselor | 09/21/2026 |
| BEA, KATELYN | DANVILLE, VA | - | RBT | 09/25/2026 |
| BEACON BEHAVIORAL HEALTH OF TEXAS INC.ORG | HOUSTON, TX | - | Case Management Agency | 09/18/2026 |
| BEACON BEHAVIORAL OUTPATIENT - BELLAIRE LLCORG | BELLAIRE, TX | - | Community/Behavioral Health Agency | 07/10/2025 |
| BEAR STEPS ABA, LLCORG | GRASS VALLEY, CA | - | Community/Behavioral Health Agency | 09/25/2026 |
| BEAR, ANGELA | NORTH PLATTE, NE | MAMFT, LMHP | Professional Counselor | 03/30/2018 |
| BEARDSLEY, EVELYN | MERCED, CA | - | Speech-Language Pathologist | 08/20/2019 |
| BEARNSON, CADIN | VERNAL, UT | - | Clinical Social Worker | 08/07/2024 |
| BEASLEY, EMILY | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| BEAUTIFUL LIFE INC.ORG | LAS VEGAS, NV | - | Case Management Agency | 10/01/2021 |
| BEAUVAIS, CLAUDIA | FARMINGTON HILLS, MI | - | RBT | 06/05/2019 |
| BEBLEY, KEIANNA | HOUSTON, TX | - | RBT | 09/21/2026 |
| BEBOUT, TORI | CANTON, OH | - | Case Manager/Care Coordinator | 11/10/2025 |
| BECERRA WELLNESS LLCORG | HOLMDEL, NJ | - | Mental Health Counselor | 09/21/2026 |
| BECERRA, DANIELA | SAN JOSE, CA | - | Clinical Social Worker | 09/23/2026 |
| BECERRA, GUADALUPE | IDAHO FALLS, ID | BS | Case Manager/Care Coordinator | 09/23/2026 |
| BECKER CHIROPRACTIC CORPORATIONORG | SAN MATEO, CA | - | Clinic/Center | 03/31/2023 |
| BECKER, ALANA | NEW YORK, NY | PH.D. | Psychologist | 05/19/2022 |
| BECKER, SARA | SCOTTSDALE, AZ | LMSW | Clinical Social Worker | 09/23/2026 |
| BECKHAM COUNSELING LLCORG | WINTER PARK, FL | - | Mental Health Counselor | 01/27/2025 |
| BECKHAM, ROBERT | WINTER PARK, FL | LMHC, NCC | Mental Health Counselor | 12/06/2023 |
| BECKMAN, NICOLE | KENOSHA, WI | M.S., CCC-SLP | Speech-Language Pathologist | 09/24/2026 |
| BECKNER, MICHAEL | AZUSA, CA | - | RBT | 09/22/2026 |
| BEDARD-CAMPBELL, JORDAN | ELKTON, MD | - | Professional Counselor | 09/24/2026 |
| BEDARD, MANUEL | NATIONAL CITY, CA | CADC-II | Addiction (Substance Use Disorder) Counselor | 07/28/2017 |
| BEDFORD, VICKI | MOUNT SHASTA, CA | - | Clinical Social Worker | 02/24/2020 |
| BEDNAR, ANN | WEST CHICAGO, IL | - | BCBA | 03/21/2018 |
| BEE WELL COUNSELING LLCORG | LEES SUMMIT, MO | - | Clinical Social Worker | 03/26/2026 |
| BEE, ALLERA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| BEEBE, MICHAEL | CASS CITY, MI | - | RBT | 09/24/2026 |
| BEENE, BRENDA | LAWTON, OK | - | RBT | 09/24/2026 |
| BEERY, ROBIN | INDIANAPOLIS, IN | - | Clinical Social Worker | 09/25/2026 |
| BEFORE THREE PCORG | BLOOMINGDALE, IL | - | BCBA | 09/24/2026 |
| BEGLEY, JONATHAN | WEST LAKE HILLS, TX | LCSW | Clinical Social Worker | 07/26/2022 |
| BEGLEY, JULIA | GRAND RAPIDS, MI | - | RBT | 09/23/2026 |
| BEHAVIOR ANALYSTS OF NAPLESORG | NAPLES, FL | - | BCBA | 01/02/2020 |
| BEHAVIOR IN ACTION LLCORG | SANTEE, CA | - | BCBA | 12/11/2023 |
| BEHAVIOR SPROUTS, LLCORG | CHICAGO, IL | - | BCBA | 08/05/2026 |
| BEHAVIORAL PROGRESSION INCORG | CLEVELAND, OH | - | BCBA | 09/22/2026 |
| BEHAVIORAL PROGRESSION INCORG | LAKELAND, FL | - | BCBA | 07/20/2026 |
| BEHAVIORAL PROGRESSION INCORG | COLUMBIA, SC | - | BCBA | 06/25/2026 |
| BEHAVIORAL PROGRESSION INCORG | LAKELAND, FL | - | BCBA | 09/04/2014 |
| BEHAVIORAL PROGRESSION INCORG | TAMPA, FL | - | BCBA | 07/19/2021 |
| BEHN, CHRISTINE | SMITHFIELD, RI | SLP | Speech-Language Pathologist | 05/12/2011 |
| BEING WELL COUNSELING SERVICES PLLCORG | HARKER HEIGHTS, TX | - | Professional Counselor | 01/30/2023 |
| BEISCOE, MELODY | GUNTERSVILLE, AL | LPC | Professional Counselor | 01/06/2025 |
| BEISER, TABATHA | SAN RAMON, CA | - | Mental Health Counselor | 09/21/2026 |
| BELANGER, CRYSTAL | CASPER, WY | - | Day Training/Habilitation Specialist | 09/22/2026 |
| BELASKI, KAUWELA | WAIPAHU, HI | - | RBT | 09/22/2026 |
| BELAUSTEGUIGOITIA SEGUIN, ELIANY | DORAL, FL | - | RBT | 02/12/2024 |
| BELC, JESSE | SAN DIEGO, CA | BCBA | BCBA | 05/28/2020 |
| BELCHER, BYRON | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| BELCHER, THOMAS | FOREST HILL, MD | - | RBT | 09/22/2026 |
| BELIEVE PSYCHOTHERAPY LCSW PLLCORG | NEW YORK, NY | - | Clinical Social Worker | 09/21/2026 |
| BELISLE, DIANE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| BELISLE, MEGHAN | PROVIDENCE, RI | LCSW | Clinical Social Worker | 04/07/2026 |
| BELK, JAMIE | SAGINAW, MI | - | Case Manager/Care Coordinator | 09/22/2026 |
| BELL OCD AND ANXIETY TREATMENT FOR ADULT AND CHILD THERAPYORG | LAKEWOOD, CA | - | Clinical Social Worker | 12/12/2019 |
| BELL, COURTNEY | STOCKTON, CA | - | RBT | 09/21/2026 |
| BELL, DANIEL | PORTLAND, ME | LCSW, CCS, LADC | Clinical Social Worker | 01/20/2017 |
| BELL, GOMATTIE | NEW YORK, NY | LMHC | Mental Health Counselor | 12/06/2018 |
| BELL, HEAVEN | ONTARIO, CA | - | RBT | 09/21/2026 |
| BELL, JORDAN | TALLAHASSEE, FL | - | RBT | 09/21/2026 |
| BELL, PAMELA | HENDERSON, NV | - | RBT | 09/21/2026 |
| BELL, PRISCILLA | LAUREL, MD | LCSW-C | Clinical Social Worker | 06/05/2023 |
| BELL, ROBERT | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| BELL, TANYLA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| BELL, TIFFANY | ASHEVILLE, NC | LCMHC | Mental Health Counselor | 03/20/2013 |
| BELLIVEAU, MARK | LEOMINSTER, MA | BS | Mental Health Counselor | 09/22/2026 |
| BELLO DIAZ, MISLEIDY | MIAMI, FL | - | RBT | 10/15/2021 |
| BELLO OLAZARRA, DAISY | MIAMI, FL | - | RBT | 09/22/2023 |
| BELLO, LIRYENNE | TAMPA, FL | BCBA | BCBA | 11/10/2023 |
| BELLORIN, ANDREA | FAIRFAX, VA | - | RBT | 09/25/2026 |
| BELONG COUNSELING AND CONSULTING, LLCORG | TAOS, NM | - | Mental Health Counselor | 07/26/2022 |
| BELOVED PEDIATRIC THERAPY LLCORG | JERSEY CITY, NJ | - | BCBA | 09/23/2026 |
| BELTRAN, ELISA | TEMECULA, CA | - | RBT | 07/22/2024 |
| BELVEDERE HEALTH SERVICES LLCORG | ALBANY, NY | - | Case Management Agency | 03/12/2008 |
| BELVEDERE HEALTH SERVICES LLC.ORG | ALBANY, NY | - | Case Management Agency | 02/24/2011 |
| BEN-DOV, SHANI | STAMFORD, CT | LCSW | Clinical Social Worker | 02/07/2026 |
| BEN, LETITIA | CONCORD, CA | - | RBT | 09/23/2026 |
| BENAGE, YVETTE | SAN ANTONIO, TX | LPC-ASSOCIATE | Professional Counselor | 11/30/2023 |
| BENAVIDES-URESTI, ALISSA | FRESNO, CA | - | BCBA | 10/05/2022 |
| BENAVIDEZ, CAROL | BROOKLYN, NY | - | RBT | 09/23/2026 |
| BENCHMARK PHYSICAL THERAPY OF DELAWARE LLCORG | MILLSBORO, DE | - | Speech-Language Pathologist | 02/27/2019 |
| BENDER, JOELLE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| BENDER, KERRY | BALLWIN, MO | ED.D, SLP | Speech-Language Pathologist | 07/13/2017 |
| BENEDICT, KALLY | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| BENGALA, AMY | FOWLERVILLE, MI | - | Speech-Language Pathologist | 09/25/2026 |
| BENITEZ DANGER, MONICA | MIAMI, FL | - | RBT | 04/30/2021 |
| BENITEZ FLORES, MELISSA | TORRANCE, CA | - | RBT | 09/21/2026 |
| BENJAMIN, BROOKE | FORT MYERS, FL | MA | Mental Health Counselor | 09/26/2026 |
| BENJAMIN, EVAN | CHARLESTON, WV | - | Mental Health Counselor | 09/21/2026 |
| BENJAMIN, JHAVIA | LOS ANGELES, CA | ASW, MSW, MA | Day Training/Habilitation Specialist | 12/13/2022 |
| BENJAMIN, PHYLLIS | LANDOVER, MD | - | Clinical Social Worker | 11/16/2023 |
| BENNETT DE VELASQUEZ, MALIAH | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| BENNETT-TOUSSAINT, ANNIKA | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| BENNETT, ANGEL | PORT SAINT LUCIE, FL | - | Mental Health Counselor | 09/25/2026 |
| BENNETT, HANNAH | MYRTLE BEACH, SC | LISW-CP | Clinical Social Worker | 09/21/2026 |
| BENNETT, JORDAN | PORT HURON, MI | MSW | Clinical Social Worker | 05/31/2019 |
| BENNETT, KATINA | CHESTERFIELD, MI | LLPC | Counselor | 03/16/2018 |
| BENNETT, KIRSTIE | SAINT MARYS, PA | M.S., CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| BENNETT, MARGO | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| BENNETT, SAMANTHA | KOKOMO, IN | BCBA | BCBA | 01/27/2021 |
| BENNETT, SHONTAY | FARMINGTON HILLS, MI | - | RBT | 08/20/2026 |
| BENNETT, TAYLOR | WESLEY CHAPEL, FL | - | RBT | 09/23/2026 |
| BENNETT, TIA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| BENOIT, DAWNE | WORCESTER, MA | - | BCBA | 09/24/2026 |
| BENOIT, LIVIA | NORTH MIAMI, FL | - | RBT | 09/21/2026 |
| BENRUBI, RACHEL | GRANITE CITY, IL | LCPC | Counselor | 10/03/2014 |
| BENSON, BROOKLYN | MESA, AZ | SLP | Speech-Language Pathologist | 03/12/2020 |
| BENTLEY, JACOB | KNOXVILLE, TN | - | Professional Counselor | 02/18/2020 |
| BENTON, MATTHEW | CIRCLEVILLE, OH | - | Case Manager/Care Coordinator | 04/11/2026 |
| BERBEROGLU, DIDAR | KATY, TX | - | RBT | 09/21/2026 |
| BERDINE, JESSICA | DAMARISCOTTA, ME | MA, CCC-SLP | Speech-Language Pathologist | 10/04/2019 |
| BERFECT, JASMINE | NEW ORLEANS, LA | LCSW | Clinical Social Worker | 07/21/2016 |
| BERG, CHERYL | EVANSTON, IL | - | Clinical Social Worker | 04/16/2007 |
| BERGEN ALL-STARS A NJ NON PROFIT CORPORATIONORG | UPPER SADDLE RIVER, NJ | - | RBT | 09/24/2026 |
| BERGJANS, JESSIE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| BERGMAN, ZOE | PHILADELPHIA, PA | - | Mental Health Counselor | 09/21/2026 |
| BERGMANN, BARBARA | FORT LAUDERDALE, FL | - | Psychologist | 04/12/2007 |
| BERLEY, MARCUS | CRANSTON, RI | LMHC | Mental Health Counselor | 01/13/2011 |
| BERLON, CLAIRE | CHICAGO, IL | - | Mental Health Counselor | 09/22/2026 |
| BERMENSOLO, MARY | BOISE, ID | LCSW | Clinical Social Worker | 01/09/2007 |
| BERMUDAS MARTINEZ, IXCHEL | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| BERNARD, EMERANCE | SEATTLE, WA | - | RBT | 09/25/2026 |
| BERNARD, HANNAH | GEORGETOWN, KY | LCSW | Clinical Social Worker | 06/06/2026 |
| BERQUIST, BAILEY | MINOT, ND | LPCC | Professional Counselor | 04/26/2018 |
| BERRIOS, JUANITA | SAN JUAN, PR | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| BERRY COUNSELING PLLCORG | DEARBORN, MI | - | Clinical Social Worker | 09/24/2026 |
| BERRY, DA'KECIA | DALLAS, TX | LCSW | Clinical Social Worker | 09/22/2026 |
| BERRY, LEIGHTON | CYPRESS, TX | RBT | RBT | 09/24/2026 |
| BERRY, MINDY | BLOSSOM, TX | - | Speech-Language Pathologist | 09/25/2026 |
| BERRY, RODERICK | DETROIT, MI | - | RBT | 09/23/2026 |
| BERRY, TYLER | RICHMOND, VA | BCBA/LBA | BCBA | 07/10/2023 |
| BERRYHILL, ASHLEIGH | GRETNA, LA | LCSW | Mental Health Counselor | 11/13/2013 |
| BERTONE, BRITTANY | FRESNO, CA | - | RBT | 09/21/2026 |
| BESHAI, YOSTINA | NEWPORT BEACH, CA | - | BCBA | 11/11/2020 |
| BESSE, BRYAN | NEW BEDFORD, MA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| BESSETTE, KRISTA | MUSKEGO, WI | LPC | Professional Counselor | 03/01/2012 |
| BEST CARE MANAGEMENT AGENCY LLCORG | GREAT NECK, NY | - | Case Management Agency | 09/21/2026 |
| BEST, KIM | FREMONT, NC | MS, LCMHCA, LCASA | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| BESTILL THERAPY SERVICES LLCORG | RIVERVIEW, FL | - | Community/Behavioral Health Agency | 09/21/2026 |
| BETANCOURT MENDEZ, CARLOS | MONROE, NC | - | Case Manager/Care Coordinator | 09/21/2026 |
| BETANCOURT, ANDREA | SAN ANTONIO, TX | - | RBT | 09/25/2026 |
| BETANCOURT, MILANNIE | HOLYOKE, MA | - | Mental Health Counselor | 09/22/2026 |
| BETH L PLACHETKA, MSW, LCSW, P.C.ORG | SUGAR GROVE, IL | - | Clinical Social Worker | 06/18/2009 |
| BETHEA, CIARA | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| BETHESDA FAMILY PHYSICIANS ASSOCIATESORG | TYLER, TX | - | Mental Health Counselor | 06/17/2009 |
| BETTER DAY RVA LLCORG | MIDLOTHIAN, VA | - | Clinical Social Worker | 09/21/2026 |
| BETTERLEY, SAVANNAH | CONCORD, NH | - | Specialist | 09/21/2026 |
| BETTGER, ALICIA | BELLINGHAM, WA | - | Mental Health Counselor | 09/23/2026 |
| BETTIS TRUJILLO, KELSEY | TORRANCE, CA | LCSW107310 | Clinical Social Worker | 09/04/2019 |
| BETWEEN TIDES BEHAVIORAL HEALTH LLCORG | BOSTON, MA | - | Mental Health Counselor | 09/23/2026 |
| BEVELS, LILLIYAN | NEWBURGH, IN | - | RBT | 09/22/2026 |
| BEY, AMIR | WILLIAMSPORT, PA | - | Mental Health Counselor | 09/22/2026 |
| BEY, JAMARA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 04/09/2026 |
| BEYOND POTENTIAL BEHAVIOR LLCORG | DADE CITY, FL | - | BCBA | 09/24/2026 |
| BEYOND RESILIENCE COUNSELING & WELLNESS PLLCORG | WINSTON SALEM, NC | - | Clinical Social Worker | 09/21/2026 |
| BEYOND THE ROOT COUNSELING AND CONSULTING,PLLCORG | SAN ANTONIO, TX | - | Clinical Social Worker | 10/26/2020 |
| BHAKTA, NANDINI | LA PUENTE, CA | - | Speech-Language Pathologist | 09/25/2026 |
| BHANGU, AMNEET | ANAHEIM, CA | - | Assistant Behavior Analyst | 09/21/2026 |
| BHAS, LIA | SAN BRUNO, CA | - | RBT | 09/21/2026 |
| BHS2 LLCORG | STERLING, VA | - | BCBA | 09/21/2026 |
| BIBEAU, CLIFFORD | NASHUA, NH | M.A., LCMHC | Mental Health Counselor | 06/23/2016 |
| BICE, MARK | CLEARLAKE, CA | - | Day Training/Habilitation Specialist | 09/15/2026 |
| BICY, LESLEY | JACKSON, MI | LPC INTERN | Mental Health Counselor | 02/21/2023 |
| BIDDLE, AMANDA | LEWISTOWN, PA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BIEHL, TARA | ALBUQUERQUE, NM | - | Mental Health Counselor | 09/25/2026 |
| BIELA, MEGAN | BENNINGTON, VT | - | Counselor | 02/26/2016 |
| BIEMULLER, RYAN | MALVERN, PA | BCBA | BCBA | 09/25/2026 |
| BIENENFELD, ANNA | FERNDALE, MI | - | Speech-Language Pathologist | 09/21/2026 |
| BIER, PAULA | SANDUSKY, OH | SPEECH THERAPIST | Speech-Language Pathologist | 11/04/2005 |
| BIG DREAMERS ABA CO LLCORG | GREELEY, CO | - | BCBA | 09/22/2026 |
| BIGGER, GRACE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BIGGINS, TIFFANY | GETTYSBURG, PA | - | Mental Health Counselor | 09/13/2020 |
| BIGGS, KARSON | NAPLES, FL | M.S., CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| BIGGS, MICHAEL | EVANSTON, IL | - | Counselor | 09/24/2026 |
| BIGLEY, G. | RENO, NV | M.D. | Specialist | 05/11/2006 |
| BIJEAUX, TRACY | LAFAYETTE, LA | - | Counselor | 09/22/2026 |
| BILEY, HARPER | HOUSTON, TX | - | RBT | 09/21/2026 |
| BILGO, THERESA | WAUKESHA, WI | MA, BCBA, LBA | Mental Health Counselor | 01/03/2019 |
| BILLEY, TAYLOR | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| BILOKURY-ADAMS, REBECCA | MINOT, ND | - | Case Manager/Care Coordinator | 09/25/2026 |
| BINAG, JOSHUA RENE | UNION CITY, NJ | MSW, LCSW | Clinical Social Worker | 01/18/2022 |
| BINFORD-BOLLING, AMBER | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/16/2026 |
| BIONDICH, STEVEN | BILLINGS, MT | LCPC | Professional Counselor | 12/08/2006 |
| BIOPHILIA PSYCHOTHERAPY, LLCORG | STUART, FL | - | Clinical Social Worker | 09/21/2026 |
| BIRCH, AMY | MIO, MI | CCC-SLP | Speech-Language Pathologist | 01/05/2014 |
| BIRD, BRITTANY | CEDAR SPRINGS, MI | - | RBT | 10/27/2022 |
| BIRDSONG, JENNIFER | KANSAS CITY, MO | LCSW, LSCSW | Clinical Social Worker | 02/09/2024 |
| BIRECH, IVY | BALTIMORE, MD | - | RBT | 07/15/2026 |
| BIRKHAUSER, CALEB | ALBUQUERQUE, NM | - | RBT | 09/25/2026 |
| BIRKLAND, JORDAN | OMAHA, NE | LIMHP | Mental Health Counselor | 10/29/2020 |
| BIRSFIELD, ABIGAIL | INDIANAPOLIS, IN | - | RBT | 09/25/2026 |
| BISHOP, AMBER | EUGENE, OR | LPC | Professional Counselor | 08/24/2021 |
| BISONO, ANNY | PHILADELPHIA, PA | - | Clinical Social Worker | 06/01/2018 |
| BISSONNETTE, SEBASTIAN | JACKSONVILLE, FL | - | RBT | 09/22/2026 |
| BITAR, NOOR | IRVING, TX | M.S. CCC-SLP | Speech-Language Pathologist | 07/31/2023 |
| BITTERLICH, CHYANNA | ASHEVILLE, NC | - | RBT | 09/21/2026 |
| BITTERMAN, AVIGAIL | HOLLYWOOD, FL | LCSW | Clinical Social Worker | 09/24/2026 |
| BITTING, ALEX | CLIVE, IA | T-LMHC | Mental Health Counselor | 09/21/2026 |
| BITTNER, JONATHAN | PHILADELPHIA, PA | - | Mental Health Counselor | 09/22/2026 |
| BIVENS, PAYTEN | WEATHERFORD, OK | - | RBT | 09/24/2026 |
| BIZZY BEES THERAPY LLCORG | SMITHFIELD, RI | - | Speech-Language Pathologist | 02/03/2021 |
| BKN LEGACY LLCORG | GREEN, OH | - | Speech-Language Pathologist | 09/25/2026 |
| BLACK BULL, JACKSON | EDEN PRAIRIE, MN | - | RBT | 09/21/2026 |
| BLACK CANYON COMMUNITY HEALTH CENTER, INC.ORG | MAYER, AZ | - | Mental Health Counselor | 12/16/2022 |
| BLACK CANYON COMMUNITY HEALTH CENTER, INC.ORG | BLACK CANYON CITY, AZ | - | Counselor | 07/08/2022 |
| BLACK SHEPERD COUNSELING LLCORG | GILLETTE, WY | - | Mental Health Counselor | 09/24/2026 |
| BLACK WING COUNSELINGORG | MORRISVILLE, PA | - | Counselor | 08/10/2026 |
| BLACK, ISAAC | MERIDIAN, ID | - | Mental Health Counselor | 02/27/2026 |
| BLACK, LAUREN | OKLAHOMA CITY, OK | LCSW, LSW-ADM | Clinical Social Worker | 09/20/2023 |
| BLACK, MADISON | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/18/2026 |
| BLACK, STEPHEN | GRASS VALLEY, CA | SUDCC-III | Addiction (Substance Use Disorder) Counselor | 05/15/2013 |
| BLACKMAN, CAITLIN | LEESBURG, VA | - | Mental Health Counselor | 03/03/2023 |
| BLACKMAN, SANIA | LEXINGTON, SC | - | Counselor | 09/24/2026 |
| BLADT, JESSICA | BEND, OR | CRM | Addiction (Substance Use Disorder) Counselor | 12/13/2021 |
| BLAIR, GRACIE | LOCUST GROVE, OK | MS, CF-SLP | Speech-Language Pathologist | 09/25/2026 |
| BLAIR, JILLIAN | NORMAN, OK | - | RBT | 09/25/2026 |
| BLAIR, KEVIN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BLAIR, TERRY | BEACHWOOD, OH | - | Counselor | 09/23/2026 |
| BLAIS, IRINA | NORTH PROVIDENCE, RI | BA, BS, MS, LMHCA | Mental Health Counselor | 09/22/2026 |
| BLAKE, GABRIEL | ALEXANDRIA, VA | - | RBT | 09/21/2026 |
| BLAKE, MICHELE | FENNVILLE, MI | CCC-SLP | Speech-Language Pathologist | 09/24/2026 |
| BLAKNEY, RYLEE | AMORY, MS | - | Speech-Language Pathologist | 09/08/2026 |
| BLANC, ABIGGAELE | BALTIMORE, MD | - | RBT | 09/23/2026 |
| BLANCHARD, AMBER | SPOKANE, WA | - | RBT | 09/22/2026 |
| BLANCO RODRIGUEZ, GEIDY | LEHIGH ACRES, FL | RBT-23-287274 | RBT | 08/24/2023 |
| BLANCO, JOSE LUIS | FRESNO, CA | - | Counselor | 09/21/2026 |
| BLANCO, KAYLA | MIAMI, FL | - | RBT | 05/12/2025 |
| BLAND, LESLIE | KERNERSVILLE, NC | LPC | Professional Counselor | 07/09/2011 |
| BLANKENSHIP, RACHEL | ALPENA, MI | - | Clinical Social Worker | 12/13/2023 |
| BLANKINSHIP, ANNA | SPRINGFIELD, VA | - | RBT | 09/21/2026 |
| BLANKS, DEMONDRE | JEFFERSONVILLE, IN | - | RBT | 09/23/2026 |
| BLAQUE LOTUS COUNSELING, LLCORG | FORT LAURDERDALE, FL | - | Clinical Social Worker | 09/21/2026 |
| BLAS, CHRISTOPHER | COLORADO SPRINGS, CO | - | Case Manager/Care Coordinator | 09/21/2026 |
| BLEDSOE, ASHLEY-MARIE | BURLINGTON, NC | - | Mental Health Counselor | 09/22/2026 |
| BLEIDISTEL, MICHAEL | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| BLESSING HEARTS LEARNING & BEHAVIORAL CENTER LLCORG | SUNRISE, FL | - | BCBA | 02/27/2025 |
| BLEVINS, SHAWNA | INDIANAPOLIS, IN | - | Clinical Social Worker | 09/25/2026 |
| BLISSFUL OAKS LLCORG | POMPANO BEACH, FL | - | Community/Behavioral Health Agency | 09/21/2026 |
| BLOCKMON, LANISHA | NORTHBROOK, IL | - | Professional Counselor | 03/25/2018 |
| BLOM, LAURA | MODESTO, CA | LCSW | Clinical Social Worker | 09/15/2025 |
| BLOMGREN, KAITLYN | SAINT JAMES, MN | - | Speech-Language Pathologist | 09/23/2026 |
| BLONDIN, RYLIE | LAWRENCE, MA | - | Mental Health Counselor | 09/23/2026 |
| BLOOM, RICHARD | BEAVERTON, OR | - | RBT | 09/22/2026 |
| BLOOMFELDT, AMANDA | KELSO, WA | CM/CC | Case Manager/Care Coordinator | 11/30/2016 |
| BLOOMFIELD, TATYANA | GREENSBORO, NC | - | Professional Counselor | 09/25/2026 |
| BLOOMWAY BEHAVIORAL HEALTH & WELLNESS, PLLCORG | WILMINGTON, NC | - | Clinical Social Worker | 09/27/2025 |
| BLOUNT, JESSICA | COLORADO SPRINGS, CO | LPC, LAC, NCC | Professional Counselor | 03/14/2018 |
| BLOUNT, LAURA | KILLEEN, TX | RBT | RBT | 09/21/2026 |
| BLUE SKIES COUNSELINGORG | HERRIMAN, UT | - | Clinical Social Worker | 04/08/2020 |
| BLUE STEM COUNSELING LLCORG | NORMAN, OK | - | Mental Health Counselor | 09/26/2026 |
| BLUESPRIG PEDIATRICSORG | KATY, TX | - | RBT | 09/24/2026 |
| BLUESTEM HEALTHORG | LINCOLN, NE | - | Mental Health Counselor | 09/23/2026 |
| BLUFORD, RUKIYA | JERSEY CITY, NJ | LPC | Professional Counselor | 01/27/2021 |
| BLUMHORST, PAIGE | CHATHAM, IL | - | Speech-Language Pathologist | 09/25/2026 |
| BLUNT CHISOLM, TAMEKA | JACKSONVILLE, NC | - | RBT | 09/22/2026 |
| BMORE PSYCHOTHERAPY GROUP, LLCORG | TIMONIUM, MD | - | Professional Counselor | 09/21/2026 |
| BODDIE, WILLIAM | MODESTO, CA | L.C.S.W | Clinical Social Worker | 06/26/2006 |
| BODERO, SHANEL | LAYTON, UT | - | Case Manager/Care Coordinator | 09/29/2025 |
| BODHOLDT, ANNA-MARIE | COLORADO SPRINGS, CO | - | RBT | 10/13/2020 |
| BODY AND VOICE LLCORG | NASHVILLE, TN | - | Speech-Language Pathologist | 09/21/2026 |
| BOEHMER, LOGAN | GRANTS PASS, OR | AA | BCBA | 09/21/2026 |
| BOEKHOFF, JESSICA | CEDAR RAPIDS, IA | MS, TLMHC | Mental Health Counselor | 09/22/2026 |
| BOFFILL CHACON, MAYDEL | MIAMI, FL | - | RBT | 09/10/2025 |
| BOGART-MONTEITH, MISHA | EUGENE, OR | LPC | Mental Health Counselor | 01/05/2017 |
| BOGART, HANNAH | SALT LAKE CITY, UT | - | Speech-Language Pathologist | 02/16/2026 |
| BOGDEWIC, CHAD | PITTSBURGH, PA | - | BCBA | 09/25/2026 |
| BOGGI, PATRICK | WHITE PLAINS, NY | - | Clinical Social Worker | 09/21/2026 |
| BOGGS, DANIELLE | FARMINGTON HILLS, MI | - | RBT | 11/01/2024 |
| BOHINSKI, LISA | LONG BEACH, CA | - | Day Training/Habilitation Specialist | 07/13/2023 |
| BOHN, JESSICA | BLOOMINGDALE, NJ | - | Mental Health Counselor | 09/25/2026 |
| BOISSERANC, KAI | ORANGE, CA | - | RBT | 09/22/2026 |
| BOITANO, BENJAMIN | FEDERAL WAY, WA | - | Clinical Social Worker | 09/21/2026 |
| BOJARSKI, MIRIAM | BROOKLYN, NY | LMSW | Clinical Social Worker | 09/22/2026 |
| BOJIC, ADI | SOMERVILLE, MA | - | RBT | 09/24/2026 |
| BOLAND, JAIME | TAHLEQUAH, OK | - | RBT | 09/24/2026 |
| BOLAND, MARCY | CLINTON, WA | - | Mental Health Counselor | 09/26/2026 |
| BOLINT, HAYLEIGH | METAIRIE, LA | - | RBT | 09/22/2026 |
| BOLIVAR, DANIELLE | WAGONER, OK | - | Clinical Social Worker | 09/22/2026 |
| BOLT, HOLLY | GREENWOOD VILLAGE, CO | - | RBT | 10/27/2021 |
| BOLTON, KERRY | LAKE ORION, MI | - | Speech-Language Pathologist | 09/24/2026 |
| BOLTON, RACHAEL | KNOXVILLE, TN | LPC-MHSP | Professional Counselor | 10/10/2012 |
| BOMBARDIER, CHEYENNE | COLORADO SPRINGS, CO | MA | Mental Health Counselor | 09/24/2026 |
| BOMMARITO, REBEKKA | JACKSON, MI | LPC | Mental Health Counselor | 02/22/2023 |
| BOMMARITO, SAMUEL | JACKSON, MI | LLPC | Mental Health Counselor | 11/11/2025 |
| BOND, ANGELA | ARLINGTON, WA | SUDP | Addiction (Substance Use Disorder) Counselor | 12/07/2020 |
| BOND, LAUREN | CONWAY, AR | - | Mental Health Counselor | 08/17/2015 |
| BONHAM, ISABELLA | TACOMA, WA | - | Clinical Social Worker | 09/22/2026 |
| BONILLA, MELANEY | TORRANCE, CA | - | RBT | 09/22/2026 |
| BONINO SOBOL, JENNIFER | DOWNERS GROVE, IL | PH.D., LCPC | Professional Counselor | 08/16/2016 |
| BONITTO, GINA | HEMPSTEAD, NY | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| BONNELL, TIMOTHY | PARKERSBURG, WV | - | Counselor | 09/24/2026 |
| BONNER GENERAL HOSPITAL, INCORG | SANDPOINT, ID | - | Clinical Social Worker | 01/17/2018 |
| BONNER, ELIZABETH | OZARK, AR | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| BONNER, SANYAH | ANTIOCH, CA | - | RBT | 09/25/2026 |
| BONNETTE, ASHLEY | COLUMBIA, SC | - | RBT | 09/24/2026 |
| BOOFER, OLIVIA | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| BOOKER, NATALIA | JEFFERSONVILLE, IN | - | RBT | 09/25/2026 |
| BOOKER, SAMAYA | DELRAY BEACH, FL | - | RBT | 09/22/2026 |
| BOOKSTORE, ERIN | AVON LAKE, OH | - | Mental Health Counselor | 09/22/2025 |
| BOONE, SHANTEL | CHESAPEAKE, VA | - | Mental Health Counselor | 09/23/2026 |
| BOONE, ZACHARY | CRESTVIEW HILLS, KY | LCSW | Clinical Social Worker | 08/19/2019 |
| BOOTH, HAILEY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BOOTH, INDIA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| BOOTHBY ZAPATA, LINA | WEBSTER, MA | LMHC | Mental Health Counselor | 03/23/2015 |
| BORDERLANDS HEALING COLLECTIVEORG | LAS CRUCES, NM | - | Clinical Social Worker | 08/17/2026 |
| BORDERS, RICHARD | ANNA, IL | LCSW | Clinical Social Worker | 09/21/2026 |
| BORDONARO, STEPHANIE | SOMERS POINT, NJ | MAS, BSHS, AAS | Addiction (Substance Use Disorder) Counselor | 11/14/2013 |
| BOREL, CHRISTINA | TORRINGTON, CT | LCSW, LICSW | Clinical Social Worker | 02/20/2008 |
| BORER, KERSTEN | OMAHA, NE | LIMHP, CMSW, LADC | Addiction (Substance Use Disorder) Counselor | 06/26/2006 |
| BORGES, NICHOLAS | AUSTIN, TX | - | Clinical Social Worker | 09/21/2026 |
| BORING, KAITLIN | PORTLAND, OR | - | RBT | 09/25/2026 |
| BORLAND, CARISSA | UPLAND, CA | - | Speech-Language Pathologist | 09/21/2026 |
| BORLIN, TORSTEN | SEATTLE, WA | - | Mental Health Counselor | 09/23/2026 |
| BORMAN, BETH | ROSEMOUNT, MN | MS CCC-SLP | Speech-Language Pathologist | 10/20/2006 |
| BORMANN, SARAH | OSWEGO, NY | - | Specialist | 09/26/2026 |
| BORNEMAN MANGIONE, HENRY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BOROWSKI, JILL | CHESHIRE, CT | - | Professional Counselor | 09/22/2026 |
| BORUS, JESSICA | KENNESAW, GA | RBT | RBT | 09/23/2026 |
| BORUS, SHARA | DEMAREST, NJ | LCSW | Clinical Social Worker | 12/01/2006 |
| BOS, KAILI | KENTWOOD, MI | - | RBT | 09/22/2026 |
| BOSCH, CHRISTINA | SPRINGFIELD, PA | - | RBT | 09/23/2026 |
| BOSTICK, NIGEL | TEGA CAY, SC | - | Mental Health Counselor | 09/23/2026 |
| BOSTON THERAPY COLLECTIVE, PLLCORG | BOSTON, MA | - | Clinical Social Worker | 05/19/2025 |
| BOTTOMS, LAUREN | REIDSVILLE, NC | - | Professional Counselor | 09/22/2026 |
| BOUCHARD, MELANIE | WILLISTON, VT | - | Psychologist | 12/02/2021 |
| BOUCHE, LAURA | WAXAHACHIE, TX | - | Professional Counselor | 09/21/2026 |
| BOUCHER, DANIA | OKLAHOMA CITY, OK | - | RBT | 09/24/2026 |
| BOUCHER, NAOMI | INDIANAPOLIS, IN | LMHC, CSAYC | Mental Health Counselor | 09/21/2022 |
| BOUDREAUX, NICOLE | PENDLETON, OR | M.S. | Mental Health Counselor | 02/26/2016 |
| BOUGERE, ANGELA | COVINA, CA | - | RBT | 11/11/2024 |
| BOUJU, ULYSSE | SACRAMENTO, CA | - | Addiction (Substance Use Disorder) Counselor | 07/17/2026 |
| BOULDEN, RAWN | MORGANTOWN, WV | - | Mental Health Counselor | 05/24/2021 |
| BOUMAN ALI, AHLAM | EVERETT, WA | - | Clinical Social Worker | 04/02/2019 |
| BOURBON, TAYLOR | PORTSMOUTH, NH | - | RBT | 09/24/2026 |
| BOURDEAU, ABIGAIL | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BOURGAULT, MAXIME | DALLAS, TX | - | Psychologist | 09/25/2026 |
| BOURGEOIS, LYRIC | TARZANA, CA | - | RBT | 09/26/2026 |
| BOURGEON, DANIELLE | PHILADELPHIA, PA | MS, LPC, NCC, CRC | Mental Health Counselor | 09/21/2024 |
| BOURNAS, ALEXANDRA | ORLAND PARK, IL | - | Mental Health Counselor | 09/25/2026 |
| BOURNE, ISABEL | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| BOUSE, ARI | LEWISTON, ME | - | Mental Health Counselor | 09/01/2011 |
| BOUSHIE, TAYLER | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| BOUTRIN, DJENNE | PHILADELPHIA, PA | - | Professional Counselor | 09/26/2026 |
| BOWE, MICHAEL | ROCKVILLE, MD | - | RBT | 09/25/2026 |
| BOWE, MICHELLE | MEDFORD, WI | PCT | Mental Health Counselor | 08/02/2013 |
| BOWEN, EMILY | WASHINGTON, IL | M.S. SLP | Speech-Language Pathologist | 09/22/2026 |
| BOWEN, JENNIFER | HARTWICK, NY | LBA | BCBA | 04/25/2023 |
| BOWERS, MACKENZIE | SUGAR HILL, GA | - | Speech-Language Pathologist | 09/25/2026 |
| BOWMAN, DIYON | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BOWMAN, JESSICA | CHICO, CA | LCSW | Clinical Social Worker | 10/03/2014 |
| BOX ELDER BEHAVIORAL HEALTH LLCORG | BUMPASS, VA | - | Counselor | 09/02/2018 |
| BOYD THERAPY CENTER, PLLCORG | BOYD, TX | - | Professional Counselor | 09/24/2026 |
| BOYD, KEOSHA | MEMPHIS, TN | BCBA, LBA | BCBA | 12/13/2023 |
| BOYD, KRISTEN | ONEIDA, NY | LMSW-LP | Counselor | 09/23/2026 |
| BOYD, MALISSA | ONTARIO, OH | LISW | Clinical Social Worker | 09/12/2018 |
| BOYD, MARIAH | TACOMA, WA | - | RBT | 09/21/2026 |
| BOYES, MARCIE | LOUISBURG, NC | LCSW | Clinical Social Worker | 08/24/2021 |
| BOYLAN, MINYOUNG | COLORADO SPRINGS, CO | - | RBT | 09/23/2026 |
| BOYLE, DAVID | MONROE, LA | PH.D, LMFT, LPC | Professional Counselor | 09/25/2012 |
| BOYLE, HANNAH | KELLER, TX | - | Professional Counselor | 09/22/2026 |
| BOYLEN, MCKENZIE | YOUNGSTOWN, OH | - | RBT | 09/23/2026 |
| BOYLEN, SARAH | SANTA ROSA, CA | - | RBT | 09/22/2026 |
| BRACY, GEORGIE | COLUMBUS, OH | LPCC | Professional Counselor | 01/04/2023 |
| BRADBURY, GRACELYNN | TOPEKA, KS | - | Speech-Language Pathologist | 09/24/2026 |
| BRADFORD, HAYLEE | SLIDELL, LA | - | Case Manager/Care Coordinator | 09/22/2026 |
| BRADFORD, JESSICA | YUMA, AZ | CF-SLP | Speech-Language Pathologist | 10/12/2017 |
| BRADLEY-BLUE, STEPHANIE | VIRGINIA BEACH, VA | PC | Professional Counselor | 06/29/2019 |
| BRADLEY-LEWIS, EZEKIEL | FARMINGTON HILLS, MI | - | RBT | 09/26/2026 |
| BRADLEY, DAWN | TOPEKA, KS | LSCSW | Clinical Social Worker | 05/28/2010 |
| BRADLEY, ELLA | KANSAS CITY, MO | - | RBT | 09/22/2026 |
| BRADLEY, ELYSSIA | METAIRIE, LA | - | RBT | 09/25/2026 |
| BRADLEY, GIANNA | TAMPA, FL | RMHCI | Mental Health Counselor | 09/22/2026 |
| BRADLEY, RAYETTA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| BRADNER-YOUNG, VIVIAN | SAINT PAUL, MN | - | RBT | 09/24/2026 |
| BRADSHAW, ASHLYN | GAINESVILLE, GA | - | Mental Health Counselor | 05/18/2024 |
| BRADSHAW, KAYDON | PROVO, UT | - | Clinical Social Worker | 08/17/2018 |
| BRADSHAW, TRINITY | FORT WORTH, TX | SLP | Speech-Language Pathologist | 09/21/2026 |
| BRADTKE, JENNIFER | STAFFORD, STAFFORDSHIRE | PSY.D., HSPP | Psychologist | 09/26/2007 |
| BRAGG, KATELYN | CHANTILLY, VA | - | RBT | 09/21/2026 |
| BRALEY, MEGHAN | BEVERLY, MA | LMHC | Mental Health Counselor | 08/07/2020 |
| BRANCH, MAKAYLA | GRANTSVILLE, UT | - | RBT | 09/21/2026 |
| BRANCH, STEPHANIE | AURORA, CO | - | RBT | 03/09/2026 |
| BRANDES, SHANNON | WICHITA, KS | LMHC | Mental Health Counselor | 07/06/2015 |
| BRANDLEY, AMY | YUKON, OK | LPC-CANDIDATE | Mental Health Counselor | 01/27/2023 |
| BRANDON JEFFERY LMHC PLLCORG | FITCHBURG, MA | - | Mental Health Counselor | 09/24/2026 |
| BRANDON, PHILLIP | KISSIMMEE, FL | LCSW | Clinical Social Worker | 09/23/2026 |
| BRANDON, SARAH | GULFPORT, MS | - | RBT | 09/22/2026 |
| BRANDT, ALICIA | FAIR OAKS, CA | - | Speech-Language Pathologist | 11/04/2021 |
| BRANN, HALIE | KANSAS CITY, MO | - | RBT | 09/24/2026 |
| BRANNON, TRACEY | GREENVILLE, SC | LISW-CP | Clinical Social Worker | 06/16/2021 |
| BRANSCUM-HIGUERA, JACOB | MONROE, WA | - | Mental Health Counselor | 11/07/2018 |
| BRANSTETTER, HEATHER | KELLOGG, ID | LPC | Professional Counselor | 03/21/2025 |
| BRATCHER, GENESE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BRAUN, MICHELLE | CRANBERRY TOWNSHIP, PA | LCSW | Clinical Social Worker | 12/04/2006 |
| BRAVE BIBLICAL COUNSELING LLCORG | DES MOINES, IA | - | Mental Health Counselor | 09/23/2026 |
| BRAVENCE, LUCIA | SAN DIEGO, CA | - | RBT | 09/26/2026 |
| BRAY, BAILEE | COCOA, FL | - | RBT | 09/23/2026 |
| BRAZIER, MELODY | MISHAWAKA, IN | - | RBT | 09/23/2026 |
| BRAZZEAL, DIANA | WESLEY CHAPEL, FL | MA, MED | Mental Health Counselor | 09/24/2026 |
| BREADY, BARBARA | WALES, MA | LICSW | Clinical Social Worker | 07/04/2006 |
| BREAKTHROUGH BEHAVIOR CONSULTATION, LLCORG | ST JOHNS, FL | - | BCBA | 09/16/2026 |
| BREAKTHROUGH ENDEAVORS PLLCORG | FRISCO, TX | - | Professional Counselor | 09/23/2026 |
| BREARLEY, TAYLOR | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| BREAZEALE ACHATZ, SYDNEY | MERIDIAN, MS | LCSW | Clinical Social Worker | 09/14/2026 |
| BREEDEN, JASON | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BREEDLOVE, EMILY | AUSTIN, TX | - | Professional Counselor | 08/31/2020 |
| BREEN, MOLLY | GREENWOOD VILLAGE, CO | LPCC | Mental Health Counselor | 07/27/2023 |
| BREEN, SAENGER | NORTHAMPTON, MA | - | RBT | 09/22/2026 |
| BREER, LYDIA | HOSCHTON, GA | LCSW | Clinical Social Worker | 02/10/2020 |
| BREGMAN, MICHAEL | MESA, AZ | LIAC | Addiction (Substance Use Disorder) Counselor | 09/16/2026 |
| BREIER, CHRISTOPHER | FLINT, MI | LPC | Counselor | 07/30/2021 |
| BREINER, EITA | LAKEWOOD, NJ | - | BCBA | 09/22/2026 |
| BREINHOLT, ADELINE | FORT WORTH, TX | RBT | RBT | 09/21/2026 |
| BREMER, GRANT | BELLINGHAM, WA | - | Case Manager/Care Coordinator | 09/22/2026 |
| BRENNA MACK COUNSELING LLCORG | MIDLOTHIAN, VA | - | Mental Health Counselor | 09/23/2026 |
| BRENNEMAN, MARY | MISSION VIEJO, CA | LPCC | Professional Counselor | 09/22/2026 |
| BRENTANO, LINDEN | LOS ANGELES, CA | - | Mental Health Counselor | 07/14/2023 |
| BRESSLER, ERIC | KATY, TX | M.A | Professional Counselor | 06/18/2021 |
| BRETHAUER, MADISON | HOFFMAN ESTATES, IL | - | RBT | 09/22/2026 |
| BRETT HELLING COUNSELING PLLCORG | SPOKANE, WA | - | Clinical Social Worker | 09/22/2026 |
| BREUNIG, JENNIFER | EL CERRITO, CA | - | Clinical Social Worker | 11/18/2016 |
| BREWER, ROSEMARY | WEST BLOOMFIELD, MI | BCBA | BCBA | 05/19/2016 |
| BREWER, TERRY | ELWOOD, IN | LCSW | Clinical Social Worker | 11/15/2019 |
| BREWER, WENDE | PACE, FL | PHD, LPC, LMHC | Mental Health Counselor | 09/24/2026 |
| BREWSTER, PATRICIA | ANCHORAGE, AK | LMT, LMSW | Mental Health Counselor | 03/04/2016 |
| BRIANA BARREY MENTAL HEALTH COUNSELING, PLLCORG | ALBANY, NY | - | Mental Health Counselor | 09/24/2026 |
| BRICE, JACK | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| BRIDGE 2 SUCCESS GROUP HOME, INCORG | HIGH POINT, NC | - | Community/Behavioral Health Agency | 01/04/2024 |
| BRIDGES, JOSIE | LAKELAND, FL | RBT | RBT | 09/24/2026 |
| BRIDGEWAY COUNSELING AND ASSESSMENT CENTER LLCORG | KALAMAZOO, MI | - | Counselor | 09/22/2026 |
| BRIDGEWAY HEALTH PLLCORG | CORBIN, KY | - | Professional Counselor | 07/07/2026 |
| BRIGETTE MAAS, LLCORG | COUNCIL BLUFFS, IA | - | Clinical Social Worker | 09/21/2026 |
| BRIGGS, EBONY | OKLAHOMA CITY, OK | - | Counselor | 05/26/2011 |
| BRIGGS, KAYLA | CEDAR PARK, TX | BCBA | BCBA | 11/23/2020 |
| BRIGGS, PRESTON | ELK GROVE, CA | - | Assistant Behavior Analyst | 02/05/2026 |
| BRIGHAM, KYLA | FARMINGTON HILLS, MI | - | RBT | 04/01/2025 |
| BRIGHT BEHAVIOR THERAPY LLCORG | DEARBORN, MI | - | BCBA | 06/21/2017 |
| BRIGHT GROVE ABA LLCORG | CONCORD, NH | - | BCBA | 09/22/2026 |
| BRIGHT LIGHT INCORG | MIRAMAR, FL | - | BCBA | 11/13/2023 |
| BRIGHT SPOT PSYCHOLOGICAL SERVICES, LTDORG | BOWLING GREEN, OH | - | Mental Health Counselor | 09/21/2026 |
| BRIGHT START ABA LLCORG | CONYERS, GA | - | BCBA | 09/23/2026 |
| BRIGHT STEPS THERAPY NETWORK IL LLCORG | CHICAGO, IL | - | Speech-Language Pathologist | 05/25/2026 |
| BRIGHT, BRIANDA | WILMINGTON, NC | - | Clinical Social Worker | 09/25/2026 |
| BRIGHTER JOURNEY COUNSELING, LLCORG | ROANOKE, VA | - | Psychologist | 09/23/2026 |
| BRIGHTPATH AUTISMORG | SILVER SPRING, MD | - | BCBA | 09/21/2026 |
| BRILLAULT-KENNY, ANNA | EAGLE RIVER, AK | - | Speech-Language Pathologist | 08/30/2023 |
| BRINEGAR, SAVEA | GREENVILLE, NC | - | RBT | 06/17/2024 |
| BRINKLEY, AMBER | BALTIMORE, MD | - | RBT | 09/22/2026 |
| BRISCOE, KATERINA | LOGAN, UT | - | RBT | 09/23/2026 |
| BRITO, FELICIA | TERRYTOWN, LA | - | Counselor | 09/21/2026 |
| BRITTANY LEHMAN COUNSELING, LLCORG | LUZERNE, PA | - | Mental Health Counselor | 05/12/2026 |
| BRITTON, MELISSA | NASHVILLE, TN | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| BROADNAX, AMILHA | BATTLE CREEK, MI | - | RBT | 09/21/2026 |
| BROADWAY-BEERS, KATHERINE | FRESNO, CA | SUDCCII #9035 | Addiction (Substance Use Disorder) Counselor | 02/05/2019 |
| BROCHE RODRIGUEZ, YORDELIS | MIAMI, FL | - | RBT | 02/26/2024 |
| BROCK, BRANDY | GAINESVILLE, GA | LPC | Professional Counselor | 03/03/2025 |
| BROCKEL, AUBREY | SEATTLE, WA | - | Counselor | 09/21/2026 |
| BRODAHL, APRIL | OLYMPIA, WA | CCC-SLP | Speech-Language Pathologist | 01/26/2023 |
| BRODERICK, KIELA | NILES, IL | - | RBT | 09/22/2026 |
| BRODERICK, PATRICIA | LEXINGTON, VA | PHD, LPC | Professional Counselor | 02/21/2013 |
| BRODICH, MILLIE | NEW PORT RICHEY, FL | LMHC, NCC | Professional Counselor | 03/10/2007 |
| BRODY, JERI | HYANNIS, MA | - | Clinical Social Worker | 09/23/2026 |
| BROKAW, MATTIE | FALLS CHURCH, VA | - | Speech-Language Pathologist | 12/02/2016 |
| BRONAUGH, ANTHONY | TOLEDO, OH | MED, BCBA, COBA | BCBA | 11/21/2016 |
| BRONTE TINKEW, LEIANNA | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| BROOK, SAGE | CHARLOTTE, NC | CNM | Specialist | 10/05/2005 |
| BROOKS, CAYLAH | PEARLAND, TX | - | RBT | 09/23/2026 |
| BROOKS, CYNTHIA | KNOXVILLE, TN | BS | Case Manager/Care Coordinator | 09/23/2026 |
| BROOKS, DESTINY | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| BROOKS, KEIONA | FORT SAM HOUSTON, TX | - | Mental Health Counselor | 09/17/2021 |
| BROOKS, LYDIA | BOCA RATON, FL | - | RBT | 09/25/2026 |
| BROOKS, ROBERT | APO, AE | LCSW | Clinical Social Worker | 08/07/2008 |
| BROOKS, ZIYA | FRISCO, TX | - | RBT | 09/23/2026 |
| BROSSARD, RYA | SALEM, OR | - | Mental Health Counselor | 05/08/2025 |
| BROTHERTON, RAYA | TAHLEQUAH, OK | - | RBT | 09/24/2026 |
| BROUCHET, KRISTY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| BROUETTE-KEISER, MARISSA | CARIBOU, ME | LCPCCC | Counselor | 09/22/2026 |
| BROWDY, KHARI | UNIVERSAL CITY, CA | - | RBT | 09/21/2026 |
| BROWN CHIROPRACTIC & ASSOCIATES, LLCORG | SPARTANBURG, SC | - | Counselor | 08/06/2015 |
| BROWN VENEGAS, AMBER | DURHAM, NC | - | Mental Health Counselor | 09/25/2026 |
| BROWN-ABREGO, JERUSIA | NAPLES, FL | BCBA | BCBA | 09/09/2009 |
| BROWN-AVILLA, BRIANNA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| BROWN, ALLEN | BALTIMORE, MD | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BROWN, AMYA | PHOENIX, AZ | - | RBT | 09/21/2026 |
| BROWN, ANNORA | HYANNIS, MA | - | Case Manager/Care Coordinator | 09/25/2026 |
| BROWN, AVA | CONCORD, CA | - | RBT | 09/16/2026 |
| BROWN, BRIANA | ENFIELD, CT | LPCA | Professional Counselor | 10/27/2025 |
| BROWN, CARA | GRANTS PASS, OR | LPC | Professional Counselor | 03/23/2007 |
| BROWN, CAROLYN | HOUSTON, TX | LCSW | Clinical Social Worker | 09/22/2026 |
| BROWN, CHERYL | GRANTS PASS, OR | LPC | Mental Health Counselor | 03/25/2007 |
| BROWN, D'NEA | MOUNT LAUREL, NJ | - | RBT | 09/22/2026 |
| BROWN, GRIFFITH | MARSHALL, MI | LPC, MA | Mental Health Counselor | 07/05/2023 |
| BROWN, HANA | HOLYOKE, MA | - | Counselor | 09/26/2026 |
| BROWN, ISADORE | EUCLID, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| BROWN, JACKSON | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| BROWN, JACQUELINE | LOS ANGELES, CA | LCSW | Psychologist | 04/20/2017 |
| BROWN, KATHERINE | BOULDER, CO | MSW, SWC | Clinical Social Worker | 09/21/2026 |
| BROWN, KELLEY | OLD SAYBROOK, CT | MA, LPC, LAC | Mental Health Counselor | 06/09/2009 |
| BROWN, KELLY | CARY, NC | LCPC | Professional Counselor | 09/25/2026 |
| BROWN, LASHUNDA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BROWN, LAUREN | CHARLOTTE, NC | - | RBT | 09/21/2026 |
| BROWN, MEGAN | LAKEWOOD, CO | - | RBT | 09/21/2026 |
| BROWN, MONIQUE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| BROWN, NATALIE | GREENWOOD VILLAGE, CO | LPCC | Professional Counselor | 07/27/2023 |
| BROWN, NAY'LISE | JUNCTION CITY, KS | - | RBT | 09/24/2026 |
| BROWN, PEYTON | HUNTSVILLE, AL | RBT | RBT | 09/23/2026 |
| BROWN, QIARRA | LOGANVILLE, GA | - | RBT | 09/24/2026 |
| BROWN, QUINCY | THIBODAUX, LA | - | Counselor | 12/05/2024 |
| BROWN, SAMONA | TUCSON, AZ | BCBA | BCBA | 10/24/2019 |
| BROWN, SAMONE | SAN DIEGO, CA | - | Mental Health Counselor | 09/22/2026 |
| BROWN, SARAH | MILWAUKIE, OR | CADC | Mental Health Counselor | 08/13/2013 |
| BROWN, TAMBRIS | PLYMOUTH, MI | - | RBT | 09/24/2026 |
| BROWN, TAMEIA | CLARKSVILLE, IN | - | BCBA | 01/30/2025 |
| BROWN, TANYA | GAINESVILLE, FL | - | RBT | 09/23/2026 |
| BROWN, TERRELL | WICHITA FALLS, TX | - | Clinical Social Worker | 08/04/2026 |
| BROWN, THEODORE | LOS ANGELES, CA | - | Clinical Social Worker | 09/15/2016 |
| BROWN, THOMASINA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| BROWN, ZOE | CHANDLER, AZ | - | Case Manager/Care Coordinator | 06/18/2025 |
| BROWNELL, TIMOTHY | PRESTONSBURG, KY | - | Mental Health Counselor | 09/22/2026 |
| BROWNFIELD, BRENNEN | MONUMENT, CO | - | RBT | 09/21/2026 |
| BROWNIE, KADEN | ELK GROVE, CA | - | RBT | 09/24/2026 |
| BROWNING, ALICE | BRANDON, FL | RBT | BCBA | 04/03/2024 |
| BROWNLEE, ELAYJAH | HAYWARD, CA | - | Assistant Behavior Analyst | 09/21/2026 |
| BRUCE, DANIEL | SUSANVILLE, CA | - | Case Manager/Care Coordinator | 01/08/2008 |
| BRUMFIELD, WILLOW | DOTHAN, AL | - | RBT | 09/22/2026 |
| BRUMMET-PETERSON, CATHERINE | PRESCOTT, AZ | LCSW-11031 | Clinical Social Worker | 09/25/2026 |
| BRUMSKINE, DELARUELLE | MARIETTA, GA | LCSW | Clinical Social Worker | 05/06/2025 |
| BRUNO, ASHLYN | MCKEESPORT, PA | - | Case Manager/Care Coordinator | 09/21/2026 |
| BRUNSON, JAZMYNE | JACKSONVILLE, FL | - | Clinical Social Worker | 09/24/2026 |
| BRUSHY CREEK EMERGENCY PHYSICIANS PLLCORG | ROUND ROCK, TX | - | Addiction (Substance Use Disorder) Counselor | 11/04/2019 |
| BRUTTON, ITIANA | POOLER, GA | - | RBT | 03/31/2025 |
| BRYAN MEDICAL CENTERORG | LINCOLN, NE | - | Professional Counselor | 01/22/2007 |
| BRYANT, ARIZMA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| BRYANT, CHRISTOPHER | CONCORD, CA | - | RBT | 10/13/2025 |
| BRYANT, CYNTHIA | CHICAGO, IL | - | Mental Health Counselor | 09/21/2026 |
| BRYANT, KEMYA | KILLEEN, TX | - | RBT | 09/25/2026 |
| BRYANT, LEINEY GRACE | GREENVILLE, SC | - | Counselor | 09/24/2026 |
| BRYANT, MADELINE | PISGAH FOREST, NC | LCSW | Clinical Social Worker | 01/02/2025 |
| BRYANT, MEGHAN | FORT CARSON, CO | LCSW | Clinical Social Worker | 01/31/2017 |
| BRYCE LIBBY LLCORG | LEWISTON, ME | - | Clinical Social Worker | 09/22/2026 |
| BRYNEXA MEDICAL BILLING LLCORG | GREENWOOD, IN | - | Clinic/Center | 09/01/2026 |
| BRYSON, MEGAN | SACRAMENTO, CA | ASW | Mental Health Counselor | 09/23/2026 |
| BRYSON, TYIKEL | GREENVILLE, SC | RBT | RBT | 09/21/2026 |
| BRZEZINSKI, MARIE | WILMETTE, IL | LPC | Professional Counselor | 09/17/2026 |
| BUCHANAN, LAUREL | AMERICUS, GA | - | BCBA | 10/19/2020 |
| BUCHER, KATELYN | PITTSBURGH, PA | - | Mental Health Counselor | 09/24/2026 |
| BUCHER, KRISTIN | THIENSVILLE, WI | - | Clinical Social Worker | 09/26/2026 |
| BUCK, KAYLA | WOODVILLE, WI | MS,LPC, | Mental Health Counselor | 04/11/2007 |
| BUCK, NAJAH | CHICAGO, IL | - | Professional Counselor | 05/27/2024 |
| BUCK, PATRICIA | NEWARK, DE | - | Clinical Social Worker | 09/22/2026 |
| BUCK, PAULA | CORVALLIS, OR | CRM, HCW, CADC-R | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BUCKHANAN, HAILEY | SPRING, TX | - | RBT | 09/22/2026 |
| BUCKINGHAM, VONDRA | AUSTIN, MN | - | RBT | 09/22/2026 |
| BUCKLEY, KEI-ANDRA | OAKLAND PARK, FL | - | RBT | 09/23/2026 |
| BUCKLEY, MALIK | COVINA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| BUCKMAN, LCSW-C, JACQUELYN | TOWSON, MD | LCSW-C | Clinical Social Worker | 09/21/2026 |
| BUCKNER, ARLIA | SHERMAN OAKS, CA | - | RBT | 09/25/2026 |
| BUDDNER, SARA | PALM COAST, FL | - | RBT | 09/23/2026 |
| BUELL, ANGELA | BLOOMINGTON, MN | LICSW | Clinical Social Worker | 05/13/2019 |
| BUENAVISTA, FRENNESY | LOS ANGELES, CA | - | Assistant Behavior Analyst | 09/24/2026 |
| BUENO, FABIAN | TOMS RIVER, NJ | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BUENO, MARYANN | RED BLUFF, CA | - | Mental Health Counselor | 09/24/2026 |
| BUERGER, TIMOTHY | MAGNOLIA, TX | - | RBT | 09/23/2026 |
| BUETTNER, JENNA | GERMANTOWN, WI | MSW, APSW | Clinical Social Worker | 05/29/2024 |
| BUGARIN, MEGAN | KANSAS CITY, MO | PLPC | Mental Health Counselor | 09/21/2026 |
| BUGG, BRANDI | TOPEKA, KS | - | Clinical Social Worker | 01/21/2022 |
| BUI, SAO KHUE | SAN JOSE, CA | - | RBT | 09/20/2024 |
| BUIE, LEILA | VANCOUVER, WA | - | RBT | 09/23/2026 |
| BUILDING POTENTIALS LLCORG | KENOSHA, WI | - | Community/Behavioral Health Agency | 09/24/2026 |
| BUISKOOL, MIKAYLA | OTSEGO, MI | LLMSW | Clinical Social Worker | 06/17/2024 |
| BUISSERETH, DAVIEON | NEWTON, MA | - | RBT | 09/22/2026 |
| BUJALSKI, AUBREY | CELINA, OH | - | Case Manager/Care Coordinator | 06/03/2025 |
| BUKHANOV, IRINA | BROOKLYN, NY | - | Mental Health Counselor | 09/22/2026 |
| BULKO, MARIANA | BRONX, NY | - | Speech-Language Pathologist | 06/03/2025 |
| BULLARD, LESTER | DANVILLE, VA | LCSW | Clinical Social Worker | 09/19/2026 |
| BULLER, EVA | NOVI, MI | - | RBT | 09/22/2026 |
| BULLIS, SCARLETT | COSTA MESA, CA | - | RBT | 09/21/2026 |
| BUMGARNER, CONSTANCE | CHARLOTTE, NC | LCSW-A | Clinical Social Worker | 09/23/2026 |
| BUNGART, BARBARA | CENTREVILLE, MI | MA LPC MITS | Professional Counselor | 07/26/2012 |
| BUONAVOLONTA, LEA | CANFIELD, OH | - | Mental Health Counselor | 09/23/2026 |
| BURAN, BENJAMIN | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| BURBIDGE, SAYDEE | ST GEORGE, UT | - | RBT | 09/23/2026 |
| BURCH, CARLOS | HUNTERSVILLE, NC | - | RBT | 09/23/2026 |
| BURCHETTE, CHRISTA | NORTH WILKESBORO, NC | BCBA | BCBA | 10/11/2022 |
| BURDETTE, EMILY | OLYMPIA, WA | M.S., LMFT | Mental Health Counselor | 10/20/2022 |
| BURGE, TIMOTHY | CLEVELAND HEIGHTS, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| BURGESS, CATHERINE | FAIRFAX, VA | RESIDENT COUNSELOR | Counselor | 05/16/2023 |
| BURGESS, GENEVA | FORT WAYNE, IN | - | RBT | 09/21/2026 |
| BURGESS, GLENN | WESTBURY, NY | - | Specialist | 09/23/2026 |
| BURGESS, TIARA | ALEXANDRIA, LA | - | RBT | 09/23/2026 |
| BURGOS, CESAR | MIAMI, FL | - | Mental Health Counselor | 08/30/2023 |
| BURGOS, SAMANTHA | CANTON, OH | CT | Counselor | 04/03/2019 |
| BURKE, ALANA | MARION, MA | M.S.W | Clinical Social Worker | 05/17/2007 |
| BURKE, DIANA | SACRAMENTO, CA | - | RBT | 09/22/2026 |
| BURKE, DYLAN | NORTHGLENN, CO | - | Addiction (Substance Use Disorder) Counselor | 06/07/2024 |
| BURKE, MADISON | BENTONVILLE, AR | - | BCBA | 09/25/2026 |
| BURKE, RILEY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 06/17/2026 |
| BURKINS, RONALD | SAN DIEGO, CA | APCC | Mental Health Counselor | 09/24/2026 |
| BURKS, MYA | CHESAPEAKE, VA | - | RBT | 09/23/2026 |
| BURLESON, HEATHER | SHELBY TWP, MI | - | BCBA | 09/02/2021 |
| BURNA, EMA | MILFORD, MA | LMHC | Mental Health Counselor | 01/02/2024 |
| BURNELL, RHONDA | HARKER HEIGHTS, TX | LPC-S, CCTP | Counselor | 03/28/2014 |
| BURNETT, QUEEN | MCKINNEY, TX | LPC | Counselor | 09/22/2026 |
| BURNETTE, TANYA | SENECA, SC | PA | Specialist | 02/07/2007 |
| BURNS, JEAN | KALAMAZOO, MI | MSW | Clinical Social Worker | 04/16/2007 |
| BURNS, JENNIFER | ANCHORAGE, AK | - | Day Training/Habilitation Specialist | 10/05/2023 |
| BURNS, KAMERON | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/16/2026 |
| BURNSIDE, JANICE | CLARKSVILLE, AR | ADC, CS, LAADAC | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| BURR, VICTORIA | CHATTANOOGA, TN | SLP-CCC | Speech-Language Pathologist | 09/24/2026 |
| BURRELL-JACKSON, CAROL | OCALA, FL | PH.D., MSW, LMSW | Clinical Social Worker | 07/20/2011 |
| BURROUGHS HOUSTON, FRANCES | FALL RIVER, MA | MA CMHC, LADC1 | Addiction (Substance Use Disorder) Counselor | 05/01/2013 |
| BURROUGHS, ANGELINA | CHICAGO, IL | MA, LPC | Professional Counselor | 09/21/2026 |
| BURTON, JERUSHA | MONTGOMERY, AL | - | Professional Counselor | 09/26/2026 |
| BURTON, MARISA | PLANO, TX | LPC | Mental Health Counselor | 03/25/2024 |
| BURTON, MYRA | GRAND RAPIDS, MI | - | Clinical Social Worker | 09/24/2026 |
| BURTON, SENAIYE | CHARLOTTE, NC | RBT | RBT | 09/22/2026 |
| BURTON, XAVIERA | PAULS VALLEY, OK | - | Case Manager/Care Coordinator | 09/21/2026 |
| BURWELL, ROBERT | HENDERSON, NC | - | RBT | 09/21/2026 |
| BUSCH, WARREN | SAUGERTIES, NY | LMSW | Mental Health Counselor | 09/22/2026 |
| BUSHE, MEGAN | FITCHBURG, MA | - | RBT | 09/22/2026 |
| BUSKETT, BRONSON | SPOKANE VALLEY, WA | - | Mental Health Counselor | 03/14/2024 |
| BUSS, MEGAN | BIG LAKE, MN | MS CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| BUSSER, BUSSER | MONROE, CT | LCSW | Clinical Social Worker | 11/22/2019 |
| BUSTAMANTE, MARIA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| BUTEYN SERVICESORG | SIOUX CENTER, IA | - | Clinical Social Worker | 09/17/2026 |
| BUTLER-THOMAS, SHAUNTORA | UNIVERSAL CITY, TX | - | RBT | 09/24/2026 |
| BUTLER, CHLOE | ANKENY, IA | - | Mental Health Counselor | 09/22/2026 |
| BUTLER, GRACE | CONCORD, NC | - | BCBA | 09/16/2026 |
| BUTLER, KELLI | LAKEWOOD, WA | BCBA | BCBA | 03/05/2019 |
| BUTLER, MACEY | HUNTSVILLE, AL | RBT | BCBA | 02/14/2025 |
| BUTLER, NORMANIQUE | BATON ROUGE, LA | - | Counselor | 08/20/2026 |
| BUTLER, SANDRA | EAST LANSING, MI | LLP | Professional Counselor | 02/08/2013 |
| BUTLER, TASHA | INDEPENDENCE, OH | - | Case Manager/Care Coordinator | 02/15/2024 |
| BUTTS, BRIDGET | WINDSOR, PA | LCSW-C | Clinical Social Worker | 05/10/2019 |
| BUXANI, RACHNA | PINECREST, FL | - | Mental Health Counselor | 04/26/2017 |
| BUZBEE, KATINA | NASHVILLE, AR | - | Case Manager/Care Coordinator | 09/26/2026 |
| BWN INCORG | WALDORF, MD | - | Community/Behavioral Health Agency | 09/26/2026 |
| BYFIELD-WARREN, MADDOX | LONGVIEW, WA | - | Counselor | 09/21/2026 |
| BYRD, ESTHER | ALBUQUERQUE, NM | - | Speech-Language Pathologist | 09/24/2026 |
| BYRD, JADE | ADA, OK | - | RBT | 09/21/2026 |
| BYRD, MAICEE | DEL MAR, CA | LCSW | Clinical Social Worker | 03/22/2021 |
| C & D BEHAVIORAL HEALTH PLLCORG | LOUISVILLE, KY | - | Community/Behavioral Health Agency | 06/12/2024 |
| C MEDLEY HAYES FOUNDATIONORG | COLUMBUS, GA | - | Community/Behavioral Health Agency | 09/25/2026 |
| CABADAS, KARINA | POMONA, CA | - | BCBA | 10/25/2021 |
| CABALES, CHLOE | SAN FRANCISCO, CA | - | RBT | 09/21/2026 |
| CABBELL, JESSICA | OMAHA, NE | - | RBT | 09/21/2026 |
| CABELLO, MARIA | MIRAMAR, FL | - | RBT | 02/09/2024 |
| CABEZA, ALEJANDRA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CABRAL, ANDREA | TORRANCE, CA | - | RBT | 05/24/2021 |
| CABRAL, JESSICA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| CABRERA, BARBARA | HAZLET, NJ | MS, LAC, NCC | Professional Counselor | 09/26/2026 |
| CABRERA, MICHELLE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CABRERA, THALIA | ROYAL OAKS, CA | - | RBT | 09/21/2026 |
| CACAO, MARIE | PORTLAND, OR | L.M.F.T. | Mental Health Counselor | 04/08/2008 |
| CADDO RIVER MEDICAL CLINIC PLLCORG | GLENWOOD, AR | - | Clinic/Center | 07/10/2026 |
| CADENA, JENNIFER | SACRAMENTO, CA | - | RBT | 09/21/2026 |
| CADET, MARIA ELENA | WEST HAVERSTRAW, NY | LMHC | Mental Health Counselor | 01/06/2014 |
| CADLAON, MARK | LAKEWOOD, CO | LPCC | Mental Health Counselor | 05/26/2022 |
| CAGE, DONEISHA | METAIRIE, LA | - | RBT | 09/24/2026 |
| CAGE, REIONA | MONROVIA, CA | - | RBT | 02/14/2022 |
| CAIN, ANN | CHICAGO, IL | LSCSW | Clinical Social Worker | 09/12/2021 |
| CAIN, ESSENCE | GRANADA HILLS, CA | - | RBT | 09/21/2026 |
| CAINZOS, VANESSA | MIAMI, FL | MASTERS, BCBA | BCBA | 09/24/2026 |
| CAL CONTINUUM OF CAREORG | REDDING, CA | - | Addiction (Substance Use Disorder) Counselor | 12/26/2023 |
| CALA, MARIA | MIRAMAR, FL | - | RBT | 09/21/2026 |
| CALDER GLEN BEHAVIORAL HEALTH, PLLCORG | MEMPHIS, TN | - | Professional Counselor | 09/11/2026 |
| CALDERA, ANNETTE | SANTA ANA, CA | - | Addiction (Substance Use Disorder) Counselor | 06/21/2022 |
| CALDERON, ALEXANDRA | GARDENA, CA | - | Day Training/Habilitation Specialist | 09/25/2026 |
| CALDERON, TANYA | MODESTO, CA | - | RBT | 09/22/2026 |
| CALDON, JAMES | SAN BERNARDINO, CA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| CALDWELL, A. G. | MORGANTOWN, IN | LCSW | Clinical Social Worker | 05/18/2007 |
| CALDWELL, HEATHER | ANCHORAGE, AK | LPC | Mental Health Counselor | 03/07/2020 |
| CALDWELL, SHAYLEE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| CALDWELL, STACEY | DETROIT, MI | - | Counselor | 09/21/2026 |
| CALEF-BORING, ELIZABETH | BRIDGEPORT, WV | LCSW | Clinical Social Worker | 10/17/2012 |
| CALERO VITON, ARIANNA | MIAMI, FL | PMHNP-BC | RBT | 03/26/2021 |
| CALHOON, EMILY | ROSEMOUNT, MN | MA | Professional Counselor | 05/31/2024 |
| CALHOON, HEATHER | SOUTH PASADENA, CA | - | Psychologist | 09/12/2017 |
| CALHOUN, ELIZA | GERMANTOWN, MD | MSW | Mental Health Counselor | 04/11/2008 |
| CALHOUN, KAI | GARDEN CITY, MI | - | RBT | 11/03/2025 |
| CALHOUN, KAYN | VICTORVILLE, CA | - | Day Training/Habilitation Specialist | 07/21/2026 |
| CALHOUN, SARAH | SCHERTZ, TX | LPC | Mental Health Counselor | 03/19/2024 |
| CALIFORNIA HEALTH COLLABORATIVEORG | SACRAMENTO, CA | - | Mental Health Counselor | 08/16/2011 |
| CALIFORNIA RENEWAL LIVING FOUDNATIONORG | MORGAN HILL, CA | - | Case Management Agency | 09/25/2026 |
| CALIX-RIVERA, REICHELLE | DEERFIELD BEACH, FL | - | RBT | 04/20/2026 |
| CALIXTE-CIVIL, PATRICIA | TAMPA, FL | PHD | Psychologist | 09/23/2024 |
| CALIXTO, KARLA | TACOMA, WA | - | Clinical Social Worker | 09/22/2026 |
| CALLENDER, ASHLEY | ALLENTOWN, PA | - | RBT | 01/12/2016 |
| CALLEY, KORBY | WAILUKU, HI | MA, MFT-I, LPC-A | Counselor | 10/14/2024 |
| CALLISTE, RHONDA | BURLINGTON, NJ | - | Mental Health Counselor | 10/16/2024 |
| CALLOWAY, SHARLA | PENSACOLA, FL | LCSW, CNS - LDN | Clinical Social Worker | 10/19/2020 |
| CALLPANI, VENETA | NEW YORK, NY | LMHC | Mental Health Counselor | 09/23/2026 |
| CALM WITHIN COUNSELINGORG | ONSTED, MI | - | Mental Health Counselor | 09/21/2026 |
| CALO, JENNIFER | CLEVELAND, OH | - | Case Manager/Care Coordinator | 08/30/2025 |
| CALOVETO, NICOLO | NAPERVILLE, IL | - | Professional Counselor | 07/28/2015 |
| CAMACHO, MONICA | ORLANDO, FL | MA, LMHC | Counselor | 06/26/2024 |
| CAMARENA, ELIZABETH | FRESNO, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| CAMARILLO, RAFAEL | PORTLAND, OR | - | Mental Health Counselor | 02/23/2024 |
| CAMEJO GOMEZ, IDALIA | CAPE CORAL, FL | - | RBT | 09/23/2026 |
| CAMEN, DANIELLA | MAITLAND, FL | RBT | RBT | 06/23/2026 |
| CAMERON, SHAN'TRESE | NEW YORK, NY | LCSW | Clinical Social Worker | 10/29/2025 |
| CAMMIRE, AUTUMN | BROOKLYN, NY | - | RBT | 09/22/2026 |
| CAMP, SARAH | MANCHESTER, TN | LCSW | Case Manager/Care Coordinator | 08/27/2012 |
| CAMPBELL, AMBER | LAYTON, UT | - | Clinical Social Worker | 09/23/2026 |
| CAMPBELL, BRIANNA | COLUMBIA, MD | - | RBT | 09/22/2026 |
| CAMPBELL, CARDEAN | DERBY, CT | - | RBT | 09/26/2026 |
| CAMPBELL, DEANNA | MCALESTER, OK | LBP, RN | Mental Health Counselor | 04/01/2009 |
| CAMPBELL, EMILY | AUSTIN, TX | LPC ASSOCIATE | Professional Counselor | 09/21/2026 |
| CAMPBELL, MARJORY | EVANS, GA | - | RBT | 11/03/2025 |
| CAMPBELL, ROSEZINA | MILWAUKEE, WI | OTHER | Mental Health Counselor | 05/09/2019 |
| CAMPECHANO ROLDAN, ISSAC | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CAMPO, JORDYN | COVINGTON, LA | - | BCBA | 07/09/2025 |
| CANAL, CARLEE | MONROE, LA | BCBA, LBA | BCBA | 09/24/2026 |
| CANALDA, EILEEN | MIAMI, FL | - | BCBA | 09/21/2026 |
| CANCEL, MARIA | SPRINGFIELD, MA | LADC | Addiction (Substance Use Disorder) Counselor | 08/26/2026 |
| CANCIO CARDONA, LETICIA | CAMUY, PR | MSW | Clinical Social Worker | 09/21/2026 |
| CANELA, IRMA | BRENTWOOD, CA | BCBA | BCBA | 03/30/2020 |
| CANESSA, SANDRA | SANTA FE, NM | - | Counselor | 05/01/2026 |
| CANFIELD, LANDRY | OLATHE, KS | T-LPC | Mental Health Counselor | 09/23/2026 |
| CANNENTA FOUNDATION INCORG | DALLAS, TX | - | Clinical Social Worker | 09/21/2026 |
| CANNON, CASSANDRA | SIOUX CITY, IA | - | Clinical Social Worker | 09/25/2026 |
| CANNON, CHERYL | TOWSON, MD | LCSW-C | Clinical Social Worker | 03/01/2023 |
| CANNON, CIARA | LIMA, OH | CDCA | Case Management Agency | 12/21/2016 |
| CANNON, DAVID | RATHDRUM, ID | LPC | Mental Health Counselor | 08/28/2023 |
| CANNON, ELLA | GREENWICH, CT | LCSW | Clinical Social Worker | 05/12/2025 |
| CANNON, MARY | HOUSTON, TX | LCSW | Clinical Social Worker | 02/28/2019 |
| CANNON, OLIVER | LAS VEGAS, NV | 22 YEARS PROF EXPERT | Community/Behavioral Health Agency | 09/25/2026 |
| CANNON, SHEILA | POPLAR BLUFF, MO | LPC | Professional Counselor | 03/26/2019 |
| CANO CERVANTES, KIMBERLY | LAS VEGAS, NV | - | RBT | 09/22/2026 |
| CANO, CYNTHIA | MCALLEN, TX | MS CCC SLP | Speech-Language Pathologist | 05/22/2007 |
| CANO, JASEY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| CANO, JENNIFER | TARZANA, CA | - | Psychologist | 04/24/2024 |
| CANTON, ALEXA-ELLEN | GARNER, NC | - | RBT | 09/22/2026 |
| CANTRELL VILLASENOR, ISAAC SALVADOR | EL CAJON, CA | - | RBT | 09/21/2026 |
| CANTU, ISAIAH | LOS ANGELES, CA | - | RBT | 09/21/2026 |
| CANTU, JAYLEE | CLOVIS, CA | - | RBT | 09/25/2026 |
| CANUP, MAKALA | SPARTANBURG, SC | - | RBT | 09/24/2026 |
| CANVAS PSYCHOLOGICAL P.C.ORG | NEW YORK, NY | - | Psychologist | 09/22/2026 |
| CAPATINA, LIVIANA | DES PLAINES, IL | - | RBT | 09/24/2026 |
| CAPITAL AREA HUMAN SERVICES DISTRICTORG | BATON ROUGE, LA | - | Community/Behavioral Health Agency | 09/23/2026 |
| CAPODICASA, ROSANNA | DEERFIELD BEACH, FL | - | RBT | 09/23/2026 |
| CAPP, JASON | LAKEWOOD, CO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| CAPRISTO, DEISE | SANTA BARBARA, CA | LCSW | Clinical Social Worker | 09/08/2008 |
| CAPSTONE WELLNESS CENTERORG | SPARTA, NC | - | Professional Counselor | 02/10/2014 |
| CAPULONG, ALJORIE FLOR | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CARABALLO SALAS, SARAHI | ORLANDO, FL | - | RBT | 09/26/2026 |
| CARABALLO, ESTELIS | BRONX, NY | LMSW | Clinical Social Worker | 01/04/2021 |
| CARATACHEA, GUADALUPE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CARBAJAL, MARLEEN | GOLETA, CA | - | BCBA | 09/23/2026 |
| CARBAJAL, SCOTT | LAKE CHARLES, LA | MD | Specialist | 07/09/2005 |
| CARDENAS BLANCO, MARIA | BERKELEY, CA | - | Psychologist | 06/22/2020 |
| CARDENAS, ALEXANDRA | RIVERBANK, CA | - | RBT | 09/21/2026 |
| CARDENAS, ISABELLA | COVINA, CA | BS | RBT | 09/23/2026 |
| CARDENAS, SAUL | CRENSHAW, CA | - | RBT | 09/21/2026 |
| CARDENAS, VANESSA | DOWNEY, CA | - | RBT | 05/12/2025 |
| CARDENAS, VIVIANA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CARDINALE, OLIVIA | AKRON, OH | CDCA | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| CARDONA-DIAZ, LIMARI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CARE SERVICES SUPPORTS MANAGEMENTORG | WILMINGTON, DE | - | Case Manager/Care Coordinator | 09/24/2026 |
| CARE SERVICES SUPPORTS MANAGEMENTORG | MOUNT LAUREL, NJ | - | Counselor | 09/24/2026 |
| CAREY, KA'DIRA | JBPHH, HI | LCSW | Case Management Agency | 06/19/2015 |
| CAREY, MARIE | MORGANTON, NC | LCMHC | Professional Counselor | 01/05/2016 |
| CARGILE, RAZIYA | PITTSBURGH, PA | - | RBT | 09/23/2026 |
| CARING ABA SERVICES INCORG | SAINT CLOUD, FL | - | BCBA | 09/17/2024 |
| CARLSON, EDEN | PROVO, UT | - | RBT | 09/21/2026 |
| CARLTON, CIDNEY | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| CARLTON, HANK | ATHENS, GA | - | Mental Health Counselor | 09/21/2026 |
| CARLYLE, RILEY | SAN ANGELO, TX | RBT | RBT | 09/22/2026 |
| CARLYON COUNSELING LLCORG | BENTON, PA | - | Professional Counselor | 09/23/2026 |
| CARMELITANO, JASMINE | MIDDLETOWN, NY | LMHC | Mental Health Counselor | 08/15/2026 |
| CARMICHAEL, KAITLIN | TAMPA, FL | - | Speech-Language Pathologist | 09/23/2026 |
| CARNEY, AMY | LAFAYETTE, IN | - | Speech-Language Pathologist | 09/23/2026 |
| CARNEY, ELIZABETH | BOHEMIA, NY | - | BCBA | 02/24/2020 |
| CARNEY, YAN | RIVERSIDE, CA | LCSW | Clinical Social Worker | 01/23/2019 |
| CAROL, JESSICA | PORT TOWNSEND, WA | - | Mental Health Counselor | 08/25/2026 |
| CAROLAN, KARI | HONOLULU, HI | - | Mental Health Counselor | 09/22/2026 |
| CAROLYN ASTIN, LLCORG | BOZEMAN, MT | - | Clinical Social Worker | 09/22/2026 |
| CARON, DEANNE | TACOMA, WA | MA, LMHC | Mental Health Counselor | 04/16/2007 |
| CARPENTER, ALEXIS | MURFREESBORO, TN | - | RBT | 09/21/2026 |
| CARPENTER, DAKOTA | NEW PALTZ, NY | - | Clinical Social Worker | 09/23/2026 |
| CARPIO CASASOLA, JORGE | VAN NUYS, CA | - | RBT | 09/24/2026 |
| CARR, OLIVIA | WILMINGTON, NC | - | RBT | 09/23/2026 |
| CARR, TATYIANNA | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| CARRANZA, CATALINA | CHULA VISTA, CA | - | RBT | 09/21/2026 |
| CARRANZA, EMMA | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| CARRAWAY, LAURA | GREENSBORO, NC | LCAS | Addiction (Substance Use Disorder) Counselor | 03/26/2009 |
| CARRAWAY, LENAI | KENNESAW, GA | - | Counselor | 09/23/2025 |
| CARRICO COUNSELING LLCORG | LOUISVILLE, KY | - | Clinical Social Worker | 08/25/2026 |
| CARRILLO, ADRIANA | SAN ANTONIO, TX | LPC | Professional Counselor | 10/22/2019 |
| CARRILLO, ANTONIO | CAMARILLO, CA | - | RBT | 09/25/2026 |
| CARRILLO, AVIANNA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| CARRILLO, CITLALY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| CARRILLO, GABRIEL | EL PASO, TX | - | Clinical Social Worker | 09/24/2026 |
| CARRILLO, JOHNNY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| CARRILLO, MACKENZIE | SAN CLEMENTE, CA | RBT | RBT | 09/24/2026 |
| CARRILLO, ROBIN | ORLANDO, FL | LMHC | Mental Health Counselor | 09/24/2026 |
| CARRILLO, TAYLOR | BOONE, NC | LCSW-A | Clinical Social Worker | 09/22/2026 |
| CARRISON, CEARA | WEST LAFAYETTE, IN | - | RBT | 09/22/2026 |
| CARROLL, BRYAN | HOUSTON, TX | - | Professional Counselor | 09/23/2026 |
| CARROLL, CLARA | MIDDLEBURY, VT | - | Mental Health Counselor | 09/24/2026 |
| CARROLL, MATTHEW | RENO, NV | - | BCBA | 01/28/2022 |
| CARROLL, SARAH | LITTLETON, CO | - | Mental Health Counselor | 09/25/2026 |
| CARSON, ALONDRA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CARSON, DANIELLE | HAYES, VA | LPC, LMFT | Professional Counselor | 01/29/2014 |
| CARTAYA RODRIGUEZ, IRENE | MIAMI, FL | - | RBT | 11/28/2023 |
| CARTER LEARNING ADVENTURE LLCORG | THE WOODLANDS, TX | - | BCBA | 02/27/2025 |
| CARTER, ANGEL | PHOENIX, AZ | - | Community/Behavioral Health Agency | 05/01/2025 |
| CARTER, BENEALIA | MECHANICSVILLE, VA | LPC, LCPC, LMHC, NCC | Professional Counselor | 12/30/2009 |
| CARTER, CATHERINE | CHATTANOOGA, TN | LCSW | Clinical Social Worker | 04/25/2018 |
| CARTER, EMILY | COLUMBUS, OH | LPC | Counselor | 06/03/2025 |
| CARTER, JEDAUN | SAN DIEGO, CA | - | Mental Health Counselor | 09/23/2026 |
| CARTER, KAREN | NILES, OH | BSW | Clinical Social Worker | 09/26/2026 |
| CARTER, NICHOLAS | FLAGSTAFF, AZ | MA, BCBA, LBA | BCBA | 06/18/2019 |
| CARTLEDGE, CHRISTINA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| CARUSO, NYBELLE | OREGON CITY, OR | - | Clinical Social Worker | 10/05/2015 |
| CARVAJAL CABRERA, NAYALI | MIAMI, FL | - | BCBA | 01/20/2023 |
| CARVALHO, LEVI | BOSTON, MA | MSW | Clinical Social Worker | 09/21/2026 |
| CARVALHO, STEPHANE | NORWOOD, MA | MS | Mental Health Counselor | 05/24/2022 |
| CARVALHO, TYLER | DEERFIELD BEACH, FL | - | RBT | 09/21/2026 |
| CARVEY, MARY | RIO RANCHO, NM | LMHC | Mental Health Counselor | 08/23/2024 |
| CARY, GRAYSON | OSWEGO, NY | - | Speech-Language Pathologist | 09/24/2026 |
| CARZON, ABIGAIL | SAN JOSE, CA | - | RBT | 07/17/2026 |
| CASA PACIFICA CENTERS FOR CHILDREN AND FAMILIESORG | CAMARILLO, CA | - | Community/Behavioral Health Agency | 03/22/2007 |
| CASALE, TONI | COOLIDGE, AZ | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| CASAS BLANCO, NATACHA | MIAMI, FL | RBT | RBT | 07/03/2020 |
| CASBY, PHILLIP | NEWARK, OH | LICDC-CS, SAP | Addiction (Substance Use Disorder) Counselor | 04/06/2016 |
| CASCADE COAST NATURAL HEALTHORG | TUMWATER, WA | - | Clinic/Center | 05/12/2022 |
| CASEY, ANGELINA | RIVERSIDE, CA | - | RBT | 08/22/2023 |
| CASILLAS GONZALEZ, RUTH | SANTA CRUZ, CA | - | RBT | 09/22/2026 |
| CASILLAS, CAYDEN | HACIENDA HEIGHTS, CA | - | RBT | 09/22/2026 |
| CASO, SCOTT | HERMOSA BEACH, CA | - | Clinical Social Worker | 09/23/2026 |
| CASPER, COLIN | LAKELAND, FL | - | Mental Health Counselor | 03/08/2017 |
| CASSELL, FRANCES | NEW YORK, NY | MHC LP | Mental Health Counselor | 09/24/2026 |
| CASSIDY, JESSICA | SAINT LOUIS, MO | - | Speech-Language Pathologist | 05/31/2018 |
| CASSIE BROWN COUNSELINGORG | VALDESE, NC | - | Mental Health Counselor | 09/21/2026 |
| CASTANEDA, AMALIA | VALENCIA, CA | - | Professional Counselor | 05/15/2023 |
| CASTANEDA, FERNANDO | TORRANCE, CA | - | RBT | 09/21/2026 |
| CASTANEDA, GABRIELA | SAN DIEGO, CA | PSY.D | Psychologist | 11/01/2021 |
| CASTANON, ERENDIRA | WHEATON, IL | BCBA | RBT | 07/27/2022 |
| CASTEEN, GRACE | RALEIGH, NC | - | Mental Health Counselor | 09/23/2026 |
| CASTELLANOS, ALYSSA | FRESNO, CA | - | RBT | 09/21/2026 |
| CASTILLO JAMES, ANA | CHICAGO, IL | - | Clinical Social Worker | 09/23/2026 |
| CASTILLO ROMERO, BRENDA | MELBOURNE, FL | - | RBT | 09/24/2026 |
| CASTILLO, ABIGAIL | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CASTILLO, ANNA | ALLEN PARK, MI | - | RBT | 10/15/2025 |
| CASTILLO, EHIMY | TORRANCE, CA | - | RBT | 09/21/2026 |
| CASTILLO, KARLY | MEDIA, PA | MA | Mental Health Counselor | 09/22/2026 |
| CASTILLO, LACHELLE | ROUND ROCK, TX | - | RBT | 09/21/2026 |
| CASTILLO, STEPHANIE | CHATSWORTH, CA | - | Mental Health Counselor | 03/29/2019 |
| CASTILLO, VANESSA | FRESNO, CA | - | Clinical Social Worker | 04/05/2022 |
| CASTLE FAMILY HEALTH CENTERS INC.ORG | ATWATER, CA | - | Clinic/Center | 09/23/2026 |
| CASTO, CHARITY | GALLIPOLIS, OH | CDCA | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| CASTORENA, JAYSON | SHAWNEE, OK | - | Mental Health Counselor | 09/25/2026 |
| CASTRO BAUTISTA, CRUISTEN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CASTRO-LEY, MABEL | EL CENTRO, CA | - | Addiction (Substance Use Disorder) Counselor | 04/28/2020 |
| CASTRO, ELENA | AZUSA, CA | - | RBT | 09/22/2026 |
| CASTRO, GEORGETTE | HOLLYWOOD, FL | - | Mental Health Counselor | 09/23/2026 |
| CASTRO, MARIBEL | GARDEN GROVE, CA | - | RBT | 04/24/2023 |
| CASTRO, QUENTIN | RIVERBANK, CA | - | RBT | 09/21/2026 |
| CATALAN, ANDREA | SACRAMENTO, CA | - | RBT | 10/26/2018 |
| CATALANO, MICHAEL | STATEN ISLAND, NY | LMSW | BCBA | 09/25/2026 |
| CATCH & RELEASE COUNSELINGORG | HAYDEN, ID | - | Counselor | 09/24/2026 |
| CATHCART, MCKENZIE | CHARLOTTE, NC | MS | BCBA | 05/30/2024 |
| CATHERINE REAMES PSYCHOTHERAPYORG | MISSOULA, MT | - | Professional Counselor | 08/26/2026 |
| CAUDLE, STEPHANIE | GREENSBORO, NC | - | Clinical Social Worker | 09/23/2026 |
| CAVARLEZ, AMBER | SAN FRANCISCO, CA | MSN, RN | Counselor | 02/02/2015 |
| CAVENDER, SAMANTHA | CLARKSTON, MI | - | BCBA | 09/18/2019 |
| CAVER, JOSEPH | MILWAUKIE, OR | PCA | Mental Health Counselor | 09/22/2026 |
| CAWTHON, SHELBY | SMYRNA, TN | - | RBT | 09/25/2026 |
| CAZA, DUSTIN | TROY, MI | - | Clinical Social Worker | 05/08/2020 |
| CEARNAL, SHELLVIA | ANGIER, NC | LMSW, LCSW-A | Clinical Social Worker | 07/23/2025 |
| CECCI, ELIZABETH | KENNESAW, GA | BCBA | BCBA | 09/23/2026 |
| CECIL, MEGAN | CENTRALIA, IL | - | Counselor | 09/25/2026 |
| CEDENO, LIZBEL | BRONX, NY | LCSW-R | Clinical Social Worker | 09/19/2026 |
| CEDERBURG, BRIANNA | WAYNE, NE | - | Day Training/Habilitation Specialist | 09/23/2026 |
| CEJA, JOSE | WALNUT CREEK, CA | - | RBT | 09/21/2026 |
| CELESTINE, BRANDI | HOUSTON, TX | LPC | Case Manager/Care Coordinator | 04/04/2016 |
| CELIS, ANA | VALENCIA, CA | - | RBT | 09/24/2026 |
| CELLA, JOSEPH | HARRISON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| CELY ABAUNZA, BLANCA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| CENLA WELLNESS 2 LLCORG | PINEVILLE, LA | - | BCBA | 09/25/2026 |
| CENTENO SANZON, LIZETH | IDAHO FALLS, ID | BA | Case Manager/Care Coordinator | 09/23/2026 |
| CENTENO, DYLAN | WOBURN, MA | - | RBT | 09/21/2026 |
| CENTER FOR ADDICTION AND COUNSELING SERVICES, LLCORG | SALEM, OR | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| CENTER FOR SKILLS DEVELOPMENT LLCORG | BREA, CA | - | BCBA | 03/20/2024 |
| CENTER OF SERENITY LLCORG | WINTERSVILLE, OH | - | Professional Counselor | 12/07/2022 |
| CENTER POINT COMMUNITY SERVICESORG | LA MESA, CA | - | Mental Health Counselor | 09/23/2026 |
| CENTRAL WASHINGTON HORIZON COUNSELINGORG | YAKIMA, WA | - | Mental Health Counselor | 11/21/2024 |
| CEPEDA, SALVADOR | MESA, AZ | LPC | Professional Counselor | 11/10/2014 |
| CERDA BISHOP, ELENA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CERDA, ERIC | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| CERDA, KATRINA | GREENVILLE, NC | - | Speech-Language Pathologist | 03/02/2026 |
| CEREBRAL PALSY KIDS CENTER INCORG | LOUISVILLE, KY | - | Clinical Social Worker | 12/08/2006 |
| CESAR, ESTHER | QUINCY, MA | - | RBT | 09/23/2026 |
| CGS COUNSELING PLLCORG | GREENFIELD, MA | - | Mental Health Counselor | 09/26/2026 |
| CHA, MELINDA | ELK GROVE, CA | - | Assistant Behavior Analyst | 02/19/2026 |
| CHACON, HOPE | SAGINAW, MI | - | RBT | 09/21/2026 |
| CHAD-FRIEDMAN, SIMONE | NEW YORK, NY | PHD | Psychologist | 06/03/2024 |
| CHADDOCK, ABIGAIL | CHARDON, OH | - | Professional Counselor | 02/20/2025 |
| CHAE, TIFFANY | PORTLAND, OR | SLP | Speech-Language Pathologist | 09/22/2026 |
| CHAFFIN, ABIGAIL | BALCH SPRINGS, TX | - | Speech-Language Pathologist | 09/21/2026 |
| CHAISANGUANTHUM, ROSLYN | SYLMAR, CA | M.D. | Specialist | 06/07/2007 |
| CHAKEY, MEGAN | MACON, GA | MED, BCBA, LBA | BCBA | 01/31/2020 |
| CHALLAPPA, KRISHNAN | ELIZABETHTOWN, KY | M.D. | Specialist | 08/12/2005 |
| CHAMBERLAIN, JASMINE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CHAMBERLIN, LAURA | LOUISVILLE, KY | MA, LPCC, ATR-BC, NC | Professional Counselor | 01/13/2010 |
| CHAMBERS, CORETTA | LAKE CHARLES, LA | - | Case Manager/Care Coordinator | 09/23/2026 |
| CHAMBERS, DARELYN | CHICAGO, IL | - | Speech-Language Pathologist | 09/23/2026 |
| CHAMBERS, DARWIN | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| CHAMPLIN, AMBER | WEST WARWICK, RI | BA, CPRS CHW | Case Manager/Care Coordinator | 09/24/2026 |
| CHAN, ADELYNE | ELK GROVE, CA | - | RBT | 09/24/2026 |
| CHANCE, SYDNI | TAMPA, FL | - | BCBA | 06/01/2016 |
| CHANDLER, ROBERT | KENT, WA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| CHANDRA-YANG, ALEXIS | KENMORE, WA | LABA | Assistant Behavior Analyst | 05/10/2022 |
| CHANEY, TAQUIESHA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| CHANG, AVIELA | TUSTIN, CA | - | RBT | 08/22/2026 |
| CHANG, COELFINNIA | PASADENA, CA | - | RBT | 10/27/2025 |
| CHANG, MOYI | SCOTT CITY, KS | CCC-SLP | Speech-Language Pathologist | 10/14/2025 |
| CHANG, OLIVIA | MARTINEZ, CA | PH.D. | Psychologist | 03/02/2009 |
| CHANICKA, OLIVIA | DAVENPORT, FL | RBT | BCBA | 03/10/2022 |
| CHANON, LIDIA | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 02/23/2023 |
| CHAPA, SAMANTHA | SHEBOYGAN, WI | APSW | Clinical Social Worker | 06/05/2023 |
| CHAPA, SIERRA | ALBUQUERQUE, NM | - | RBT | 09/21/2026 |
| CHAPARIAN, LITIA | LA VERNE, CA | M.S., CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| CHAPIN, SARAH | BIG RAPIDS, MI | - | Speech-Language Pathologist | 09/26/2026 |
| CHAPMAN, CATHERINE | NORMAN, OK | LCSW | Clinical Social Worker | 04/23/2020 |
| CHAPMAN, DOUGLAS | PORTLAND, OR | LPC, CADCIII | Mental Health Counselor | 11/28/2006 |
| CHAPMAN, EMMA | ST GEORGE, UT | - | RBT | 09/23/2026 |
| CHAPPELL, KILISA | SOUTHFIELD, MI | - | RBT | 09/26/2026 |
| CHARAPATA, KATELYN | GRANDVILLE, MI | - | BCBA | 01/24/2022 |
| CHARBONNEAU, DENISE | YUCCA VALLEY, CA | - | Clinical Social Worker | 04/12/2019 |
| CHARBONNEAU, RAMONA | MINOT, ND | - | Case Manager/Care Coordinator | 09/25/2026 |
| CHARBONNET, RANDI | LAS VEGAS, NV | LCPC | Professional Counselor | 03/11/2016 |
| CHARI, JORDYN | KANSAS CITY, MO | - | Professional Counselor | 10/19/2023 |
| CHARISMATIC COUNSELORORG | SEAGOVILLE, TX | - | Mental Health Counselor | 09/22/2026 |
| CHARLAND, MARISSA | BOSTON, MA | - | Speech-Language Pathologist | 02/20/2024 |
| CHARLSON, BRIDGET | FAIRLAWN, OH | - | RBT | 09/21/2026 |
| CHASE, SHELBY | LAPEER, MI | - | RBT | 06/22/2017 |
| CHATMAN, DARCHELL | LAWTON, OK | - | Case Manager/Care Coordinator | 01/19/2021 |
| CHATTER NEST SPEECH THERAPY PLLCORG | YONKERS, NY | - | Speech-Language Pathologist | 04/20/2026 |
| CHAU, WINNIFRED | SUNNYVALE, CA | - | Speech-Language Pathologist | 09/24/2026 |
| CHAVARRIA, MARTHA | SALINAS, CA | - | Case Management Agency | 09/21/2026 |
| CHAVES, ISIS | ORLANDO, FL | RBT-23-318231 | Assistant Behavior Analyst | 12/21/2023 |
| CHAVEZ RODRIGUEZ, NANCY | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CHAVEZ-MARTINEZ, DARIUS | TORRANCE, CA | MSW | Clinical Social Worker | 05/02/2024 |
| CHAVEZ, ABIGAIL | FAYETTEVILLE, AR | - | Case Manager/Care Coordinator | 03/08/2023 |
| CHAVEZ, ANA | CAMPBELL, CA | - | RBT | 07/16/2026 |
| CHAVEZ, BITHIA | PHOENIX, AZ | LCSW | Clinical Social Worker | 01/20/2026 |
| CHAVEZ, CAROLINA | ALAMOSA, CO | - | Speech-Language Pathologist | 09/23/2026 |
| CHAVEZ, JESSE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CHAVEZ, JESSICA | RED BLUFF, CA | AMFT | Mental Health Counselor | 07/31/2023 |
| CHAVEZ, JOSE | VENTURA, CA | - | RBT | 09/21/2026 |
| CHAVEZ, JOZELYNE | ALBUQUERQUE, NM | - | RBT | 09/21/2026 |
| CHAVEZ, RANDY | TARZANA, CA | - | RBT | 09/22/2026 |
| CHAVIANO MARRERO, RUTH | JACKSONVILLE, FL | - | Assistant Behavior Analyst | 09/21/2026 |
| CHAVIS, FALLON | GREENVILLE, NC | - | Clinical Social Worker | 09/21/2026 |
| CHAYIM COUNSELING LLCORG | WEST LINN, OR | - | Clinical Social Worker | 12/21/2021 |
| CHEATHAM, ELEANOR | NEWNAN, GA | - | Mental Health Counselor | 05/04/2020 |
| CHEAYE, ISHA | RICHMOND, VA | - | Speech-Language Pathologist | 09/16/2024 |
| CHEEMA, GULVEEN | FRESNO, CA | LCSW | Clinical Social Worker | 01/16/2018 |
| CHEK COLLINS, JOY | PARKER, CO | - | RBT | 09/25/2026 |
| CHEKWAS, WILLIAM | HOUSTON, TX | - | RBT | 09/24/2026 |
| CHELSEA ALBAN COUNSELING, LLCORG | WEST ORANGE, NJ | - | Mental Health Counselor | 08/04/2026 |
| CHEN, CHEREY | NEWARK, CA | - | RBT | 09/18/2025 |
| CHEN, XINYU | PENFIELD, NY | - | Counselor | 09/25/2026 |
| CHENG, ELYSSA | BOISE, ID | - | RBT | 09/23/2026 |
| CHENG, ERIC | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| CHEONG, KIRSTEN | RANCHO CUCAMONGA, CA | - | Addiction (Substance Use Disorder) Counselor | 01/05/2016 |
| CHERRY, JEREMY | BOWLING GREEN, OH | LPCC-S, LMFT | Professional Counselor | 11/20/2008 |
| CHERRY, TAWANA | MC LEANSVILLE, NC | MSW, LCSWA | Clinical Social Worker | 09/25/2026 |
| CHERY, ALAN | NEW BRITAIN, CT | - | Clinical Social Worker | 11/09/2021 |
| CHESSER, PATRICE | MILILANI, HI | - | RBT | 09/22/2026 |
| CHESTER, AMANDA | NAPA, CA | - | RBT | 08/07/2025 |
| CHEYNE, FIONA | KATY, TX | LPC | Professional Counselor | 10/23/2024 |
| CHHOEUN, MELINDA | PORTSMOUTH, NH | - | RBT | 09/22/2026 |
| CHICO, ANA | FORT WORTH, TX | LPC | Mental Health Counselor | 05/23/2026 |
| CHIDLEY, JOE | WASHINGTON, DC | LMSW | Clinical Social Worker | 09/25/2026 |
| CHILDRE, GWENDOLYN | BATON ROUGE, LA | RAC | Addiction (Substance Use Disorder) Counselor | 05/04/2023 |
| CHILDREN AND FAMILY WELLNESS CENTER LLCORG | LIVERMORE, CA | - | Mental Health Counselor | 09/22/2026 |
| CHILDREN'S HOSPITAL OF PHILADELPHIAORG | PHILADELPHIA, PA | - | Community/Behavioral Health Agency | 11/28/2022 |
| CHILDREN'S THERAPY CTR, INCORG | ROSEMOUNT, MN | - | Speech-Language Pathologist | 02/06/2007 |
| CHILDRENS HOSPITAL OF PHILADELPHIAORG | PHILADELPHIA, PA | - | Clinic/Center | 09/02/2005 |
| CHILLIS, ADRIANNAH | MILWAUKEE, WI | - | BCBA | 09/25/2026 |
| CHILSON, KELLEY | DU BOIS, PA | PSYD | Psychologist | 08/11/2020 |
| CHIN, CAMELLIA | NEWARK, CA | - | RBT | 09/22/2026 |
| CHIN, TIFFANY | CHICAGO, IL | LCSW | Clinical Social Worker | 06/24/2021 |
| CHINESE PSYCHOLOGICAL ASSISTANCE FOUNDATIONORG | LOS ANGELES, CA | - | Community/Behavioral Health Agency | 09/26/2026 |
| CHIPPEWA VALLEY COUNSELING CENTERORG | EAU CLAIRE, WI | - | Mental Health Counselor | 10/17/2025 |
| CHIPPEWA VALLEY SPEECH THERAPY LLCORG | EAU CLAIRE, WI | - | Speech-Language Pathologist | 06/08/2017 |
| CHIRIBOGA, MELISSA | HOUSTON, TX | LPC ASSOCIATE | Mental Health Counselor | 09/25/2026 |
| CHIRINO MONTERO, KENDRI | BRANDON, FL | - | RBT | 09/21/2026 |
| CHISHOLM, COLIN | RENO, NV | MSW, LCSW | Clinical Social Worker | 03/30/2010 |
| CHLEBANOWSKI, SARA | BLOOMINGTON, IL | LCSW | Clinical Social Worker | 11/24/2014 |
| CHO, ANGELINA | POMONA, CA | - | RBT | 09/21/2026 |
| CHO, DILAND | LANHAM, MD | - | Case Manager/Care Coordinator | 09/21/2026 |
| CHO, HENSON | FLUSHING, NY | - | Speech-Language Pathologist | 09/21/2026 |
| CHOATE, REBECCA | BELLEVILLE, IL | LPC | Counselor | 07/14/2022 |
| CHOFFIN, MARRA | ROCHESTER, NY | - | Mental Health Counselor | 09/21/2026 |
| CHOI, KATLYNN | CYPRESS, TX | - | BCBA | 09/23/2026 |
| CHOI, MATTIE | NORTH WALES, PA | - | Mental Health Counselor | 09/22/2026 |
| CHOJNACKI, NICOLE | AURORA, CO | BCBA, MA | BCBA | 11/26/2025 |
| CHOSEN COUNSELING LLCORG | OMAHA, NE | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| CHOTANI, MINHA | COLUMBIA, MD | - | RBT | 06/08/2026 |
| CHOUDHARY, SHUBHAM | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/11/2026 |
| CHOUDHURY, RAVITA | NEW YORK, NY | LMSW | Clinical Social Worker | 09/23/2024 |
| CHOW, LAUREN | LOS ANGELES, CA | - | Speech-Language Pathologist | 09/21/2026 |
| CHOW, LAURIE | HAYWARD, CA | - | RBT | 09/21/2026 |
| CHRISTENSEN, JESSICA | HUGO, MN | LICSW | Clinical Social Worker | 04/27/2018 |
| CHRISTI, KIM | SAINT CLAIR SHORES, MI | LMSW | Clinical Social Worker | 10/03/2008 |
| CHRISTIAN, DARLENE | ZELIENOPLE, PA | LBS, BCBA | BCBA | 09/25/2026 |
| CHRISTIAN, LISA | COLUMBUS, OH | BEHAVIOR ANALYST | BCBA | 04/13/2021 |
| CHRISTIAN, SARISHA | HIGHLAND PARK, NJ | - | BCBA | 06/10/2026 |
| CHRISTIANSON, JAMES | NEWTON, IA | BA, CADC | Addiction (Substance Use Disorder) Counselor | 11/15/2006 |
| CHRISTIANSON, MOLLY | PROVO, UT | - | Clinical Social Worker | 09/21/2026 |
| CHRISTIE, CHERYL | HOUSTON, TX | - | Professional Counselor | 09/21/2026 |
| CHRISTINA M. MCALPIN, MD. A PROF CORPORG | LOS ANGELES, CA | - | Specialist | 07/01/2008 |
| CHRISTMAN, ABIGAIL | ONTARIO, OH | - | RBT | 06/10/2026 |
| CHRISTMANN, ALEXANDRA | PITTSBURGH, PA | - | Mental Health Counselor | 09/23/2026 |
| CHRISTMAS, ANGELA | BUFORD, GA | - | BCBA | 03/14/2022 |
| CHRISTO, DEBRA | MANSFIELD, OH | - | RBT | 09/25/2026 |
| CHRISTOPHER L BROWN LPCCORG | GARDENA, CA | - | Mental Health Counselor | 08/08/2026 |
| CHRISTOPHERSON, MADILYN | KAYSVILLE, UT | - | RBT | 09/25/2026 |
| CHRISTY SUGGS COUNSELING, LLCORG | TOLEDO, OH | - | Mental Health Counselor | 09/24/2026 |
| CHRONISTER, MADALENE | MUSKEGON, MI | - | RBT | 09/21/2026 |
| CHUBEI, NATALIA | ROCHESTER, MA | - | RBT | 09/21/2026 |
| CHUNG, KAYLI | MIAMI, FL | - | Speech-Language Pathologist | 10/12/2020 |
| CHUNG, TSOI YI | WALNUT CREEK, CA | PSYD | Psychologist | 06/17/2026 |
| CIANCIARULLO, BARBARA | CONCORD, NC | - | RBT | 09/22/2026 |
| CICCHETTI, AMANDA | DAYVILLE, CT | LPC-A | Counselor | 09/23/2025 |
| CIKOVIC, MARISSA | BEL AIR, MD | - | Clinical Social Worker | 03/02/2023 |
| CINCIONE, ELISABETH | PALO ALTO, CA | - | Psychologist | 09/20/2022 |
| CINTRON, CARISA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| CIOTTA, JENNIFER | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| CIPRIANO, ELYSE | SHORELINE, WA | - | Speech-Language Pathologist | 10/11/2023 |
| CISNEROS SANTANA, DULCE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| CISNEROS-RAMIREZ, SARAHI | SALINAS, CA | - | RBT | 09/21/2026 |
| CISNEROS, ANAHY | SACRAMENTO, CA | - | RBT | 09/22/2026 |
| CITY BEAUTIFUL SPEECH THERAPY LLCORG | ORLANDO, FL | - | Speech-Language Pathologist | 09/24/2026 |
| CITY OF HOPE MEDICAL GROUP OF ILLINOIS PLLCORG | ZION, IL | - | Specialist | 10/10/2005 |
| CIZEK, KRISTIN | BRICK, NJ | LPC | Professional Counselor | 08/25/2017 |
| CLAIMORA MEDICAL BILLING LLCORG | SAN JOSE, CA | - | Clinic/Center | 09/23/2026 |
| CLAIR, JOHANNA | BRIGHTON, MA | - | Counselor | 07/22/2025 |
| CLAMMER, ELIAS | BARRE, VT | - | Case Manager/Care Coordinator | 09/24/2026 |
| CLARDY, KENNETH | FORT SMITH, AR | - | Case Manager/Care Coordinator | 09/22/2026 |
| CLARICE BEHAVIORAL CONSULTING LLCORG | FAYETTEVILLE, AR | - | BCBA | 09/23/2026 |
| CLARIOMED LLCORG | SAN JOSE, CA | - | Clinic/Center | 09/23/2026 |
| CLARITY & CONNECTION THERAPY PLLCORG | COLORADO SPRINGS, CO | - | Clinical Social Worker | 06/24/2024 |
| CLARITY PATH COUNSELLING OF MID MICHIGAN LLCORG | MT PLEASANT, MI | - | Mental Health Counselor | 09/21/2026 |
| CLARITY PEAK HEALTH LLCORG | HUMBLE, TX | - | Community/Behavioral Health Agency | 12/25/2023 |
| CLARK, BONNIE | LOS ANGELES, CA | - | Clinical Social Worker | 04/14/2023 |
| CLARK, BROOKLYN | ORLANDO, FL | - | RBT | 09/21/2026 |
| CLARK, CATHERINE | MILWAUKIE, OR | - | Speech-Language Pathologist | 09/22/2026 |
| CLARK, CHANTE' | FORT BRAGG, NC | LCSW | Clinical Social Worker | 05/13/2016 |
| CLARK, CHRISTIANNA | MONTEREY PARK, CA | - | Mental Health Counselor | 09/24/2026 |
| CLARK, DIAMOND | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| CLARK, HEATHER | SAN ANTONIO, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/23/2026 |
| CLARK, JEFFREY | WARREN, OH | - | Case Manager/Care Coordinator | 01/17/2025 |
| CLARK, JULI | SACRAMENTO, CA | - | Counselor | 10/14/2013 |
| CLARK, KARA | CROWLEY, LA | LCSW | Clinical Social Worker | 11/12/2018 |
| CLARK, KAREN | BIRMINGHAM, AL | PH.D. | Psychologist | 05/20/2008 |
| CLARK, KIMBERLY | COVINGTON, GA | - | Speech-Language Pathologist | 09/25/2026 |
| CLARK, MCKENZIE | FORT WAYNE, IN | - | BCBA | 12/06/2024 |
| CLARK, MICHAEL | IRONTON, OH | - | Case Manager/Care Coordinator | 05/15/2026 |
| CLARK, MYESHA | FARMINGTON HILLS, MI | - | RBT | 08/10/2022 |
| CLARK, NOAH | HOOVER, AL | - | RBT | 11/07/2025 |
| CLARK, VESTA | SUMMERSVILLE, WV | - | Counselor | 09/23/2026 |
| CLARKE, JALANI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CLARKE, LENA | LAS VEGAS, NV | MSCP | Mental Health Counselor | 09/25/2026 |
| CLARKE, MARQUIS | CHESTERFIELD, VA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| CLARY, MARGARET | KEY WEST, FL | - | RBT | 09/25/2026 |
| CLAY, JEANETTE | FRENCH CAMP, CA | - | Clinical Social Worker | 03/05/2019 |
| CLAYTON-SPIKES, TORRIE | GARDENA, CA | - | Case Manager/Care Coordinator | 09/22/2026 |
| CLAYTOR, LIAINA | VACAVILLE, CA | LCSW | Mental Health Counselor | 09/24/2026 |
| CLEANING BRAINS UPORG | CORONA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| CLEAR HORIZON COUNSELING SERVICES, LLCORG | OWASSO, OK | - | Mental Health Counselor | 09/21/2026 |
| CLEARY, DREW | SPOKANE, WA | - | RBT | 09/23/2026 |
| CLEMENTE, ETHAN | LA PALMA, CA | - | RBT | 09/23/2026 |
| CLEMENTS, MICKALEA | RIVERBANK, CA | - | RBT | 09/21/2026 |
| CLENDENIN, MARIANA | ANCHORAGE, AK | - | Mental Health Counselor | 09/23/2026 |
| CLEVELAND, EMILY | PORTLAND, ME | LCPC | Professional Counselor | 09/22/2026 |
| CLEVELAND, TAYA | COLORADO SPRINGS, CO | LCSW, LAC | Clinical Social Worker | 08/14/2007 |
| CLIETT, SARAH | COLUMBUS, MS | - | RBT | 09/24/2026 |
| CLIFTON, CHRISTY | WILMINGTON, NC | M.S. CCC-SLP | Speech-Language Pathologist | 05/03/2016 |
| CLIFTON, KARLIE | KENNESAW, GA | - | Mental Health Counselor | 05/14/2024 |
| CLINE, SARAH | WAYLAND, MI | LLMSW | Clinical Social Worker | 09/04/2020 |
| CLINICA DE TERAPIA TIC TALK TOE LLCORG | HUMACAO, PR | - | Psychologist | 08/27/2018 |
| CLINICAL SOLUTIONS GROUP, LLCORG | GLENVIEW, IL | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| CLOCK, ANNIE | BOSTON, MA | MSW, LICSW | Clinical Social Worker | 11/18/2015 |
| CLOUDBERRY COUNSELING LCSW PLLCORG | ITHACA, NY | - | Clinical Social Worker | 08/31/2026 |
| CLOUDSCAPE DEVELOPMENTAL THERAPY AND WELLNESS CENTERORG | MOUNT HOOD PARKDALE, OR | - | Speech-Language Pathologist | 09/25/2026 |
| CLOUSER, PATRICIA | DU BOIS, PA | LSW | Clinical Social Worker | 10/30/2012 |
| CLOVER, ADISON | MCALESTER, OK | - | Speech-Language Pathologist | 09/24/2026 |
| CLOWER, TALA | CHICAGO, IL | LSW | Clinical Social Worker | 08/24/2023 |
| CLOWNEY, KNICOAL | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| CMM COUNSELING, INCORG | CHARLOTTESVILLE, VA | - | Clinical Social Worker | 09/14/2026 |
| COACHMAN, PHYLLIS | STATEN ISLAND, NY | LCSWR | Clinical Social Worker | 10/14/2006 |
| COAL COUNTY GENERAL HOSPITALORG | COALGATE, OK | - | Clinic/Center | 12/02/2022 |
| COAL COUNTY GENERAL HOSPITALORG | ATOKA, OK | - | Clinic/Center | 02/17/2023 |
| COAL COUNTY GENERAL HOSPITALORG | MCALESTER, OK | - | Clinic/Center | 02/17/2023 |
| COAL COUNTY GENERAL HOSPITALORG | COALGATE, OK | - | Clinic/Center | 11/30/2006 |
| COAL COUNTY GENERAL HOSPITALORG | COALGATE, OK | - | Clinic/Center | 07/18/2005 |
| COASTAL HORIZONS CENTER INC.ORG | WILMINGTON, NC | - | Mental Health Counselor | 09/21/2026 |
| COASTAL HORIZONS CENTER INC.ORG | JACKSONVILLE, NC | - | Mental Health Counselor | 12/28/2016 |
| COATES, ANAISHA | BALTIMORE, MD | - | Mental Health Counselor | 07/19/2022 |
| COBB, ELIZABETH | SOUTH BEND, IN | MSW LCSW | Clinical Social Worker | 12/17/2021 |
| COBB, SAMARA | LAS VEGAS, NV | - | Clinical Social Worker | 09/23/2026 |
| COBB, YAKABIR | FAYETTEVILLE, NC | LCMHC | Mental Health Counselor | 01/30/2025 |
| COCHRAN, OWEN | GAITHERSBURG, MD | - | RBT | 08/06/2026 |
| COCREATION COMMUNICATIONS, LLCORG | GARDEN CITY, ID | - | Speech-Language Pathologist | 08/10/2026 |
| CODDINGTON, TAYLOR | ASHEVILLE, NC | - | Professional Counselor | 09/22/2026 |
| COFFEY, HANNAH | DENVER, CO | PSY | Psychologist | 06/17/2025 |
| COFFEY, KARLEE | PORTLAND, OR | LMT | Mental Health Counselor | 11/29/2017 |
| COFFEY, NANCY | MCCLELLAN, CA | LCSW | Clinical Social Worker | 12/26/2019 |
| COFRIN-SHAW, BRYNA | FLORENCE, MA | LMHC | Mental Health Counselor | 09/21/2026 |
| COGNIVIA PSCORG | GREENWOOD, IN | - | Mental Health Counselor | 02/10/2026 |
| COHEN, ADDISON | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| COHEN, ARIEL | STATEN ISLAND, NY | - | Speech-Language Pathologist | 09/24/2026 |
| COHEN, SYDNEY | SANDY SPRINGS, GA | LMSW | Clinical Social Worker | 09/23/2026 |
| COHEN, YUKA | FAIRVIEW, TX | PSY.D. | Psychologist | 04/20/2012 |
| COLBERT, ANNA | BOSTON, MA | MSW, LCSW | Clinical Social Worker | 09/26/2026 |
| COLE, ALLISON | ROLLING MEADOWS, IL | - | BCBA | 05/07/2025 |
| COLE, AVA | GAYLORD, MI | - | RBT | 09/22/2026 |
| COLE, AZARIA | ENNIS, TX | - | RBT | 09/22/2026 |
| COLE, DYNISHA | HUTTO, TX | - | RBT | 09/23/2026 |
| COLE, EMILY | CHEYENNE, WY | LCSW | Clinical Social Worker | 11/21/2012 |
| COLE, KAREN | STEPHENVILLE, TX | MS | Professional Counselor | 05/13/2009 |
| COLE, MELINDA | EXETER, NH | M.S. | RBT | 10/24/2014 |
| COLE, MIRANDA | WEST SPRINGFIELD, MA | - | RBT | 09/21/2026 |
| COLEMAN, BRITNEY | CENTRAL POINT, OR | - | Mental Health Counselor | 08/14/2023 |
| COLEMAN, BRITTIANY | JACKSONVILLE, FL | - | Mental Health Counselor | 09/21/2026 |
| COLEMAN, KIRA | WALNUT CREEK, CA | - | RBT | 09/23/2026 |
| COLEMAN, REBECCA | SAN DIEGO, CA | MCD, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| COLEY, MIRESHA | GLENWOOD, AR | - | RBT | 12/01/2021 |
| COLGAN, SHANNON | BOYERTOWN, PA | LPC | Mental Health Counselor | 11/14/2022 |
| COLL, GRACE | BROOKLYN, NY | - | Speech-Language Pathologist | 09/24/2026 |
| COLLABORATIVE COUNSELING SOLUTIONSORG | APEX, NC | - | Clinical Social Worker | 07/20/2026 |
| COLLABORATIVE THERAPY INNOVATIONSORG | KENT, OH | - | Professional Counselor | 09/23/2026 |
| COLLADO, ANNA | SPOKANE, WA | - | RBT | 04/04/2025 |
| COLLAZO, ANDREW | NEW BEDFORD, MA | - | RBT | 09/23/2026 |
| COLLECTIVE COUNSELING LLCORG | HONOLULU, HI | - | Mental Health Counselor | 12/12/2023 |
| COLLES, LAUREN | COLUMBUS, OH | LPCC | Professional Counselor | 01/04/2021 |
| COLLETTE, CALANDRE | MILWAUKIE, OR | LCSW | Clinical Social Worker | 02/26/2007 |
| COLLIE, LATONIA | JOHNSON CITY, TN | LCSW | Clinical Social Worker | 09/23/2026 |
| COLLIER, CAROLINE | BOSTON, MA | - | Speech-Language Pathologist | 09/23/2026 |
| COLLIER, JENNIFER | EUGENE, OR | - | Mental Health Counselor | 09/22/2026 |
| COLLIER, JENNIFER | ROLLA, MO | LPC | Professional Counselor | 11/11/2024 |
| COLLINS PSYCHOTHERAPY & COUNSELING SERVICES PLLCORG | SIOUX CITY, IA | - | Mental Health Counselor | 09/23/2026 |
| COLLINS, AMANDA | LINTHICUM, MD | BS, MS, MA | Psychologist | 07/02/2025 |
| COLLINS, KELLY | GRAND RAPIDS, MI | MA | Mental Health Counselor | 05/20/2025 |
| COLLINS, MIKAYLA | TAMPA, FL | RBT | RBT | 05/30/2025 |
| COLLINS, SARINITY | VICTORVILLE, CA | - | RBT | 09/21/2026 |
| COLLINS, SHEILA | CHICAGO, IL | PSYD | Psychologist | 12/15/2014 |
| COLLINS, TRINITY | DURANT, OK | - | RBT | 09/21/2026 |
| COLLISON, VANESSA | SILVER SPRING, MD | - | RBT | 06/14/2021 |
| COLON, DANIELA | SUNRISE, FL | - | Speech-Language Pathologist | 08/26/2025 |
| COLON, SHAYIANA | PIKESVILLE, MD | - | RBT | 09/25/2026 |
| COLORADO CARDIOVASCULAR SURGICAL ASSOCIATES,INCORG | DENVER, CO | - | Specialist | 08/05/2022 |
| COLORADO CARDIOVASCULAR SURGICAL ASSOCIATES,INC.ORG | ENGLEWOOD, CO | - | Specialist | 05/26/2006 |
| COLORADO CLINICAL CONSULTANTS, LLCORG | DENVER, CO | - | Community/Behavioral Health Agency | 05/04/2026 |
| COLORADO WEST REGIONAL MENTAL HEALTH, INC.ORG | GRAND JUNCTION, CO | - | Community/Behavioral Health Agency | 09/25/2026 |
| COLSON, SARAH | JUNCTION CITY, OR | - | Mental Health Counselor | 12/31/2024 |
| COLVIN, LISA | CONWAY, AR | - | RBT | 09/24/2026 |
| COMBS, CHASITY | FISHERS, IN | - | RBT | 09/22/2026 |
| COMFORT, CHRISTOPHER | BRONX, NY | M.D. | Specialist | 10/12/2006 |
| COMMA CO LLCORG | LARGO, FL | - | Mental Health Counselor | 09/26/2026 |
| COMMUNICATION CONNECTION, INC.ORG | MIAMI, FL | - | BCBA | 11/22/2023 |
| COMMUNICATION CONNECTION, INC.ORG | MIAMI, FL | - | Clinic/Center | 08/24/2016 |
| COMMUNITY ACCESS NETWORK LLCORG | LAS VEGAS, NV | - | Community/Behavioral Health Agency | 09/24/2026 |
| COMMUNITY BEHAVIORAL HEALTHORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/23/2017 |
| COMMUNITY BEHAVIORAL HEALTHORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/23/2017 |
| COMMUNITY BEHAVIORAL HEALTHORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/03/2017 |
| COMMUNITY BEHAVIORAL HEALTHORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/23/2017 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 10/10/2016 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 02/02/2016 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 10/05/2020 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | CENTREVILLE, MD | - | Community/Behavioral Health Agency | 01/09/2015 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | EASTON, MD | - | Community/Behavioral Health Agency | 12/16/2019 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | CAMBRIDGE, MD | - | Community/Behavioral Health Agency | 10/20/2016 |
| COMMUNITY BEHAVIORAL HEALTH LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 10/11/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CAMBRIDGE, MD | - | Community/Behavioral Health Agency | 01/23/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CAMBRIDGE, MD | - | Community/Behavioral Health Agency | 01/24/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | PRINCESS ANNE, MD | - | Community/Behavioral Health Agency | 03/19/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 01/24/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 08/18/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CENTREVILLE, MD | - | Community/Behavioral Health Agency | 10/11/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 08/18/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | PRINCESS ANNE, MD | - | Community/Behavioral Health Agency | 12/06/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/03/2017 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CAMBRIDGE, MD | - | Community/Behavioral Health Agency | 01/23/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 01/24/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 01/23/2017 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | PRINCESS ANNE, MD | - | Community/Behavioral Health Agency | 05/18/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 02/05/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 07/02/2019 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | PRINCESS ANNE, MD | - | Community/Behavioral Health Agency | 12/01/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CHESTERTOWN, MD | - | Community/Behavioral Health Agency | 12/16/2021 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/03/2017 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 11/12/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CENTREVILLE, MD | - | Community/Behavioral Health Agency | 01/24/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CAMBRIDGE, MD | - | Case Management Agency | 06/14/2024 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | DENTON, MD | - | Addiction (Substance Use Disorder) Counselor | 09/02/2022 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | DENTON, MD | - | Community/Behavioral Health Agency | 09/02/2022 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 03/08/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 02/23/2017 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 01/23/2017 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CENTREVILLE, MD | - | Community/Behavioral Health Agency | 01/24/2013 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SNOW HILL, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SNOW HILL, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SNOW HILL, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SALISBURY, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | SNOW HILL, MD | - | Community/Behavioral Health Agency | 09/03/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CHESTERTOWN, MD | - | Addiction (Substance Use Disorder) Counselor | 05/25/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | CHESTERTOWN, MD | - | Community/Behavioral Health Agency | 06/07/2016 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | COLUMBIA, MD | - | Community/Behavioral Health Agency | 01/02/2020 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | EASTON, MD | - | Community/Behavioral Health Agency | 12/16/2019 |
| COMMUNITY BEHAVIORAL HEALTH, LLCORG | EASTON, MD | - | Community/Behavioral Health Agency | 12/11/2019 |
| COMMUNITY COUNSELING SERVICESORG | COLUMBUS, MS | - | Mental Health Counselor | 09/21/2026 |
| COMMUNITY HEALTH CARE ASSOCIATES, INCORG | FREDERICKTOWN, MO | - | Clinical Social Worker | 05/18/2007 |
| COMMUNITY HEALTH CENTERS, INC.ORG | OKLAHOMA CITY, OK | - | Community/Behavioral Health Agency | 03/09/2012 |
| COMMUNITY HEALTH CLINIC, INC.ORG | VANDERGRIFT, PA | - | Clinic/Center | 06/03/2016 |
| COMMUNITY HEALTH RESOURCES, INCORG | WINDSOR, CT | - | Case Management Agency | 11/21/2006 |
| COMMUNITY HELPING ALL NEEDING GROWTH EVERYWHEREORG | PHILADELPHIA, PA | - | Case Management Agency | 09/23/2026 |
| COMMUNITY OUTREACH ASSISTANCE TEAMORG | ALBANY, OR | - | Case Management Agency | 09/24/2026 |
| COMPASS FAMILY SERVICESORG | ANNISTON, AL | - | Mental Health Counselor | 09/25/2026 |
| COMPASSION COUNSELINGORG | COLUMBUS, GA | - | Mental Health Counselor | 07/07/2026 |
| COMPASSIONATE CONNECTIONS COUNSELING LLCORG | LAS CRUCES, NM | - | Clinical Social Worker | 05/12/2022 |
| COMPLETE NEUROPSYCHOLOGY SERVICES, INCORG | BRIGHTON, MI | - | Psychologist | 08/17/2015 |
| COMPLETE SUPPORT SERVICES LLCORG | MEDFORD, OR | - | Community/Behavioral Health Agency | 09/22/2026 |
| COMPTON, GRACE | SPRING LAKE, NC | - | RBT | 11/22/2025 |
| CONAWAY, KIRA | SAVANNAH, GA | - | RBT | 09/25/2026 |
| CONCIERGE MENTAL HEALTH COUNSELING SERVICES PLLCORG | KINGSTON, NY | - | Mental Health Counselor | 08/13/2024 |
| CONDA, CHRYSTAL | SEDRO WOOLLEY, WA | - | Counselor | 09/25/2026 |
| CONDREY, ELIZABETH | ALBANY, NY | LCSW | Clinical Social Worker | 10/22/2018 |
| CONKLIN, SABRINA | POWELL, TN | DSW, LCSW | Clinical Social Worker | 07/03/2012 |
| CONLEY, KENDALL | BRIGHTON, MA | - | Clinical Social Worker | 05/09/2024 |
| CONLEY, SHARON | CECILIA, KY | LPCC | Professional Counselor | 09/26/2026 |
| CONNECT CARE SUPPORT SERVICESORG | LAKEWOOD, NJ | - | Community/Behavioral Health Agency | 09/23/2026 |
| CONNECT WELLNESS CENTER LLCORG | NORTHFIELD, OH | - | Mental Health Counselor | 04/09/2025 |
| CONNECTED HEALING & WELLNESS PLLCORG | CHICAGO, IL | - | Mental Health Counselor | 09/18/2026 |
| CONNECTED HEARTS THERAPY & WELLNESSORG | NEEDHAM, MA | - | Mental Health Counselor | 09/23/2026 |
| CONNECTIFY THERAPY LLCORG | DENVER, CO | - | BCBA | 06/25/2025 |
| CONNECTIONS HEALTHVA, LLCORG | WOODBRIDGE, VA | - | Community/Behavioral Health Agency | 08/08/2023 |
| CONNER, JACOB | MAUMEE, OH | - | Case Manager/Care Coordinator | 09/16/2026 |
| CONNER, KATHLEEN | TUCSON, AZ | LPC | Mental Health Counselor | 10/04/2023 |
| CONNOLLY, COURTNEY | TAUNTON, MA | - | Mental Health Counselor | 09/14/2016 |
| CONNOR-SMITH, CELIA | JAMAICA PLAIN, MA | - | Clinical Social Worker | 09/23/2026 |
| CONNORS, ALEXA | NEW YORK, NY | MSW | Clinical Social Worker | 05/28/2020 |
| CONRAD, SHELBY | LINCOLN, NE | LMHP | Mental Health Counselor | 07/21/2021 |
| CONSTANCE A FULLILOVE PHD LTDORG | CHICAGO, IL | - | Mental Health Counselor | 08/03/2026 |
| CONSTANT, CHRISTA | BANGOR, ME | - | Mental Health Counselor | 09/22/2026 |
| CONSTANTE, KRISTEN | CORPUS CHRISTI, TX | - | RBT | 09/23/2026 |
| CONTI, KATHRYN | KINGSTON, NH | PSY.D. | Mental Health Counselor | 11/19/2014 |
| CONTINUUM COUNSELING PLLCORG | HOMEWOOD, IL | - | Professional Counselor | 12/30/2025 |
| CONTRERAS, DAVID | SACRAMENTO, CA | - | RBT | 09/23/2026 |
| CONTRERAS, JAHAHI | RENO, NV | - | Clinical Social Worker | 03/15/2021 |
| CONWAY, KEITH | CHICAGO, IL | MA | Mental Health Counselor | 09/24/2026 |
| COOK & ASSOCIATESORG | WASHINGTON, DC | - | Professional Counselor | 09/24/2024 |
| COOK, ADRIANA | SPRINGFIELD, OH | - | Case Manager/Care Coordinator | 11/04/2024 |
| COOK, ANGELIQUE | BROOKLYN, MI | - | Case Manager/Care Coordinator | 12/08/2022 |
| COOK, HUNTER | JOHNSON CITY, TN | LPC/MHSP | Professional Counselor | 04/17/2013 |
| COOK, KAYLA | NEW BEDFORD, MA | - | RBT | 09/23/2026 |
| COOK, LAINA | KEOKUK, IA | CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| COOKE, DANIEL | STATESVILLE, NC | LCMHC-A | Addiction (Substance Use Disorder) Counselor | 07/27/2016 |
| COOKE, JESSICA | CLOVIS, CA | - | RBT | 06/30/2019 |
| COOKSEY, KENNETH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| COOLEY, ALAYSIA | PIKESVILLE, MD | - | RBT | 09/25/2026 |
| COOLIDGE COUNSELING SERVICES INCORG | LINDSTROM, MN | - | Professional Counselor | 01/16/2023 |
| COOPER COUNSELING AND WELLNESS LLCORG | HOUSTON, TX | - | Counselor | 03/09/2019 |
| COOPER, ANNA | CONCORD, NC | - | RBT | 09/22/2026 |
| COOPER, BROCK | MUSTANG, OK | - | RBT | 09/23/2026 |
| COOPER, CAREN | HOUSTON, TX | ED.D., LPC-S, PMH-C | Counselor | 05/20/2013 |
| COOPER, EMILY | VAN BUREN TOWNSHIP, MI | LPC, NCC | Professional Counselor | 09/21/2026 |
| COOPER, HAYLEY | PARKVILLE, MO | - | Professional Counselor | 09/22/2026 |
| COOPER, KAYLA | ESTANCIA, NM | LCSW | Clinical Social Worker | 06/03/2015 |
| COOPER, MIKAELA | OMAHA, NE | PLMHP | Mental Health Counselor | 09/24/2026 |
| COPELAND, SYDNEY | ALPHARETTA, GA | - | BCBA | 09/21/2026 |
| COPPEDGE, KRISTIE | PORT ANGELES, WA | LICSW | Clinical Social Worker | 02/21/2007 |
| CORA RICHTER PSYCHOTHERAPY LCSW PLLCORG | STATEN ISLAND, NY | - | Clinical Social Worker | 09/21/2026 |
| CORBI, PHILLIP | WOODBURY, CT | M.S. BCBA | BCBA | 06/03/2020 |
| CORCORAN, LILLIAN | LEONIA, NJ | LPC | Mental Health Counselor | 07/29/2026 |
| CORDERO, KAYLA | AMHERST, NY | - | Mental Health Counselor | 09/25/2026 |
| CORDERO, SANDRA | CORAL GABLES, FL | RBT | RBT | 11/02/2021 |
| CORDES, GINA | GREENWOOD VILLAGE, CO | LCSW | Clinical Social Worker | 01/23/2023 |
| CORDES, LORELEI | FREMONT, CA | - | RBT | 09/22/2026 |
| CORDOVA, ALYSSA | LAKEWOOD, CO | - | RBT | 09/25/2026 |
| CORDOVA, REBEKAH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CORDOVA, SUZETTE | CASA GRANDE, AZ | - | RBT | 09/24/2026 |
| CORENEVSKY, SARA | CALIFORNIA, MD | - | RBT | 09/24/2026 |
| CORIARTY, MADISON | SAINT PETERSBURG, FL | - | RBT | 09/10/2026 |
| CORLEW, JADE | POMONA, CA | - | BCBA | 02/03/2020 |
| CORLEY, NATASHA | DURHAM, NC | MSW | Clinical Social Worker | 09/16/2006 |
| CORLEY, VICTORIA | BATON ROUGE, LA | LCSW | Clinical Social Worker | 07/15/2022 |
| CORNEA, EMILY | LAKE ORION, MI | LLPC | Mental Health Counselor | 09/22/2026 |
| CORNELIUS, KARLEY | OKLAHOMA CITY, OK | MHR, LPC | Counselor | 12/05/2019 |
| CORNERSTONE CHRISTIAN COUNSELING, INCORG | COLORADO SPRINGS, CO | - | Community/Behavioral Health Agency | 01/21/2021 |
| CORNERSTONE CHRISTIAN COUNSELING, INCORG | BOULDER, CO | - | Community/Behavioral Health Agency | 09/21/2026 |
| CORNERSTONE COMMUNITY CHURCHORG | LAKE ELSINORE, CA | - | Counselor | 09/25/2026 |
| CORNERSTONE COUNSELINGORG | CHICO, CA | - | Clinical Social Worker | 09/26/2026 |
| CORNETT, ANDREA | SAN JOSE, CA | - | Addiction (Substance Use Disorder) Counselor | 04/17/2018 |
| CORNETT, JUSTIN | RICHMOND, IN | - | RBT | 09/21/2026 |
| CORNISH, CIARA | BATON ROUGE, LA | - | RBT | 09/23/2026 |
| CORNS, DEREK | PALM SPRINGS, CA | ASW | Clinical Social Worker | 05/08/2023 |
| CORONA, VANESSA | FEDERAL HEIGHTS, CO | - | RBT | 09/22/2026 |
| CORONADO, ARATH | FRIDLEY, MN | - | RBT | 09/21/2026 |
| CORRAL SANTOS, DEREK | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| CORRAL, RAFAEL | WOODLAND HILLS, CA | BA PSYCHOLOGY, BCAT | BCBA | 09/27/2022 |
| CORRAL, SIDNEY | LAS VEGAS, NV | - | RBT | 09/25/2026 |
| CORRALES, CYNTHIA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| CORRALES, NICOLAS | CHINO HILLS, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| CORREA, ANYA | LAKEWOOD, CO | - | Case Manager/Care Coordinator | 09/23/2026 |
| CORREIA, OLIVIA | FRAMINGHAM, MA | - | RBT | 09/25/2026 |
| CORRY, NOLAN | ANAHEIM, CA | - | Addiction (Substance Use Disorder) Counselor | 07/23/2026 |
| CORTES-MORENO, SOPHIA | AURORA, IL | - | Counselor | 09/01/2016 |
| CORTES, DANILU | ALHAMBRA, CA | - | RBT | 09/21/2026 |
| CORTESE, DANIEL | ASHEVILLE, NC | LCMHC | Mental Health Counselor | 12/17/2015 |
| CORTEZ, ANDREW | CHANDLER, AZ | - | Clinical Social Worker | 09/24/2026 |
| CORTEZ, ITZELT | YUBA CITY, CA | - | Clinical Social Worker | 01/30/2023 |
| CORTEZ, JAZMINE | YAKIMA, WA | - | Case Manager/Care Coordinator | 06/18/2025 |
| COSMIC BEHAVIOR THERAPYORG | COLORADO SPRINGS, CO | - | BCBA | 09/21/2026 |
| COSS, BRANDON | PARKERSBURG, WV | - | Counselor | 09/24/2026 |
| COSSETTE, MARGARET | WEST FARGO, ND | - | Case Manager/Care Coordinator | 09/21/2026 |
| COSTA, ELIZA | SALINAS, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| COTA, CARLOS | DOWNEY, CA | - | RBT | 09/24/2026 |
| COTHREN, TARA | FOREST, VA | - | Professional Counselor | 03/08/2017 |
| COTNER, REBEKAH | DAYTON, OH | LMHC | Mental Health Counselor | 07/27/2018 |
| COTTER, COLIN | FRISCO, TX | LPC | Professional Counselor | 02/03/2008 |
| COTTONWOOD COUNSELING PLLC DBA DESERT PEAR PSYCHOTHERAPYORG | ALBUQUERQUE, NM | - | Clinical Social Worker | 06/17/2026 |
| COUGHLIN, COURTNIE | WILMINGTON, NC | MSW, LCSWA | Clinical Social Worker | 09/23/2026 |
| COULTER, SHANNON | PERRY, GA | - | RBT | 09/22/2026 |
| COUNSELING AND RESEARCH ASSOCIATES, INC.ORG | NORWALK, CA | - | Community/Behavioral Health Agency | 11/06/2007 |
| COUNSELING ASSOCIATES OF AMERICA A PROFESSIONAL CORPORATIONORG | SANDY, UT | - | Counselor | 12/04/2019 |
| COUNSELING PLACE COLLECTIVEORG | LONE TREE, CO | - | Mental Health Counselor | 09/24/2026 |
| COUNSELING SOLUTIONS & INTERVENTIONS, LLCORG | OKLAHOMA CITY, OK | - | Community/Behavioral Health Agency | 09/14/2010 |
| COUNTY OF CALAVERASORG | SAN ANDREAS, CA | - | Case Manager/Care Coordinator | 05/05/2006 |
| COUNTY OF CALAVERASORG | SAN ANDREAS, CA | - | Case Manager/Care Coordinator | 05/05/2025 |
| COUNTY OF GRANT DBA UNIFIED COMMUNITY SERVICESORG | LANCASTER, WI | - | Community/Behavioral Health Agency | 11/05/2008 |
| COUNTY OF GRANT DBA UNIFIED COMMUNITY SERVICESORG | DODGEVILLE, WI | - | Case Management Agency | 11/05/2008 |
| COUNTY OF SOLANOORG | FAIRFIELD, CA | - | Case Management Agency | 05/07/2007 |
| COUNTY OF STANISLAUSORG | MODESTO, CA | - | Community/Behavioral Health Agency | 03/14/2007 |
| COURTNEY, LIDIA | AUSTIN, TX | - | RBT | 09/25/2026 |
| COUVRETTE, MAPLE | MEDFORD, OR | - | Mental Health Counselor | 07/21/2026 |
| COVA SPEECH THERAPY PLLCORG | MISSOULA, MT | - | Speech-Language Pathologist | 09/22/2026 |
| COVENANT COUNSEL, LLCORG | LAGRANGE, GA | - | Professional Counselor | 06/28/2025 |
| COWAN, JAYME | MIDWEST CITY, OK | LPC CANDIDATE | Counselor | 10/24/2025 |
| COX, CHARLEE | LEWISTON, ME | LCPC-C | Professional Counselor | 09/23/2026 |
| COX, EMMA | DANVERS, MA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2020 |
| COX, MADYSEN | KOKOMO, IN | - | RBT | 12/19/2024 |
| COX, SARA | CONIFER, CO | LPC | Mental Health Counselor | 02/25/2013 |
| COX, SHELBY | MANASQUAN, NJ | - | Mental Health Counselor | 04/22/2025 |
| COZART, DIANA | NASHVILLE, TN | - | RBT | 09/26/2026 |
| CPF IDAHO BEHAVIORAL HEALTH, LLCORG | BOISE, ID | - | Addiction (Substance Use Disorder) Counselor | 11/15/2021 |
| CRAFT, KATIE | BEVERLY, MA | MS CCC/SLP | Speech-Language Pathologist | 07/12/2009 |
| CRAIG, AIDAN | NEW PALESTINE, IN | - | RBT | 09/21/2026 |
| CRAIG, BRANDI | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| CRAIG, ELEANOR | KALISPELL, MT | PCLC | Mental Health Counselor | 09/23/2026 |
| CRAIG, EMILY | BOSTON, MA | - | Mental Health Counselor | 09/23/2026 |
| CRAIG, JASMINE | LAKEWOOD, CO | - | Case Manager/Care Coordinator | 09/22/2026 |
| CRAIL, ERIN | NASHUA, NH | LCMHC | Mental Health Counselor | 01/03/2007 |
| CRANDALL, ELLI | FENNVILLE, MI | CF-SLP | Speech-Language Pathologist | 09/24/2026 |
| CRANDALL, RACHEL | REXBURG, ID | RDN, LPC | Professional Counselor | 07/27/2023 |
| CRANE-TUCKER, KASHAELLE | MODESTO, CA | - | RBT | 09/24/2026 |
| CRANE, LYNDSAY | WATERFORD, MI | - | Speech-Language Pathologist | 03/06/2026 |
| CRAVENS, ALEXANDRA | SPOKANE, WA | MSW, LICSW | Clinical Social Worker | 10/30/2018 |
| CRAVENS, CANA | TAMPA, FL | - | Mental Health Counselor | 09/22/2026 |
| CRAVEY, MALAYSHA | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/21/2026 |
| CRAWFORD, MONIQUE | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| CRAWFORD, OLIVER | MARTINSBURG, WV | - | Mental Health Counselor | 11/14/2025 |
| CRAWFORD, RYAN | HOUSTON, TX | MS, LPC | Mental Health Counselor | 11/04/2008 |
| CRAWFORD, SPARKLE | LAWRENCEVILLE, GA | LPC | Mental Health Counselor | 09/22/2026 |
| CRAWFORD, TANODA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| CRAWFORD, TERESSA | LOUISVILLE, KY | ED.S LPCC | Professional Counselor | 12/27/2017 |
| CREATE ANEW WELLNESS PLLCORG | GRAYSLAKE, IL | - | Mental Health Counselor | 08/14/2026 |
| CREATING CONNECTIONS COUNSELING SERVICES LLCORG | COLORADO SPRINGS, CO | - | Mental Health Counselor | 10/14/2022 |
| CREATIVE ELEMENTS HEALTH & WELLNESS, PLLCORG | RICHMOND, VA | - | Mental Health Counselor | 09/22/2026 |
| CREATIVE EXPRESSION COUNSELINGORG | BROOKFIELD, WI | - | Mental Health Counselor | 09/25/2026 |
| CREATIVE WELLNESS CENTER INCORG | OAK PARK, MI | - | Professional Counselor | 10/06/2025 |
| CREEKMORE, IZABELLA | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| CREEKMORE, JODI | KNOXVILLE, TN | - | RBT | 09/25/2026 |
| CREELMAN, GABRIELLA | EVERETT, WA | LSWAIC | Clinical Social Worker | 06/29/2023 |
| CREIGHTON, PHILIP | BROOKFIELD, WI | - | RBT | 09/25/2026 |
| CRISP, MARGARET | HUNTERSVILLE, NC | - | Mental Health Counselor | 09/03/2026 |
| CRISS, DESTINY | NEWBURGH, IN | - | RBT | 09/22/2026 |
| CRIST-BURIN, BRIANA | GRAND RAPIDS, MI | LLP | Psychologist | 06/12/2019 |
| CRIST, CONNOR | HOUSTON, TX | - | RBT | 09/23/2026 |
| CRISTE, SIENNA | ROCHESTER, NY | MS | Speech-Language Pathologist | 09/22/2026 |
| CRISWELL, AMANDA | MADRAS, OR | QMHP | Mental Health Counselor | 05/09/2019 |
| CROCKER, KIRA | KNOXVILLE, TN | LMSW | Clinical Social Worker | 08/20/2026 |
| CROCKETT, IAIN | SPOKANE, WA | LMHC, M.S | Mental Health Counselor | 09/12/2014 |
| CROMARTIE, VANESSA | LAKELAND, FL | - | BCBA | 09/24/2026 |
| CROMER, KENIESHA | BALTIMORE, MD | - | RBT | 09/23/2026 |
| CROMWELL, NIA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CRONIN-BROWN, MELISSA | OXNARD, CA | - | RBT | 09/26/2026 |
| CROSS TIMBERS ORTHOPAEDICSORG | STEPHENVILLE, TX | - | Specialist | 09/13/2006 |
| CROSS, STEPHANIE | NAMPA, ID | - | Mental Health Counselor | 02/29/2016 |
| CROSSROADS TREATMENT CENTER OF ASHEVILLE, PCORG | ASHEVILLE, NC | - | Addiction (Substance Use Disorder) Counselor | 11/05/2013 |
| CROUCH, CELESTINA | MODESTO, CA | - | RBT | 09/23/2026 |
| CROWDER, KELVIN | AUBREY, TX | - | BCBA | 01/31/2025 |
| CROWE, ALIVIA | AUSTIN, TX | LCSW | Clinical Social Worker | 03/16/2022 |
| CROWLEY, DESIREE | SOMERSET, KY | - | Clinical Social Worker | 09/23/2026 |
| CROWLEY, KAYLA | WORCESTER, MA | MA | BCBA | 09/21/2026 |
| CROWLEY, MICHAEL | COLUMBIA, MD | LCPC, NCC | Professional Counselor | 04/30/2018 |
| CROWSTON-HICKEY, CALLIE | TORRINGTON, CT | LPC | Mental Health Counselor | 09/24/2026 |
| CRUTCHFIELD, ABIGAIL | BASEHOR, KS | - | RBT | 09/22/2026 |
| CRUTCHFIELD, KENNEDY | GRETNA, LA | - | Mental Health Counselor | 01/23/2020 |
| CRUTHIRDS, NATALIE | KERNERSVILLE, NC | - | Mental Health Counselor | 03/15/2024 |
| CRUZ FAMILY CARE LLCORG | NORTH LAUDERDALE, FL | - | BCBA | 09/21/2026 |
| CRUZ FRANCISCO, GISELLE | SHERMAN OAKS, CA | - | RBT | 09/25/2026 |
| CRUZ OROZCO, JAMIE | COLORADO SPRINGS, CO | - | RBT | 09/26/2026 |
| CRUZ-MARTINEZ, ASHLEY | CHICAGO, IL | - | Professional Counselor | 05/25/2026 |
| CRUZ-RIVERA, HARLEY | JACKSONVILLE, FL | - | RBT | 08/13/2026 |
| CRUZ, ALEXANDER | SUGAR LAND, TX | M.ED., LPC | Mental Health Counselor | 06/06/2024 |
| CRUZ, AMANDA | CHINO, CA | - | Clinical Social Worker | 05/10/2021 |
| CRUZ, DESHANAYE | PHOENIX, AZ | LCSW | Clinical Social Worker | 05/10/2022 |
| CRUZ, ISIS | RIVERVIEW, FL | - | RBT | 09/23/2026 |
| CRUZ, LINDSAY | OREM, UT | - | Mental Health Counselor | 09/24/2026 |
| CRUZ, MARTHA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| CRUZ, NANCY | FRESNO, CA | - | Day Training/Habilitation Specialist | 10/04/2022 |
| CRUZ, SABRINA | MIAMI, FL | MSW | Clinical Social Worker | 02/22/2023 |
| CRUZ, YERALDY | LOS ANGELES, CA | - | Speech-Language Pathologist | 11/17/2021 |
| CRYSTAL COUNSELING PLLCORG | SAN ANTONIO, TX | - | Case Management Agency | 05/14/2012 |
| CSW SERVICES, LLCORG | VIRGINIA BEACH, VA | - | Clinical Social Worker | 07/01/2021 |
| CUBA, BARBARA | TAMPA, FL | - | Mental Health Counselor | 05/08/2024 |
| CUBAQUE ALZATE, SOFIA | CONCORD, CA | - | RBT | 09/24/2026 |
| CUBELLI, DANI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| CUBILLO, STEPHANIE | LOS ANGELES, CA | - | Professional Counselor | 09/14/2022 |
| CUDDIHEE, TEA | FARMINGTON HILLS, MI | - | RBT | 09/07/2023 |
| CUELLAR, JANET | WATSONVILLE, CA | - | RBT | 09/21/2026 |
| CUEVAS, SANTA | HAYWARD, CA | - | RBT | 09/25/2026 |
| CUFF, STACEY | GAITHERSBURG, MD | - | RBT | 09/22/2026 |
| CUHACIYAN, CHRISTINE | BOTHELL, WA | LMHC | Mental Health Counselor | 08/28/2016 |
| CUKAJ, LYNN | NEW YORK, NY | - | Mental Health Counselor | 01/10/2022 |
| CULLEN, COLLEEN | CHARLESTON, SC | - | Clinical Social Worker | 11/22/2024 |
| CULLEY, JESSIE | KANSAS CITY, MO | LPC | Professional Counselor | 09/09/2024 |
| CULLIP, TAYLOR | CORTLAND, NY | LMSW-LP | Counselor | 09/23/2026 |
| CULLITY, SAMANTHA | SANTA ROSA, CA | - | RBT | 09/22/2026 |
| CULP, AINSLEY | MEDINA, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| CULVAHOUSE, SANFORD | RICHMOND, IN | - | RBT | 09/15/2026 |
| CULWELL, MIRANDA | OWASSO, OK | - | RBT | 05/18/2026 |
| CUMMINGS, CHELSEA | WAYNE, MI | - | Case Manager/Care Coordinator | 01/18/2019 |
| CUMMINGS, JENNIFER | LAS CRUCES, NM | M.A., BCBA | BCBA | 10/02/2015 |
| CUMMINGS, KAITLYN | PINEHURST, NC | LBA, BCBA | BCBA | 01/14/2019 |
| CUMMINGS, KYLEIGH | APPLE VALLEY, CA | - | Clinical Social Worker | 08/06/2018 |
| CUMMINGS, SHANNON | YARMOUTH, ME | LCPC | Professional Counselor | 03/04/2025 |
| CUMMINGS, SHAUN | AKRON, OH | - | Professional Counselor | 09/25/2026 |
| CUNNINGHAM, BELLE | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| CUNNINGHAM, ISIS | RIALTO, CA | - | Case Manager/Care Coordinator | 08/29/2018 |
| CUNNINGHAM, JAKYLA | SAN BERNARDINO, CA | - | RBT | 09/25/2026 |
| CUNNINGHAM, MONIKA | WOODBRIDGE, NJ | LSW | Clinical Social Worker | 09/24/2026 |
| CUNNINGHAM, MORGAN | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| CUNNINGHAM, RORY | CHICAGO, IL | LCSW | Clinical Social Worker | 09/25/2026 |
| CUNNINGHAM, SIOBHAN | PALMER, AK | LCSW | Clinical Social Worker | 02/11/2013 |
| CUREXIS MEDICAL LLCORG | HOUSTON, TX | - | Clinic/Center | 07/09/2026 |
| CURLEY, KATHLEEN | BROCKTON, MA | - | Clinical Social Worker | 11/12/2021 |
| CURLIS, SUZANNE | DAVIS, CA | - | Speech-Language Pathologist | 09/24/2026 |
| CURRAN, ADDISON | WORTHINGTON, OH | LPCC | Mental Health Counselor | 02/21/2023 |
| CURRIER, DANIELLE | BELEN, NM | - | RBT | 09/24/2026 |
| CURRIER, MARCEL | LECANTO, FL | LCSW | Clinical Social Worker | 10/19/2022 |
| CURRY, MADISON | PETALUMA, CA | - | Mental Health Counselor | 09/01/2026 |
| CURTIS, KIRSTEN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| CUSACK, JENNA | WAUWATOSA, WI | APSW | Clinical Social Worker | 09/21/2026 |
| CUSHING, CRISTAL | DEARBORN, MI | - | RBT | 09/23/2026 |
| CUSPILICH, SAMANTHA | TAMPA, FL | - | Speech-Language Pathologist | 09/25/2026 |
| CUSTODIO, LILYNN | MONCKS CORNER, SC | - | Mental Health Counselor | 09/22/2026 |
| CUSUMANO, VICTORIA | MELVILLE, NY | - | RBT | 09/23/2026 |
| CUTLER, ELIJAH | DURHAM, NC | LCSWA | Clinical Social Worker | 09/21/2026 |
| CUTSHALL, KAYLA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| CYPLIK, MEGHAN | VIRGINIA BEACH, VA | M.S, CCC-SLP | Speech-Language Pathologist | 09/23/2014 |
| D.O.V.E. COUNSELING LLCORG | OMAHA, NE | - | Mental Health Counselor | 08/25/2026 |
| D&D REHAB CENTER, INCORG | HIALEAH, FL | - | Clinic/Center | 06/03/2013 |
| DA COSTA, LUCAS | RENO, NV | - | RBT | 07/21/2025 |
| DA CUNHA, CARLA | CHICAGO, IL | LCPC | Mental Health Counselor | 01/15/2020 |
| DABAGHIAN, JASON | SACRAMENTO, CA | - | RBT | 09/22/2026 |
| DABBS, KRISTEN | MISSOULA, MT | LCPC | Professional Counselor | 09/27/2024 |
| DACUS, REBECCA | BOISE, ID | LPC | Mental Health Counselor | 09/01/2022 |
| DAGLE, SAMANTHA | PALM BEACH GARDENS, FL | LCSW | Clinical Social Worker | 09/23/2026 |
| DAHABRA, TALA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| DAHL, KYLEIGH | MANDAN, ND | - | Speech-Language Pathologist | 09/23/2026 |
| DAHL, MCKENZIE | LAKEWOOD, CO | RBT | RBT | 01/10/2022 |
| DAHL, TESS | WYOMISSING, PA | - | RBT | 09/22/2026 |
| DAHL, TRUDY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| DAHLMAN, AMANDA | GERMANTOWN, WI | LPC | Mental Health Counselor | 06/16/2026 |
| DAHODWALA, AMATULLAH | BURR RIDGE, IL | MS, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| DAIGLE, CODY | WHITEHALL, OH | - | Case Manager/Care Coordinator | 08/05/2026 |
| DAIGLE, SAVANNAH | SEARCY, AR | LCSW | Clinical Social Worker | 09/25/2026 |
| DAKANE, FATHI | BURNSVILLE, MN | - | RBT | 01/11/2023 |
| DALE, TAYLOR | MORGANTON, NC | LCSW, LCAS | Clinical Social Worker | 07/29/2022 |
| DALEY-MARTIN, SHERIKA | CHAMPIONS GATE, FL | - | RBT | 09/21/2026 |
| DALEY, SOLVEIG | TORRANCE, CA | - | RBT | 09/21/2026 |
| DALLAS COUNTY HOSPITAL DISTRICTORG | FARMERS BRANCH, TX | - | Psychologist | 06/01/2006 |
| DALLAS COUNTY HOSPITAL DISTRICTORG | DALLAS, TX | - | Clinical Social Worker | 08/15/2014 |
| DALLAS COUNTY HOSPITAL DISTRICTORG | DALLAS, TX | - | Clinical Social Worker | 08/14/2014 |
| DALLAS COUNTY HOSPITAL DISTRICTORG | DALLAS, TX | - | Counselor | 07/13/2021 |
| DALLAS COUNTY HOSPITAL DISTRICTORG | DALLAS, TX | - | Counselor | 08/06/2021 |
| DALLETT, MAYA | HAYWARD, CA | - | RBT | 09/22/2026 |
| DALLI, CARLA | CARY, NC | CCC-SLP | Speech-Language Pathologist | 02/07/2007 |
| DALLOZZI, MYCH-JARROD | MINNEAPOLIS, MN | PSYD, NCC, LPCC | Professional Counselor | 02/28/2019 |
| DAMIA, CHRISTINA | CERRITOS, CA | MSW | Mental Health Counselor | 11/02/2006 |
| DAMIAN MORAN, GIOVANI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| DAMIANO, NYAH | WYOMISSING, PA | - | RBT | 09/22/2026 |
| DAMJI, NOORIN | DURHAM, NC | MD | Counselor | 07/05/2016 |
| DANACEAU, ELIZABETH | GREENWOOD VILLAGE, CO | MA, LPC | Professional Counselor | 11/07/2006 |
| DANDA, ANDREA | MINNEAPOLIS, MN | LPCC, LADC | Mental Health Counselor | 09/23/2015 |
| DANG, JONATHAN | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| DANIEL, CHRISTINE | CRANFORD, NJ | - | Mental Health Counselor | 09/23/2026 |
| DANIEL, CLAIRE | KENNETT SQUARE, PA | - | BCBA | 06/03/2024 |
| DANIEL, HERRAN | ORANGE, CA | - | RBT | 09/22/2026 |
| DANIELS, ALEXIS | METAMORA, MI | - | RBT | 06/01/2018 |
| DANIELS, ELIZABETH | SPOKANE, WA | M.A., LMHC | Mental Health Counselor | 12/02/2008 |
| DANIELS, JENNIFER | ALBUQUERQUE, NM | - | Case Manager/Care Coordinator | 09/21/2026 |
| DANKS, SARAH | INDIANAPOLIS, IN | - | RBT | 09/25/2026 |
| DANKYI, SAMUEL | STOCKTON, CA | - | Day Training/Habilitation Specialist | 07/16/2025 |
| DANOFF, ALEXA | NEW YORK, NY | PHD | Psychologist | 09/24/2026 |
| DANSIN, INCORG | CHULA VISTA, CA | - | Specialist | 02/15/2008 |
| DANSO, REBECCA | NEW HAVEN, CT | - | Mental Health Counselor | 05/09/2023 |
| DAOUST, LINDSEY | ALPENA, MI | - | Clinical Social Worker | 08/24/2018 |
| DARDEN, QUIANA | BEDFORD, TX | LPC | Professional Counselor | 02/11/2022 |
| DARGOLTZ, SIMMONE | AVENTURA, FL | - | Mental Health Counselor | 06/07/2016 |
| DARMODY, CAMERON | HENDERSON, NV | - | Specialist | 09/25/2026 |
| DARNELL, JOSHUA | BECKLEY, WV | - | Mental Health Counselor | 09/21/2026 |
| DARNER, STEPHANIE | COLUMBUS, OH | MSW/LISW | Clinical Social Worker | 09/21/2026 |
| DARRAH, RENAE | OMAHA, NE | LICSW | Clinical Social Worker | 01/17/2019 |
| DARROW, DORIEN | SANTA MARIA, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| DASARO, LOIS | SANTA MONICA, CA | PHD | Psychologist | 04/04/2007 |
| DASCHIL, LILLIANNA | FAIR LAWN, NJ | - | BCBA | 09/23/2026 |
| DATINO, ANTHONY | LITTLETON, CO | - | Mental Health Counselor | 09/23/2026 |
| DAUBER, AUBREY | SPOKANE, WA | PHD | Psychologist | 09/08/2025 |
| DAUGHERTY, SIOBHAN | SAN DIEGO, CA | AMFT | Mental Health Counselor | 09/21/2026 |
| DAUGHERTY, TIERZAH | LANSING, MI | LMHC | Counselor | 08/27/2015 |
| DAUMONT ORTIZ, CLAUDETTE | FORT LEONARD WOOD, MO | - | RBT | 09/22/2026 |
| DAVEY, ZONAE | CHARLOTTE, NC | - | Case Manager/Care Coordinator | 09/21/2026 |
| DAVID, ALANA | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| DAVID, CYDEL | DUNCANVILLE, TX | BCBA | BCBA | 12/09/2025 |
| DAVID, SHARLA ISABEL | MONROVIA, CA | - | RBT | 09/24/2026 |
| DAVIDSON, AMANDA | AUSTIN, TX | LPC | Professional Counselor | 12/17/2018 |
| DAVIDSON, JEREMIAH | MODESTO, CA | - | RBT | 09/21/2026 |
| DAVIDSON, KIMBERLIE | FOUNTAIN INN, SC | LPC | Counselor | 09/16/2024 |
| DAVIES, SERENA | COCOA, FL | - | RBT | 09/23/2026 |
| DAVIGNON, SUZANNE | ROCK HILL, SC | LAC-S | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| DAVIS-GENTRY, HANNAH | LANCASTER, PA | MS, LPC, NCC | Professional Counselor | 09/21/2026 |
| DAVIS, AAMYAH | SAN DIEGO, CA | - | RBT | 09/22/2026 |
| DAVIS, BRANDON | SILVER SPRING, MD | PSYD | Psychologist | 03/01/2011 |
| DAVIS, CADENCE | NEW YORK, NY | - | Clinical Social Worker | 09/24/2026 |
| DAVIS, CHELSEA | YOUNGSTOWN, OH | - | RBT | 09/23/2026 |
| DAVIS, COLLIN | HOUSTON, TX | LPC | Professional Counselor | 08/03/2021 |
| DAVIS, HANNAH | MODESTO, CA | - | RBT | 09/23/2026 |
| DAVIS, JASMINE | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| DAVIS, JORDAN | PITTSBURGH, PA | - | RBT | 09/21/2026 |
| DAVIS, KATHRYN | COLUMBUS, GA | LCSW | Clinical Social Worker | 08/17/2015 |
| DAVIS, KATREESE | BROOKLYN, NY | - | Clinical Social Worker | 09/24/2026 |
| DAVIS, KERA | GULFPORT, MS | - | RBT | 09/22/2026 |
| DAVIS, KYLE | DILLINGHAM, AK | M.A., CDC 1, BHA III | Addiction (Substance Use Disorder) Counselor | 07/17/2023 |
| DAVIS, LAKEVIA | MONTGOMERY, AL | BCBA, LBA | BCBA | 09/24/2026 |
| DAVIS, LATOYA | LAS VEGAS, NV | - | RBT | 09/14/2022 |
| DAVIS, LOGAN | NEWBURGH, IN | - | RBT | 09/22/2026 |
| DAVIS, MAEGAN | WEST PALM BEACH, FL | - | Mental Health Counselor | 06/25/2024 |
| DAVIS, MATTHEW | MESA, AZ | LAC | Mental Health Counselor | 07/14/2020 |
| DAVIS, NICOLE | SAINT MICHAEL, MN | CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| DAVIS, PORTIA | TUCSON, AZ | LPC | Professional Counselor | 09/12/2025 |
| DAVIS, PRESTON | CHEYENNE, WY | - | Speech-Language Pathologist | 09/25/2026 |
| DAVIS, RYAN | IONIA, MI | LPC | Professional Counselor | 11/13/2020 |
| DAVIS, SARAH | ALEDO, TX | M.S. CCC-SLP | Speech-Language Pathologist | 09/16/2014 |
| DAVIS, SHAYBRE | HOLLYWOOD, FL | - | Assistant Behavior Analyst | 09/30/2022 |
| DAVIS, SHENICA | DETROIT, MI | - | RBT | 02/27/2018 |
| DAVIS, SIERRA | UNCASVILLE, CT | LPC | Mental Health Counselor | 06/05/2023 |
| DAVIS, YANCY | RALEIGH, NC | D. MIN, CRAADC, LCAS | Addiction (Substance Use Disorder) Counselor | 05/30/2025 |
| DAVISON, MARIO | COLUMBUS, OH | - | Case Manager/Care Coordinator | 07/21/2018 |
| DAWKINS, SAMANTHA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| DAWN, BRESCIA | LONGMONT, CO | - | Speech-Language Pathologist | 09/30/2024 |
| DAWRA, RADHIKA | MILLBURN, NJ | LPC | Professional Counselor | 11/28/2023 |
| DAWSON JENKINS, NEISHA | CHARLOTTE, NC | LCMHC | Mental Health Counselor | 02/26/2022 |
| DAWSON, DEIRDRE | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 09/24/2026 |
| DAWSON, KRISTEANA | PHILADELPHIA, PA | - | BCBA | 04/11/2017 |
| DAWSON, RYAN | PORTLAND, OR | LCSW | Clinical Social Worker | 10/31/2021 |
| DAY, YAPREE | EVERGREEN PK, IL | - | RBT | 09/21/2026 |
| DAYTON PAIN CENTER LLCORG | DAYTON, OH | - | Addiction (Substance Use Disorder) Counselor | 11/13/2017 |
| DE CARDENAS BEHAVIORAL HEALTH SERVICES INC.ORG | MIAMI, FL | - | Mental Health Counselor | 08/27/2026 |
| DE CARDENAS, LORENA | MIAMI, FL | LMHC | Mental Health Counselor | 06/24/2021 |
| DE DIOS-MANALOTO, CATHERINE LOUISE | CULVER CITY, CA | ASW | Clinical Social Worker | 09/04/2018 |
| DE HAAN, LAUREN | KALAMAZOO, MI | - | RBT | 09/09/2026 |
| DE JESUS, PAOLA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| DE LA CRUZ COMPRES, RUTH | PORT SAINT LUCIE, FL | - | Case Manager/Care Coordinator | 09/18/2026 |
| DE LA CRUZ, ANGELINE | CHICAGO, IL | - | RBT | 09/22/2026 |
| DE LA CRUZ, KCARIN | BRONXVILLE, NY | - | Clinical Social Worker | 11/14/2013 |
| DE LA CRUZ, THOMAS | OXNARD, CA | - | RBT | 05/28/2026 |
| DE LA GARZA, JOSHUA | COLLEGE STATION, TX | LPC | Mental Health Counselor | 09/22/2026 |
| DE LA PAZ, NOAH | ORANGE, CA | - | RBT | 09/01/2026 |
| DE LA ROSA, BRENDA | EL PASO, TX | LPC-A | Professional Counselor | 03/24/2026 |
| DE LA ROSA, IVAN | BROOKLYN, NY | - | Mental Health Counselor | 09/23/2026 |
| DE LA ROSA, MIRIAM | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| DE LEON, KRISTEN ANNE | SAN DIEGO, CA | - | Speech-Language Pathologist | 09/23/2026 |
| DE MEDEIROS VECCHI, LARISSA | HYRUM, UT | CSW | Clinical Social Worker | 11/25/2025 |
| DEAL, KIERSTIN | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| DEAN, CRYSTAL | AKRON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| DEANER, ALYXANDRE | AUBURN HILLS, MI | LPC | Professional Counselor | 12/27/2019 |
| DEBEAUCOURT, DAVID | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| DEBELLE, MAKALEE | IRONTON, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| DEBORAH WHALEN LCSW & DEBORAH WHALEN EQUINE, LLCORG | LAMY, NM | - | Clinical Social Worker | 02/12/2013 |
| DEBRAH, MAAME AMA | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| DEBRAMALETTA, MIKAYLA | DENVER, CO | - | RBT | 09/22/2026 |
| DECKMAN, KIMBERLY | EUREKA, CA | CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| DECRU, NATHANIEL | SPRINGFIELD, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| DEE, BAILEY | MAPLE GROVE, MN | - | BCBA | 01/13/2020 |
| DEEBRAH, MIRANDA | BRONX, NY | LCSW | Clinical Social Worker | 11/16/2021 |
| DEECE, PRECIOUS | GARDEN CITY, MI | - | RBT | 09/23/2026 |
| DEEN, ALIZA | MIDDLETOWN, NY | LMSW | Mental Health Counselor | 06/07/2021 |
| DEEP WATERS THERAPY PLLCORG | COMPTON, IL | - | Clinical Social Worker | 09/14/2026 |
| DEEPIKA SAINI MEDICAL CORPORATIONORG | VICTORVILLE, CA | - | Clinic/Center | 12/08/2025 |
| DEERING, DA'YONA | ZIONSVILLE, IN | - | RBT | 09/22/2026 |
| DEFAZIO, NOAH | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| DEFELICE, WILLIAM | YOUNGSTOWN, OH | LPCC AND LICDC-CS | Professional Counselor | 04/19/2007 |
| DEFINO, ANNIKA | IRVING, TX | - | BCBA | 09/23/2026 |
| DEFLANDERS, KEONDRE | COLUMBIA, SC | MS, BCBA | BCBA | 02/17/2021 |
| DEGADO, ANNABELLE | SPOKANE, WA | MSW | Counselor | 09/22/2026 |
| DEGRANGE, LAUREN | AUGUSTA, ME | PMHNP, LCSW, RN | Clinical Social Worker | 12/26/2018 |
| DEHNERT, JILL | SILVIS, IL | - | Mental Health Counselor | 09/24/2026 |
| DEISHER, NICOLE | MANSFIELD, OH | LISW-S | Clinical Social Worker | 06/08/2015 |
| DEITZ, AMANDA | SUMMERSVILLE, WV | - | Counselor | 09/23/2026 |
| DEJNO, MORGAN | CHANDLER, AZ | - | Speech-Language Pathologist | 07/20/2022 |
| DEJOHNETTE, KEANDRA | MISHAWAKA, IN | - | RBT | 09/23/2026 |
| DEKKER, KERSTEN | JACKSON, MI | MSW INTERN | Clinical Social Worker | 01/28/2026 |
| DEL MUNDO, VIRGILIE ALYANA | LATHROP, CA | - | BCBA | 07/09/2021 |
| DELA CRUZ, ANGELINA | NEWARK, CA | - | RBT | 07/02/2026 |
| DELA CRUZ, ANNE | FONTANA, CA | - | RBT | 09/22/2026 |
| DELA CRUZ, KYLIE | AIEA, HI | - | RBT | 09/22/2026 |
| DELA CRUZ, MALIA | ONTARIO, CA | - | RBT | 09/22/2026 |
| DELACRUZ, CARLOS | LITTLETON, CO | - | Mental Health Counselor | 09/21/2026 |
| DELACRUZ, ISIDORA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| DELANIE SUBSTANCE ABUSE COUNSELING & WELLNESS INCORG | TAMPA, FL | - | Addiction (Substance Use Disorder) Counselor | 10/25/2024 |
| DELANIE SUBSTANCE ABUSE COUNSELING & WELLNESS INCORG | TAMPA, FL | - | Mental Health Counselor | 09/23/2026 |
| DELEMOS, DANA | ALLENTOWN, PA | - | Mental Health Counselor | 06/24/2019 |
| DELEON, ANGELA | TEMECULA, CA | - | RBT | 09/22/2026 |
| DELEON, KLARETH | SHERMAN OAKS, CA | - | RBT | 09/21/2026 |
| DELEON, RENE | TORRANCE, CA | - | RBT | 09/21/2026 |
| DELGADILLO, JENNIFER | ALAMEDA, CA | BCBA | RBT | 08/29/2019 |
| DELGADO CRUZ, LUZ | MODESTO, CA | - | RBT | 09/21/2026 |
| DELGADO-PEREZ, LIZBETH | DUBLIN, CA | - | RBT | 09/21/2026 |
| DELISLE, LOREN | MOUNT PLEASANT, SC | - | Speech-Language Pathologist | 07/29/2021 |
| DELLEDONNE, KELLY | POINT PLEASANT BORO, NJ | LCSW | Clinical Social Worker | 05/12/2016 |
| DELP, EMILIE | BELLEVILLE, IL | LCSW | Clinical Social Worker | 09/17/2024 |
| DEMAIO, ANDREA | ORLANDO, FL | RCMHI | Mental Health Counselor | 09/23/2026 |
| DEMAIORIBUS, LILY | DENVER, CO | - | RBT | 09/23/2026 |
| DEMARCO, ELVIRA | CUMBERLAND, RI | - | Mental Health Counselor | 06/22/2011 |
| DEMARINO, VERONICA | ROSEBURG, OR | QMHA-R | Counselor | 09/24/2026 |
| DEMELO, RUTH | ACWORTH, GA | MS, CF | Speech-Language Pathologist | 09/22/2026 |
| DEMINO, ANTONIETTA | PIKESVILLE, MD | - | RBT | 09/22/2026 |
| DEMMERS, BETHANI | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| DEMPSEY, STEPHANIE | MADISON, AL | BCBA | BCBA | 10/20/2022 |
| DENARIE, MARIE-CHRISTINE | MOORESVILLE, NC | BCBA | BCBA | 07/21/2022 |
| DENBY, BRITTANY | DANSVILLE, NY | LMSW | Clinical Social Worker | 06/27/2023 |
| DENEGA, KELLY | CLIFTON, NJ | - | Speech-Language Pathologist | 10/17/2016 |
| DENMARK, ANNABELLE | DENVER, CO | LPC | Professional Counselor | 01/18/2023 |
| DENNIS, ANGELA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| DENNIS, KIMBERLY | BAYPORT, NY | - | RBT | 09/22/2026 |
| DENNY, ASTRIANNA | AIEA, HI | - | RBT | 09/21/2026 |
| DENVER HYPERBARIC CENTER INC.ORG | CENTENNIAL, CO | - | Clinic/Center | 09/11/2026 |
| DEO, SAVITA | CASTRO VALLEY, CA | - | Day Training/Habilitation Specialist | 09/25/2026 |
| DEPIERRO, MARIA | MIAMI LAKES, FL | - | RBT | 09/24/2026 |
| DEROIN, KIM | TULSA, OK | - | Case Manager/Care Coordinator | 09/30/2022 |
| DERRICK MILLER PLLCORG | RAMONA, CA | - | Clinical Social Worker | 08/23/2019 |
| DERRICK, TIFFANY | GAINESVILLE, GA | NCC, LPC, LCPC | Mental Health Counselor | 01/17/2012 |
| DESERT GRIT MENTAL HEALTH LLCORG | LAS VEGAS, NV | - | Mental Health Counselor | 11/23/2020 |
| DESERT ROSE COUNSELING, LLCORG | COLUMBIA, SC | - | Professional Counselor | 09/25/2026 |
| DESGROSELLIER, LISA | SPOKANE VALLEY, WA | LMHC | Mental Health Counselor | 12/28/2024 |
| DESHAY, ALYSSA | INDEPENDENCE, MO | - | Speech-Language Pathologist | 09/24/2026 |
| DESHINCOE, ANGELICA | LAKEWOOD, CO | - | Case Manager/Care Coordinator | 09/25/2026 |
| DESIR, MICHELLE | NEW YORK, NY | L.C.S.W. | Clinical Social Worker | 12/11/2006 |
| DESLAURIERS, LINDSEY | NORWELL, MA | - | Specialist | 09/23/2026 |
| DESROCHES, FREDLYNE | BAYPORT, NY | - | RBT | 09/23/2026 |
| DESROSIERS, MEGAN | TAMPA, FL | M.A., LMHC, CAP | Mental Health Counselor | 05/28/2008 |
| DEVAUGHN, LATOYA | MAUMEE, OH | - | Case Manager/Care Coordinator | 06/28/2021 |
| DEVER, DANETTE | MARIETTA, GA | M.ED., LPC | Professional Counselor | 04/24/2008 |
| DEVITO, RUTH | WAKE FOREST, NC | M.A | Professional Counselor | 11/18/2013 |
| DEVORAH KOSOWSKY, LMHC, LLCORG | SHARON, MA | - | Mental Health Counselor | 09/21/2026 |
| DEVORKIN, ISABEL | SARASOTA, FL | - | Mental Health Counselor | 05/20/2022 |
| DEWALL, SHAWN | PORTLAND, OR | - | Professional Counselor | 02/25/2022 |
| DEWITT, LAUREN | SAVANNAH, GA | - | RBT | 09/17/2024 |
| DEWSON, ERIN | WEST DEPTFORD, NJ | - | Mental Health Counselor | 09/22/2026 |
| DEYAPP, LENA | ALBUQUERQUE, NM | - | Mental Health Counselor | 09/23/2026 |
| DGP HEALTH & WELLNESS, CORPORG | DELRAY BEACH, FL | - | Case Management Agency | 06/15/2023 |
| DHALIWAL, NAVJIND | HAUPPAUGE, NY | - | Specialist | 09/21/2026 |
| DIALLO, FATOUMATA | BRONX, NY | - | Counselor | 09/22/2026 |
| DIAMOND DOGS COUNSELING GROUP PLLCORG | PITTSFIELD, MA | - | Clinical Social Worker | 08/24/2026 |
| DIAMOND HEALTH & WELLNESSORG | HOUSTON, TX | - | Mental Health Counselor | 09/21/2026 |
| DIAMOND, TAYLOR | WACO, TX | - | Clinical Social Worker | 09/25/2026 |
| DIAZ ABREU, LAURA | MIAMI, FL | RBT | Mental Health Counselor | 03/24/2022 |
| DIAZ BATISTA, IVETTE | ORLANDO, FL | LCSW | Clinical Social Worker | 02/12/2020 |
| DIAZ HERNANDEZ, KRYSTAL | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| DIAZ LEYVA, DAYANE | MIAMI, FL | - | RBT | 03/09/2017 |
| DIAZ NIETO, JORGE | MIAMI, FL | - | RBT | 07/31/2026 |
| DIAZ PEREZ, ISELA | CAMPBELL, CA | - | RBT | 09/22/2026 |
| DIAZ PORTORREAL, PAMELA | WORCESTER, MA | - | RBT | 09/21/2026 |
| DIAZ VAZQUEZ, KARLA | LISLE, IL | - | RBT | 09/21/2026 |
| DIAZ-SORIANO, STEPHANIE | CHICAGO, IL | CCC-SLP/L | Speech-Language Pathologist | 12/27/2023 |
| DIAZ, AURORA | RIVERSIDE, CA | - | RBT | 12/16/2020 |
| DIAZ, CHRISTIAN | LOS ANGELES, CA | B.A. SOCIAL WORK | Clinical Social Worker | 06/29/2022 |
| DIAZ, CIARRA | CHAMPIONS GATE, FL | - | RBT | 08/05/2024 |
| DIAZ, DANAI | TAMPA, FL | PHD, BCBA | BCBA | 05/23/2007 |
| DIAZ, DANIELLE | NEW YORK, NY | - | Mental Health Counselor | 05/04/2023 |
| DIAZ, EDGARDO | MCCHORD AFB, WA | MS, CAADC | Professional Counselor | 08/28/2025 |
| DIAZ, GLADIS | LANCASTER, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| DIAZ, IRAIDA | MIAMI, FL | - | RBT | 11/29/2017 |
| DIAZ, JEANETTE | LOS RANCHOS, NM | LMHC | Mental Health Counselor | 09/22/2026 |
| DIAZ, JOSHUA | DOYLESTOWN, PA | - | BCBA | 12/12/2023 |
| DIAZ, KELLCY | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| DIAZ, LAUREN | HOBART, IN | - | BCBA | 07/02/2025 |
| DIAZ, MARIANA | YUMA, AZ | - | Speech-Language Pathologist | 03/09/2022 |
| DIAZ, MIGUEL | SHERMAN OAKS, CA | M.S. | RBT | 09/26/2026 |
| DIAZ, PEDRO | NEWPORT BEACH, CA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| DIAZ, SERENA | ADDISON, IL | - | Clinical Social Worker | 04/29/2025 |
| DIAZ, TIANA | BROOKLYN, NY | - | Professional Counselor | 06/05/2025 |
| DIAZ, YESENIA | DELANO, CA | - | Clinical Social Worker | 12/07/2022 |
| DIBARTOLO, DEBRA | ITHACA, NY | FNP, PMHNP | Addiction (Substance Use Disorder) Counselor | 07/06/2011 |
| DICK, GAVIN | ONTARIO, CA | - | RBT | 09/22/2026 |
| DICKERSON, ROBERT | TUCSON, AZ | - | RBT | 09/21/2026 |
| DICKERSON, TAMYKA | INDIANAPOLIS, IN | - | RBT | 09/25/2026 |
| DICKEY, WILLOE | KOKOMO, IN | - | BCBA | 01/14/2025 |
| DICKINSON, ANNA | CONWAY, SC | - | Mental Health Counselor | 08/26/2021 |
| DICKINSON, HEIDI | MARQUETTE, MI | - | Clinical Social Worker | 09/23/2026 |
| DICKINSON, LAURA | CONWAY, AR | - | Mental Health Counselor | 09/21/2026 |
| DICKINSON, MADILINE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| DICKSON, MADISON | CONWAY, AR | - | RBT | 09/22/2026 |
| DICKSON, SYDNEY | QUAKERTOWN, PA | - | Counselor | 09/25/2026 |
| DIEP, JENNIFER | COVINA, CA | - | RBT | 09/23/2026 |
| DIEP, SHEILA | DULUTH, MN | - | RBT | 09/21/2026 |
| DIETZ, AMY | SOUTH LYON, MI | - | Speech-Language Pathologist | 09/22/2026 |
| DIETZEL, ASHLEY | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| DIGATONO, DANIEL | SIOUX FALLS, SD | PHD,LMFT,LPC | Professional Counselor | 04/20/2006 |
| DIGGS, OSCSHIVELLA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| DIGIORGI, NICHOLAS | ROCKVILLE CENTRE, NY | - | Mental Health Counselor | 03/26/2026 |
| DIGNITY IN ACTIONORG | CALIFORNIA CITY, CA | - | Community/Behavioral Health Agency | 09/26/2026 |
| DILEO, MARCOLENA | LAS VEGAS, NV | - | RBT | 09/23/2026 |
| DILI, JEAN | DENVER, CO | BC-DMT, LPC | Professional Counselor | 03/05/2007 |
| DILIBERTO, ZACK | WOODLAND HILLS, CA | SUDCCIII (12062) | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| DILL, CHELSEA | FT CARSON, CO | SLP | Speech-Language Pathologist | 06/30/2020 |
| DILLARD, MARIKA | ASHEVILLE, NC | - | Clinical Social Worker | 09/19/2018 |
| DILLON, DAX | PHOENIX, AZ | LAC | Mental Health Counselor | 09/21/2026 |
| DILLON, EMMA | SEATTLE, WA | - | Counselor | 09/21/2026 |
| DILLS, SHELBY | CLEVELAND, TN | BEHAVIOR TECHNICIAN | RBT | 09/21/2026 |
| DIMINO, PHILLIP | PUEBLO, CO | - | RBT | 09/22/2026 |
| DINGY, ALEXIS | CANANDAIGUA, NY | LCSW | Clinical Social Worker | 02/02/2021 |
| DIPASALEGNE, MONIQUE | LINTHICUM HEIGHTS, MD | LCSW-C | Clinical Social Worker | 10/09/2018 |
| DIPESH PATEL LCSW COUNSELING SERVICESORG | CHICAGO, IL | - | Clinical Social Worker | 09/21/2026 |
| DIRIYE, FILSAN | COON RAPIDS, MN | - | RBT | 06/16/2026 |
| DIRIYE, ZAMZAM | VANCOUVER, WA | - | RBT | 09/21/2026 |
| DISALVO, ELISSA | LINDENHURST, NY | - | Specialist | 09/21/2026 |
| DISILVIO, JACQUELYN | PITTSBURGH, PA | - | Mental Health Counselor | 09/21/2026 |
| DISON, ALANA | METAIRIE, LA | - | BCBA | 12/15/2020 |
| DISS, ANNA | SEATTLE, WA | M.S. CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| DISTLE, WILLIAM | MONTROSE, CO | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| DIVERGE AND BLOOM COUNSELING, PLLCORG | DALLAS, TX | - | Community/Behavioral Health Agency | 09/25/2026 |
| DIVERGENT MINDS COLLECTIVEORG | PUYALLUP, WA | - | Mental Health Counselor | 04/23/2026 |
| DIVINE INTERVENTIONISTORG | CHARLOTTE, TN | - | Community/Behavioral Health Agency | 07/23/2026 |
| DIVINE PROVIDENCE HEALTH RESOURCES INCORG | SUGAR LAND, TX | - | Case Management Agency | 05/11/2020 |
| DIVINO, LILY ANN | FLUSHING, NY | LCSW, MPH | Clinical Social Worker | 09/14/2006 |
| DIXON, ELIJAH | NORMAN, OK | - | Mental Health Counselor | 09/25/2026 |
| DIXON, ELIZABETH | CHARLOTTESVILLE, VA | LPC | Professional Counselor | 03/30/2023 |
| DIXON, EQUISHA | SUGAR LAND, TX | - | Assistant Behavior Analyst | 05/20/2026 |
| DIXON, IREON | METAIRIE, LA | - | RBT | 09/21/2026 |
| DIXON, MIKAELA | LOS ALTOS, CA | - | Clinical Social Worker | 05/07/2025 |
| DJUIKOUA EYANGO, JUDITH | WASHINGTON, DC | - | Case Manager/Care Coordinator | 05/23/2019 |
| DO, RENE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| DOBBINS, NICOLE | MOUNT LAUREL, NJ | LBA | BCBA | 09/24/2026 |
| DOBBS, AMBER | KILLEEN, TX | LPC ASSOCIATE 102786 | Professional Counselor | 06/22/2026 |
| DOBRZYNSKI, HALEY | MASON, OH | LPC | Professional Counselor | 06/14/2022 |
| DOC EASE LLCORG | DALLAS, TX | - | Clinic/Center | 06/16/2025 |
| DOCAUER, AIMEE | CHICAGO, IL | - | Speech-Language Pathologist | 04/21/2026 |
| DODD, ISABEL | KILLEEN, TX | - | RBT | 09/23/2026 |
| DODGE, DAMON | TORRANCE, CA | - | RBT | 09/23/2026 |
| DODGE, FRED | MERIDIAN, ID | LCSW | Clinical Social Worker | 05/04/2022 |
| DODGE, SHELLEY | ZANESVILLE, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| DODHIYA, NASHEEL | STAFFORD, TX | - | RBT | 05/17/2022 |
| DODSON, ASHLEY | GRAND RAPIDS, MI | - | RBT | 09/24/2026 |
| DODSON, JACOB | COLUMBUS, OH | LPCC | Professional Counselor | 11/22/2022 |
| DODSON, JODY | SMYRNA, GA | APC, CTP, NCC | Professional Counselor | 09/22/2026 |
| DOGBE-FOLLY, MELBA | CENTREVILLE, VA | LPC | Mental Health Counselor | 12/14/2021 |
| DOLAN-BOPP, BAILEY | NAMPA, ID | - | RBT | 09/24/2026 |
| DOLAN, BREANNA | KALAMAZOO, MI | - | RBT | 09/23/2026 |
| DOLAN, ERIN | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| DOLE, MENTEE | RIVERVIEW, FL | BEHAVIOR TECHNICIAN | RBT | 09/21/2026 |
| DOLLAR, BETHANY | VALDOSTA, GA | LCSW | Clinical Social Worker | 12/10/2010 |
| DOLLAR, CHARLOTTE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| DOMINGUEZ-MARTIN, JENNIFER | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| DOMINGUEZ, KENNEDY | WASCO, CA | - | Clinical Social Worker | 08/26/2024 |
| DOMINGUEZ, SABRINA | BOCA RATON, FL | - | RBT | 08/13/2019 |
| DOMINICUS HEALTHCARE SERVICES LLCORG | BOWIE, MD | - | Community/Behavioral Health Agency | 09/25/2026 |
| DOMONDON, CANDICE | TEMECULA, CA | - | RBT | 02/28/2019 |
| DONALDSON, LASWANNA | CORDOVA, TN | LCSW | Clinical Social Worker | 03/19/2007 |
| DONLEY, DEBORAH | SPOKANE VALLEY, WA | - | RBT | 09/21/2026 |
| DONNELLAN, HEIDI | PLAINVILLE, MA | LICSW | Clinical Social Worker | 03/29/2006 |
| DONNELLY, JEREMY | ELLSWORTH, ME | - | Clinical Social Worker | 04/15/2024 |
| DONOSO, SOFIA | VICTORVILLE, CA | - | RBT | 09/22/2026 |
| DONOVAN, ELLA | EVERGREEN PARK, IL | - | RBT | 09/21/2026 |
| DOO, CHRISTOPHER | PORTLAND, OR | MSW | Clinical Social Worker | 08/17/2026 |
| DOOLAN, LUCAS | SAN FRANCISCO, CA | - | BCBA | 11/30/2021 |
| DORAN, JENNIFER | ARLINGTON HEIGHTS, IL | MA, NCC | Professional Counselor | 09/19/2022 |
| DORAN, KRISTINA | CENTENNIAL, CO | - | Mental Health Counselor | 05/04/2023 |
| DOSS, JAMIE | GRANITE CITY, IL | LCPC | Counselor | 10/22/2021 |
| DOSSMAN, CERISE | LONG BEACH, CA | - | Clinical Social Worker | 06/15/2023 |
| DOTSON, JENNIFER | TAYLORSVILLE, UT | LCSW | Clinical Social Worker | 05/29/2019 |
| DOTY, AMANDA | SACRAMENTO, CA | - | Case Manager/Care Coordinator | 11/28/2007 |
| DOUBLE TALK THERAPY, PLLCORG | MCKINNEY, TX | - | Speech-Language Pathologist | 06/15/2021 |
| DOUGE, MARIE JODELLE | ORLANDO, FL | - | RBT | 07/01/2024 |
| DOUGHERTY, MARLENA | BELLINGHAM, WA | LMHCA | Mental Health Counselor | 11/28/2025 |
| DOUGHTY, ZAIRA | BROOMALL, PA | - | RBT | 09/23/2026 |
| DOUGLAS, ASHLAY | NEW ORLEANS, LA | LCSW | Clinical Social Worker | 09/23/2026 |
| DOUGLAS, BRIANNA | FRISCO, TX | - | RBT | 09/25/2026 |
| DOUGLAS, BYRON | GLASGOW, KY | LPCC-S | Professional Counselor | 03/25/2009 |
| DOUGLAS, JANE | WAREHAM, MA | MSW, LCSW | Clinical Social Worker | 09/14/2026 |
| DOUGLAS, KIARA | COLORADO SPRINGS, CO | - | RBT | 09/26/2026 |
| DOUGLAS, LINIQUA | SHREVEPORT, LA | - | Professional Counselor | 08/29/2017 |
| DOUGLASS, MORGAN | FORT COLLINS, CO | PHD | Psychologist | 10/23/2018 |
| DOUKAS, HEATHER | COLORADO SPRINGS, CO | - | Speech-Language Pathologist | 05/26/2021 |
| DOUTE, HEATHER | RIXEYVILLE, VA | MA, LPC, CSOTP | Mental Health Counselor | 09/21/2026 |
| DOVE FORENSIC & CLINICAL CONSULTING LLCORG | WATERBURY, CT | - | Clinical Social Worker | 09/26/2026 |
| DOVE OF PEACE CHRISTIAN COUNSELING PLLCORG | IRA, MI | - | Mental Health Counselor | 11/11/2022 |
| DOVE, SARAH | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| DOWDELL, CARL | SHELBY, NC | LCSW, LCAS | Addiction (Substance Use Disorder) Counselor | 02/03/2016 |
| DOWDY, SARAH | FAIRVIEW, TN | LCSW | Clinical Social Worker | 08/08/2020 |
| DOWNAM, RACHEL | SPOKANE, WA | - | Clinical Social Worker | 06/22/2023 |
| DOWNER, ROWAN | WINCHESTER, VA | - | RBT | 09/21/2026 |
| DOWNES, KIAN | EDGEWATER, NJ | LSW | BCBA | 09/21/2026 |
| DOWNEY, ANGELINA | GROSSE POINTE FARMS, MI | - | RBT | 09/22/2026 |
| DOWNS, JOHNISHA | MARTINEZ, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| DOYLE, BRITTNEY | LOUISVILLE, KY | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| DOYLE, NIKKI | HOT SPRINGS, AR | QBHP | Case Manager/Care Coordinator | 10/28/2025 |
| DOZIER, JESSICA | MISHAWAKA, IN | LCSW | Clinical Social Worker | 09/25/2026 |
| DR ASHLEY LJ BELCHER PSYD PLLCORG | LOUISVILLE, KY | - | Psychologist | 09/21/2026 |
| DRAGG, MORGAN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| DRAKE, JADA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| DRAKEFORD, JANICE | WALDORF, MD | - | Case Manager/Care Coordinator | 09/25/2026 |
| DRAPP, MORGAN | DOYLESTOWN, PA | LCSW | Clinical Social Worker | 03/28/2025 |
| DRAWDY, CONNOR | DELAND, FL | - | Mental Health Counselor | 09/23/2026 |
| DRAYMORE, EVA | LEXINGTON, MA | - | Mental Health Counselor | 09/23/2026 |
| DREYER-GOLDMAN, IVY | EUGENE, OR | MSW, LCSW | Clinical Social Worker | 08/10/2022 |
| DRISKEL, EVELYN | ANDERSON, IN | LCSW | Clinical Social Worker | 09/21/2026 |
| DRISSEL, REBECCA | MARIETTA, GA | - | RBT | 09/22/2026 |
| DROUET, CLAUDE | LOUISVILLE, KY | LCSW | Clinical Social Worker | 04/06/2007 |
| DRUMMONDS, GIOVANNA | GLASSBORO, NJ | MSW, LSW | Clinical Social Worker | 02/23/2026 |
| DRUSCHEL, MACIE | MARTINS FERRY, OH | CCC-SLP | Speech-Language Pathologist | 06/24/2020 |
| DUARTE, MIA | MONTEREY, CA | - | RBT | 09/21/2026 |
| DUBENDORF, CLAIRE | BELLINGHAM, WA | - | RBT | 09/21/2026 |
| DUBLER, JUSTIN | PHILADELPHIA, PA | - | RBT | 12/16/2024 |
| DUBOIS REGIONAL MEDICAL CENTERORG | DU BOIS, PA | - | Professional Counselor | 08/30/2007 |
| DUBOW, NATASHA | MURRIETA, CA | - | RBT | 09/22/2026 |
| DUBROCA, DACHE | MIAMI, FL | - | RBT | 09/24/2026 |
| DUCHESNE, ALYSSA | CENTER MORICHES, NY | LCSW | Clinical Social Worker | 09/22/2026 |
| DUCKETT, NOAH | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 05/23/2017 |
| DUCOFFE, VICTORIA | WAUWATOSA, WI | - | Mental Health Counselor | 10/26/2023 |
| DUDGEON, MEGAN | NACOGDOCHES, TX | BCBA | BCBA | 09/22/2026 |
| DUDLEY, WISDOM | MEMPHIS, TN | - | RBT | 09/22/2026 |
| DUENAS, VICTORIA | TORRANCE, CA | - | RBT | 09/21/2026 |
| DUESENBERG-MARSHALL, MCKINZIE | SAINT CHARLES, MO | PHD | Psychologist | 03/07/2025 |
| DUESSEL, EMILY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| DUFFETT, RICHARD | SAN DIEGO, CA | - | RBT | 09/25/2026 |
| DUFFIE, TAYLOR | MECHANICSBURG, PA | MA, NCC, LAPC | Professional Counselor | 02/17/2025 |
| DUFFIELD, ISALY | NASHVILLE, AR | - | Case Manager/Care Coordinator | 09/25/2026 |
| DUFFY, ROSEMARY | PHILADELPHIA, PA | - | RBT | 01/19/2021 |
| DUHULOW, SAHRA | ST ANTHONY, MN | - | RBT | 09/16/2026 |
| DUKE, TARA | CLARKSVILLE, TN | - | RBT | 09/21/2026 |
| DUKES, JASMINE | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| DULMES, KELSEY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 08/17/2015 |
| DUMAS, AMAHJAE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| DUMAS, CARTER | TAMPA, FL | - | BCBA | 03/22/2022 |
| DUMLAO-KAPULE, COURTNEY | KAILUA, HI | - | RBT | 09/23/2026 |
| DUNAMIS CENTER INCORPORATEDORG | REDDING, CA | - | Mental Health Counselor | 02/16/2017 |
| DUNAMIS WELLNESS GROUPORG | REDDING, CA | - | Mental Health Counselor | 10/12/2023 |
| DUNBAR, KIARA | HAYWARD, CA | - | RBT | 09/22/2026 |
| DUNCAN, ANTONISHA | SAINT LOUIS, MO | - | Case Manager/Care Coordinator | 09/25/2026 |
| DUNCAN, ERIKA | GREENVILLE, SC | - | RBT | 09/24/2026 |
| DUNCAN, JACK | FAYETTEVILLE, AR | - | RBT | 09/25/2026 |
| DUNCAN, JENNIFER | MILACA, MN | - | Mental Health Counselor | 09/21/2026 |
| DUNCAN, KAITLYN | GLASGOW, KY | - | RBT | 09/21/2026 |
| DUNCAN, KY-SHA | MATHER, CA | LCSW. LCAS, CCS | Addiction (Substance Use Disorder) Counselor | 06/19/2017 |
| DUNHAM, ERICK | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| DUNLAP, MERCEDES | COAL GROVE, OH | LCDCII.162286 | Addiction (Substance Use Disorder) Counselor | 06/13/2023 |
| DUNLAP, MYA | SAN MARCOS, CA | - | RBT | 09/21/2026 |
| DUNLAP, SANDRA | COLORADO SPRINGS, CO | - | Mental Health Counselor | 09/21/2023 |
| DUNN, BRIAN | AUSTIN, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/22/2026 |
| DUNN, EMILY | CHICAGO, IL | LCSW | Clinical Social Worker | 08/24/2026 |
| DUNN, MILTON | HOUSTON, TX | LPC | Professional Counselor | 01/08/2024 |
| DUNN, RACHEL | ROCKY MOUNT, NC | - | RBT | 04/07/2023 |
| DUNNE, GAY | STATE COLLEGE, PA | M.D. | Specialist | 03/22/2006 |
| DUPONT, SAMANTHA | CENTENNIAL, CO | - | RBT | 09/23/2026 |
| DUPONT, SIOBHAN | ALBANY, NY | MHC-LP | Mental Health Counselor | 09/24/2026 |
| DUPRE, RANIKA | METAIRIE, LA | - | RBT | 09/24/2026 |
| DURAN ARELLANO, FRIDA | CHULA VISTA, CA | - | RBT | 09/21/2026 |
| DURAN, ANDREA | CONCORD, CA | - | RBT | 09/22/2026 |
| DURAN, ITALY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| DURAN, JOSE | NEWPORT BEACH, CA | - | RBT | 09/21/2026 |
| DURGAN CRF LLCORG | BIRMINGHAM, AL | - | Community/Behavioral Health Agency | 05/06/2026 |
| DURHAM, KAHLAYLA | FISHERS, IN | - | RBT | 09/24/2026 |
| DURHAM, NERISSA | RICHMOND HEIGHTS, OH | - | Case Manager/Care Coordinator | 08/27/2019 |
| DURHAM, SABRINA | BOISE, ID | - | Case Manager/Care Coordinator | 09/23/2026 |
| DURKALSKI, JOSHUA | CLEVELAND, OH | SW | Clinical Social Worker | 02/10/2016 |
| DURO, DEVYN | DENVER, CO | MS LPCC | Addiction (Substance Use Disorder) Counselor | 09/16/2021 |
| DURON, SAHAIRA | PALM DESERT, CA | - | RBT | 09/24/2026 |
| DUROSIER, BRIEANNA | ORLANDO, FL | - | Speech-Language Pathologist | 08/11/2022 |
| DUROST, J-LIN | LOCK HAVEN, PA | - | BCBA | 01/14/2026 |
| DUT, NUMAN | HAUPPAUGE, NY | - | Mental Health Counselor | 08/13/2026 |
| DUTSON, RYLIE | SALT LAKE CITY, UT | CCC-SLP | Speech-Language Pathologist | 09/11/2025 |
| DUVALL-HOUSTON, JOSHUA | ALBUQUERQUE, NM | CPSW LSAA | Addiction (Substance Use Disorder) Counselor | 03/07/2024 |
| DWYER, PATRICK | FAIRFAX, VA | LPC | Professional Counselor | 09/22/2026 |
| DYCUS, CHRISTOPHER | CENTRALIA, WA | - | Counselor | 06/17/2025 |
| DYE, DELANIE | CRANDALL, TX | - | BCBA | 05/05/2023 |
| DYER-YBARRONDO, ALLISON | SALEM, OR | - | Addiction (Substance Use Disorder) Counselor | 07/13/2017 |
| DYER, GRACE | CAMBRIDGE, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| DYER, MARY | MEMPHIS, TN | - | Mental Health Counselor | 08/12/2021 |
| DYKSHORN, ELISABETH | CLIVE, IA | LMSW | Mental Health Counselor | 09/21/2026 |
| DYLAN RINCKER COUNSELING SERVICES, PCORG | MISSOULA, MT | - | Clinical Social Worker | 09/21/2026 |
| DYMOND LIFE HEALTHCARE PLLCORG | SALISBURY, NC | - | Case Management Agency | 07/28/2023 |
| DZIKOWSKI, ANDREW | LYNNWOOD, WA | ND, L.AC, ARNP, SUDP | Addiction (Substance Use Disorder) Counselor | 07/01/2021 |
| E&E SHAPING BEHAVIORS LLCORG | BONITA SPRINGS, FL | - | BCBA | 09/22/2026 |
| EAGER, HANNAH | WEST MONROE, LA | PLPC | Professional Counselor | 10/04/2022 |
| EAGLE, ALEXANDRIA | WORCESTER, MA | - | RBT | 09/23/2026 |
| EAGLE, IRENE | DEMING, NM | - | Case Manager/Care Coordinator | 03/07/2013 |
| EAP, DALIN | CONCORD, CA | - | RBT | 09/22/2026 |
| EARLEY, ERIN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| EARTHEN VESSEL COUNSELING PLLCORG | FAYETTEVILLE, AR | - | Mental Health Counselor | 09/21/2026 |
| EASTERLING, BIANCA | FAYETTEVILLE, NC | RBT | RBT | 09/25/2026 |
| EASTLAND, ZECHARIAH | MISHAWAKA, IN | - | RBT | 09/23/2026 |
| EAT TALK LIVE LLCORG | CHESAPEAKE BEACH, MD | - | Speech-Language Pathologist | 09/25/2026 |
| EATON, SUSAN | ROCKWALL, TX | LPC-S | Mental Health Counselor | 08/16/2021 |
| EBEN MBOE, CHARLES | GAITHERSBURG, MD | - | Case Manager/Care Coordinator | 09/24/2026 |
| EBERLE, NATASHA | DENVER, CO | - | Mental Health Counselor | 09/25/2026 |
| EBERSOLE, MEREDITH | RALEIGH, NC | - | Speech-Language Pathologist | 09/24/2026 |
| EBERT, LAUREN | CONCORD, NH | - | Counselor | 04/22/2025 |
| EBERTS, KATIE | BOWLING GREEN, KY | RBT | RBT | 09/21/2026 |
| EBNER, KIMBERLY | KLAMATH FALLS, OR | - | RBT | 09/23/2026 |
| ECHELON CONSULTING INCORG | CHARLOTTE, NC | - | Community/Behavioral Health Agency | 08/18/2008 |
| ECHENDU, CHINENYEM | INDEPENDENCE, MO | - | RBT | 09/23/2026 |
| ECHEVARRIA MENDOZA, ISMAEL | ST GEORGE, UT | - | RBT | 09/23/2026 |
| ECHEVARRIA VARGAS, ASHLEY | ANASCO, PR | MS-SLP | Speech-Language Pathologist | 09/22/2026 |
| ECHEVARRIA, MARIA | EAGLE, ID | - | RBT | 09/25/2026 |
| ECHEZONA, IRENE | MISSOURI CITY, TX | - | RBT | 09/23/2026 |
| ECHOLS, CHRISTOPHER | SAVOY, IL | LSW | Clinical Social Worker | 09/23/2026 |
| ECHOLS, DONALD | PINELLAS PARK, FL | - | Mental Health Counselor | 09/24/2026 |
| ECK, SKYLER | FARGO, ND | - | Case Manager/Care Coordinator | 12/29/2025 |
| ECKERSON, MAX | CHARLOTTE, NC | LCMHCA | Mental Health Counselor | 05/13/2025 |
| ECKFORD, JANEISHA | MUNCIE, IN | - | RBT | 09/24/2026 |
| ECKMAN, WALTER | TUPELO, MS | M.D. | Specialist | 08/24/2005 |
| ECKROTE, BRYANNA | TUCSON, AZ | - | RBT | 09/21/2026 |
| EDDINGTON, TRACIE | MARTINEZ, CA | LCSW | Clinical Social Worker | 10/20/2006 |
| EDDLEMAN, KATELYN | FORT WORTH, TX | LPC | Counselor | 09/23/2026 |
| EDDY, AMANDA | SACRAMENTO, CA | - | Professional Counselor | 12/11/2024 |
| EDDY, ROGER | TUKWILA, WA | MHP | Counselor | 09/21/2026 |
| EDEN CARE FACILITY LLCORG | CENTENNIAL, CO | - | Day Training/Habilitation Specialist | 08/01/2017 |
| EDEN, IDA | STATESVILLE, NC | MS, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| EDER, CHRISTINE | ORANGE, CA | - | RBT | 09/21/2026 |
| EDEWAARD, LIZA | FENNVILLE, MI | LLMSW | Clinical Social Worker | 03/08/2021 |
| EDGAR, ELLIOT | MARQUETTE, MI | LLMSW-C | Clinical Social Worker | 09/23/2026 |
| EDGE OF MIND COUNSELING PLLCORG | GRAHAM, NC | - | Mental Health Counselor | 09/25/2026 |
| EDGERTON, VERONICA | COMMERCE TOWNSHIP, MI | - | Clinical Social Worker | 09/21/2026 |
| EDGETON-MARTIN, CAROLINE | ALEXANDRIA, VA | M.S.ED., LPC, NCC | Professional Counselor | 03/11/2026 |
| EDHEALTH, LLC.ORG | DENVER, CO | - | Mental Health Counselor | 06/03/2022 |
| EDMISTON, KATHLEEN | SAN ANTONIO, TX | - | RBT | 09/25/2026 |
| EDMONDS, ANNAH | SEATTLE, WA | LMHC | Mental Health Counselor | 09/21/2015 |
| EDMONDSON, GABRIEL | FOLSOM, CA | - | RBT | 09/21/2026 |
| EDMONDSON, JANEE | MINNEAPOLIS, MN | - | RBT | 09/21/2026 |
| EDSON, KATIE LYNNE | MUSKEGON, MI | LMSW, CAADC | Addiction (Substance Use Disorder) Counselor | 07/07/2018 |
| EDUCARE COMMUNITY LIVING - NORMAL LIFE, INC.ORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/29/2007 |
| EDUCARE COMMUNITY LIVING - NORMAL LIFE, INC.ORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/29/2007 |
| EDUCARE COMMUNITY LIVING - NORMAL LIFE, INC.ORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/24/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - GULF COASTORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/28/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - GULF COASTORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/30/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/29/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/24/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/29/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 06/13/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/30/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/30/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AUSTIN, TX | - | Community/Behavioral Health Agency | 05/29/2007 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | AMARILLO, TX | - | Community/Behavioral Health Agency | 07/13/2013 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | CORPUS CHRISTI, TX | - | Community/Behavioral Health Agency | 07/17/2013 |
| EDUCARE COMMUNITY LIVING CORPORATION - TEXASORG | LUBBOCK, TX | - | Community/Behavioral Health Agency | 07/18/2013 |
| EDUCATE EMPOWERMENT LLCORG | LOS ALAMOS, NM | - | Clinical Social Worker | 07/13/2026 |
| EDWARDS, ALI | SALISBURY, NC | LCSW-A | Clinical Social Worker | 09/24/2026 |
| EDWARDS, ANGEL | AUGUSTA, GA | - | RBT | 04/21/2021 |
| EDWARDS, BRIDGET | MISSOULA, MT | L.C.P.C. | Professional Counselor | 03/23/2016 |
| EDWARDS, DEBORAH | BELLEVILLE, IL | LPC | Professional Counselor | 03/01/2016 |
| EDWARDS, EDWIN | WEST JORDAN, UT | RBT | RBT | 06/18/2024 |
| EDWARDS, LAUREN | TALLAHASSEE, FL | - | RBT | 09/24/2026 |
| EFOMI, YONA | GAITHERSBURG, MD | - | RBT | 09/21/2026 |
| EGAN, SHAUNESSY | GLASTONBURY, CT | BCBA | Psychologist | 10/22/2009 |
| EGAN, TORREY | KAYSVILLE, UT | - | RBT | 09/25/2026 |
| EGGEBRECHT, SAMUEL | SANTA FE, NM | - | Professional Counselor | 03/28/2023 |
| EGGLESTON, MERCEDES | OREM, UT | - | RBT | 06/08/2021 |
| EGUAKUN, GIANNI | AUSTIN, TX | LPC | Mental Health Counselor | 12/31/2018 |
| EIDAM, EDWARD | NORRISTOWN, PA | - | Professional Counselor | 12/31/2025 |
| EIDE, ROMI | KENOSHA, WI | - | Speech-Language Pathologist | 09/21/2026 |
| EILETS, SHAQUILLA | LAS VEGAS, NV | - | RBT | 09/23/2026 |
| EISENBERG, RACHEL | MONSEY, NY | LSW | Clinical Social Worker | 01/22/2024 |
| EISENGA, MORGAN | MT PLEASANT, MI | - | RBT | 09/21/2026 |
| EISENMAN, ERIKA | MIDVALE, UT | - | Clinical Social Worker | 09/03/2014 |
| EISENZIMMER, TIMOTHY | MINOT, ND | LPCC | Mental Health Counselor | 06/14/2022 |
| EKHTIAR, MARYAM | MISSION VIEJO, CA | D.D.S. | Mental Health Counselor | 05/08/2007 |
| EKINS, GRETCHEN | HARTFORD, WI | - | Clinical Social Worker | 08/26/2026 |
| ELBEDEIWY, SHAMS | LYNDHURST, NJ | - | Clinical Social Worker | 08/23/2023 |
| ELDRIDGE, BLAKE | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ELDRIDGE, SHADE | ALBUQUERQUE, NM | - | RBT | 09/24/2026 |
| ELEFTHERIOU, SYDNEY | WALTHAM, MA | BCBA, LABA | BCBA | 06/05/2023 |
| ELEVATE COUNSELING & WELLNESS LLCORG | CRANSTON, RI | - | Professional Counselor | 06/02/2026 |
| ELEVATE HEALTH MEDICAL CENTER CORPORG | MIAMI, FL | - | Clinic/Center | 09/21/2026 |
| ELEVATION SPEECH AND FEEDING THERAPY, LLCORG | SPARKS, NV | - | Speech-Language Pathologist | 09/25/2026 |
| ELFERS, ALEXANDRA | DAYTON, OH | BCBA | BCBA | 07/17/2018 |
| ELHUR, ROZAN | FARMINGTON HILLS, MI | - | RBT | 02/28/2022 |
| ELIAS IZQUIERDO, JADE | GREENACRES, FL | - | RBT | 09/25/2026 |
| ELISE DREXLER COUNSELING, LLCORG | KAILUA KONA, HI | - | Clinical Social Worker | 09/25/2026 |
| ELIZABETH ARREDONDOORG | GARDEN RIDGE, TX | - | Addiction (Substance Use Disorder) Counselor | 06/04/2013 |
| ELIZONDO, CYNTHIA | SAINT PAUL, MN | LPC | Professional Counselor | 09/25/2006 |
| ELK, ALIYHA | PARSIPPANY, NJ | - | Mental Health Counselor | 09/25/2026 |
| ELKIN-AQUINO, MADELINE | PORTLAND, OR | BA | Professional Counselor | 06/20/2023 |
| ELKINS, CHANDA | LOVELAND, CO | - | Clinical Social Worker | 04/26/2023 |
| ELLEDGE, LINDSAY | SAN DIEGO, CA | - | Clinical Social Worker | 10/23/2016 |
| ELLIMAC-RAHEEM, CAMILLE | NAPERVILLE, IL | LCPC | Professional Counselor | 06/19/2022 |
| ELLINGSON, ELIZABETH | FARGO, ND | LAPC | Professional Counselor | 09/24/2026 |
| ELLINGTON, NICHOLE | MT PLEASANT, IA | LMHC-T | Mental Health Counselor | 09/25/2026 |
| ELLIOTT, KAYLEE | VAN NUYS, CA | - | RBT | 09/21/2026 |
| ELLIOTT, MEGHAN | CLACKAMAS, OR | - | Mental Health Counselor | 09/24/2026 |
| ELLIOTT, NOA | DALY CITY, CA | MSW | Clinical Social Worker | 09/24/2026 |
| ELLIOTT, RACHEL | WORCESTER, MA | - | Speech-Language Pathologist | 11/06/2019 |
| ELLIS, AMELIA | FRANKLINTON, NC | - | RBT | 09/24/2026 |
| ELLIS, BRIANNA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| ELLIS, EMERSON | COON RAPIDS, MN | - | RBT | 09/25/2026 |
| ELLIS, EMILY | FAIRMONT, WV | - | Counselor | 03/25/2025 |
| ELLIS, TRACIE | COLORADO SPRINGS, CO | - | Professional Counselor | 09/23/2026 |
| ELLSWORTH, IVY | SHAKER HEIGHTS, OH | MS | Speech-Language Pathologist | 03/20/2025 |
| ELLSWORTH, JOSHUA | WILMINGTON, NC | LCMHCA, LCAS | Addiction (Substance Use Disorder) Counselor | 05/24/2024 |
| ELMER, EMILY | SAN MARCOS, CA | - | RBT | 09/22/2026 |
| ELMORE, CALVIN | OKLAHOMA CITY, OK | - | Professional Counselor | 08/02/2021 |
| ELMY, MARGARET | CONCORD, CA | BCBA | BCBA | 05/16/2018 |
| ELORA THERAPY ASSOCIATES LLCORG | BOCA RATON, FL | - | Speech-Language Pathologist | 09/22/2026 |
| ELSYIED, HAMSA | STATEN ISLAND, NY | - | Speech-Language Pathologist | 09/22/2026 |
| ELYASI, BRENDAN | VAN NUYS, CA | - | RBT | 09/24/2026 |
| EMADI, JAZMYN | LONG BEACH, CA | - | Mental Health Counselor | 01/08/2024 |
| EMAPTHY WITH BOUNDARIES COUNSELING SERVICES LLCORG | VOORHEES, NJ | - | Clinical Social Worker | 09/24/2026 |
| EMBOLDEN THERAPEUTIC SERVICESORG | ROSWELL, GA | - | Mental Health Counselor | 04/15/2024 |
| EMBRACE REAL HEALING, MENTAL HEALTH THERAPY LCCORG | MOOSIC, PA | - | Clinical Social Worker | 09/26/2026 |
| EMDAZZ HEALTH SERVICESORG | BRICK, NJ | - | Community/Behavioral Health Agency | 09/22/2026 |
| EMERGE ABA CO LLCORG | DENVER, CO | - | BCBA | 09/22/2026 |
| EMERGE COUNSELING & COACHING, LLCORG | YOUNGSTOWN, OH | - | Mental Health Counselor | 09/21/2026 |
| EMERGENCE PSYCHOTHERAPY GROUP, LLCORG | PITTSFIELD, MA | - | Mental Health Counselor | 09/25/2026 |
| EMERSON, LATANYA | WESTLAKE, OH | - | Mental Health Counselor | 09/25/2026 |
| EMERY, DESIRAE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| EMI, MIWA | SEAL BEACH, CA | MSW | Clinical Social Worker | 07/31/2007 |
| EMIGDIO, RUBI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| EMILE, LYNDA | BRIDGEWATER, MA | - | Mental Health Counselor | 09/24/2026 |
| EMILY LEMKE THERAPY & CONSULTATION, LLCORG | ROCKVILLE, MD | - | Clinical Social Worker | 06/23/2026 |
| EMMA FLAVIN STANTON, LMHC, LLCORG | BEVERLY, MA | - | Mental Health Counselor | 09/21/2026 |
| EMMETT, KYEMAH | BLOOMSBURG, PA | LAPC | Counselor | 09/22/2026 |
| EMPOWERED 2 THRIVE, LLCORG | HILLSBORO, OR | - | Mental Health Counselor | 09/22/2026 |
| EMPOWERED CHOICES LLCORG | CARTER LAKE, IA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| EMRICK, TARA | DENVER, CO | LCSW | Clinical Social Worker | 05/19/2025 |
| EMRY, AMY | OXNARD, CA | - | RBT | 09/24/2026 |
| ENCINIAS, JAHAZEL | SAN GABRIEL, CA | - | RBT | 09/22/2026 |
| ENDERLE, MCKENNA | FUQUAY VARINA, NC | - | RBT | 03/20/2024 |
| ENERSON, NOELLE | SAN DIEGO, CA | - | RBT | 09/25/2026 |
| ENG, JESSICA | NEW YORK, NY | LMHC | Mental Health Counselor | 05/16/2020 |
| ENGBER, KEITH | INDIO, CA | - | Mental Health Counselor | 09/24/2026 |
| ENGEL, HANNAH | SANTA ROSA, CA | - | Speech-Language Pathologist | 09/24/2026 |
| ENGELBRECHT, NATHAN | LAS CRUCES, NM | MAC, LADAC, CCSS | Mental Health Counselor | 04/20/2023 |
| ENGLE, DENIS | HOLLAND, MI | - | RBT | 05/04/2021 |
| ENGLISH, SANAA | FORT MILL, SC | RBT | RBT | 09/21/2026 |
| ENGLISH, SARAH | CORDOVA, TN | NP | RBT | 09/14/2017 |
| ENGLISH, TIFFANY | MATHER, CA | LCSW | Clinical Social Worker | 07/10/2007 |
| ENNIS, ASHLEY | LITTLETON, CO | - | Clinical Social Worker | 09/22/2026 |
| ENOCH, MELISSA | CHARLOTTE, NC | LCMHC,LCAS, CCS, MAC | Addiction (Substance Use Disorder) Counselor | 10/20/2014 |
| ENOCH, MICHAEL | COLUMBUS, OH | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| ENRIGHT, FRANCIS | CHARLOTTE, NC | LCMHC-S, LPC-S | Mental Health Counselor | 06/10/2008 |
| ENRIQUEZ, JASMINE | ORANGE, CA | - | RBT | 09/22/2026 |
| ENRIQUEZ, STEPHANIE | PACOIMA, CA | - | Clinical Social Worker | 02/12/2018 |
| ENTER GRACEORG | LAKE ELSINORE, CA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| ENVISAGE COUNSELING SERVICES LLCORG | CHAMPAIGN, IL | - | Mental Health Counselor | 04/05/2022 |
| ENVISION QUALITY SUPPORTSORG | MURRAY, UT | - | Case Manager/Care Coordinator | 09/23/2026 |
| EP THERAPY, PLLCORG | BERRIEN SPRINGS, MI | - | Clinical Social Worker | 03/01/2024 |
| EPHRAIM MCDOWELL HEALTH RESOURCE, INC.ORG | SOMERSET, KY | - | Clinical Social Worker | 02/18/2026 |
| EPHRAIM MCDOWELL REGIONAL MEDICAL CENTER, INCORPORATEDORG | DANVILLE, KY | - | Clinical Social Worker | 07/16/2013 |
| EPPERSON, NOAH | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| EPSTEIN, CAYLA | CHARLOTTE, NC | M.A., BCBA | BCBA | 02/21/2023 |
| EQUANIMITY THERAPY & CONSULTING PLLCORG | DURHAM, NC | - | Clinical Social Worker | 09/25/2026 |
| ERDLY, COURTNEY | OMAHA, NE | PSYD | Psychologist | 08/14/2025 |
| ERHARDT, ROBIN | EDGEWOOD, MD | - | Mental Health Counselor | 09/23/2026 |
| ERIC GOODWIN COUNSELING, LLCORG | PORTLAND, OR | - | Professional Counselor | 04/26/2022 |
| ERICKS, ALLISON | OTSEGO, MI | LMSW | Clinical Social Worker | 09/25/2026 |
| ERICKSEN, JODI | SILVERDALE, WA | - | Mental Health Counselor | 08/22/2026 |
| ERICKSON, AMANDA | EUREKA, MT | - | Speech-Language Pathologist | 04/17/2023 |
| ERLEWINE, ELISE | SANTA CRUZ, CA | - | RBT | 09/21/2026 |
| ERVIN, JASMINE | MCKINNEY, TX | - | Professional Counselor | 03/01/2023 |
| ERVIN, MIRA | SPRINGFIELD, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| ERVING, JESSICA | CHICAGO, IL | - | Clinical Social Worker | 09/23/2026 |
| ERWIN HARRIS, IYANA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| ERWIN, SHELBY | CONCORD, CA | - | RBT | 09/21/2026 |
| ESCALA, ANTOINETTE | VERO BEACH, FL | - | RBT | 09/22/2026 |
| ESCALADA, ROMALYN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| ESCALERA, AMARIS | CONVERSE, TX | - | Clinical Social Worker | 09/25/2026 |
| ESCOBAR BARRERA, RUBY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| ESCOBAR LEMES, AINELIS | MIAMI, FL | - | Assistant Behavior Analyst | 09/21/2026 |
| ESCOBAR, SEDINA | RENO, NV | CLINICAL SOCIAL WORK | Clinical Social Worker | 09/25/2026 |
| ESCOBEDO CORN, TREVOR | SAN DIEGO, CA | M.A. | Psychologist | 08/25/2021 |
| ESGAR, JENNA | COLUMBIA, MO | PLPC | Professional Counselor | 08/14/2026 |
| ESPINOZA, ALEXIS | SANTA ANA, CA | - | RBT | 09/23/2026 |
| ESPINOZA, ANDRES | GARDEN GROVE, CA | - | RBT | 09/23/2026 |
| ESPINOZA, CAROLINA | CHICAGO, IL | - | Clinical Social Worker | 09/25/2026 |
| ESPINOZA, NATALIE | PHOENIX, AZ | - | RBT | 09/21/2026 |
| ESPOSITO, ALYSSA | STATEN ISLAND, NY | - | Speech-Language Pathologist | 01/29/2024 |
| ESQUIVEL, EVELYN | GROVELAND, CA | - | BCBA | 08/24/2022 |
| ESRAL, MICHAL | PIKESVILLE, MD | LMSW | Counselor | 09/22/2026 |
| ESSIGMANN, ANNELIESE | COLORADO SPRINGS, CO | M.A. AMFT, LPC | Professional Counselor | 11/20/2019 |
| ESSIGMANN, MADISON | WHEELING, WV | - | Professional Counselor | 08/31/2026 |
| ESSOMBE, WILFRED | SANTA CRUZ, CA | - | RBT | 09/25/2026 |
| ESTEVEZ, AIMARA | MIAMI, FL | - | RBT | 06/21/2017 |
| ESTRADA, BAILEY | VENTURA, CA | - | RBT | 09/23/2026 |
| ESTRADA, DIXIE | SAN DIEGO, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| ESTRADA, EMILY | ANNAPOLIS, MD | PH.D. | Psychologist | 03/02/2022 |
| ESTRADA, GUSTAVO | COVINA, CA | - | RBT | 09/24/2026 |
| ESTUPINAN CARDENAS, LAURA | CEDAR PARK, TX | - | RBT | 09/25/2026 |
| ETHERTON, MONTANNA | CLARKSVILLE, IN | - | RBT | 09/24/2026 |
| ETIENNE, KATELYNN | PORT SAINT LUCIE, FL | - | RBT | 08/04/2026 |
| ETTER, CHRISTOPHER | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| ETUK, EDEN | HOUSTON, TX | - | RBT | 09/21/2026 |
| EULER, TOMI | GRANITE BAY, CA | LMFT | Mental Health Counselor | 09/26/2026 |
| EVANS, BUSSIE | PANAMA CITY BEACH, FL | MD | Specialist | 07/18/2006 |
| EVANS, CHANDLER | HIGHLANDS RANCH, CO | - | RBT | 09/21/2026 |
| EVANS, DANIELLE | WEST PLAINS, MO | - | RBT | 09/22/2026 |
| EVANS, DAVID | TIGARD, OR | - | Mental Health Counselor | 09/21/2026 |
| EVANS, JASON | SEATTLE, WA | - | Counselor | 09/08/2026 |
| EVANS, KRISTOPHER | TORRANCE, CA | - | Addiction (Substance Use Disorder) Counselor | 03/21/2017 |
| EVANS, MARK | CHARLOTTESVILLE, VA | SLP | Speech-Language Pathologist | 06/12/2019 |
| EVANS, MARTIN | CHATTANOOGA, TN | RBT | RBT | 01/26/2026 |
| EVANS, ROY | STAUNTON, VA | LPC,CSAC | Addiction (Substance Use Disorder) Counselor | 07/24/2006 |
| EVARISTO HERNANDEZ, CELESTE | FRESNO, CA | - | RBT | 09/23/2026 |
| EVARISTO, RICARDO | COSTA MESA, CA | - | RBT | 02/07/2018 |
| EVBUOMWAN, HENRY | OKLAHOMA CITY, OK | LPC | Professional Counselor | 07/03/2012 |
| EVERARD, KIMBERLY | BENSON, NC | LCSW-CP | Clinical Social Worker | 09/11/2020 |
| EVERETT, ANGELIA | TUPELO, MS | LCSW | Clinical Social Worker | 09/24/2026 |
| EVERGREEN MARRIAGE AND FAMILY COUNSELING SERVICES, CORP.ORG | MARIPOSA, CA | - | Professional Counselor | 02/27/2024 |
| EVERMIND BEHAVIORAL HEALTHORG | MESA, AZ | - | Case Management Agency | 09/22/2026 |
| EVERTS, ETHAN | HOUSTON, TX | - | Mental Health Counselor | 09/21/2026 |
| EVERTS, NOELLE | ROSEMOUNT, MN | MA CCC SLP | Speech-Language Pathologist | 06/01/2007 |
| EVERTZ, ROCHON | BROOKLYN, NY | - | Specialist | 08/31/2026 |
| EVERWELL LUXEORG | KISSIMMEE, FL | - | Clinic/Center | 09/24/2026 |
| EVERY CHAPTER COUNSELING, PLLCORG | GREENSBORO, NC | - | Clinical Social Worker | 09/23/2026 |
| EVOLUTION THERAPY GROUP, PLLCORG | SEATTLE, WA | - | Mental Health Counselor | 09/21/2026 |
| EVOLVE BEHAVIORAL HEALTH AND THERAPY, PLLCORG | RAYMOND, NH | - | Mental Health Counselor | 09/11/2026 |
| EVOLVE COUNSELING SERVICES, LLCORG | TULSA, OK | - | Mental Health Counselor | 09/22/2026 |
| EVOLVE LEARNING & THERAPY CENTER LLCORG | KISSIMMEE, FL | - | BCBA | 09/21/2026 |
| EVOLVE PEDIATRICS, LLCORG | HENDERSON, KY | - | Speech-Language Pathologist | 04/21/2021 |
| EVORA MIRO, REBECA | MIAMI, FL | PSY.D., BCBA | Psychologist | 07/25/2017 |
| EWALD, AUBRIE | SAN DIEGO, CA | - | BCBA | 09/23/2026 |
| EWING, KIMANI | HERMOSA BEACH, CA | - | RBT | 09/21/2026 |
| EXPRESSIVE MINDS THERAPY GROUP LLCORG | JUPITER, FL | - | Speech-Language Pathologist | 09/23/2026 |
| EYONG, THERESIA | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/23/2026 |
| EYONGESI, MAGDALINE | BOWIE, MD | - | Case Manager/Care Coordinator | 09/23/2026 |
| EZEANI, GLORIA | HOUSTON, TX | - | Mental Health Counselor | 09/21/2026 |
| FABELA, STEPHANIE | KILLEEN, TX | - | RBT | 09/24/2026 |
| FABIO, COURTNEY | NASHVILLE, TN | LMSW | Clinical Social Worker | 01/31/2023 |
| FACUNDO, ZAELIA | BAY CITY, MI | - | RBT | 09/22/2026 |
| FAGA, KAYLA | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| FAGENBUH, DEVIN | MARICOPA, AZ | - | RBT | 09/25/2026 |
| FAGNANO, THAISSE | LITTLETON, CO | - | Mental Health Counselor | 09/24/2026 |
| FAHAIM, KAREN | GRETNA, LA | LMFT, LPC | Counselor | 09/21/2026 |
| FAHD-LEOPAR, GABRIELLA | IRWIN, PA | - | RBT | 09/22/2026 |
| FAHEY, KACEY | MINOT, ND | - | Speech-Language Pathologist | 09/23/2026 |
| FAILES, KIMBERLY | TWIN FALLS, ID | MS LPC LAT | Mental Health Counselor | 01/15/2009 |
| FAIR, ALEXUS | SELMA, NC | - | BCBA | 09/23/2026 |
| FAITH WALKER COUNSELING LLCORG | WEST ROXBURY, MA | - | Mental Health Counselor | 05/18/2026 |
| FAITHFUL FOUNDATION THERAPY PLLCORG | BUCKEYE, AZ | - | Clinical Social Worker | 09/25/2026 |
| FAITHWALKS ABA LLCORG | LOS ANGELES, CA | - | Community/Behavioral Health Agency | 08/19/2026 |
| FAJARDO, DIANA | BRONX, NY | - | Specialist | 05/22/2013 |
| FAKHRI, SARA | CHICAGO, IL | LCPC | Mental Health Counselor | 07/19/2023 |
| FALCON, LETZY | VAN BUREN, AR | BCBA | BCBA | 06/28/2024 |
| FALLA, CARLO | SAN RAFAEL, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| FAMILY FIRST BEHAVIORAL HEALTH LLCORG | LAS VEGAS, NV | - | Mental Health Counselor | 03/19/2026 |
| FAMILY FLOW STRATEGIES LLCORG | LAS VEGAS, NV | - | BCBA | 08/06/2024 |
| FAMILY IN FOCUS HEALTH PLLCORG | CHESAPEAKE, VA | - | Clinic/Center | 09/19/2024 |
| FAMILY OF CHOICE LLCORG | HAYES, VA | - | Professional Counselor | 01/03/2023 |
| FAMILY RESOURCE CENTERORG | CHICAGO, IL | - | Clinical Social Worker | 01/27/2023 |
| FAMILY, INC.ORG | LOUISVILLE, KY | - | Case Management Agency | 09/21/2026 |
| FANARA, ADA | SAN ANTONIO, TX | SLP | Speech-Language Pathologist | 06/17/2006 |
| FANNING, IRIS | ROCKFORD, IL | - | Clinical Social Worker | 09/25/2026 |
| FARAHMAND, FARZANA | MANASSAS, VA | - | RBT | 09/09/2026 |
| FARENKOPF, KATHERINE | WHEATON, IL | - | Clinical Social Worker | 08/10/2023 |
| FARGAS, ARACELIS | HOLYOKE, MA | - | Addiction (Substance Use Disorder) Counselor | 09/26/2026 |
| FARINAS, MELANIE | ORLANDO, FL | - | RBT | 09/25/2026 |
| FARLAM, JUNE | WAYNE, PA | - | Clinical Social Worker | 09/25/2026 |
| FARMER, ISABELLA | PHOENIX, AZ | - | Speech-Language Pathologist | 09/21/2026 |
| FARMER, JESSICA | YAKIMA, WA | LMHCA | Mental Health Counselor | 09/25/2026 |
| FARMER, MADELINE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| FARO BEHAVIORAL HEALTHORG | TEMECULA, CA | - | BCBA | 03/06/2026 |
| FAROOQ, MAHNOOR | JOHNS CREEK, GA | - | Professional Counselor | 09/22/2026 |
| FARPOUR, BENJAMIN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| FARR, DAVID | ARVADA, CO | MA, JD, MBA | Mental Health Counselor | 09/21/2026 |
| FARRAR, JACLYN | PEMBROKE, MA | M.ED, BCBA | BCBA | 04/24/2014 |
| FARRELL, MICHELLE | LEBANON, NH | LICSW | Clinical Social Worker | 08/03/2014 |
| FARRELL, S | COATESVILLE, PA | LCSW | Clinical Social Worker | 07/20/2006 |
| FASSLER, JULIA | ASTORIA, NY | - | Clinical Social Worker | 07/15/2024 |
| FATIMA, SYEDA FIZZA | ASHBURN, VA | - | BCBA | 09/28/2021 |
| FAUDOA-BARRIOS, TANIA | LAKEWOOD, CO | - | RBT | 09/23/2026 |
| FAULKINBURY, KATHLEEN | DURHAM, NC | - | RBT | 09/23/2026 |
| FAUNTLEROY, JONELLE | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| FAURRIETA RUIZ, AZUL | MOUNTAIN VIEW, CA | - | RBT | 02/24/2026 |
| FAVILLA, SARAH | BELLAIRE, TX | MA, LBA, BCBA | BCBA | 04/05/2018 |
| FAY, SARAH | JUPITER, FL | LCSW | Clinical Social Worker | 09/25/2026 |
| FAYAD, LUNA | OAKLAND, CA | - | Psychologist | 09/07/2026 |
| FBTC TRANSITIONAL SUB, LLCORG | PROVIDENCE, RI | - | Speech-Language Pathologist | 09/01/2025 |
| FEDORUK, AMY | ROSEMOUNT, MN | SLP | Speech-Language Pathologist | 10/10/2008 |
| FEDULCHAK, MORGAN | LIVONIA, MI | - | RBT | 05/01/2023 |
| FEISEL, TIFFANY | ZANESVILLE, OH | PRS | Case Manager/Care Coordinator | 08/02/2021 |
| FEIST BROWN, TRISTA | SUPERIOR, MT | ACLC | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| FELIX, CARLOS | MANTECA, CA | - | Day Training/Habilitation Specialist | 09/07/2021 |
| FELIX, JENNIFER | PALMDALE, CA | - | Case Manager/Care Coordinator | 07/21/2023 |
| FELIX, MICHELLE | SAN DIEGO, CA | - | BCBA | 01/22/2019 |
| FELIZ, ANTONIO | PUEBLO, CO | M.D. | Specialist | 06/23/2005 |
| FELIZ, EBONY | PORTSMOUTH, VA | FNP-BC | Case Manager/Care Coordinator | 09/19/2017 |
| FELIZ, ENMANUEL | LEOMINSTER, MA | - | Clinical Social Worker | 02/26/2021 |
| FELLER-KOPMAN, ISABEL | CONCORD, MA | - | Clinical Social Worker | 08/15/2022 |
| FELTHUBBARD, ELSPETH | FRAMINGHAM, MA | - | RBT | 09/21/2026 |
| FELTON, THERESA | CROWN POINT, IN | LMHC | Mental Health Counselor | 08/18/2014 |
| FENNELL, SCOTLYNNE | PITTSBURGH, PA | - | Mental Health Counselor | 10/29/2025 |
| FERGUSON, CARLY | TOLEDO, OH | CT | Counselor | 02/02/2024 |
| FERGUSON, HAYLEY | BROOKFIELD, OH | - | Case Manager/Care Coordinator | 09/26/2026 |
| FERGUSON, NICOLE | ARLINGTON, TX | LCSW | Clinical Social Worker | 03/20/2023 |
| FERGUSON, REBECCA | SPRINGDALE, AR | MS, LPC | Professional Counselor | 02/12/2020 |
| FERM, JOAN | CHICO, CA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2012 |
| FERNANDES, ADRIANA | FALL RIVER, MA | MSW | Clinical Social Worker | 08/24/2026 |
| FERNANDEZ, ALEXAH | EAST STROUDSBURG, PA | - | RBT | 09/21/2026 |
| FERNANDEZ, ALONDRA | PALATINE, IL | - | BCBA | 09/24/2026 |
| FERNANDEZ, EMILIE | EAST ORANGE, NJ | - | Mental Health Counselor | 09/26/2026 |
| FERNANDEZ, EMILY | MIRAMAR, FL | - | RBT | 09/25/2026 |
| FERNANDEZ, NANCY | TRACY, CA | - | Speech-Language Pathologist | 09/23/2026 |
| FERNANDEZ, REGINA | ELK GROVE, CA | - | RBT | 09/24/2026 |
| FERNANDEZ, SOFIA | ELMHURST, IL | LCSW | Clinical Social Worker | 09/18/2026 |
| FERRANTE, NICOLETTE | RED BANK, NJ | MS, LAC, NCC | Mental Health Counselor | 01/18/2024 |
| FERRARI, LAURIE | MCCLELLAN, CA | LCSW | Clinical Social Worker | 08/30/2006 |
| FERRELL, JAMARI | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| FERRERAS COUNSELING LLCORG | LAWRENCE, MA | - | Addiction (Substance Use Disorder) Counselor | 10/07/2016 |
| FERRILL, SAVANNAH | GULFPORT, MS | - | RBT | 09/22/2026 |
| FERRIS, MEGAN | CHARLOTTESVILLE, VA | SLP | Speech-Language Pathologist | 05/30/2019 |
| FERRIS, THOMAS | ODENTON, MD | - | Clinical Social Worker | 09/24/2026 |
| FERRO, JOLIE | NEW BEDFORD, MA | - | RBT | 09/23/2026 |
| FERRON, EMILY OLIVER | PETALUMA, CA | - | Day Training/Habilitation Specialist | 09/17/2026 |
| FERRY, ALEXIS | STAUNTON, VA | LCSW | Clinical Social Worker | 09/22/2026 |
| FESTER-BROWN, ASHLEY | BERKELEY, IL | - | Mental Health Counselor | 09/21/2026 |
| FICKES, MEGHAN | WILMINGTON, DE | LPCMH | Mental Health Counselor | 06/27/2024 |
| FIELD, CHRISTOPHER | NORTH PALM BEACH, FL | LMHC | Mental Health Counselor | 09/22/2026 |
| FIELDS, LUCRESIA | UNIVERSAL CITY, TX | - | Professional Counselor | 06/22/2023 |
| FIEWIG, BRITTANY | YPSILANTI, MI | LCSW | Clinical Social Worker | 09/24/2026 |
| FIGLAR, KAYLA | IRWIN, PA | - | BCBA | 09/22/2026 |
| FIGUEROA, BLANCA | ROCKWALL, TX | LPC | Professional Counselor | 12/05/2013 |
| FIGUEROA, CAMILA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| FIGUEROA, CECILIA | CAPE CORAL, FL | - | BCBA | 07/12/2022 |
| FIGUEROA, CHRISTIAN | YOUNGSTOWN, OH | - | RBT | 09/23/2026 |
| FIGUEROA, SYLVIA | LAKELAND, FL | - | RBT | 09/21/2026 |
| FILIS, JACQUELINE | STATEN ISLAND, NY | LCSW, CASAC | Clinical Social Worker | 12/09/2011 |
| FILS-AIME, ROODELINE | WESTON, FL | - | RBT | 09/25/2026 |
| FINAZZO, GIROLAMO | CAMBRIDGE, MA | LCSW, LICSW, LCAS | Clinical Social Worker | 07/11/2022 |
| FINCHER, SHANNON | SAPULPA, OK | - | Counselor | 10/14/2019 |
| FINCK, AMBER | ELIZABETH CITY, NC | LCSW | Clinical Social Worker | 10/10/2022 |
| FINEBERG, MIA | IRVINE, CA | - | Assistant Behavior Analyst | 03/10/2025 |
| FINESTONE, ANGELIQUE | MARTINEZ, CA | PHD | Psychologist | 04/23/2024 |
| FINGLAND, TERESA | NEW ULM, MN | MS, CCC-SLP | Speech-Language Pathologist | 03/29/2007 |
| FINISH LINE THERAPY LLCORG | WARREN, AR | - | Mental Health Counselor | 09/22/2026 |
| FINK, AMBER | FORT LEAVENWORTH, KS | - | RBT | 09/22/2026 |
| FINKELSTON-BROWN, ALEXANDRA | FORT COLLINS, CO | LPC | Mental Health Counselor | 07/21/2026 |
| FINLEY, ROBIN | ALEXANDRIA, VA | - | RBT | 09/21/2026 |
| FINN, LINDA | ROUND ROCK, TX | LPC-S | Mental Health Counselor | 03/16/2021 |
| FINNEGAN, ROSEBELLA | DANBURY, CT | MA | BCBA | 08/10/2017 |
| FISCHER, ANCA | ALLENDALE, MI | LMSW | Clinical Social Worker | 09/12/2022 |
| FISCHER, HALEY | WILMINGTON, NC | LCSW | Clinical Social Worker | 05/15/2023 |
| FISCHER, LYNDSI | WEST RUTLAND, VT | MA | Mental Health Counselor | 08/12/2019 |
| FISCHER, SHANNON | KIRKWOOD, MO | LPC | Professional Counselor | 04/16/2021 |
| FISH, CHALTU | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| FISHER, AARON | NORCROSS, GA | - | Counselor | 09/24/2026 |
| FISHER, ABBY | ANN ARBOR, MI | LPC | Mental Health Counselor | 11/06/2018 |
| FISHER, ASHLEY | ROCKWALL, TX | LPC | Counselor | 10/06/2022 |
| FISHER, HAYLEY | THORNTON, CO | - | Counselor | 09/23/2026 |
| FISHER, JANEAN | MONROVIA, CA | - | RBT | 03/11/2021 |
| FISHER, JILL | MOSINEE, WI | - | Speech-Language Pathologist | 09/21/2026 |
| FISHER, LAURA | LAS VEGAS, NV | LCPC | Professional Counselor | 08/06/2015 |
| FISHER, MAKAYLA | STUART, FL | - | RBT | 09/21/2026 |
| FISHMAN, JAMES | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| FITZGERALD, MARY ANN | WETHERSFIELD, CT | PC | Professional Counselor | 06/14/2007 |
| FITZGERALD, MORGAN | MANSFIELD, TX | M.S., CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| FITZPATRICK, ALICIA | TOMS RIVER, NJ | - | BCBA | 09/22/2026 |
| FITZPATRICK, KRISTEN | MIDDLEVILLE, MI | LMSW | Clinical Social Worker | 06/23/2026 |
| FITZSIMMONS, HEIDI | TULSA, OK | - | Case Manager/Care Coordinator | 09/21/2026 |
| FIVE STAR SUPPORT SERVICES LLCORG | O FALLON, MO | - | Community/Behavioral Health Agency | 09/22/2026 |
| FLACK, JENNIFER | PHOENIX, AZ | LCSW | Clinical Social Worker | 02/09/2017 |
| FLAGEL, BARBARA | CEDAR RAPIDS, IA | LMSW | Clinical Social Worker | 06/21/2021 |
| FLAGG, COURTNAY | GREELEY, CO | BCBA | BCBA | 07/07/2022 |
| FLAM-JONES, YAEL | BROOKLYN, NY | - | Mental Health Counselor | 12/07/2021 |
| FLAMBAUM, SYDNEY | WASHINGTON, DC | CCC-SLP | Speech-Language Pathologist | 01/09/2025 |
| FLAME COUNSELING COALITION LLCORG | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| FLANAGAN, CATHERINE | LITTLETON, CO | - | Counselor | 09/23/2026 |
| FLANAGAN, KELLY | EVANSTON, IL | LPC | Mental Health Counselor | 09/23/2026 |
| FLANAGAN, PAIGE | FAIRMONT, WV | MS | Counselor | 03/24/2023 |
| FLANARY, STEVEN | FRANKLIN, ID | LCSW | Mental Health Counselor | 02/27/2017 |
| FLANDERS, ALAN | BROOKINGS, OR | - | Professional Counselor | 09/22/2026 |
| FLEGEL, KENDRA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 07/14/2025 |
| FLEMING, MIRANDA | FRISCO, TX | MS, LPC-ASSOCIATE | Mental Health Counselor | 10/18/2021 |
| FLEMING, SAXON | ALBUQUERQUE, NM | - | Professional Counselor | 01/19/2026 |
| FLEMINGS, CADENA | THORNTON, CO | - | Mental Health Counselor | 09/23/2026 |
| FLETCHER, SHANE | CHARLESTON AFB, SC | LCSW | Clinical Social Worker | 07/21/2022 |
| FLEXIBLE WORKPLACE INITIATIVEORG | SUGAR LAND, TX | - | Case Management Agency | 05/04/2018 |
| FLICEK, AMBER | AUGUSTA, GA | OT | RBT | 01/22/2019 |
| FLIEG, SCOTT | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| FLOERSCH, SAMANTHA | KIRKLAND, WA | - | Addiction (Substance Use Disorder) Counselor | 08/07/2020 |
| FLOHR, HANNAH | KING OF PRUSSIA, PA | - | BCBA | 12/07/2021 |
| FLORENCE, ZOE | TOLEDO, OH | - | RBT | 09/22/2026 |
| FLORES JACOBO, LUCERO | WATSONVILLE, CA | - | RBT | 09/22/2026 |
| FLORES LOPEZ, EDITH | COVINGTON, GA | - | Speech-Language Pathologist | 09/22/2026 |
| FLORES MACHUCA, MARITZA | CONCORD, CA | - | RBT | 09/22/2026 |
| FLORES MARTELL, YULEISSY | LEHIGH ACRES, FL | - | RBT | 09/24/2026 |
| FLORES-BONILLA, DANIELA | SARTELL, MN | - | RBT | 09/22/2026 |
| FLORES-MCGREW, VERONICA | ELK GROVE, CA | - | Clinical Social Worker | 06/30/2010 |
| FLORES, ADRIAN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| FLORES, CRISTIAN | WALNUT CREEK, CA | - | BCBA | 12/16/2024 |
| FLORES, DEISI | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| FLORES, FABBIAN | RANCHO CUCAMONGA, CA | - | RBT | 09/21/2026 |
| FLORES, GABRIELLE | VIRGINIA BEACH, VA | MA, BCABA | RBT | 08/08/2019 |
| FLORES, HANNAH | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| FLORES, JACQUELINE | ONTARIO, CA | - | RBT | 09/24/2026 |
| FLORES, JASMIN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| FLORES, JULISSA | FREMONT, CA | - | RBT | 09/22/2026 |
| FLORES, KAYLA | KENOSHA, WI | LCSW | Clinical Social Worker | 09/21/2026 |
| FLORES, LEEANDRA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| FLORES, MARC | CHARLESTON, SC | LISW-CP | Clinical Social Worker | 10/20/2015 |
| FLORES, MARINA | HOUSTON, TX | M.S. | Professional Counselor | 09/25/2026 |
| FLORES, ROSY | LOS ANGELES, CA | - | Mental Health Counselor | 08/11/2016 |
| FLORES, TAYLOR | OCEANSIDE, CA | M.S. CCC-SLP | RBT | 12/14/2017 |
| FLORES, VIVIANNE | SAN BERNARDINO, CA | - | RBT | 09/17/2024 |
| FLORIDA SPEECH & LANGUAGE LLCORG | CLERMONT, FL | - | Speech-Language Pathologist | 04/13/2007 |
| FLORIDA STATE UNIVERSITYORG | TALLAHASSEE, FL | - | Speech-Language Pathologist | 10/06/2005 |
| FLOTO, KASSIDIE | ROY, UT | - | RBT | 09/21/2026 |
| FLOURISH DOT SUPPORT LCSW PLLCORG | CLINTON, NY | - | Clinical Social Worker | 03/07/2022 |
| FLOW BEHAVIORAL HEALTH PLLCORG | KALISPELL, MT | - | Addiction (Substance Use Disorder) Counselor | 12/01/2025 |
| FLOWERS, SHERITA | FORNEY, TX | - | Clinical Social Worker | 09/22/2026 |
| FLOWERS, STACEY | WINSTED, CT | LPC-A | Professional Counselor | 09/26/2026 |
| FLOYD, BRYANNA | BELLEFONTAINE, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| FLOYD, MEGAN | SOMERSET, KY | - | Case Manager/Care Coordinator | 09/23/2026 |
| FLOYD, WILLIAM | AUSTIN, TX | - | RBT | 03/07/2023 |
| FLUDD, LATISA | OAK RIDGE, TN | - | Specialist | 09/23/2026 |
| FLUEGGE, MAYA | MANKATO, MN | LICSW | Clinical Social Worker | 02/27/2023 |
| FLYNN, KAITLYNN | COVINA, CA | - | RBT | 12/08/2022 |
| FOCKEL, MELISSA | ELM GROVE, WI | MSW LCSW | Clinical Social Worker | 02/08/2006 |
| FOCKLER, AILISH | ZIONSVILLE, IN | - | RBT | 09/22/2026 |
| FOCUS BEHAVIORAL HEALTH SERVICES LLCORG | HICKORY, NC | - | Community/Behavioral Health Agency | 09/23/2026 |
| FOERST, ELIZABETH | CARMEL, NY | LMHC | Mental Health Counselor | 04/10/2019 |
| FOFIE-GONZALEZ, DORIS | BROOKLYN, NY | LCSW | Clinical Social Worker | 12/15/2011 |
| FOLEY, IRES | RICHMOND, VA | LCSW | Clinical Social Worker | 09/23/2026 |
| FOLEY, SAVANNA | CALDWELL, ID | - | Counselor | 03/07/2025 |
| FOLEY, SEANARIA | DEERFIELD BEACH, FL | - | RBT | 09/23/2026 |
| FOLLESVOLD, JUSTIN | AUBURN, CA | RADT | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| FOLLOW YOUR HEART COUNSELING LLCORG | LITTLE EGG HARBOR TWP, NJ | - | Clinical Social Worker | 09/21/2026 |
| FONTENELLE, DARLENE | VIRGINIA BEACH, VA | - | RBT | 09/21/2026 |
| FONTENOT, MADISON | CHICAGO, IL | MS, LPC | Mental Health Counselor | 09/14/2026 |
| FONTES, ELYSSA | BRIDGEWATER, MA | - | RBT | 09/26/2026 |
| FOOKSON, SABRINA | WATERTOWN, MA | - | Mental Health Counselor | 09/24/2026 |
| FOOTE, HANNAH | GIG HARBOR, WA | LMHCA | Mental Health Counselor | 09/22/2026 |
| FOOTPRINTS OF CHANGE COUNSELING PLLCORG | CANISTOTA, SD | - | Professional Counselor | 11/08/2021 |
| FOR THE LOVE OF YOU COUNSELING LLCORG | COUNTRY CLUB HILLS, IL | - | Clinical Social Worker | 03/01/2025 |
| FORBES, VIOLET | CLEARWATER, FL | LCSW | Clinical Social Worker | 09/04/2008 |
| FORD, AMANDA | INDIANAPOLIS, IN | - | Case Manager/Care Coordinator | 09/25/2026 |
| FORD, KIANNA | WESTAMPTON, NJ | - | Mental Health Counselor | 09/22/2026 |
| FORD, MICHAELA | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| FORD, SHERITA | RICHMOND, VA | - | Clinical Social Worker | 09/24/2026 |
| FOREMAN, DAMANIQUE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| FOREVER HEARTS LLCORG | MEMPHIS, TN | - | Case Manager/Care Coordinator | 09/23/2026 |
| FORGING ROOTS, PLLCORG | LUFKIN, TX | - | Clinical Social Worker | 12/01/2025 |
| FORISTER, VANESSA | BALLWIN, MO | PLBA | BCBA | 09/25/2026 |
| FORNEY, VEDETTE | COLORADO SPRINGS, CO | - | BCBA | 12/23/2025 |
| FORSMAN, DOMINIQUE | CHURCHTON, MD | - | Counselor | 09/27/2024 |
| FORTENER, HAILEY | LOS GATOS, CA | - | RBT | 01/17/2024 |
| FOSS, FARRIN | WESTMINSTER, CO | MA, LPC | Professional Counselor | 09/21/2026 |
| FOSS, JULIE | MALDEN, MA | - | Mental Health Counselor | 09/19/2007 |
| FOSTER, ASHER | PORTLAND, OR | - | RBT | 09/21/2026 |
| FOSTER, ASIA | LILBURN, GA | - | RBT | 09/21/2026 |
| FOSTER, DEUNTE | AUGUSTA, GA | M.ED NCC LAPC | Professional Counselor | 09/23/2026 |
| FOSTER, FREDRIKA | SPARTANBURG, SC | MA, LPC | Professional Counselor | 07/07/2022 |
| FOSTER, SHENELLE | OAKLAND, CA | LCSW, LICSW | Clinical Social Worker | 09/22/2017 |
| FOSTER, SOPHIA | SHARON, WI | - | Speech-Language Pathologist | 09/25/2026 |
| FOUNTAIN, XAVIER | FOUNTAIN, CO | - | RBT | 09/21/2026 |
| FOUST, CALLIE | KERNERSVILLE, NC | - | RBT | 09/25/2026 |
| FOWLER, JUWONJA | BRYANT, AR | - | RBT | 09/21/2026 |
| FOWLER, MONIQUE | DECATUR, GA | - | Clinical Social Worker | 09/21/2026 |
| FOWLER, SAMARA | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| FOWLER, TAMARA | LITTLE ROCK, AR | - | Speech-Language Pathologist | 01/27/2016 |
| FOX, BRYN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| FOX, CASSANDRA | RIVERSIDE, CA | LPCC | Mental Health Counselor | 07/15/2019 |
| FOX, ELYSE | BROOKLYN, NY | - | Mental Health Counselor | 07/30/2022 |
| FOX, JAMES | LOVELAND, CO | ED.D. | Addiction (Substance Use Disorder) Counselor | 07/06/2007 |
| FOX, REEM | HUMBLE, TX | - | Mental Health Counselor | 09/21/2026 |
| FOX, STEPHANIE | LACEY, WA | LMHCA | Mental Health Counselor | 09/24/2026 |
| FRALEY, CARLEY | BAYTOWN, TX | - | BCBA | 02/27/2026 |
| FRAMEWORK THERAPYORG | WAYNE, PA | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| FRANCIS, PRISCILLA | HOUSTON, TX | LCSW | Clinical Social Worker | 02/28/2018 |
| FRANCIS, TARA | LOS ANGELES, CA | - | RBT | 09/25/2026 |
| FRANCIS, UVOLTTA | GILBERT, AZ | LPC-22105 | Professional Counselor | 06/20/2018 |
| FRANCIS, VICTORIA | RHOME, TX | - | Mental Health Counselor | 09/22/2026 |
| FRANCISCO, JASMINE | ANCHORAGE, AK | - | RBT | 09/24/2026 |
| FRANCISCO, MAYELIN | ANCHORAGE, AK | - | RBT | 09/24/2026 |
| FRANCO, ADILENE | NORTHBROOK, IL | - | Case Manager/Care Coordinator | 02/02/2022 |
| FRANCO, CAROLINA | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| FRANCO, JENNIFFER | TUCSON, AZ | - | RBT | 09/26/2026 |
| FRANK, GILLYAN | ALEXANDRIA, VA | - | RBT | 09/01/2026 |
| FRANK, HARERIMANA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| FRANKLIN, BRYAUNA | BATON ROUGE, LA | - | Case Manager/Care Coordinator | 09/30/2022 |
| FRANKLIN, TARA | BEEVILLE, TX | LPC | Professional Counselor | 09/13/2017 |
| FRANZIA, AUDREY | WINSTON SALEM, NC | LCAS | Addiction (Substance Use Disorder) Counselor | 11/08/2018 |
| FRASCONE, ADRIANA | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| FRASER, KENTYAH | NEW YORK, NY | LMFT | Mental Health Counselor | 05/20/2014 |
| FRASHER, JADE | EAST TAWAS, MI | - | Clinical Social Worker | 09/24/2026 |
| FRATARCANGELI, MARK | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| FRAZIER, JENNIFER | SLAUGHTERVILLE, OK | - | Case Management Agency | 11/22/2025 |
| FRAZIER, SHELLEY | SPRINGFIELD, MO | MS, LPC | Professional Counselor | 01/04/2016 |
| FRECHETTE, MOLLY | PORTLAND, OR | LCSW | Mental Health Counselor | 05/21/2020 |
| FREE, ALEYDA | TAMPA, FL | LCSW | Professional Counselor | 04/13/2022 |
| FREEBERG, AMY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| FREEL, CHRISTA | WILMINGTON, NC | - | RBT | 09/22/2026 |
| FREELS, JORDAN | BETHLEHEM, PA | - | RBT | 12/13/2021 |
| FREEMAN-BOOKER, LAURETTA | MONTGOMERY, AL | M.ED., LPC, NCC | Mental Health Counselor | 09/21/2026 |
| FREEMAN, ARIEL | CHARLOTTE, NC | - | Clinical Social Worker | 09/22/2026 |
| FREEMAN, CATHERINE | DECATUR, GA | RBT | RBT | 09/22/2026 |
| FREEMAN, ELIANA | CAMBRIDGE, MA | LICSW | Clinical Social Worker | 04/30/2021 |
| FREEMAN, JAHTERIA | UPPER MARLBORO, MD | - | RBT | 09/21/2026 |
| FREEMAN, LEXIE | BAXTER, MN | - | BCBA | 03/02/2020 |
| FREEMAN, MICHAELANN | MANSFIELD, TX | - | RBT | 09/21/2026 |
| FREEMAN, TRACY | MESA, AZ | LAC | Mental Health Counselor | 11/13/2014 |
| FREEME PSYCHOTHERAPY LLCORG | WATERVILLE, ME | - | Clinical Social Worker | 09/22/2026 |
| FREEMIND THERAPY INC.ORG | FORT LAUDERDALE, FL | - | Mental Health Counselor | 08/10/2026 |
| FREISLEBEN, MARIE | BOSTON, MA | - | Mental Health Counselor | 09/25/2026 |
| FREISLINGER, KLAUDIA | WATERVLIET, MI | - | Speech-Language Pathologist | 09/22/2026 |
| FREITAS, DANIEL | YREKA, CA | - | Counselor | 09/22/2026 |
| FRENCH, KATIE | COLORADO SPRINGS, CO | - | Case Manager/Care Coordinator | 09/21/2026 |
| FRESHWATER, OLIVIA | CHICAGO, IL | - | Counselor | 09/25/2026 |
| FRESNO AMERICAN INDIAN HEALTH PROJECTORG | FRESNO, CA | - | Case Manager/Care Coordinator | 05/03/2012 |
| FRICKE, WHITNEY | CHICAGO, IL | LPC, NCC | Professional Counselor | 07/31/2018 |
| FRIDDELL, KYLIE | SAN DIEGO, CA | - | RBT | 09/23/2026 |
| FRIEDMAN, BETHANY | NEW YORK, NY | LMHC | Mental Health Counselor | 09/23/2026 |
| FRIERA, SYDNEY | REDWOOD CITY, CA | CATC-II | Addiction (Substance Use Disorder) Counselor | 04/13/2023 |
| FRITZ, CARA | CHETEK, WI | MS, CCC-SLP | Speech-Language Pathologist | 11/21/2014 |
| FRITZ, CATHERINE | ANN ARBOR, MI | LLPC | Professional Counselor | 09/23/2026 |
| FROHM, SAMANTHA | MASSENA, NY | BCBA, LBA | BCBA | 09/24/2026 |
| FROLA, JASON | PITTSBURGH, PA | LPC | Professional Counselor | 11/16/2022 |
| FRONTIER INFUSION CENTER RP LLCORG | GEORGETOWN, TX | - | Clinic/Center | 11/28/2023 |
| FROST, TAYLOR | NEW YORK, NY | LMSW | RBT | 11/10/2020 |
| FRUGIER, AMY | AURORA, CO | - | Professional Counselor | 12/13/2019 |
| FRUHLING, MELANIE | THORNTON, CO | - | Counselor | 09/22/2026 |
| FRYAR, KATAYA | DENHAM SPRINGS, LA | - | Mental Health Counselor | 03/20/2025 |
| FRYER, JORDAN | SOUTH BARRINGTON, IL | - | Mental Health Counselor | 09/22/2026 |
| FRYER, LAUREN | RICHARDSON, TX | PH.D. | Psychologist | 08/04/2008 |
| FUCHS, CHEYENNE | WAUKESHA, WI | - | Case Manager/Care Coordinator | 09/21/2026 |
| FUCHS, KATHLEEN | CHARLOTTESVILLE, VA | PH.D. | Psychologist | 11/07/2006 |
| FUGATE, LAUREN | KNOXVILLE, TN | LPC-MHSP, NCC | Mental Health Counselor | 12/10/2007 |
| FUGEE, AMELIA | RICHMOND, VA | - | Mental Health Counselor | 09/21/2026 |
| FUHRIMAN-SILLS, DAMON MILES | BRIGHAM CITY, UT | - | RBT | 07/23/2026 |
| FUJIKAWA, KAREN | MADISON, WI | MS, LCSW | Clinical Social Worker | 06/28/2010 |
| FULL MEASURE THERAPY PLLCORG | CHICAGO, IL | - | Professional Counselor | 09/23/2026 |
| FULL SAIL THERAPY SERVICES PLLCORG | HOLLAND, MI | - | Clinical Social Worker | 05/14/2026 |
| FULLER, MICHAEL | WEST JORDAN, UT | - | RBT | 09/22/2026 |
| FULLER, MORGAN | PORTAGE, MI | - | RBT | 09/21/2026 |
| FULTON, AARON | SPRINGFIELD, OR | - | Mental Health Counselor | 09/24/2026 |
| FULTZ, JASMINE | CHICAGO, IL | - | Clinical Social Worker | 09/23/2026 |
| FUNDOH CHUMBA, BERTRAND | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/23/2026 |
| FUNG, KUULEILAUAE | HONOLULU, HI | - | RBT | 09/25/2026 |
| FUNK-CHANCE, ANNE | WOOSTER, OH | LSW | Clinical Social Worker | 01/30/2014 |
| FUNK, MARIAH | GRASS VALLEY, CA | - | Clinical Social Worker | 12/03/2021 |
| FURBISH, ELIZABETH | CHICAGO, IL | LCPC | Professional Counselor | 06/26/2023 |
| FUREY, MELANIE | OCONOMOWOC, WI | - | Speech-Language Pathologist | 03/06/2020 |
| FUSION BEHAVIORAL CARE, LLCORG | CONCORD, NH | - | Mental Health Counselor | 02/29/2024 |
| FUSION CHILD DEVELOPMENT CENTER INC.ORG | SUN VALLEY, CA | - | Community/Behavioral Health Agency | 03/12/2026 |
| GABBANI, UMNIYA | BETHESDA, MD | - | Mental Health Counselor | 05/15/2023 |
| GABEL, DAVID | WELLINGTON, OH | - | Clinical Social Worker | 09/24/2026 |
| GABRIEL, WEDDIE | DURHAM, NC | - | RBT | 09/23/2026 |
| GABRIELLA PASSAMANTE, LLCORG | HAMMONTON, NJ | - | Mental Health Counselor | 09/21/2026 |
| GADBERRY, CAROLINA | PHOENIX, AZ | - | RBT | 09/22/2026 |
| GAFFNEY, CRYSTAL | UNION, SC | - | RBT | 09/23/2026 |
| GAGLIA, JOSEPH | RHINEBECK, NY | MHC-LP | Mental Health Counselor | 09/21/2026 |
| GAH ABA SERVICES INCORG | VISALIA, CA | - | BCBA | 03/23/2026 |
| GAILEY, BEATRICE | SEATTLE, WA | SUDP | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| GAINER, DANIEL | AKRON, OH | LSW | Addiction (Substance Use Disorder) Counselor | 05/28/2020 |
| GAINES, JODIE | PLYMOUTH, OH | LCSW, LCAC | Addiction (Substance Use Disorder) Counselor | 08/24/2022 |
| GAINES, MYSHAWN | FAIRFIELD TOWNSHIP, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| GAINOUS, KENT | ORLANDO, FL | - | RBT | 09/23/2026 |
| GAITERS, TONYA | COLUMBUS, OH | - | Mental Health Counselor | 09/23/2026 |
| GALBREATH, MACKENZIE | ALLEGAN, MI | MA CCC-SLP | Speech-Language Pathologist | 05/31/2018 |
| GALIANO CAMEJO, ANA | MIAMI, FL | - | RBT | 08/18/2025 |
| GALICHANSKY, JENNIFER | CENTREVILLE, MI | CFLE | Clinical Social Worker | 03/31/2022 |
| GALICIA, CHRISTIAN | RANCHO CUCAMONGA, CA | BEHAVIOR TECHNICIAN | BCBA | 11/30/2018 |
| GALILEO MEDICAL GROUP, NM PCORG | NEW YORK, NY | - | Mental Health Counselor | 01/10/2022 |
| GALINDO RODRIGUEZ, KAREN | LYNWOOD, CA | BA | Clinical Social Worker | 08/23/2022 |
| GALLAGHER, ELIZABETH | NEEDHAM, MA | - | Speech-Language Pathologist | 09/22/2026 |
| GALLARDO, ANGELO | DOWNEY, CA | - | RBT | 09/24/2026 |
| GALLEGOS, ANN | SAN JOSE, CA | - | Mental Health Counselor | 12/07/2015 |
| GALLEGOS, MARTHA | ARLINGTON, TX | - | Speech-Language Pathologist | 05/06/2015 |
| GALLEGOS, MELANIE | ALBUQUERQUE, NM | - | Case Manager/Care Coordinator | 05/01/2026 |
| GALLEGOS, OMAR | BROWNSVILLE, TX | - | RBT | 04/13/2026 |
| GALM, KESHA | SPOKANE, WA | - | RBT | 09/22/2026 |
| GALORE ANGELESORG | RALEIGH, NC | - | Community/Behavioral Health Agency | 09/15/2026 |
| GALVAN ORDUNA, RICARDO | COSTA MESA, CA | - | RBT | 09/24/2026 |
| GALVAN, ANA | AUSTIN, TX | - | RBT | 09/22/2026 |
| GALVAN, JACQUELYN | SAN DIEGO, CA | - | Assistant Behavior Analyst | 09/21/2026 |
| GALVAN, MELISSA | PAW PAW, MI | LLMSW | Clinical Social Worker | 08/27/2014 |
| GALVAN, OFILIA | MANTECA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| GALVEZ SOLANO, PATRICIA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GAMARRA ALIAGA, ROSA | PATERSON, NJ | - | Assistant Behavior Analyst | 09/23/2026 |
| GAMBELUNGHE, EMMA | MURPHY, NC | - | RBT | 05/31/2024 |
| GAMEZ-GARCIA, LEONARDO | HAINES CITY, FL | - | RBT | 09/21/2026 |
| GAMEZ, MAYA | ANCHORAGE, AK | - | Speech-Language Pathologist | 05/08/2013 |
| GAMEZ, SARAI | LA VISTA, NE | PLMHP | Mental Health Counselor | 06/26/2025 |
| GAMMAGE, SHANE | MINNEAPOLIS, MN | - | BCBA | 06/05/2018 |
| GANDEE, OLIVIA | WINFIELD, WV | BCBA | BCBA | 09/22/2026 |
| GANDY, TAYLOR | SAN DIEGO, CA | - | RBT | 09/23/2026 |
| GANINO, AUSTIN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| GAONA, ESTEBAN | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GARAY, GABRIEL | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GARBA, JESSICA | EDMOND, OK | - | Speech-Language Pathologist | 09/25/2026 |
| GARBER, JENNIFER | MINNEAPOLIS, MN | LICSW | Clinical Social Worker | 05/01/2025 |
| GARBO, JOED | ROSEMEAD, CA | - | Day Training/Habilitation Specialist | 07/10/2025 |
| GARCIA BAEZ, MAYRA | MIAMI, FL | - | RBT | 11/02/2020 |
| GARCIA BASTIDAS, KARLA | ROHNERT PARK, CA | RBT | RBT | 09/22/2026 |
| GARCIA FUNDORA, ANNERIS | HOLIDAY, FL | - | RBT | 09/25/2026 |
| GARCIA GODINEZ, CLAUDIA | LOS ANGELES, CA | - | Clinical Social Worker | 09/24/2008 |
| GARCIA LOPEZ, EVELIN | JACKSONVILLE, NC | - | RBT | 09/22/2026 |
| GARCIA RAMOS, YUNAIRA | CAPE CORAL, FL | - | RBT | 01/26/2024 |
| GARCIA RODRIGUEZ, MARIA | MODESTO, CA | - | RBT | 09/26/2026 |
| GARCIA STEVENSON, NADIA | BELEN, NM | - | RBT | 09/23/2026 |
| GARCIA-ARELLANO, SYLVIA | SAN PEDRO, CA | - | RBT | 09/21/2026 |
| GARCIA-GORDILLO, JOCELYN | POMONA, CA | - | RBT | 09/22/2026 |
| GARCIA, ALEXANDRA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| GARCIA, ALINY | ANAHEIM, CA | - | RBT | 09/23/2026 |
| GARCIA, ANGEL | RIVERBANK, CA | - | RBT | 09/21/2026 |
| GARCIA, ARIANA | LOS LUNAS, NM | - | RBT | 09/23/2026 |
| GARCIA, CARLOS | MIAMI, FL | LMHC, MSC, MBA | Mental Health Counselor | 12/17/2024 |
| GARCIA, CAROLINA | LINCOLN, NE | PLMHP | Mental Health Counselor | 02/08/2024 |
| GARCIA, CRYSTAL | SHERMAN OAKS, CA | - | RBT | 09/21/2026 |
| GARCIA, CYNTHIA | SOUTH LAKE TAHOE, CA | - | Case Manager/Care Coordinator | 09/26/2026 |
| GARCIA, DANNA | SUWANEE, GA | - | RBT | 09/26/2026 |
| GARCIA, DAVID | HACKENSACK, NJ | - | Mental Health Counselor | 09/24/2026 |
| GARCIA, DENISSE | RIVERSIDE, CA | - | RBT | 09/18/2026 |
| GARCIA, DESTINY | EL PASO, TX | - | Clinical Social Worker | 09/24/2026 |
| GARCIA, ERNEST | FRESNO, CA | - | Addiction (Substance Use Disorder) Counselor | 11/04/2024 |
| GARCIA, ESTEVAN | NORWALK, CT | - | RBT | 09/23/2026 |
| GARCIA, HAILEY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GARCIA, JANESSA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| GARCIA, JORGE | HOLYOKE, MA | - | Mental Health Counselor | 09/21/2026 |
| GARCIA, K'LEE | LOS LUNAS, NM | - | RBT | 09/23/2026 |
| GARCIA, KATHERINE | SAINT LOUIS, MO | - | Mental Health Counselor | 09/23/2026 |
| GARCIA, MARIAH | COSTA MESA, CA | - | RBT | 09/22/2026 |
| GARCIA, MARICIA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| GARCIA, MARLENE | TORRANCE, CA | - | Professional Counselor | 07/24/2024 |
| GARCIA, MAYRA | SAN ANTONIO, TX | - | Mental Health Counselor | 05/11/2021 |
| GARCIA, MELINA | ORANGE, CA | - | RBT | 09/21/2026 |
| GARCIA, MERCEDES | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| GARCIA, MIRALYS | BRIDGEPORT, CT | LCSW | Clinical Social Worker | 09/25/2026 |
| GARCIA, SAMANTHA | SAINT MARYS, GA | RBT | RBT | 09/21/2026 |
| GARCIA, STEPHANIE | KISSIMMEE, FL | RBT | RBT | 09/22/2021 |
| GARDNER-JACKSON, SHIRRON | COLUMBUS, OH | LCDCIII | Addiction (Substance Use Disorder) Counselor | 03/15/2017 |
| GARDNER, ERICA | DEARBORN, MI | - | RBT | 09/24/2026 |
| GARDNER, I'YONNA | PALM COAST, FL | - | RBT | 09/21/2026 |
| GARDNER, JALIN | BALTIMORE, MD | - | RBT | 09/21/2026 |
| GARDNER, LYNDZEAHIA | BURNSVILLE, MN | - | RBT | 09/21/2026 |
| GARDNER, QUINN | NEW YORK, NY | - | Speech-Language Pathologist | 01/11/2021 |
| GARDNER, RIVA | LAGUNA BEACH, CA | LCSW | Clinical Social Worker | 08/04/2020 |
| GARFF, TAYLOR | POST FALLS, ID | LCPC, CMHC | Mental Health Counselor | 07/30/2014 |
| GARKAVCHENKO, OXANA | KEY LARGO, FL | PHD, LMHC, BCBA | Case Manager/Care Coordinator | 03/17/2015 |
| GARL, SARA | GURNEE, IL | LCPC | Mental Health Counselor | 01/07/2016 |
| GARLEY, DANIEL | LOS LUNAS, NM | - | RBT | 09/25/2026 |
| GARLOBO, ESMIRNA | CAPE CORAL, FL | RBT | RBT | 10/07/2017 |
| GARNETT, TYKYYA | GLASGOW, KY | - | RBT | 08/25/2026 |
| GARNICA, ADRIANA | EL PASO, TX | - | RBT | 09/21/2026 |
| GARNICA, ISABEL | CORONA, CA | - | Mental Health Counselor | 08/25/2025 |
| GARRASTEGUI SEGARRA, ARIANA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GARRETT, AALIYAH | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| GARRETT, MORGAN | DURHAM, NC | - | BCBA | 07/23/2020 |
| GARRETT, NICOLE | LAS VEGAS, NV | - | RBT | 09/21/2026 |
| GARRISON, ANNAH | GRAIN VALLEY, MO | - | RBT | 09/23/2026 |
| GARRITANO, GAIL MARGARETTE | LAS VEGAS, NV | BCBA, LBA | BCBA | 10/31/2019 |
| GARVIN, VICTORIA | BELLINGHAM, WA | - | Clinical Social Worker | 07/01/2022 |
| GARYANTES, ABIGAIL | PITTSBURGH, PA | - | Clinical Social Worker | 05/12/2026 |
| GARZA, CIARA | WESTCHASE, FL | - | RBT | 09/21/2026 |
| GARZA, FRANCISCO | MIDLAND, TX | LCSW | Clinical Social Worker | 09/24/2026 |
| GARZA, JORGE | MISSION, TX | M.S., CCC-SLP | Speech-Language Pathologist | 08/14/2018 |
| GARZA, VANESSA | DALLAS, TX | - | RBT | 09/23/2026 |
| GASHI-SENKA, MERITA | STATEN ISLAND, NY | - | Mental Health Counselor | 05/06/2015 |
| GASKINS, NICOLE | LAKE WYLIE, SC | LPC-A, LCMHC-A | Professional Counselor | 02/13/2021 |
| GASPAROTTO, LAUREN | FARMINGTON, MI | LMSW | Clinical Social Worker | 10/17/2007 |
| GASSAWAY, HANNAH | MUSKOGEE, OK | M.S. CCC-SLP | Speech-Language Pathologist | 06/04/2024 |
| GATCHALIAN, SAMANTHA | HANFORD, CA | - | Speech-Language Pathologist | 09/21/2026 |
| GATHUA, SILVIAH | SEATTLE, WA | - | Specialist | 09/22/2026 |
| GATT, ADRIANNA | PORTLAND, OR | - | Counselor | 09/22/2026 |
| GATTI, MATTHEW | DETROIT, MI | LMSW | Clinical Social Worker | 09/23/2026 |
| GAUDIN, MACIE | BATON ROUGE, LA | LBA | BCBA | 09/24/2026 |
| GAULDIN, KIMBERLY | DANVILLE, VA | - | Addiction (Substance Use Disorder) Counselor | 02/01/2023 |
| GAUTHIER, KATRINA | NEWTON, NJ | - | Mental Health Counselor | 09/23/2026 |
| GAYED, JACENTA | UPPER MARLBORO, MD | BCBA | BCBA | 07/03/2023 |
| GAYLE, TAKIRAH | STOCKBRIDGE, GA | - | Professional Counselor | 08/04/2023 |
| GAYLOR, ELYCE | PLEASANTON, CA | - | BCBA | 02/22/2018 |
| GEHLHOFF, JUBILEE | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| GEHMAN, JOSHUA | SPRING, TX | - | RBT | 02/02/2019 |
| GEIBIG, KYLE | JOHNSTOWN, PA | BA | Community/Behavioral Health Agency | 07/19/2021 |
| GEIER, CHELSEA | BOULDER, CO | MA, LPCC | Mental Health Counselor | 06/09/2025 |
| GEIGER, MIA | FORT WAYNE, IN | - | RBT | 09/25/2026 |
| GEISINGER MEDICAL CENTERORG | COAL TOWNSHIP, PA | - | Clinic/Center | 09/20/2011 |
| GEISLER, MITCHELL | WAUWATOSA, WI | - | BCBA | 12/30/2022 |
| GEM HEALING GROUPORG | HOUSTON, TX | - | Clinical Social Worker | 05/10/2022 |
| GENDRON, ERIKA | GROVETON, NH | MS,CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| GENERAL BEHAVIOR ANALYSIS LLCORG | TAMPA, FL | - | BCBA | 03/17/2021 |
| GENERAL BEHAVIOR ANALYSIS LLCORG | LAKELAND, FL | - | BCBA | 08/14/2026 |
| GENESIS BEHAVIORAL HEALTH AND DEVELOPMENT LLCORG | WOBURN, MA | - | BCBA | 09/22/2026 |
| GENORE, GABRIELLA | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/21/2026 |
| GENOVEZ, SAMANTHA | GARDENA, CA | - | BCBA | 09/25/2026 |
| GENTLE CURRENT THERAPY PLCORG | NEWAYGO, MI | - | Professional Counselor | 08/22/2026 |
| GENTRY, REESE | WINSTON SALEM, NC | - | RBT | 09/24/2026 |
| GEO REENTRY INCORG | DOYLESTOWN, PA | - | Mental Health Counselor | 09/24/2026 |
| GEORGE, ARIEL | MEMPHIS, TN | - | RBT | 09/23/2026 |
| GEORGE, ORLANDO | SIOUX FALLS, SD | - | Professional Counselor | 08/22/2025 |
| GEORGE, RACHEL | BECKLEY, WV | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| GEORGE, RASHIDA | COLUMBIA, MD | - | Clinical Social Worker | 09/26/2026 |
| GEORGIA BAYERL LMSW PLLCORG | OKEMOS, MI | - | Clinical Social Worker | 09/23/2026 |
| GERACE, WESLEY | ROCHESTER, NY | - | Mental Health Counselor | 09/15/2026 |
| GEREMIA, CHRISTOPHER | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/16/2026 |
| GEREN, VICTORIA | EAST TAWAS, MI | - | RBT | 06/06/2025 |
| GERMAIN, ELIZABETH | CLEVELAND, OH | - | Case Manager/Care Coordinator | 08/15/2025 |
| GERMAN, ASHTON | CLARKSVILLE, TN | M.ED., BCBA, LBA | BCBA | 06/17/2019 |
| GERMINO, MARIBETH | CHICAGO, IL | LCPC | Professional Counselor | 03/17/2020 |
| GERNER, DONALD | NILES, OH | - | Mental Health Counselor | 07/22/2024 |
| GERRITS, VALERIE | OLYMPIA, WA | CCC-SLP | Speech-Language Pathologist | 06/05/2012 |
| GERTNER, SHANE | STERLING, CO | - | Case Manager/Care Coordinator | 09/25/2026 |
| GET OUT YOUR FEELINGS LLCORG | LAWTON, OK | - | Mental Health Counselor | 10/30/2025 |
| GETACHEW, NARDOS | LAS VEGAS, NV | RBT | RBT | 09/22/2026 |
| GFELLER, MALLORY | DOWNEY, CA | - | Day Training/Habilitation Specialist | 07/28/2026 |
| GHIRARDO, KEIANNA | KAYSVILLE, UT | - | RBT | 09/22/2026 |
| GHIRMAI, NARDOS | ELKRIDGE, MD | - | Clinical Social Worker | 09/21/2026 |
| GIAMMANCO, OLIVIA | BROOKFIELD, WI | LPC-IT | Professional Counselor | 05/16/2022 |
| GIAMPAOLI, JANICE | RED BLUFF, CA | ASW | Counselor | 07/14/2021 |
| GIBBINS, TASHINA | COBURG, OR | CADC-1 | Addiction (Substance Use Disorder) Counselor | 04/12/2024 |
| GIBBONS, ALEXIS | COVINA, CA | - | RBT | 09/23/2026 |
| GIBBONS, CHRISTINA | APO, AP | LICSW | Clinical Social Worker | 11/14/2023 |
| GIBBS, BOBBY | WATERFORD, MI | BA,, FADOP | Addiction (Substance Use Disorder) Counselor | 09/13/2006 |
| GIBBS, MARIA | SACRAMENTO, CA | - | RBT | 09/25/2026 |
| GIBBS, SARAH | NEWNAN, GA | MS-CCC SLP | Speech-Language Pathologist | 07/09/2025 |
| GIBBS, THOMAS | ALEXANDRIA, LA | - | Mental Health Counselor | 12/16/2018 |
| GIBBY, NICOLE | MONROE, MI | MSW LLSW | Addiction (Substance Use Disorder) Counselor | 12/11/2007 |
| GIBONS, ZOE | ELIZABETHTOWN, KY | - | RBT | 09/08/2025 |
| GIBSON, CARLA | ELLENWOOD, GA | APC | Mental Health Counselor | 09/24/2026 |
| GIBSON, JAYLIN | DEERFIELD BEACH, FL | - | RBT | 09/25/2026 |
| GIBSON, KATIE | PARSONS, TN | - | Speech-Language Pathologist | 07/28/2022 |
| GIBSON, MISTY | WASHINGTON, DC | - | Mental Health Counselor | 09/23/2026 |
| GIBSON, RILEY | WEST JORDAN, UT | - | RBT | 09/22/2026 |
| GIBSON, SAMANTHA | DOTHAN, AL | - | RBT | 09/18/2026 |
| GIL, MIA | GAINESVILLE, FL | - | RBT | 06/12/2026 |
| GILBERT, HANNAH | BOSTON, MA | LCSW | Clinical Social Worker | 07/15/2024 |
| GILBERT, PORCHE | MUSKEGON, MI | - | Counselor | 09/21/2026 |
| GILBERTSON, KRISTY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| GILCHRIST, KENNETH | ATTLEBORO, MA | LCSW | Clinical Social Worker | 04/29/2024 |
| GILES, ASHLEY | SANTA ANA, CA | - | RBT | 09/22/2026 |
| GILL, ALEENA | NEWARK, CA | - | RBT | 06/15/2026 |
| GILL, TORRIE | FRESNO, CA | - | Clinical Social Worker | 07/03/2017 |
| GILLANI, TAHZEEB | ALBUQUERQUE, NM | LMFT,LPC,NCC | Counselor | 04/01/2017 |
| GILLIAM, SAMAIYA | TAMPA, FL | - | RBT | 01/08/2026 |
| GILLIS, JULIA | ASHLAND, MA | - | Speech-Language Pathologist | 09/21/2026 |
| GILMER, KAYLIE | TUSCUMBIA, AL | - | RBT | 09/23/2026 |
| GILMORE, DESTINEE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/19/2024 |
| GILMORE, SAMANTHA | NEW YORK, NY | - | Mental Health Counselor | 09/24/2026 |
| GILMORE, SAVANNA | BARBOURVILLE, KY | MSW, CSW | Clinical Social Worker | 09/21/2026 |
| GILPIN, BETSY | HOLLY SPRINGS, NC | LCPC, LCMHC | Professional Counselor | 08/29/2014 |
| GILSON, KATELYN | COVINA, CA | - | RBT | 11/07/2024 |
| GILTNER, AMANDA | SEATTLE, WA | - | Counselor | 08/21/2023 |
| GINGLARDI, FRANKI | POST FALLS, ID | - | Clinical Social Worker | 09/22/2026 |
| GINTER, DOUGLAS | TUMWATER, WA | BSN, RN-BC, MHP | Mental Health Counselor | 01/06/2020 |
| GIRARD, KIRSTEN | TULSA, OK | - | RBT | 05/16/2024 |
| GIRLS&GOALS LLCORG | COLUMBUS, OH | - | Community/Behavioral Health Agency | 09/25/2026 |
| GIRON, JENNIFER | NOVI, MI | - | BCBA | 04/14/2017 |
| GIRSCH, JAMEE | SAN ANGELO, TX | BCBA | BCBA | 06/21/2023 |
| GIUFFRE, ELYSE | DOVER, NJ | LCSW | Clinical Social Worker | 07/24/2021 |
| GIULIANO, ALYANNA | SOUTH PORTLAND, ME | LMSW-CC | Clinical Social Worker | 09/23/2026 |
| GIWA, SABRINA | INDEPENDENCE, MO | LPC | Professional Counselor | 05/12/2011 |
| GKIMISIS, LEONIDAS | CHICAGO, IL | - | Professional Counselor | 03/01/2021 |
| GLADDEN, DAJANAE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| GLANT, ANDREA | BELLEVILLE, IL | LCSW | Clinical Social Worker | 06/10/2021 |
| GLASER, SHELBY | SEWARD, NE | ED.S., NCSP | Psychologist | 05/22/2025 |
| GLASS, JENNIFER | NEWINGTON, CT | - | Clinical Social Worker | 10/14/2008 |
| GLASS, KENNEDY | TOMBALL, TX | - | RBT | 09/21/2026 |
| GLASSMAN, EMILY | BROOKLYN, NY | - | RBT | 09/23/2026 |
| GLAZE, AMANDA | ROCHESTER HILLS, MI | LMSW | Clinical Social Worker | 12/31/2018 |
| GLEN MANOR COUNSELING, LTDORG | PEORIA, IL | - | Psychologist | 09/26/2006 |
| GLENN, APPHIA | WEST MELBOURNE, FL | RCSWI | Clinical Social Worker | 09/26/2022 |
| GLENN, JESSICA | WEST CHESTER, PA | LCSW-S | Clinical Social Worker | 02/15/2011 |
| GLENN, NATALIE | SACRAMENTO, CA | - | Mental Health Counselor | 09/24/2018 |
| GLENN, SARA | LARAMIE, WY | LCSW | Clinical Social Worker | 06/11/2024 |
| GLENN, TERRY | BELLEVILLE, IL | - | Counselor | 09/30/2019 |
| GLICKSTERN, TROY | VERNON HILLS, IL | LCPC | Professional Counselor | 02/23/2022 |
| GLOSEMEYER, JILL | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| GLOVER, ALAINA | NEW ORLEANS, LA | LPC | Professional Counselor | 11/04/2015 |
| GLOVER, ELAYNA | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| GLOW AND GROW THERAPYORG | TELL CITY, IN | - | Speech-Language Pathologist | 09/23/2026 |
| GLOWACKI, CHRISTOPHER | MATHER, CA | PSY.D. | Psychologist | 11/07/2019 |
| GLYNN, LAVORIS | IRWIN, PA | - | RBT | 09/22/2026 |
| GOBEN, ALEXANDRIA | ROCHESTER, NY | LCAT, ATR-BC | Counselor | 02/10/2021 |
| GOBLE, PHOEBE | KALAMAZOO, MI | RBT | RBT | 09/25/2026 |
| GOD SMILES MINISTRIESORG | HOUSTON, TX | - | Case Management Agency | 09/25/2023 |
| GODBEY, ADAM | GRASS VALLEY, CA | - | Speech-Language Pathologist | 09/22/2026 |
| GODDARD, MICHAEL | FT. LAUDERDALE, FL | - | Psychologist | 08/14/2021 |
| GODDARD, RACHEL | PORTLAND, OR | - | Professional Counselor | 08/17/2017 |
| GODFREY, RAPHAEL | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| GODINA ARTEAGA, DULCE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GODLEY, JADE | SAN BERNARDINO, CA | - | RBT | 11/25/2025 |
| GOEBEL, ANDREW | NEENAH, WI | - | Psychologist | 08/11/2016 |
| GOENTZEL, ELIZABETH | NORTH PLATTE, NE | - | Speech-Language Pathologist | 09/23/2026 |
| GOETZ, KASEY | LANSING, MI | - | Clinical Social Worker | 09/21/2026 |
| GOLAS, KELLY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| GOLD TIER COLLECTIVE, LLCORG | ERIE, PA | - | Clinical Social Worker | 09/21/2026 |
| GOLDBLATT, JONAH | NEW YORK, NY | MD | Specialist | 04/01/2021 |
| GOLDCARE THERAPY SERVICES PLLCORG | OCALA, FL | - | Mental Health Counselor | 09/21/2026 |
| GOLDEN HIVE ABA LLCORG | PORT CHARLOTTE, FL | - | Community/Behavioral Health Agency | 09/23/2026 |
| GOLDEN ROAD COUNSELINGORG | GOLDEN, CO | - | Professional Counselor | 09/21/2026 |
| GOLDEN TOUCH ABAORG | SALT LAKE CITY, UT | - | RBT | 09/24/2026 |
| GOLDEN-GOOD, MARY | WALSENBURG, CO | - | Mental Health Counselor | 12/08/2016 |
| GOLDEN-TAYLOR, TRANQUILLA | ORLANDO, FL | LMFT/LMHC | Mental Health Counselor | 10/09/2020 |
| GOLDEN, ALAN | DOWNEY, CA | - | Clinical Social Worker | 09/23/2026 |
| GOLDEN, BREIONA | COLUMBUS, OH | - | Case Manager/Care Coordinator | 12/05/2025 |
| GOLDFARB, RACHAEL | WALTHAM, MA | - | Clinical Social Worker | 03/19/2020 |
| GOLDY, CHLOIE | SILVERDALE, WA | - | RBT | 09/21/2026 |
| GOLISH, CABELA | TERRE HAUTE, IN | - | RBT | 09/21/2026 |
| GOMEZ ALVAREZ, RENEE | AUSTIN, TX | - | RBT | 09/22/2026 |
| GOMEZ DE LA CRUZ, CLEYVER | ORLANDO, FL | - | RBT | 07/15/2026 |
| GOMEZ GARCIA, GERALDINE | MARYLAND HEIGHTS, MO | - | RBT | 09/25/2026 |
| GOMEZ HERRERA, MIGUEL | WEST PALM BEACH, FL | - | Assistant Behavior Analyst | 09/04/2023 |
| GOMEZ LARA, DENISSE | CONCORD, CA | - | RBT | 09/23/2026 |
| GOMEZ QUINAREZ, MIRANDA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GOMEZ-GALVAN, VALERIA | AUSTIN, TX | SLP | Speech-Language Pathologist | 08/06/2018 |
| GOMEZ-SHIMABUKU, CHRISTOPHER | SAN BRUNO, CA | - | RBT | 09/23/2026 |
| GOMEZ, ANNA | MCALLEN, TX | LPC | Professional Counselor | 09/16/2021 |
| GOMEZ, BRENDA | SAN ANTONIO, TX | LPC, NCC | Professional Counselor | 09/29/2022 |
| GOMEZ, BRIANNA | DOWNEY, CA | - | RBT | 09/22/2026 |
| GOMEZ, LAURA | MODESTO, CA | - | RBT | 09/21/2026 |
| GOMEZ, NATALIA | LOMPOC, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| GOMEZ, RAQUEL | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GONCALVES, SARAH | WEBSTER, NY | - | Case Manager/Care Coordinator | 09/25/2026 |
| GONZALES, CAROLINE | DAYTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| GONZALES, CHEYENNE | AURORA, CO | LPC | Professional Counselor | 07/14/2023 |
| GONZALES, DANIELLE | DENVER, CO | - | Case Manager/Care Coordinator | 09/25/2026 |
| GONZALES, JOSEPH | POMONA, CA | - | RBT | 09/23/2026 |
| GONZALES, JOSHUA | COMSTOCK PARK, MI | CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| GONZALES, MARTHA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| GONZALES, SERGIO | FULLERTON, CA | - | Mental Health Counselor | 07/15/2025 |
| GONZALEZ AVILA, YURELIS | FORT PIERCE, FL | - | BCBA | 01/11/2021 |
| GONZALEZ BESIO, NEYMIS | PEMBROKE PINES, FL | - | Assistant Behavior Analyst | 10/15/2019 |
| GONZALEZ CARABALLO, JESSICA | ROXBURY, MA | - | Counselor | 12/18/2020 |
| GONZALEZ CHAVEZ, VALORIE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GONZALEZ CUEVAS, SYLVIA | SAN JOSE, CA | - | Speech-Language Pathologist | 09/25/2026 |
| GONZALEZ HERNANDEZ, ARLETY | MIAMI LAKES, FL | - | RBT | 11/20/2025 |
| GONZALEZ HERNANDEZ, MARIELYS | MIAMI, FL | - | Case Manager/Care Coordinator | 03/20/2025 |
| GONZALEZ MARTINEZ, YVETTE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| GONZALEZ NAVARRO, MARY TERE | SANTA ANA, CA | LCSW | Clinical Social Worker | 11/27/2017 |
| GONZALEZ RIVERA, RICHARD | BARRANQUITAS, PR | LCSW-CPNP, DSW(C) | Clinical Social Worker | 08/30/2024 |
| GONZALEZ TORRES, ANGEL | PORT ST LUCIE, FL | - | RBT | 09/25/2026 |
| GONZALEZ-DUFRESNE, EVANGELINA | WORCESTER, MA | MSW, LICSW | Clinical Social Worker | 08/30/2006 |
| GONZALEZ-PEREZ, MARIANA | STATESVILLE, NC | LCMHC-A | Mental Health Counselor | 01/20/2026 |
| GONZALEZ-SALAZAR, KAREN | IRVINE, CA | - | RBT | 09/23/2026 |
| GONZALEZ, ALEXANDRA | TORRANCE, CA | - | RBT | 11/19/2020 |
| GONZALEZ, AMANDA | SAN ANTONIO, TX | - | Speech-Language Pathologist | 09/22/2026 |
| GONZALEZ, ANABEL | BUFFALO GROVE, IL | BCBA | BCBA | 09/21/2026 |
| GONZALEZ, BERENIS | SAN DIEGO, CA | - | Mental Health Counselor | 12/29/2021 |
| GONZALEZ, BIANCA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| GONZALEZ, BRAYAM | FRESNO, CA | - | RBT | 09/21/2026 |
| GONZALEZ, DARLENE | CHICAGO, IL | - | RBT | 09/21/2026 |
| GONZALEZ, DAVID | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| GONZALEZ, DIANA | TAMARAC, FL | - | RBT | 09/21/2026 |
| GONZALEZ, EILEEN | COVINA, CA | - | Psychologist | 09/13/2010 |
| GONZALEZ, GABRIELA | ALHAMBRA, CA | - | RBT | 09/25/2026 |
| GONZALEZ, IRENE | FONTANA, CA | - | RBT | 09/22/2026 |
| GONZALEZ, ISABELLE | VAN NUYS, CA | - | RBT | 09/24/2026 |
| GONZALEZ, ISABELLE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GONZALEZ, JACQUELINE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| GONZALEZ, JENNY | HIALEAH GARDENS, FL | RBT-20-125908 | RBT | 08/04/2021 |
| GONZALEZ, JOHN | HOUSTON, TX | - | BCBA | 09/21/2026 |
| GONZALEZ, JONAH | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| GONZALEZ, KIMBERLY | TORRANCE, CA | - | RBT | 09/21/2026 |
| GONZALEZ, KRYSTAL | PEMBROKE PINES, FL | SLPA | Speech-Language Pathologist | 10/18/2021 |
| GONZALEZ, LARISSA | CHULA VISTA, CA | - | RBT | 09/21/2026 |
| GONZALEZ, LAYDEEN | CORAL GABLES, FL | - | RBT | 09/21/2026 |
| GONZALEZ, LISNEISY | HOMESTEAD, FL | - | BCBA | 03/02/2020 |
| GONZALEZ, LIZETH | SAN DIEGO, CA | - | Day Training/Habilitation Specialist | 08/04/2026 |
| GONZALEZ, LOURDES | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GONZALEZ, MERALIS | MIAMI, FL | - | RBT | 06/18/2020 |
| GONZALEZ, NATHAN | DALLAS, TX | LPC | Professional Counselor | 09/23/2026 |
| GONZALEZ, OSCAR | LONGVIEW, WA | MSW, LICSWA | Counselor | 10/26/2020 |
| GONZALEZ, SANTINO | TORRANCE, CA | - | RBT | 09/21/2026 |
| GONZALEZ, SARA | SEATTLE, WA | - | Counselor | 07/02/2024 |
| GONZALEZ, VANESSA | DALTON, GA | - | RBT | 09/22/2026 |
| GONZALEZ, ZACHIRA | FORT MYERS, FL | RCSWI | Mental Health Counselor | 09/19/2024 |
| GOODALL, TRISHA | CHARLOTTESVILLE, VA | - | Mental Health Counselor | 09/22/2026 |
| GOODE, EMMA | SPARTANBURG, SC | - | RBT | 09/24/2026 |
| GOODE, YAZMINE | FORT WORTH, TX | - | RBT | 09/21/2026 |
| GOODENOUGH, RENEA | FOLSOM, CA | - | RBT | 09/09/2026 |
| GOODMAN, JAIMIE | SALEM, VA | LCSW | Clinical Social Worker | 09/23/2026 |
| GOODMAN, RACHEL | CARVER, MA | B.A | Mental Health Counselor | 09/18/2023 |
| GOODRICH, SARA | EUREKA, CA | - | Clinical Social Worker | 09/14/2022 |
| GOODRIDGE, JASMINE | ALBUQUERQUE, NM | - | RBT | 09/21/2026 |
| GOODWIN, JORDAN | GARDEN CITY, MI | - | RBT | 09/25/2026 |
| GOOSSEN, KELLY | MUSKEGON, MI | - | Counselor | 09/21/2026 |
| GORDON, CAITLIN | CHICAGO, IL | - | Counselor | 09/23/2026 |
| GORDON, CHELSEA | COLUMBIA, PA | LPC | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| GORDON, JASON | HEMPSTEAD, NY | - | BCBA | 09/23/2026 |
| GORDON, LAURA | HORSHAM, PA | LPC | Professional Counselor | 02/24/2020 |
| GORDON, LAUREN | MADISON, WI | - | Professional Counselor | 08/19/2022 |
| GORDON, MAR'CHAEL | COVINA, CA | - | RBT | 09/24/2026 |
| GORDON, NICOLE | TOWANDA, PA | LSW | Clinical Social Worker | 12/26/2021 |
| GORE, DEVAN | ANAHUAC, TX | - | Speech-Language Pathologist | 03/30/2022 |
| GORECKI, JESSICA | ERIE, PA | LCSW | Clinical Social Worker | 09/24/2026 |
| GORLICKI, AMANDA | JACKSONVILLE, FL | LCSW | Clinical Social Worker | 11/29/2022 |
| GORNIAK, AMY | SAN ANTONIO, TX | PSYD | Mental Health Counselor | 08/26/2020 |
| GOSCICKI, TERESA | PLYMOUTH, MI | MA, LLP | Psychologist | 09/12/2013 |
| GOSE-STARK, MICHIELE | SALINAS, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| GOSHAY, TYKWA | DENVER, CO | LPCC | Mental Health Counselor | 08/11/2021 |
| GOSSETT, JORDYN | GREENSBORO, NC | - | Speech-Language Pathologist | 08/03/2026 |
| GOSSIP & GROWTH LLCORG | JOBSTOWN, NJ | - | Mental Health Counselor | 09/21/2026 |
| GOT, PIERRE | PARSIPPANY, NJ | MA, LAC, NCC | Counselor | 09/09/2026 |
| GOUBADIA, MICHAEL | UNION, NJ | - | BCBA | 09/21/2026 |
| GOUGE, PHILLIP | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| GOULD, STEPHANIE | CARMEL, NY | - | Addiction (Substance Use Disorder) Counselor | 02/16/2023 |
| GOVAN, SANDY | SOUTHFIELD, MI | - | RBT | 09/21/2026 |
| GOWDA, VASANTHI | THE WOODLANDS, TX | - | RBT | 09/21/2026 |
| GRACE BEHAVIORAL HEALTH LLCORG | FORT MILL, SC | - | Community/Behavioral Health Agency | 09/21/2026 |
| GRACE CHAPEL CHRISTIAN CHURCHORG | SANFORD, NC | - | Speech-Language Pathologist | 09/25/2026 |
| GRACEFUL CARE SERVICES, LLCORG | NORTH BRUNSWICK, NJ | - | Community/Behavioral Health Agency | 09/07/2026 |
| GRACEFUL HERON THERAPY LLCORG | COLUMBUS, OH | - | Clinical Social Worker | 09/21/2026 |
| GRAF, BENJAMIN | COLORADO SPRINGS, CO | MA | Mental Health Counselor | 09/09/2021 |
| GRAFELMAN, ANNA | ELKHORN, NE | - | Mental Health Counselor | 09/21/2026 |
| GRAFT AND BLOSSOM THERAPY - A LICENSED CLINICAL SOCIAL WORKER CORPORATIONORG | HOLLISTER, CA | - | Mental Health Counselor | 07/15/2026 |
| GRAFT, ERIN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GRAHAM, AMBER | CHICAGO, IL | LPC | Professional Counselor | 02/12/2026 |
| GRAHAM, CODY | IRVINE, CA | - | RBT | 09/21/2026 |
| GRAHAM, JENA | CHARLESTON, WV | - | Case Manager/Care Coordinator | 09/22/2026 |
| GRAHAM, PAIGE | CRANFORD, NJ | - | Speech-Language Pathologist | 09/21/2026 |
| GRANADOS-SCHRADER, TANIA | HENDERSON, NV | - | Assistant Behavior Analyst | 09/22/2026 |
| GRANADOS, JILLSBURY | SACRAMENTO, CA | - | BCBA | 05/18/2018 |
| GRANDA, JACQUELYN | LOS ALAMITOS, CA | AA | RBT | 09/22/2026 |
| GRANDBERRY, SHERRIKA | JACKSON, TN | - | Professional Counselor | 09/26/2026 |
| GRANILLO, JULIANA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| GRANT, RIECELLE | BRONX, NY | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| GRANT, VENICE | SAN ANTONIO, TX | PSYD | Psychologist | 06/09/2021 |
| GRANVILLE, ASHLEY | TOPEKA, KS | - | Clinical Social Worker | 07/25/2016 |
| GRAVEEN, CASSIE | WAUSAU, WI | LPC, ATR | Professional Counselor | 10/19/2017 |
| GRAVERT, MAGNOLIA | WACO, TX | BCBA | BCBA | 09/17/2026 |
| GRAVES, ALISON | SAINT JOSEPH, MI | - | Speech-Language Pathologist | 09/21/2026 |
| GRAVES, NORA | ELIZABETHTOWN, NY | - | Mental Health Counselor | 09/22/2026 |
| GRAY-CAINE, JAMERA | LEANDER, TX | - | RBT | 09/21/2026 |
| GRAY, ALEXIS | SHREVEPORT, LA | MS, PLPC, NCC | Mental Health Counselor | 09/21/2026 |
| GRAY, ASHA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| GRAY, ASHLEY | FEDERALSBURG, MD | LPCMH | Professional Counselor | 02/03/2022 |
| GRAY, COZY | RIDGELAND, MS | LPC, M.ED, NCC | Mental Health Counselor | 09/05/2022 |
| GRAY, DONALD | FRIENDSWOOD, TX | LMFTA | Mental Health Counselor | 06/28/2018 |
| GRAY, ELIZABETH | REYNOLDSBURG, OH | LISW | Clinical Social Worker | 06/07/2021 |
| GRAY, SYDNEY | LONDON, KY | - | Speech-Language Pathologist | 09/23/2026 |
| GRAZIANO, BRADY | DURHAM, NC | - | RBT | 09/22/2026 |
| GREATER PURPOSE LIVINGORG | GREENSBORO, NC | - | Community/Behavioral Health Agency | 09/24/2026 |
| GREAUX, LUCRETIA | KNIGHTDALE, NC | LCSW | Clinical Social Worker | 11/14/2013 |
| GRECO, ALEXA | OLD GREENWICH, CT | - | Mental Health Counselor | 10/02/2023 |
| GREEAR, RACHEL | AURORA, CO | LPC | Professional Counselor | 09/04/2026 |
| GREEN FEATHER THERAPYORG | SAINT LEONARD, MD | - | Clinical Social Worker | 09/25/2026 |
| GREEN LEAF ABA THERAPY LLCORG | PARSIPPANY, NJ | - | BCBA | 09/18/2026 |
| GREEN, ANGELA | TOLEDO, OH | LSW | Case Manager/Care Coordinator | 08/05/2019 |
| GREEN, ANNA | MUSKOGEE, OK | - | Case Manager/Care Coordinator | 09/26/2026 |
| GREEN, AR'REIONA | SAN DIEGO, CA | - | RBT | 09/25/2026 |
| GREEN, ASLI | HAMPTON, VA | - | RBT | 09/24/2026 |
| GREEN, DE LISA | MAMARONECK, NY | - | RBT | 02/28/2018 |
| GREEN, GAVIN | AUBURN, WA | - | Mental Health Counselor | 08/12/2025 |
| GREEN, KERRI | ALBUQUERQUE, NM | LMFT | Counselor | 09/26/2013 |
| GREEN, LEILA | DANVILLE, VA | - | Addiction (Substance Use Disorder) Counselor | 05/27/2025 |
| GREEN, LISA | BALTIMORE, MD | LGSW | Clinical Social Worker | 03/02/2012 |
| GREEN, RACHEL | STANFORD, CA | - | Mental Health Counselor | 05/17/2024 |
| GREEN, RANASIA | ROANOKE, VA | - | Addiction (Substance Use Disorder) Counselor | 08/12/2024 |
| GREEN, REBECCA | TEMECULA, CA | - | RBT | 09/22/2026 |
| GREEN, SHAUNTAE | CLEVELAND, OH | - | Case Manager/Care Coordinator | 08/21/2025 |
| GREENE, LINISE | SPARTANBURG, SC | - | Speech-Language Pathologist | 09/24/2026 |
| GREENICH, SHAINNA | ATHENS, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| GREENMAN, LORI | PARK RIDGE, IL | - | Professional Counselor | 05/23/2016 |
| GREENVILLE BILINGUAL THERAPYORG | GREENVILLE, SC | - | Speech-Language Pathologist | 06/20/2014 |
| GREENWOOD, CASSANDRA | FITCHBURG, MA | - | Mental Health Counselor | 09/22/2022 |
| GREESON, ISABELLE | MODESTO, CA | - | RBT | 09/25/2026 |
| GREGOIRE, JENNA | MCKINNEY, TX | - | RBT | 09/21/2026 |
| GREGORY, ALEXANDREA | BOYNTON BEACH, FL | - | RBT | 03/08/2020 |
| GREGORY, TIANNA | CONCORD, NC | LCAS | Addiction (Substance Use Disorder) Counselor | 03/22/2012 |
| GREMILLION, HALEY | HAMILTON, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| GRENNAN, PAUL | MOUNT VERNON, NY | - | Mental Health Counselor | 07/20/2020 |
| GRESETH, LEVI | JAMESTOWN, ND | - | Addiction (Substance Use Disorder) Counselor | 11/01/2024 |
| GRESETH, TERESA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| GRETTENBERGER, MARY | IRA, MI | - | Clinical Social Worker | 08/25/2020 |
| GREY, SOFIA | SEATTLE, WA | - | Mental Health Counselor | 09/22/2026 |
| GRIEBNO, ALLYCIA | ANDERSON, SC | - | Professional Counselor | 11/16/2023 |
| GRIFFEE, TRACY | CASPER, WY | - | Case Manager/Care Coordinator | 10/26/2009 |
| GRIFFIN, HEATHER | TULLAHOMA, TN | - | Mental Health Counselor | 08/11/2026 |
| GRIFFIN, LAURA KAY | GARDEN RIDGE, TX | LPC | Professional Counselor | 10/06/2023 |
| GRIFFIN, MARIA | FRESNO, CA | - | Mental Health Counselor | 04/01/2024 |
| GRIFFIN, MELVIN | LOCKPORT, NY | - | RBT | 09/21/2026 |
| GRIFFITH, JENNIFER | SAN CLEMENTE, CA | LCSW | Clinical Social Worker | 12/13/2023 |
| GRIFFITH, MEGHAN | NILES, OH | - | Mental Health Counselor | 08/17/2026 |
| GRILLO, MAYARA | MIAMI, FL | - | RBT | 04/26/2024 |
| GRIM, KATHERINE | AURORA, CO | LPC, LAC | Professional Counselor | 01/24/2024 |
| GRIMALDI, JENNA | RAMSEY, NJ | LPC | Professional Counselor | 12/23/2019 |
| GRIMES, JOSHUA | OREGON, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| GRIMES, MELITA | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 03/23/2021 |
| GRINNELL, ELLISON | BENTONVILLE, AR | - | RBT | 09/22/2026 |
| GRIPENTROG, JUSTIN | BAY CITY, MI | CCC-SLP | Speech-Language Pathologist | 04/19/2019 |
| GRISHKEVICH, NICOL | CHESTERFIELD, MI | MA, LPC | Counselor | 07/10/2019 |
| GROH, LINDSAY | KANSAS CITY, MO | MS | Psychologist | 08/01/2024 |
| GROHOWSKY, CHRISTY | RIVERSIDE, CA | BEHAVIOR TECH | RBT | 09/24/2026 |
| GRONOW GUTIERREZ, KAREN | HERNDON, VA | - | RBT | 02/28/2025 |
| GROS, ASHLEY | GARDENA, CA | - | RBT | 09/25/2026 |
| GROSE, JESSICA | SAN MARCOS, CA | M.S., CCC-SLP | Speech-Language Pathologist | 03/01/2019 |
| GROSHONG, KRISTINA | MAPLE VALLEY, WA | - | BCBA | 05/03/2021 |
| GROSS, RACHEL | RED BLUFF, CA | ASW | Mental Health Counselor | 06/04/2024 |
| GROSS, SALENA | SOUTHFIELD, MI | - | Professional Counselor | 09/13/2019 |
| GROSS, TERESA | PALM BAY, FL | - | RBT | 09/21/2026 |
| GROVE THERAPEUTIC SERVICES LLCORG | CINCINNATI, OH | - | Clinical Social Worker | 09/25/2026 |
| GROVER, GABRIELLA | GREENWOOD VILLAGE, CO | - | Mental Health Counselor | 09/04/2023 |
| GROW COUNSELING AND CONSULTANTORG | KNIGHTDALE, NC | - | Clinical Social Worker | 12/15/2025 |
| GROW TOGETHER THERAPY, PLLCORG | DEARBORN, MI | - | Mental Health Counselor | 04/24/2026 |
| GROWING TOGETHER THERAPY LLCORG | MACOMB, MI | - | Mental Health Counselor | 03/04/2026 |
| GRUBBS, JENNIFER | SOUTH BEND, IN | LCSW | Clinical Social Worker | 11/11/2021 |
| GRUBER, CHARIS | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| GRUBER, KELLY | GLENDALE, AZ | LCSW | Clinical Social Worker | 09/23/2026 |
| GRUBY, EMMA | LYNNWOOD, WA | - | RBT | 09/23/2026 |
| GRUGIN, KATHERINE | LEXINGTON, KY | - | Clinical Social Worker | 08/15/2023 |
| GRULLON, ARIANNEY | BROOKLYN, NY | - | BCBA | 09/21/2026 |
| GRUZLEWSKI, MORGAN | HICKORY HILLS, IL | - | RBT | 09/22/2026 |
| GUANCHE ADAY, DAIDY | MIAMI, FL | - | RBT | 09/22/2026 |
| GUARDDON-LEDBETTER, ISABELLA | NORMAN, OK | - | RBT | 06/12/2023 |
| GUARDIPEE, KIM | VANCOUVER, WA | - | Speech-Language Pathologist | 09/23/2026 |
| GUASSO, JOSE | ATASCADERO, CA | - | Addiction (Substance Use Disorder) Counselor | 09/08/2026 |
| GUBERMAN, JACOB | FORT LAUDERDALE, FL | - | RBT | 09/23/2026 |
| GUCIARDO, AVA | SAINT CLAIR SHORES, MI | - | RBT | 09/23/2026 |
| GUDIEL-JOSHI, ELMER | FREDERICKSBURG, VA | VA LICENSE | Speech-Language Pathologist | 10/03/2022 |
| GUDINO, MONICA | HOUSTON, TX | - | RBT | 09/25/2026 |
| GUERRA QUINTANILLA, AMBER | SAN DIEGO, CA | - | RBT | 09/25/2026 |
| GUERRA, ALEXANDRA | MIAMI, FL | CF-SLP | Speech-Language Pathologist | 09/18/2026 |
| GUERRA, ANDREA | TRACY, CA | - | RBT | 09/24/2026 |
| GUERRA, ASHLEE | EDINBURG, TX | LPC | Professional Counselor | 09/22/2026 |
| GUERRA, BRIANNA | LOS ANGELES, CA | - | RBT | 09/22/2026 |
| GUERRERO RODRIGUEZ, SOLANGE | IDAHO FALLS, ID | BA | Case Manager/Care Coordinator | 09/23/2026 |
| GUERRERO URRUTIA, SARA | SAN FRANCISCO, CA | - | Professional Counselor | 09/26/2026 |
| GUERRERO VALENTIN, RAIZZA | CARLSBAD, CA | - | RBT | 09/22/2026 |
| GUERRERO, ADRIANA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| GUERRERO, JENNIFER | HOUSTON, TX | M.S. CCC-SLP | Speech-Language Pathologist | 02/11/2022 |
| GUERRERO, KIMBERLY | THE COLONY, TX | - | RBT | 09/22/2026 |
| GUERRERO, LETICIA | SAN JOSE, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| GUESS-LEPCZYK, SUSAN | NEW LONDON, CT | MA, CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| GUEVARA CEJA, INGRID | LONG BEACH, CA | - | RBT | 09/21/2026 |
| GUEVARA VERA, FRANCIA | SAN ANTONIO, TX | - | RBT | 09/25/2026 |
| GUEVARA, DARYNNE FRANCESCA | SHERWOOD, OR | - | Case Manager/Care Coordinator | 09/24/2026 |
| GUEVARA, HAILEY | CONCORD, CA | - | RBT | 09/22/2026 |
| GUEVARRA, KELLY | ORANGE, CA | - | RBT | 09/21/2026 |
| GUFFEY, ADDISON | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| GUHL, RACHEL | MENTOR, OH | LISW | Clinical Social Worker | 07/26/2022 |
| GUIDANCE IN LIFEORG | PHOENIX, AZ | - | Professional Counselor | 09/23/2026 |
| GUIDESTONE COUNSELING AND WELLNESSORG | LAS CRUCES, NM | - | Clinical Social Worker | 09/21/2026 |
| GUIDING LIGHT BEHAVIOR SERVICES LLCORG | CONCORD, CA | - | RBT | 09/25/2026 |
| GUIDING LIGHT BEHAVIORAL HEALTH CARE SERVICES LLCORG | MONTGOMERY, AL | - | Clinical Social Worker | 09/22/2026 |
| GUIDO, JULIE | GLEN MILLS, PA | MSW, LCSW | Clinical Social Worker | 01/14/2015 |
| GUIDRY, RAE | LAFAYETTE, LA | MS, PLPC | Professional Counselor | 09/22/2026 |
| GUIGLIANO, MEGAN | NAPLES, FL | BCBA | BCBA | 01/31/2022 |
| GUJARATHI, RHEA | HAYWARD, CA | - | RBT | 09/22/2026 |
| GULLATTE, MICHAEL | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| GULLETT, KAEYLA | MIDLAND, MI | - | Counselor | 07/02/2021 |
| GULLETT, PALLIE | LOUISVILLE, KY | - | BCBA | 12/30/2021 |
| GULLO, SKYLYN | HERRIN, IL | - | RBT | 09/24/2026 |
| GUNDERSON, CHRISTOPHER | ANCHORAGE, AK | RN, LPC, NCC | Professional Counselor | 06/10/2020 |
| GUNNELS, DARA | ALAMOSA, CO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| GURGIOLO, NICOLE | ASHEVILLE, NC | - | Clinical Social Worker | 03/09/2026 |
| GURNEY, CLAIRE | SHERMAN, TX | M.S.,CCC-SLP | Speech-Language Pathologist | 04/23/2024 |
| GUSSY ELVIK, PLLCORG | NORMAN, OK | - | Professional Counselor | 08/18/2026 |
| GUSZAK-AWAD, JESSICA | OMAHA, NE | LIMHP | Mental Health Counselor | 09/04/2018 |
| GUTHRIE, MIRANDA | PORT ORANGE, FL | RBT | RBT | 09/24/2026 |
| GUTHRIE, STACEY | HACKETTSTOWN, NJ | - | RBT | 09/24/2026 |
| GUTIERREZ ESPARZA, GISELL | CONCORD, CA | - | RBT | 09/22/2026 |
| GUTIERREZ GARCIA, YULEIVY | LEHIGH ACRES, FL | RBT-24-361652 | RBT | 07/15/2024 |
| GUTIERREZ ORTEGA, STEPHANIE | LONG BEACH, CA | ED.S., PPS | RBT | 04/17/2021 |
| GUTIERREZ, ABIGAIL | FRESNO, CA | - | RBT | 09/25/2026 |
| GUTIERREZ, ARLENE | OXNARD, CA | - | Day Training/Habilitation Specialist | 09/16/2021 |
| GUTIERREZ, DAKOTA | SANTA BARBARA, CA | - | RBT | 07/22/2026 |
| GUTIERREZ, DALILAH | SAN BERNARDINO, CA | - | RBT | 09/23/2026 |
| GUTIERREZ, JOHN | SAN JOSE, CA | - | RBT | 09/24/2026 |
| GUTIERREZ, NADIA | LOS BANOS, CA | - | RBT | 04/11/2025 |
| GUTIERREZ, NATALIA | LOS ANGELES, CA | - | RBT | 09/25/2026 |
| GUTIERREZ, RENEE | IRVINE, CA | - | Counselor | 11/27/2015 |
| GUTOWSKI, ANNA | DALY CITY, CA | - | RBT | 09/25/2026 |
| GUY, KAMIYHA | GLENDALE, AZ | - | RBT | 09/21/2026 |
| GUY, TRAVIS | RICHMOND, IL | - | Mental Health Counselor | 09/14/2026 |
| GUZIK, ROBYN | GONZALES, CA | ASW | Clinical Social Worker | 09/21/2026 |
| GUZMAN VIGIL, NATALIE | SACRAMENTO, CA | - | Speech-Language Pathologist | 09/22/2026 |
| GUZMAN, FRANCISCO | MERCED, CA | ACSW | Clinical Social Worker | 03/02/2009 |
| GUZMAN, GABRIELLA | WEST PALM BEACH, FL | MS | Case Manager/Care Coordinator | 07/16/2021 |
| GUZMAN, GILBERT | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| GWAABE, GODLOVE | OKLAHOMA CITY, OK | BA | Counselor | 12/15/2016 |
| GWIZDALSKI, JEREMY | MESA, AZ | - | Professional Counselor | 09/21/2021 |
| GYAN, PATRICK | FAIRFAX, VA | - | RBT | 06/16/2025 |
| GYUK, SOPHIA | SEATTLE, WA | - | RBT | 09/25/2026 |
| HA, ALYSSA | BATON ROUGE, LA | - | Mental Health Counselor | 09/08/2026 |
| HA, KELLY | WOODBRIDGE, VA | LPC, CSOTP | Mental Health Counselor | 07/12/2022 |
| HA, KITTY | SAN FRANCISCO, CA | - | Specialist | 03/02/2009 |
| HA, SOSUN | TWENTYNINE PALMS, CA | - | Professional Counselor | 12/18/2023 |
| HAAG, KAREN | SALEM, OR | MA, LPC | Professional Counselor | 07/16/2013 |
| HAARSTAD-MEAD, ADALYAH | MINNEAPOLIS, MN | - | Clinical Social Worker | 08/10/2022 |
| HAAS, ASIALAKAY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| HACHE, DAISY | MOUNT DORA, FL | BT | RBT | 08/31/2026 |
| HACK, ANSLEY | MOUNT PLEASANT, SC | - | Clinical Social Worker | 10/17/2019 |
| HADDIX, GABRIELLE | TRAVERSE CITY, MI | - | Clinical Social Worker | 09/22/2026 |
| HAFNER, CAROLINE | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| HAGAN, ROSS | BIRMINGHAM, AL | - | RBT | 09/22/2026 |
| HAGANS, LAUREN | ARLINGTON, TX | LPC ASSOCIATE | Professional Counselor | 01/29/2026 |
| HAGGINS, AMIYA | FORT MILL, SC | RBT | RBT | 09/22/2026 |
| HAHN, PATRICK | BROOKLYN, NY | LCSW | Clinical Social Worker | 12/18/2017 |
| HAHNKE, JULIE | MAPLEWOOD, MN | LICSW | Clinical Social Worker | 09/21/2026 |
| HAIDER, KINZA | PEMBROKE PINES, FL | RBT | BCBA | 11/29/2022 |
| HAINES, HALEY | BUSHNELL, FL | BCBA | BCBA | 08/15/2018 |
| HAIRSTON, KAYLA | GREENSBORO, NC | - | Clinical Social Worker | 10/24/2021 |
| HAJI, MASITI | BELLINGHAM, WA | - | RBT | 09/21/2026 |
| HAKIM, ARSIYA | PLANO, TX | - | BCBA | 05/16/2025 |
| HAKOBYAN, ELEN | BURBANK, CA | - | RBT | 09/23/2026 |
| HALAUFIA, ELIZABETH | SAN JOSE, CA | - | Day Training/Habilitation Specialist | 09/15/2026 |
| HALE, ANNA | CARIBOU, ME | LCSW | Clinical Social Worker | 11/29/2007 |
| HALE, JAYCEE | AUSTIN, TX | BCBA | BCBA | 09/22/2026 |
| HALE, KALLI | SAN ANGELO, TX | - | RBT | 09/22/2026 |
| HALES, IKRAM | HARTFORD, CT | - | Mental Health Counselor | 09/26/2026 |
| HALFON, DANIEL | VALLEY STREAM, NY | - | Case Manager/Care Coordinator | 09/24/2026 |
| HALIM, GEHAN | SAN DIEGO, CA | LCSW | Clinical Social Worker | 08/27/2013 |
| HALL HEALTH COUNSELINGORG | HATTIESBURG, MS | - | Mental Health Counselor | 09/17/2026 |
| HALL-TAYLOR, KLARISSA | BRANDON, FL | - | RBT | 09/22/2026 |
| HALL, ANTHONY | RIVERBANK, CA | - | RBT | 09/21/2026 |
| HALL, ASHLYN | ORANGE, VA | LCSW | Clinical Social Worker | 09/21/2026 |
| HALL, BECKY | HARRISON TWP, MI | LMSW | Clinical Social Worker | 09/28/2012 |
| HALL, DJAEDA | NEWPORT BEACH, CA | - | RBT | 09/26/2026 |
| HALL, HAYLEY | MEDFORD, OR | LPC | Professional Counselor | 02/05/2019 |
| HALL, JEANINE | RALEIGH, NC | - | RBT | 07/08/2026 |
| HALL, JESSICA | MIDWEST CITY, OK | - | RBT | 05/25/2026 |
| HALL, NATALIE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| HALL, RACHAEL | ROCHESTER, NY | - | Mental Health Counselor | 09/11/2026 |
| HALL, TAMARA | CABIN CREEK, WV | THERAPIST | Counselor | 08/24/2020 |
| HALL, TANISHA | SOUTHFIELD, MI | - | RBT | 09/23/2026 |
| HALL, TYLER | FRISCO, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/24/2026 |
| HALL, WHITNEY | LEBANON, VA | M.S., CCC-SLP | Speech-Language Pathologist | 02/05/2016 |
| HALL, ZACHARY | SAVANNAH, GA | - | RBT | 09/22/2026 |
| HALLECK, MICHAEL | JACKSON, MI | LPC | Mental Health Counselor | 02/20/2023 |
| HALLETT, LIANNA | JAMAICA, NY | - | Mental Health Counselor | 09/24/2026 |
| HALM, MICHELLE | CHICAGO, IL | LCPC | Mental Health Counselor | 09/21/2026 |
| HALVERSON, GRACE | SEATTLE, WA | - | Counselor | 09/25/2026 |
| HALVERSON, STACEY | GILBERT, AZ | PH D | Psychologist | 01/22/2018 |
| HAMBLEN, RACQUEL | OAKLAND, CA | - | RBT | 06/09/2021 |
| HAMILTON-MOBLEY, EDGWINA | NASHVILLE, TN | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| HAMILTON, BROOKE | NILES, OH | - | Case Manager/Care Coordinator | 07/07/2022 |
| HAMILTON, BROOKE | CHESTERFIELD, MI | - | RBT | 09/25/2026 |
| HAMILTON, SETH | ANCHORAGE, AK | - | RBT | 01/21/2025 |
| HAMILTON, TAMATHA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/26/2026 |
| HAMLANI, SONIA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| HAMLETT, LE'COREYAN | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| HAMM, CHLOE | HERRIN, IL | - | RBT | 09/24/2026 |
| HAMM, LAUREN | MANHATTAN, KS | LPC | Professional Counselor | 07/22/2026 |
| HAMMERICH, ASHLEY | FAYETTEVILLE, NY | LMHC | Mental Health Counselor | 09/21/2026 |
| HAMMOND, SAVYON | INDIANAPOLIS, IN | - | RBT | 09/23/2026 |
| HAMPSON, KYRA | PORTLAND, OR | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| HAMPTON, MAHLIA | BREA, CA | - | RBT | 09/21/2026 |
| HAMRICK, CORY | CHEBOYGAN, MI | - | RBT | 09/24/2026 |
| HAMYICHUDIM INC.ORG | LAKEWOOD, NJ | - | BCBA | 09/25/2026 |
| HAMZA, FARIDA | LITTLE ROCK, AR | - | Professional Counselor | 08/21/2026 |
| HANCOCK, JENNIFER | COEUR D ALENE, ID | LCSW | Clinical Social Worker | 09/05/2023 |
| HANCOCK, LISA | KATY, TX | LPC | Professional Counselor | 06/18/2020 |
| HANCOCK, WILLIAM | WESTWOOD, NJ | LSW | Clinical Social Worker | 02/13/2018 |
| HAND & ORTHOPEDIC REHABILITATION SPECIALISTSORG | DRAPER, UT | - | Specialist | 03/10/2011 |
| HAND, TAYLOR | BLOOMINGTON, IN | LPCC | Counselor | 02/18/2019 |
| HANDSMAN, NICOLE | ASHEVILLE, NC | LCSW | Clinical Social Worker | 02/13/2017 |
| HANIK, MARTHA | NORMAN, OK | LPC-C | Mental Health Counselor | 09/24/2026 |
| HANJIEV, ETHAN | OWASSO, OK | - | RBT | 09/22/2026 |
| HANKS, KAYLA | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| HANNAH, CODY | ELKINS, WV | BA,BS | Case Manager/Care Coordinator | 09/22/2026 |
| HANNAH, KYERA | HEMET, CA | - | RBT | 11/26/2024 |
| HANNIGAN MORRISON, CHRISTINE | HARVARD, MA | L.I.C.S.W. | Clinical Social Worker | 01/26/2007 |
| HANOPOLE, KAYLEE | NEW YORK, NY | - | Mental Health Counselor | 09/21/2026 |
| HANSEN, ARIANA | RIVERBANK, CA | - | RBT | 09/21/2026 |
| HANSEN, ASHLEIGH | SURPRISE, AZ | - | Counselor | 09/23/2026 |
| HANSEN, JOELLE | HAYWARD, CA | - | RBT | 09/25/2026 |
| HANSEN, KAYLENE | PORT ANGELES, WA | CO61536110 | Counselor | 04/04/2024 |
| HANSEN, RENAE | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| HANSEN, RILEY | AMES, IA | - | Mental Health Counselor | 09/23/2026 |
| HANSON, ELIZABETH | BONITA SPRINGS, FL | - | Clinical Social Worker | 02/04/2019 |
| HANSON, ETHAN | WEST JORDAN, UT | - | RBT | 09/23/2026 |
| HANSTEIN, JOSHUA | PORT ORANGE, FL | - | RBT | 05/17/2021 |
| HAPPYBURY LLCORG | SACRAMENTO, CA | - | BCBA | 09/23/2026 |
| HARARI, RENATA | NORTH MIAMI BEACH, FL | - | RBT | 09/22/2026 |
| HARAZIN, PAIGE | MELBOURNE, FL | MS, BCBA | BCBA | 11/07/2023 |
| HARBINSON, RACHEL | FARMINGTON HILLS, MI | - | RBT | 12/18/2024 |
| HARBISON, CARL | POPLAR BLUFF, MO | - | Mental Health Counselor | 10/05/2018 |
| HARDBEAUTY FOUNDATIONORG | CASTLE ROCK, CO | - | Community/Behavioral Health Agency | 07/20/2026 |
| HARDBEAUTY FOUNDATIONORG | GLENWOOD SPRINGS, CO | - | Community/Behavioral Health Agency | 09/24/2026 |
| HARDEN, SHERRON | BROOKLYN, NY | - | RBT | 09/24/2026 |
| HARDING, BRANDI | CATONSVILLE, MD | LCSW-C | Clinical Social Worker | 02/22/2021 |
| HARDING, CARRIE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| HARDING, ESTHER | NEW YORK, NY | LCSW ACSW CASAC | Clinical Social Worker | 12/07/2007 |
| HARDING, JAYNA | EUGENE, OR | - | Counselor | 09/22/2026 |
| HARDMAN, BRITTNEY | GREENVILLE, MI | - | RBT | 09/21/2026 |
| HARGETT, KISA | GARNER, NC | - | RBT | 09/21/2026 |
| HARKER, KIMBERLY | DENVER, CO | MS, LPC, LAC | Professional Counselor | 01/17/2022 |
| HARLAN, BRYNNE | ALAMOGORDO, NM | - | RBT | 09/26/2026 |
| HARLAN, EMMA | CATOOSA, OK | - | Case Manager/Care Coordinator | 09/24/2026 |
| HARLAND, ELIZABETH | LUDLOW, MA | - | BCBA | 04/10/2018 |
| HARMAN, MIKAYLA | FORT MYERS, FL | RBT | RBT | 11/14/2022 |
| HARMON, KAYVRYELLE | OKLAHOMA CITY, OK | B.A., A.A | Mental Health Counselor | 09/13/2011 |
| HARMON, KELLY | HATTIESBURG, MS | LMSW | Clinical Social Worker | 03/16/2010 |
| HARMON, MALORIE | CLARE, MI | - | RBT | 09/25/2020 |
| HARMON, MICHELE | IDAHO FALLS, ID | LCSW | Clinical Social Worker | 05/31/2022 |
| HARMONIOUS MINDS COUNSELING PLLCORG | CHAMPAIGN, IL | - | Professional Counselor | 09/01/2026 |
| HARMONY ALLIANCE LLCORG | GLENDALE, AZ | - | Community/Behavioral Health Agency | 03/23/2022 |
| HARNESSING STRENGTH A LICENSED CLINICAL SOCIAL WORKER CORPORATIONORG | CARLSBAD, CA | - | Clinical Social Worker | 04/20/2023 |
| HARNEY, CHEYENNE | MEDFORD, OR | - | Mental Health Counselor | 09/21/2026 |
| HARO, SUMAYA | STILLWATER, MN | - | RBT | 09/21/2026 |
| HARP, KELLY | WACO, TX | - | Professional Counselor | 09/23/2026 |
| HARPER, CANDANCE | CHARLESTON, SC | LMSW | Clinical Social Worker | 08/04/2022 |
| HARPER, MOLLY | LAS VEGAS, NV | - | RBT | 09/21/2026 |
| HARRINGTON, JEFFREY | SANTEE, CA | - | Addiction (Substance Use Disorder) Counselor | 11/16/2021 |
| HARRIS-JANK, AMANDA | GREEN BAY, WI | MS | Speech-Language Pathologist | 09/24/2026 |
| HARRIS, AMBER | INDIANAPOLIS, IN | - | RBT | 04/20/2020 |
| HARRIS, ASHLEY | BATON ROUGE, LA | - | RBT | 09/24/2026 |
| HARRIS, BRANDI | HOUMA, LA | - | Case Manager/Care Coordinator | 09/24/2026 |
| HARRIS, CAROLINA | WESTMINSTER, CA | - | Clinical Social Worker | 03/07/2016 |
| HARRIS, IBARRA | FORT COLLINS, CO | - | Mental Health Counselor | 09/25/2026 |
| HARRIS, INEZ | MENTOR, OH | - | Community/Behavioral Health Agency | 09/25/2026 |
| HARRIS, JAYDA | PITTSBURGH, PA | - | RBT | 09/23/2026 |
| HARRIS, JENNIFER | CORNELIUS, NC | LCSW-A, LCAS, CADC | Clinical Social Worker | 10/03/2024 |
| HARRIS, JILLIAN | LUFKIN, TX | - | BCBA | 09/22/2026 |
| HARRIS, JUSTIN | KISSIMMEE, FL | - | Mental Health Counselor | 09/24/2026 |
| HARRIS, KAITLIN | SANTA MARIA, CA | - | Day Training/Habilitation Specialist | 04/15/2024 |
| HARRIS, KIYESHA | OKEMOS, MI | - | RBT | 09/23/2026 |
| HARRIS, LEAIJA | NORTH PORT, FL | - | RBT | 09/23/2026 |
| HARRIS, MADELYN | VESTAVIA HILLS, AL | - | Speech-Language Pathologist | 09/23/2026 |
| HARRIS, MARKEISHA | HOUSTON, TX | - | Case Manager/Care Coordinator | 11/13/2016 |
| HARRIS, MONIQUE | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| HARRIS, RACHEL | SEATTLE, WA | LMHC | Mental Health Counselor | 07/07/2021 |
| HARRIS, TESSA | FARMINGTON, MN | - | Addiction (Substance Use Disorder) Counselor | 03/28/2026 |
| HARRISON, CAMELE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| HARRISON, CONNOR | BLUE ASH, OH | LPC | Counselor | 06/03/2024 |
| HARRISON, JENNIFER | MATHER, CA | MPH, LCSW | Clinical Social Worker | 08/27/2013 |
| HARRISON, MATTHEW | TORRANCE, CA | - | RBT | 09/25/2026 |
| HARRISON, MATTIE | GIG HARBOR, WA | LMFT | Mental Health Counselor | 10/11/2018 |
| HARRISON, SANDRA | LECANTO, FL | L.C.S.W | Clinical Social Worker | 09/26/2006 |
| HARRISON, SPRING | MORENO VALLEY, CA | - | BCBA | 08/19/2019 |
| HARRIZON, ELENA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| HARROD, AMAYA | GREENVILLE, SC | - | RBT | 09/21/2026 |
| HARRY, KERRYANN | STAFFORD, TX | - | Assistant Behavior Analyst | 08/02/2020 |
| HARRY, LISETTE | PALM CITY, FL | - | Case Manager/Care Coordinator | 12/11/2020 |
| HARSHEY, CAMERYN | FARMINGTON HILLS, MI | - | RBT | 03/30/2026 |
| HART ALDERMAN, TI'JAY | BALTIMORE, MD | - | RBT | 09/22/2026 |
| HART-BURHOOP, TARA | OMAHA, NE | PH.D., LP | Psychologist | 06/02/2015 |
| HART, DANIELLE | WASHINGTON COURT HOUSE, OH | LSW | Counselor | 09/23/2014 |
| HART, KENDRA | CONCORD, NH | - | Specialist | 09/21/2026 |
| HART, MYESIAMSHELLE | HOUSTON, TX | - | RBT | 09/21/2026 |
| HART, SUSAN | APPLE VALLEY, MN | - | Speech-Language Pathologist | 09/23/2026 |
| HARTDIGE, TATIANA | SYLMAR, CA | - | Day Training/Habilitation Specialist | 02/02/2026 |
| HARTER, MICHELLE | ALEXANDRIA, VA | LPC | Professional Counselor | 07/07/2020 |
| HARTLE, HAILEY | GAINESVILLE, FL | - | Assistant Behavior Analyst | 10/25/2023 |
| HARTLE, RACHAEL | MARSHFIELD, WI | - | Counselor | 07/09/2026 |
| HARTMAN, CASEY | FREMONT, CA | - | RBT | 09/22/2026 |
| HARTMAN, OLIVER | HOLLADAY, UT | - | Clinical Social Worker | 09/21/2026 |
| HARTMAN, SARA | HOOVER, AL | ALC, CRC | Mental Health Counselor | 10/08/2024 |
| HARTMANN, ALYSSA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| HARTWICK, JENNIFER | EAST TAWAS, MI | - | RBT | 11/19/2025 |
| HARTZ, TRINITY | DAYTON, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| HARVEY, ALEX | CLARKSTON, MI | MA, BCBA, LBA | BCBA | 05/03/2022 |
| HARVEY, CATHERINE | CHARLESTON, SC | - | BCBA | 09/24/2026 |
| HARVEY, LYDIA | KNOXVILLE, TN | - | RBT | 09/23/2026 |
| HARVI TECHNOLOGIES INCORG | NEW YORK, NY | - | BCBA | 12/02/2024 |
| HARWARD, TEFANY | IDAHO FALLS, ID | BA | Case Manager/Care Coordinator | 09/23/2026 |
| HASBERRY, AMYIA | RIDGELAND, MS | - | RBT | 09/23/2026 |
| HASHEMI, HOMAYOUN | FAIRFAX, VA | M.D. | Specialist | 03/16/2006 |
| HASKINS, CHLOE | COMSTOCK PARK, MI | - | Speech-Language Pathologist | 09/22/2026 |
| HASKVITZ, LEAH | HERNDON, VA | CRNA | Specialist | 07/07/2005 |
| HASSEVOORT, BRANDON | BYRON CENTER, MI | LMSW | Clinical Social Worker | 08/14/2025 |
| HASSLER, HOLLY | STATESVILLE, NC | MA CCC-SLP | Speech-Language Pathologist | 09/15/2026 |
| HASTINGS, TESSA | HUDSON, FL | LPC | Mental Health Counselor | 09/14/2011 |
| HATCHER, JOELY | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| HATIFI, SHANAZ | SACRAMENTO, CA | - | Counselor | 12/21/2016 |
| HATT, JEAN | WARNER ROBINS, GA | LPC, CPCS | Mental Health Counselor | 03/07/2017 |
| HATTAWAY, AIMEE | MACON, GA | - | Assistant Behavior Analyst | 09/21/2026 |
| HATZ, LAURA | SAN DIEGO, CA | PHD | Psychologist | 10/21/2024 |
| HATZAW, GRACE NIIANG | TULSA, OK | - | Case Manager/Care Coordinator | 09/23/2026 |
| HAUBEIL, BOBBI | CIRCLEVILLE, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| HAUGLIE, CASSANDRA | COON RAPIDS, MN | - | RBT | 09/23/2026 |
| HAUSER BRYDON, JESSICA | GRAND HAVEN, MI | LMSW | Clinical Social Worker | 09/25/2026 |
| HAUXWELL, ANNA | BROOKLYN CENTER, MN | M.A. LPC, BCBA, LBA | BCBA | 08/22/2006 |
| HAVEN HOUSE COUNSELING AND CONSULTING LLCORG | WEST MONROE, LA | - | Mental Health Counselor | 09/23/2026 |
| HAVEN INSIGHT COUNSELING, LLCORG | LOCK HAVEN, PA | - | Professional Counselor | 09/21/2026 |
| HAVEN TREATMENT HOMESTEADORG | KNOB NOSTER, MO | - | Mental Health Counselor | 09/21/2026 |
| HAVENS, BRIGID | CALUMET, MI | LPC | Mental Health Counselor | 08/02/2022 |
| HAVERDINK, CAITLIN | GRAND RAPIDS, MI | - | Clinical Social Worker | 08/26/2025 |
| HAVERS, KAYLEIGH | LITHIA, FL | - | RBT | 11/29/2023 |
| HAVILI, ILINA | GRESHAM, OR | - | RBT | 09/22/2026 |
| HAWKINS HARBOR PLLCORG | AUBURNDALE, MA | - | Mental Health Counselor | 09/26/2026 |
| HAWKINS, ERIKA | CHAPEL HILL, NC | SLP | Speech-Language Pathologist | 08/31/2009 |
| HAWKINS, NANETTE | STUART, FL | - | RBT | 09/21/2026 |
| HAWKINS, RONDAL | BECKLEY, WV | - | Case Manager/Care Coordinator | 09/21/2026 |
| HAWKINS, TAMISHIO | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| HAWLEY, AUTUMN | GREENVILLE, SC | - | BCBA | 04/29/2024 |
| HAWLEY, SYDNEY | LAS VEGAS, NV | - | RBT | 09/23/2026 |
| HAWORTH, MARAYNA | MIDDLETOWN, OH | - | RBT | 09/23/2026 |
| HAWTHORNE, DUANE | MARYLAND HEIGHTS, MO | - | RBT | 09/24/2026 |
| HAWTHORNE, MOLLY | LANDISVILLE, PA | - | Counselor | 09/21/2026 |
| HAY, SHAUNA | LAKE OSWEGO, OR | MS | Speech-Language Pathologist | 06/09/2025 |
| HAYES, BRISTIN | MIDWEST CITY, OK | - | RBT | 09/21/2026 |
| HAYES, ROBERTA SUE | DEVILS LAKE, ND | - | Case Manager/Care Coordinator | 09/24/2026 |
| HAYES, SARAH | CAMPBELLSVILLE, KY | LCSW | Clinical Social Worker | 03/11/2024 |
| HAYFORD, ABA | NEW YORK, NY | - | Case Management Agency | 01/24/2025 |
| HAYGOOD, JENNIFER | ALPENA, MI | - | RBT | 09/21/2026 |
| HAYS, ADAM | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| HAYS, TAYLOR | BRENTWOOD, TN | LPC-MHSP | Mental Health Counselor | 09/21/2026 |
| HAYWOOD, LAURA | SAINT LOUIS, MO | - | RBT | 06/02/2026 |
| HAYWOOD, MEGAN | HENDERSON, NV | - | RBT | 09/21/2026 |
| HAZELWOOD COUNSELING LLCORG | TEWKSBURY, MA | - | Mental Health Counselor | 09/23/2026 |
| HAZELWOOD, JACKY | MARYVILLE, TN | - | RBT | 09/24/2026 |
| HAZELWOOD, JAMIE | EDMOND, OK | - | Case Manager/Care Coordinator | 10/18/2023 |
| HAZIME, MANAL | DEARBORN, MI | - | Mental Health Counselor | 01/11/2016 |
| HAZZARD-MORRISON, MARY | SCARBOROUGH, ME | MS, LCPC | Mental Health Counselor | 05/02/2007 |
| HE, RACHEL | NORTHFIELD, IL | LPC | Mental Health Counselor | 09/24/2026 |
| HEAD, KEITH | PETOSKEY, MI | LMSW | Clinical Social Worker | 10/22/2019 |
| HEALING CENTER COLLECTIVE, P.L.L.C.ORG | AUSTIN, TX | - | Clinical Social Worker | 08/27/2026 |
| HEALING HEARTZ DAILY LLCORG | CARROLLTON, GA | - | RBT | 08/17/2026 |
| HEALING PLAN COUNSELING CENTER LLCORG | CLINTON TOWNSHIP, MI | - | Clinical Social Worker | 09/23/2026 |
| HEALING SYSTEMS COLLECTIVE, LLCORG | EUGENE, OR | - | Clinical Social Worker | 09/23/2026 |
| HEALING THROUGH COMPASSION, LLCORG | HAYDEN, ID | - | Counselor | 03/27/2023 |
| HEALINQUE AESTHETIC AND LONGEVITY CLINIC INC.ORG | POWAY, CA | - | Clinic/Center | 09/21/2026 |
| HEALTH ACCESS RX SERVICES INCORG | CHAPEL HILL, NC | - | Specialist | 09/21/2026 |
| HEALTH CENTER MSO LLCORG | ATLANTA, GA | - | Case Management Agency | 09/21/2026 |
| HEALTH MEETS WEALTH VENTURES LLCORG | JUNO BEACH, FL | - | Clinic/Center | 02/19/2024 |
| HEALTH PLANNING COUNCIL OF SOUTHWEST FLORIDA, INCORG | FORT MYERS, FL | - | BCBA | 09/20/2006 |
| HEALTH PLANNING COUNCIL OF SOUTHWEST FLORIDA, INCORG | FORT MYERS, FL | - | Case Management Agency | 02/15/2022 |
| HEALTH PLANNING COUNCIL OF SOUTHWEST FLORIDA, INCORG | SARASOTA, FL | - | Clinic/Center | 02/01/2022 |
| HEALTHCENTRIX LLCORG | RALEIGH, NC | - | Case Management Agency | 09/21/2026 |
| HEALTHCHECK SYSTEMS INCORG | RICHARDSON, TX | - | Clinic/Center | 09/21/2026 |
| HEALTHFORCE 365 LLCORG | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/26/2026 |
| HEALTHY ALL TIME LLCORG | BRIDGEVIEW, IL | - | Clinical Social Worker | 05/22/2024 |
| HEALTHY MINDS PSYCHOLOGICAL SERVICESORG | WASHINGTON, DC | - | Mental Health Counselor | 02/21/2026 |
| HEALU LLCORG | PHILADELPHIA, PA | - | Professional Counselor | 09/22/2026 |
| HEALY, SAVANNAH | GLENDALE, AZ | - | Mental Health Counselor | 12/17/2025 |
| HEARD, ANGELA | VINITA, OK | - | RBT | 11/28/2023 |
| HEART & GRACE THERAPYORG | LAUREL, MD | - | Mental Health Counselor | 10/20/2025 |
| HEART OF FLORIDA HEALTH CENTER, INCORG | OCALA, FL | - | Clinical Social Worker | 06/20/2006 |
| HEART OF VIRGINIA SUPPORTIVE SERVICES, LLCORG | CHESTERFIELD, VA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| HEART-CENTERED HEALING COLLECTIVE PLLCORG | CHICAGO, IL | - | Professional Counselor | 09/22/2026 |
| HEARTFELT IN HOME SUPPORT SERVICES INC.ORG | PORTSMOUTH, VA | - | Community/Behavioral Health Agency | 05/15/2024 |
| HEARTHLIGHT MENTAL HEALTH PLLCORG | SAN ANTONIO, TX | - | Psychologist | 09/22/2026 |
| HEARTSPACE PRACTICE, PCORG | AMHERST, MA | - | Clinical Social Worker | 09/25/2026 |
| HEASLET, ABIGAIL | OCEANSIDE, CA | - | RBT | 09/23/2026 |
| HEASLEY, HANNAH | CORPUS CHRISTI, TX | LPC | Professional Counselor | 09/18/2026 |
| HEAVEN, MICHAEL | MANCHESTER, CT | - | Clinical Social Worker | 02/03/2017 |
| HEAVY IS THE HEAD LLCORG | WASHINGTON, DC | - | Mental Health Counselor | 09/21/2026 |
| HEBERT, TAYLOR | CONCORD, NH | - | BCBA | 09/21/2026 |
| HECK, MEGAN | JACKSONVILLE, FL | - | Clinical Social Worker | 09/03/2025 |
| HECKER, MICHELLE | CHANDLER, AZ | - | BCBA | 11/18/2025 |
| HECKMAN, COLLEEN | AVONDALE, PA | MS OTR L | Specialist | 05/02/2007 |
| HEDGCOCK, SARAH | MILWAUKEE, WI | LCSW | Clinical Social Worker | 04/23/2020 |
| HEERA, ANU | SEATTLE, WA | MA, LMHCA | Mental Health Counselor | 09/17/2026 |
| HEEREN, REBECCA | ANKENY, IA | LMSW | Clinical Social Worker | 09/23/2026 |
| HEETER, CATHRYN | WOODSTOCK, GA | - | Clinical Social Worker | 09/03/2025 |
| HEIGERT, HEATHER | MANHATTAN, KS | LSCSW | Clinical Social Worker | 04/20/2017 |
| HEINTZ, JESSICA | PORTLAND, OR | CADC-R | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| HELBERG, MASON | NEWPORT BEACH, CA | SUDRC | Mental Health Counselor | 09/23/2026 |
| HELFER, CORY | SEATTLE, WA | LMHCA | Mental Health Counselor | 11/12/2024 |
| HELGERSON, STEPHANIE | ROSEMOUNT, MN | MSE CCC-SLP | Speech-Language Pathologist | 12/29/2006 |
| HELLA GOOD THERAPY, PLLCORG | SAN DIEGO, CA | - | Mental Health Counselor | 11/27/2023 |
| HELLWIG THERAPY SERVICES LLCORG | WINSTON SALEM, NC | - | Clinical Social Worker | 04/29/2019 |
| HELLWIG, REBECCA | WINSTON SALEM, NC | LMSW | Clinical Social Worker | 02/16/2011 |
| HELM, JOHNATHON | CLEVELAND, OH | - | RBT | 09/25/2026 |
| HELMANDI, SAFEENA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| HELMICK, MOLLEE | LAFAYETTE, LA | - | Professional Counselor | 09/22/2026 |
| HEMAYA, MARIAM | CYPRESS, TX | - | RBT | 09/21/2026 |
| HEMENWAY, JO | PORTLAND, OR | - | Mental Health Counselor | 09/21/2026 |
| HEMENWAY, NATALIE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| HENCH, KRISTEN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| HENDERLONG, DEBRA | ROCKLAND, ME | LCSW | Clinical Social Worker | 11/12/2009 |
| HENDERSON BEHAVIORAL HEALTH, INC.ORG | LAUDERDALE LAKES, FL | - | Case Management Agency | 07/03/2006 |
| HENDERSON, JEREMY | BOSTON, MA | - | Mental Health Counselor | 09/26/2026 |
| HENDERSON, KATHERINE | WALTHAM, MA | CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| HENDERSON, TYONNA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| HENDERSON, ZARIA | NASHVILLE, AR | - | Case Manager/Care Coordinator | 09/26/2026 |
| HENDRICKS, COKETHA | CHICAGO, IL | LCSW | Clinical Social Worker | 06/23/2020 |
| HENDRICKS, MASHAUN | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| HENDRICKSON, LUCIE | GOLD RIVER, CA | - | Counselor | 12/06/2025 |
| HENDRIX, JANESSA | FORT DODGE, IA | - | RBT | 09/21/2026 |
| HENLEY, ERICA | EVANS, GA | - | RBT | 05/08/2023 |
| HENNESSY, BRYN | MINNEAPOLIS, MN | MA, LPC | Professional Counselor | 09/22/2026 |
| HENNINGS, SHELLY | TULALIP, WA | CDP, NCAC-I | Addiction (Substance Use Disorder) Counselor | 10/17/2008 |
| HENRY, ABBRIELLE | BOCA RATON, FL | RBT | BCBA | 09/11/2023 |
| HENRY, JOANIE | FORT SMITH, AR | LPC | Professional Counselor | 02/12/2008 |
| HENRY, ROCHELLE | GRAPEVINE, TX | PHD | Psychologist | 11/06/2024 |
| HENSLEY, AALIYAH | KENT, WA | - | RBT | 09/01/2026 |
| HENSON, MAGGIE | EDMOND, OK | - | RBT | 09/22/2026 |
| HENSON, MATTHEW | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| HENTZ, ABIGAIL | CINCINNATI, OH | - | Case Manager/Care Coordinator | 08/02/2022 |
| HER HAVEN COLLECTIVE PLLCORG | LINDON, UT | - | Mental Health Counselor | 09/17/2026 |
| HER HAVEN COUNSELING, PLLCORG | ALTOONA, IA | - | Mental Health Counselor | 09/23/2026 |
| HER, DAO | VAN NUYS, CA | - | RBT | 12/05/2023 |
| HER, JENNY | GRANITE BAY, CA | - | RBT | 09/23/2026 |
| HERBERT, MORGAN | O FALLON, MO | - | Speech-Language Pathologist | 08/18/2023 |
| HERDMAN, REBEKAH | MEDINA, OH | I.2102680-SUPV | Mental Health Counselor | 04/04/2018 |
| HERDT, JULIE | OREM, UT | - | BCBA | 06/15/2018 |
| HEREDIA, ANTHONY | EL SEGUNDO, CA | - | RBT | 07/15/2026 |
| HEREDIA, JOHANKA | LOWELL, MA | - | RBT | 09/22/2026 |
| HEREDIA, LEONARDO | SACRAMENTO, CA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| HERKERT, KIMBERLY | EUREKA, CA | LMFT | Mental Health Counselor | 02/14/2007 |
| HERNANDEZ ESTENOZ, LISIANET | MIAMI, FL | - | RBT | 10/27/2023 |
| HERNANDEZ GARCIA, IAN | EL CENTRO, CA | - | Assistant Behavior Analyst | 09/24/2026 |
| HERNANDEZ GUTIERREZ, SAMANTHA | LOS ANGELES, CA | - | RBT | 09/23/2026 |
| HERNANDEZ KUKTA, JOLENE | POMONA, CA | - | RBT | 09/21/2026 |
| HERNANDEZ LOPEZ, YANAISY | BOCA RATON, FL | BCBA | BCBA | 06/27/2019 |
| HERNANDEZ MENDEZ, EMILY | VENTURA, CA | - | RBT | 09/21/2026 |
| HERNANDEZ PRIETO, LILIANIS | CAPE CORAL, FL | - | BCBA | 12/19/2018 |
| HERNANDEZ, ALEXANDRA | WEST VALLEY, UT | - | RBT | 09/23/2026 |
| HERNANDEZ, AMANDA | ALBUQUERQUE, NM | - | Case Manager/Care Coordinator | 09/16/2024 |
| HERNANDEZ, BRENDA | MENIFEE, CA | - | RBT | 04/03/2026 |
| HERNANDEZ, BRIANNA | BELL GARDENS, CA | - | Clinical Social Worker | 01/12/2018 |
| HERNANDEZ, CHRISTY | ABILENE, TX | LPC | Mental Health Counselor | 03/10/2020 |
| HERNANDEZ, CLAUDIA | SPRING HILL, FL | - | RBT | 09/23/2026 |
| HERNANDEZ, DESTINY | SANTA ANA, CA | - | RBT | 09/22/2026 |
| HERNANDEZ, DESTINY | SAN ANTONIO, TX | - | Counselor | 04/23/2022 |
| HERNANDEZ, EDGAR | HUNTINGTON, WV | LICSW | Clinical Social Worker | 08/02/2021 |
| HERNANDEZ, ELISE | AUSTIN, TX | LPC | Professional Counselor | 06/16/2020 |
| HERNANDEZ, EMELY | LOMBARD, IL | - | RBT | 09/22/2026 |
| HERNANDEZ, EVELYN | LOS ANGELES, CA | - | RBT | 09/24/2026 |
| HERNANDEZ, FRANCISCO | SANTA ANA, CA | MA | RBT | 02/27/2019 |
| HERNANDEZ, FREDDY | OAKLAND, CA | - | Day Training/Habilitation Specialist | 11/08/2023 |
| HERNANDEZ, HAILY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| HERNANDEZ, ITZEL | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| HERNANDEZ, JACLYN | HILLSBOROUGH, NJ | LCSW | Mental Health Counselor | 12/30/2014 |
| HERNANDEZ, JAZMIN | LAKE ELSINORE, CA | - | Clinical Social Worker | 01/13/2020 |
| HERNANDEZ, JENNIFER | ESCONDIDO, CA | - | Case Manager/Care Coordinator | 05/06/2024 |
| HERNANDEZ, LAURA | GLENDALE, CA | - | RBT | 09/25/2026 |
| HERNANDEZ, MALLORY | BRYAN, TX | - | RBT | 09/24/2026 |
| HERNANDEZ, MARIA | TULSA, OK | - | Case Manager/Care Coordinator | 09/25/2026 |
| HERNANDEZ, MARY | MODESTO, CA | - | RBT | 09/24/2026 |
| HERNANDEZ, MAYLEEN | LAKE MARY, FL | - | RBT | 09/21/2026 |
| HERNANDEZ, MELISA | LUBBOCK, TX | M. A., LPC | Mental Health Counselor | 10/19/2016 |
| HERNANDEZ, NALLELY | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 09/25/2026 |
| HERNANDEZ, NINEL | ALBUQUERQUE, NM | - | Speech-Language Pathologist | 09/24/2026 |
| HERNANDEZ, NITZI | REDONDO BEACH, CA | - | RBT | 09/23/2026 |
| HERNANDEZ, RAMON | LEHIGH ACRES, FL | - | Speech-Language Pathologist | 09/21/2026 |
| HERNANDEZ, ROSPIGLIOSY | JUNCOS, PR | - | Mental Health Counselor | 09/24/2026 |
| HERNANDEZ, SAMANTHA | EL SEGUNDO, CA | - | RBT | 10/05/2023 |
| HERNANDEZ, SAVANNAH | LOS LUNAS, NM | - | RBT | 09/22/2026 |
| HERNANDEZ, SYDNEY | PALO ALTO, CA | PHD | Psychologist | 07/15/2025 |
| HERNANDEZ, VICTOR | LITTLETON, CO | - | RBT | 09/21/2026 |
| HERNANDEZ, YASMIN | COALINGA, CA | - | RBT | 01/28/2019 |
| HERNANDO, MA ELIZABETH | LOS ANGELES, CA | - | RBT | 09/22/2026 |
| HERRERA RIVERA, ISABEL | MOUNT VERNON, WA | - | Speech-Language Pathologist | 09/23/2026 |
| HERRERA-ORTEGA, MARISOL | COMPTON, CA | - | Clinical Social Worker | 03/21/2022 |
| HERRERA-REYNA, ALEXIS | LAS CRUCES, NM | - | RBT | 11/13/2023 |
| HERRERA, ADAN | FRESNO, CA | - | Addiction (Substance Use Disorder) Counselor | 04/23/2020 |
| HERRERA, ANGELINA | CLERMONT, FL | - | Mental Health Counselor | 09/22/2026 |
| HERRERA, BRITTANY | DOWNEY, CA | - | Clinical Social Worker | 09/21/2026 |
| HERRERA, CORINA | LAKEWOOD, CO | - | RBT | 09/23/2026 |
| HERRERA, DIANA | SANTA ANA, CA | - | RBT | 09/24/2026 |
| HERRERA, SOPHIA | WHITTIER, CA | - | Speech-Language Pathologist | 09/21/2026 |
| HERRERA, VALERIE | DOWNEY, CA | - | RBT | 09/25/2026 |
| HERRERA, VICTORIA | MORA, NM | CCC-SLP | Speech-Language Pathologist | 11/14/2007 |
| HERRLEIN, LAKYN | MOUNT WASHINGTON, KY | - | RBT | 09/21/2026 |
| HERSETH, ELIZABETH | NASHVILLE, TN | - | RBT | 09/24/2026 |
| HERVEY, DAVID | TUCSON, AZ | LCSW | Clinical Social Worker | 11/18/2016 |
| HERZOG, ALEXANDRA | INDIANAPOLIS, IN | LMSW | Clinical Social Worker | 09/22/2026 |
| HESKETH, KARI | MESA, AZ | LPC | Counselor | 06/03/2020 |
| HESLINGA, LAUREN | SKOKIE, IL | LCPC | Professional Counselor | 09/24/2026 |
| HESS, ASHLEY | AURORA, CO | BCBA | BCBA | 09/25/2026 |
| HESS, ELLEN | FLORENCE, OR | MHC.LH.60704304 | Mental Health Counselor | 10/31/2018 |
| HESS, SHELDON | MENTOR, OH | LPCC | Professional Counselor | 03/05/2007 |
| HESS, ZACHERY | MASON, OH | - | Counselor | 01/04/2023 |
| HESSERT, KYLIE | BUXTON, ME | - | Speech-Language Pathologist | 06/03/2010 |
| HESTAND, EMILY | VERSAILLES, KY | - | RBT | 09/23/2026 |
| HESTER, JEWEL | TUSCUMBIA, AL | - | Assistant Behavior Analyst | 09/24/2026 |
| HETHERINGTON, ZOE | CHICAGO, IL | - | Speech-Language Pathologist | 07/12/2022 |
| HETTENA, JOLIE | SEAFORD, NY | - | Speech-Language Pathologist | 05/11/2026 |
| HETTIARACHCHILAGE, PRAVEENA | BALTIMORE, MD | - | RBT | 09/22/2026 |
| HETTINGA, AUSTIN | CHICAGO, IL | - | Professional Counselor | 09/02/2026 |
| HEUTZ, SARAH | MEDIA, PA | MS | Mental Health Counselor | 09/22/2026 |
| HEWITT, KIERA | JASPER, IN | - | RBT | 09/22/2026 |
| HEYER, TAYLER | BEMIDJI, MN | - | Professional Counselor | 04/27/2026 |
| HEYWOOD, CLAIRE | POTTSTOWN, PA | - | Mental Health Counselor | 09/24/2026 |
| HIBBLER, SHAWNA | CHEYENNE, WY | MSW | Clinical Social Worker | 04/01/2010 |
| HICKERSON, TOLETA | MEMPHIS, TN | - | Case Manager/Care Coordinator | 05/01/2026 |
| HICKEY, KATHRYN | AMESBURY, MA | MED | Mental Health Counselor | 05/05/2025 |
| HICKMAN, SUZANNE | EDINA, MN | LPCC | Mental Health Counselor | 09/23/2026 |
| HICKS, SAMANTHA | NORTH LITTLE ROCK, AR | QBHP | RBT | 07/07/2025 |
| HID, JACQUELINE | SAN DIEGO, CA | - | Mental Health Counselor | 01/09/2017 |
| HIDALGO LOPEZ, VALERIA | FREDERICK, MD | - | Speech-Language Pathologist | 09/23/2026 |
| HIDALGO, ZAMANTHA | ALBUQUERQUE, NM | - | Case Manager/Care Coordinator | 09/23/2026 |
| HIDDEN WITHIN COUNSELING & SEX THERAPY, PLLCORG | FENTON, MI | - | Community/Behavioral Health Agency | 03/19/2024 |
| HIEGER, PAMELA | CREVE COEUR, MO | - | Professional Counselor | 11/25/2020 |
| HIETT, KAYLA | ZANESVILLE, OH | MSW, LISW | Case Manager/Care Coordinator | 06/08/2018 |
| HIGDEN, PHOEBE | GREENSBORO, NC | LCSWA | Mental Health Counselor | 09/22/2026 |
| HIGDON, SAMONA | BEACHWOOD, OH | - | Counselor | 09/23/2026 |
| HIGGINBOTTOM, ASHLEY | WOONSOCKET, RI | LCSW | Clinical Social Worker | 09/07/2022 |
| HIGGINS, ALEXIS | SAVANNAH, GA | - | RBT | 09/25/2026 |
| HIGGINS, ROSHANE | ROCKVILLE, MD | - | RBT | 09/25/2026 |
| HIGGINS, STAFFORD | ALEXANDRIA, VA | LCSW-C | Clinical Social Worker | 08/22/2022 |
| HIGH POINT WELLNESSORG | ROCK SPRINGS, WY | - | Clinic/Center | 02/10/2026 |
| HIGH RISE THERAPY PLLCORG | KYLE, TX | - | Professional Counselor | 09/22/2026 |
| HIGHER LIFE PATHWAYS COUNSELING SERVICES LLCORG | ALEXANDRIA, VA | - | Counselor | 10/16/2018 |
| HIGHTOWER, ELIYAH | DALLAS, TX | LCDC, LPC | Mental Health Counselor | 02/23/2024 |
| HIGLEY, AMANDA | SPOKANE, WA | CARE COORDINATOR | Counselor | 09/24/2026 |
| HILARY HORRIGAN LLCORG | LITTLETON, CO | - | Professional Counselor | 11/12/2024 |
| HILD, NICOLE | CALABASAS, CA | - | RBT | 11/23/2021 |
| HILL COUNTRY COMMUNITY MHMR CENTERORG | KERRVILLE, TX | - | Professional Counselor | 08/19/2006 |
| HILL, ALANA | TEMECULA, CA | - | RBT | 09/12/2026 |
| HILL, JADA | GREENVILLE, SC | - | RBT | 09/21/2026 |
| HILL, KALIB | PIKESVILLE, MD | - | RBT | 09/22/2026 |
| HILL, KAYLA | TALLAHASSEE, FL | - | RBT | 09/23/2026 |
| HILL, MAYA | SHERMAN OAKS, CA | - | RBT | 09/24/2026 |
| HILL, REGINALD | SPRINGFIELD, MO | MS, PLPC | Professional Counselor | 07/25/2023 |
| HILL, RICHARD | ONTARIO, CA | - | RBT | 09/22/2026 |
| HILL, SHAKEITA | FARMINGTON HILLS, MI | - | Assistant Behavior Analyst | 06/24/2026 |
| HILL, TAJUNA | MONTICELLO, AR | - | Case Manager/Care Coordinator | 09/25/2026 |
| HILLMAN, AARON | TARZANA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| HILLSNAPP-RANKIN, PATRICIA | CASCADE, ID | - | Counselor | 09/25/2026 |
| HINDE, HAYLEY | ALBUQUERQUE, NM | LPC | Professional Counselor | 05/17/2023 |
| HINES, ALIYAH | GWYNN OAK, MD | BT | BCBA | 09/23/2026 |
| HINES, IMANI | GREENSBORO, NC | - | Clinical Social Worker | 09/21/2026 |
| HINES, KIANA | ATLANTA, GA | PHD, CCC-SLP | Speech-Language Pathologist | 01/26/2022 |
| HINES, KOBY | SPOKANE, WA | LMHCA | Mental Health Counselor | 07/11/2023 |
| HINES, PARIS | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| HINES, SYDNEY | TUSCUMBIA, AL | - | RBT | 09/23/2026 |
| HINKE, ELSA | HALES CORNERS, WI | M.S. | Mental Health Counselor | 09/21/2026 |
| HINKLE, GRETA | FRANKFORT, IN | MS BCBA | BCBA | 02/09/2024 |
| HINMAN, BRYAN | BLOOMINGTON, IL | M.A. | Mental Health Counselor | 06/22/2012 |
| HINMAN, LAURA | EAST LANSING, MI | - | RBT | 11/30/2022 |
| HINNANT-JOHNS, JEANNINE | PHILADELPHIA, PA | - | Counselor | 11/03/2015 |
| HINOJOSA-VILLARREAL, CHRISTOPHER | BROWNSVILLE, TX | MPSY, LPC | Professional Counselor | 03/03/2025 |
| HINTON, KATHERINE | AUGUSTA, GA | - | Mental Health Counselor | 09/21/2026 |
| HINTON, VICTORIA | WOODBURY, MN | - | RBT | 09/21/2026 |
| HIPOLITO MARTINEZ, DALIA | SAN MARCOS, CA | MSW, ASW, PPS | Clinical Social Worker | 09/25/2026 |
| HIRACHETA, HANNAH | AUSTIN, TX | - | RBT | 09/22/2026 |
| HIRSCH, STEVEN | SAN DIEGO, CA | PHD | Psychologist | 07/28/2006 |
| HITE, ABIGAIL | RALEIGH, NC | LCSWA | Clinical Social Worker | 05/30/2024 |
| HM CARDIOLOGYORG | CLIFTON, NJ | - | Clinic/Center | 04/16/2020 |
| HO, BOI KHIET | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| HO, LEIGH | ALBUQUERQUE, NM | LPCC | Professional Counselor | 03/03/2023 |
| HOBAN, JENNY | LAKE GENEVA, WI | - | Speech-Language Pathologist | 09/23/2026 |
| HOBLIT, CALLIE | ARLINGTON, TX | - | Speech-Language Pathologist | 03/22/2022 |
| HOBSON, XARIA | NORTH LAS VEGAS, NV | - | BCBA | 09/23/2026 |
| HOBURG, VICTORIA | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| HOCHBERG, ERICA | EXETER, NH | LICSW | Clinical Social Worker | 03/06/2021 |
| HOCKMAN, BRANDON | LONGVIEW, WA | - | Counselor | 05/11/2026 |
| HODES, ROBERT | LAKEWOOD RANCH, FL | PHD | Psychologist | 08/10/2006 |
| HODGE, HANNAH | RADCLIFF, KY | RBT | RBT | 05/22/2025 |
| HODGE, MISTY | CYPRESS, TX | LPC | Professional Counselor | 01/26/2023 |
| HODGE, NTASHA | STONE MOUNTAIN, GA | LPC | Mental Health Counselor | 03/06/2023 |
| HODGE, SAMUEL | CINCINNATI, OH | LPC | Counselor | 05/05/2025 |
| HODGES, AMANDA | COLUMBIA, SC | - | RBT | 09/21/2026 |
| HOEPPNER, CHRISTINA | SAN ANTONIO, TX | LPC | Professional Counselor | 06/08/2006 |
| HOFFMAN, KATE | SKOKIE, IL | - | Mental Health Counselor | 09/21/2026 |
| HOFFMAN, KRISTA | MARRIOTTSVILLE, MD | M.S. L.C.P.C. | Mental Health Counselor | 09/17/2006 |
| HOFFMAN, NATALIE | FRANKLIN, TN | - | RBT | 09/21/2026 |
| HOGAN, CHANDYN | STATESVILLE, NC | CCC-SLP | Speech-Language Pathologist | 07/29/2026 |
| HOGAN, RICO | AUGUSTA, GA | LCSW | Clinical Social Worker | 01/04/2024 |
| HOGAN, TYLER | PINE BROOK, NJ | LPC, NCC | Mental Health Counselor | 11/10/2022 |
| HOGUE, KAYLI | OLD WASHINGTON, OH | - | Case Manager/Care Coordinator | 03/02/2026 |
| HOISINGTON, EMMA | DRAPER, UT | LCSW | Clinical Social Worker | 09/25/2026 |
| HOLBROOK, JORDYN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| HOLDER, DINELLY | ALEXANDRIA, VA | PHD, NCC, CCMHC | Professional Counselor | 12/22/2012 |
| HOLDERBY, SEBASTIAN | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| HOLEY, SARAH | JENISON, MI | MA CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| HOLGUIN- GRADO, MARISA | SAN ANTONIO, TX | LCSW | Clinical Social Worker | 01/15/2018 |
| HOLGUIN, MATTHEW | PASADENA, CA | - | Professional Counselor | 08/29/2022 |
| HOLISTIC ALLIES PR LLCORG | CEIBA, PR | - | Clinical Social Worker | 09/22/2026 |
| HOLISTIC JOURNEY COUNSELING AND CONSULTING, PLLCORG | ST GEORGE, UT | - | Clinical Social Worker | 04/08/2026 |
| HOLLADAY, ABRIANNA | STUART, FL | - | Assistant Behavior Analyst | 05/04/2023 |
| HOLLAND, HEATHER | CARY, NC | - | Speech-Language Pathologist | 10/21/2020 |
| HOLLEY, KATHERINE | ST PETERSBURG, FL | LMSW, CAADC | Clinical Social Worker | 03/09/2010 |
| HOLLIDAY, MELINDA | GRAND RAPIDS, MI | LMSW, CAADC | Clinical Social Worker | 01/29/2017 |
| HOLLINGSWORTH, HANNAH | MARTIN, TN | - | Mental Health Counselor | 06/30/2025 |
| HOLLIS, APRIL | HIGHLAND PARK, MI | - | Case Manager/Care Coordinator | 09/24/2026 |
| HOLLYLEAF HEALING LICENSED CLINICAL SOCIAL WORKER PROFESSIONAL CORPORG | SOUTH PASADENA, CA | - | Clinical Social Worker | 09/24/2026 |
| HOLMES, LATETIA | CHARLOTTE, NC | - | Mental Health Counselor | 09/23/2026 |
| HOLMQUEST, CYNTHIA | SIOUX FALLS, SD | CSW | Clinical Social Worker | 08/08/2022 |
| HOLMQUIST, QUINN | CHAPEL HILL, NC | - | Mental Health Counselor | 09/22/2026 |
| HOLT, KRISTIN | HOUSTON, TX | LCSW | Clinical Social Worker | 01/31/2022 |
| HOLT, STEPHANIE | PORT ST LUCIE, FL | RMFTI | Mental Health Counselor | 05/26/2022 |
| HOLTON, KELLEE | CLERMONT, FL | - | Speech-Language Pathologist | 09/23/2026 |
| HOLTZ, KASONDRA | LAPEER, MI | LMSW | Clinical Social Worker | 03/11/2026 |
| HOLTZ, SAMANTHA | MINNEAPOLIS, MN | LICSW | Clinical Social Worker | 09/21/2026 |
| HOLTZCLAW, BRIANNA | LENEXA, KS | - | RBT | 09/22/2026 |
| HOLZER, SALLY | LAS VEGAS, NV | - | Clinical Social Worker | 01/06/2011 |
| HOMAN, KAYLA | JOHNSTOWN, PA | SLP | Speech-Language Pathologist | 10/03/2023 |
| HOME RESILIENCE PLLCORG | KEEGO HARBOR, MI | - | Mental Health Counselor | 09/21/2026 |
| HOMESTEAD CARES FOUNDATIONORG | HOMESTEAD, FL | - | Case Management Agency | 04/28/2025 |
| HOMETOWN FINANCIAL SERVICES, INC.ORG | AUSTIN, TX | - | Case Management Agency | 09/23/2026 |
| HONEY, RIVER | PORTLAND, OR | - | Counselor | 03/16/2021 |
| HONG, SARA | HONOLULU, HI | - | RBT | 08/22/2023 |
| HONKEN, GABRIELLE | ELMHURST, IL | - | RBT | 09/25/2026 |
| HONORHEALTH MEDICAL GROUP, LLCORG | PHOENIX, AZ | - | Psychologist | 06/18/2006 |
| HOOFMAN, JESSICA | MELBOURNE, FL | BCBA | BCBA | 09/26/2018 |
| HOOIKAIKA MANSANAS, MAKEALANI | WAILUKU, HI | RBT | RBT | 09/24/2026 |
| HOOPER, GINA | SMYRNA, TN | - | Professional Counselor | 09/09/2026 |
| HOOVER, CAITLIN | VANCOUVER, WA | - | RBT | 09/21/2026 |
| HOOVER, HULLY | STATE COLLEGE, PA | M.ED, LAPC | Mental Health Counselor | 08/19/2025 |
| HOPE CENTER FOR BEHAVIOR CHANGE INCORG | WEST PALM BEACH, FL | - | BCBA | 06/14/2022 |
| HOPE MEDICAL CENTER PLLCORG | DOWNERS GROVE, IL | - | Specialist | 04/19/2024 |
| HOPE'S WINGS ABA CORPORG | PEMBROKE PINES, FL | - | BCBA | 09/30/2024 |
| HOPKINS, AMANDA | SALISBURY, MD | LCSW-C | Mental Health Counselor | 07/13/2012 |
| HOPKINS, JASMINE | DIAMOND SPRINGS, CA | LCSW | Clinical Social Worker | 12/13/2023 |
| HOPKINS, JESSICA | WINTHROP, ME | LCSW | Clinical Social Worker | 10/05/2006 |
| HOPKINS, STEPHANIE | ROSEMOUNT, MN | M.S. | Speech-Language Pathologist | 06/13/2012 |
| HOPPE, KELLY | MADISON, WI | LPC | Professional Counselor | 09/11/2014 |
| HOPPE, MICHELLE | CORALVILLE, IA | - | RBT | 09/24/2026 |
| HOPPER, RODNEY | VALPARAISO, IN | - | Mental Health Counselor | 05/05/2025 |
| HOPPING, DEVON | RIVERVIEW, FL | - | Mental Health Counselor | 09/25/2026 |
| HOPPING, LEAH | JOHNSTON, RI | - | Counselor | 11/07/2024 |
| HOQUE, NASIF | FRESH MEADOWS, NY | - | Case Manager/Care Coordinator | 09/25/2026 |
| HORA, TONISHA | NEW RICHMOND, WI | APSW | Clinical Social Worker | 09/22/2026 |
| HORENSTEIN, CAROLINE | SCOTTSDALE, AZ | SLP-CCC | Speech-Language Pathologist | 06/21/2021 |
| HORIZON CENTERS OF SAN JOSEORG | SAN JOSE, CA | - | Case Manager/Care Coordinator | 04/28/2025 |
| HORN-TOLLACK, TEAGEN | PHELAN, CA | - | Assistant Behavior Analyst | 09/22/2026 |
| HORN, DEBRA | THE WOODLANDS, TX | - | Mental Health Counselor | 04/25/2022 |
| HORNBECK, MELISSA | CHAPEL HILL, NC | LCSWA, LCAS | Clinical Social Worker | 12/08/2020 |
| HORNE, OLIVIA | PARKERSBURG, WV | BS | Case Manager/Care Coordinator | 09/23/2026 |
| HORNE, SALLY | CHATTANOOGA, TN | M.D. | Specialist | 08/15/2006 |
| HORNER, CHARLES | RANDOLPH, MA | - | RBT | 09/21/2026 |
| HORNICK, MARTHA | ROANOKE, VA | LCSW | Clinical Social Worker | 06/08/2006 |
| HORTON, MADISEN | MIAMI, OK | - | RBT | 05/28/2024 |
| HORTON, TIFFANY | ALPHARETTA, GA | - | Speech-Language Pathologist | 03/16/2026 |
| HOSSENLOPP, JENNIFER | ROCHESTER, NY | LMSW, CASAC | Addiction (Substance Use Disorder) Counselor | 06/06/2025 |
| HOTHEM, MADISON | BOISE, ID | - | Community/Behavioral Health Agency | 09/24/2026 |
| HOTTMANN, KASSANDRA | CANTON, OH | LPC | Counselor | 06/17/2024 |
| HOULDIN, MARK | DURHAM, NC | - | Clinical Social Worker | 08/24/2026 |
| HOUNNOU, STEPHANIE | LOS ANGELES, CA | - | Mental Health Counselor | 01/14/2019 |
| HOURGLASS BODY CONTOURING SPA, LLCORG | TIMONIUM, MD | - | Clinic/Center | 09/24/2026 |
| HOUSE, AUGUST | MOORE, OK | - | Case Manager/Care Coordinator | 09/22/2026 |
| HOUSEHOLDER, GRACE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| HOUSTON, KATESHA | ALICE, TX | LCDC | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| HOUTING, CAITLIN | TRENTON, MI | - | RBT | 09/24/2026 |
| HOVAN, LINDSEY | CHICAGO, IL | PSYD | Psychologist | 05/14/2019 |
| HOWARD, ELIZABETH | KNOX, IN | M.S., CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| HOWARD, KALLIE | LAKELAND, FL | - | RBT | 09/13/2025 |
| HOWARD, LEIA | CONCORD, CA | - | RBT | 09/25/2026 |
| HOWARD, MADELEINE | GRAND RAPIDS, MI | LLMSW | Clinical Social Worker | 09/21/2026 |
| HOWARD, MEAGAN | KANSAS CITY, MO | LSCSW | Clinical Social Worker | 09/15/2020 |
| HOWARD, ROCQUELL | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| HOWE, MATTHEW | MANSFIELD, OH | - | Mental Health Counselor | 04/13/2023 |
| HOWELL, ALLYSON | BOUNTIFUL, UT | LCSW, PMH-C | Clinical Social Worker | 09/24/2026 |
| HOWELL, MEGAN | FRISCO, TX | - | Counselor | 09/26/2026 |
| HOWER, LISA | RIVERSIDE, CA | CADC II | Addiction (Substance Use Disorder) Counselor | 02/29/2016 |
| HOWIE, AMELIA | BLUE SPRINGS, MO | - | RBT | 09/23/2026 |
| HOWLAND, ALAINA | LOS ANGELES, CA | LCSW | Clinical Social Worker | 09/25/2026 |
| HOYNG, ALYSSA | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| HOYOS, JESSICA | CHICAGO, IL | LMFT, LCPC | Professional Counselor | 10/28/2015 |
| HOYT, MADAE | ODESSA, FL | - | RBT | 09/25/2026 |
| HSA LOUISIANA PHYSICIAN GROUP INCORG | WEST MONROE, LA | - | Specialist | 11/13/2024 |
| HTUT, THUWUNNA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| HU, DANIELLE KARYLLE | MADISON, WI | - | Speech-Language Pathologist | 05/17/2021 |
| HU, SHAWN | ONTARIO, CA | MS, BCBA | BCBA | 10/31/2023 |
| HUA, GLORIA | SANTA CRUZ, CA | - | RBT | 09/25/2026 |
| HUA, JENNIFER | ARLINGTON, VA | - | Mental Health Counselor | 09/23/2026 |
| HUALLANCA ECHAJAYA, GIOMARA | LAKE VIEW TERRACE, CA | - | Day Training/Habilitation Specialist | 04/30/2024 |
| HUANG, YA-HSUAN | WOODLAND HILLS, CA | - | BCBA | 09/22/2026 |
| HUANG, YAN-JHEN | RANCHO CUCAMONGA, CA | - | RBT | 09/21/2026 |
| HUBBARD, AMARIS | FARMINGTON HILLS, MI | - | Assistant Behavior Analyst | 04/08/2024 |
| HUBBARD, BRITTANY | EAST BRIDGEWATER, MA | M.S., CCC-SLP, CLC | Speech-Language Pathologist | 06/30/2014 |
| HUCKS-SMITH, CYNTHIA | SAVANNAH, GA | PHD | Psychologist | 02/27/2017 |
| HUCKSTEP, LINDA | WAUKESHA, WI | LPC | Professional Counselor | 06/27/2017 |
| HUDDLESTON, KELLEY | YUBA CITY, CA | LCSW | Clinical Social Worker | 06/11/2007 |
| HUDNALL, BOBBY | INWOOD, WV | - | Counselor | 09/25/2026 |
| HUDNALL, MELANIE | SAN ANTONIO, TX | - | Mental Health Counselor | 07/25/2017 |
| HUDNETT, CHRISTY | PISCATAWAY, NJ | LAC | Professional Counselor | 09/08/2023 |
| HUDSON ADRIAN, BRIGETTE | FARMINGTON HILLS, MI | - | RBT | 09/23/2026 |
| HUDSON, JENNIFER | SAN RAFAEL, CA | - | Addiction (Substance Use Disorder) Counselor | 01/25/2021 |
| HUDSON, TASMAN | REDONDO BEACH, CA | - | RBT | 10/05/2023 |
| HUDSON, TRISTIN | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| HUDSPETH, GABRIELLE | RUSSELLVILLE, AR | - | RBT | 09/21/2026 |
| HUEBNER, MELISSA | BELLEVILLE, IL | LCPC | Mental Health Counselor | 02/05/2019 |
| HUERTA, ANA | LOUISVILLE, KY | RBT | RBT | 09/26/2026 |
| HUETTLER, CAITLYN | JACKSON, NJ | - | Mental Health Counselor | 07/17/2018 |
| HUFF, BRANDY | SOUTH BEND, IN | - | Clinical Social Worker | 09/25/2026 |
| HUFF, JONATHAN | HONOLULU, HI | - | BCBA | 09/22/2018 |
| HUFF, TAYLOR | STATESVILLE, NC | - | Speech-Language Pathologist | 09/16/2026 |
| HUGHBANKS, CIARRA | AMELIA, OH | - | RBT | 09/22/2026 |
| HUGHES-HADAWAY, AKILAH | WOODBURY, NJ | LAC, LCADC, CCS | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| HUGHES, HEATHER | SUMMERVILLE, SC | LPCA | Mental Health Counselor | 09/24/2026 |
| HUGHES, JAZMINE | NORCROSS, GA | - | BCBA | 05/14/2020 |
| HUGHES, LANE | MCALLEN, TX | MS, CCC/SLP | Speech-Language Pathologist | 05/16/2017 |
| HUGHES, VANTRANIQUE | FORT WORTH, TX | M.A.,LCDC,CSAT-C | Addiction (Substance Use Disorder) Counselor | 01/17/2023 |
| HUI, MADELYN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| HUI, WILLIAM | WALNUT CREEK, CA | - | RBT | 09/23/2026 |
| HUIZENGA, TIFFANY | CHETEK, WI | SLP | Speech-Language Pathologist | 11/28/2006 |
| HULEN, REESE | RICHFIELD, MN | - | RBT | 09/21/2026 |
| HULL, KATHERINE | BENNINGTON, VT | LICSW | Clinical Social Worker | 10/15/2019 |
| HUMAN DEVELOPMENT & STRESS MANAGEMENT CENTER, LLCORG | BREMERTON, WA | - | Clinic/Center | 07/04/2008 |
| HUMANKINDNESS HEALTHORG | TACOMA, WA | - | Clinical Social Worker | 09/24/2026 |
| HUMIEDA, OUTHMAN | NEWPORT BEACH, CA | - | RBT | 09/23/2026 |
| HUMMEL, ANNA | GRINNELL, IA | TLMHC | Mental Health Counselor | 09/23/2026 |
| HUMMEL, JADE | FORT WORTH, TX | - | RBT | 09/24/2026 |
| HUMPERT, LINDSAY | AURORA, CO | LPC | Mental Health Counselor | 06/08/2022 |
| HUMPHREY, DMONIQUE | OVERLAND PARK, KS | - | RBT | 09/24/2026 |
| HUMPHREY, RIISA | EUGENE, OR | LPC, NCC | Professional Counselor | 06/09/2016 |
| HUMPHRIES, ELISE | RENO, NV | CSW-I | Clinical Social Worker | 07/16/2024 |
| HUMS, LAUREN | RED BANK, NJ | LPC | Mental Health Counselor | 09/21/2026 |
| HUNNICUTT HOLLENBAUGH, KAREN | CORPUS CHRISTI, TX | LPC | Professional Counselor | 11/13/2006 |
| HUNSUCKER, ROBYN | EDMOND, OK | LPC | Mental Health Counselor | 05/09/2022 |
| HUNT, ASHLEY | ALEXANDRIA, VA | - | Mental Health Counselor | 09/23/2026 |
| HUNT, CHRISTIE | DEDHAM, MA | - | Speech-Language Pathologist | 08/19/2026 |
| HUNT, CHRISTY | HARTFORD, MI | - | RBT | 09/24/2026 |
| HUNT, LINDA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| HUNTER SPRADLIN COUNSELING LLCORG | FORT SMITH, AR | - | Mental Health Counselor | 05/12/2026 |
| HUNTER, EMILY | WESTFIELD, IN | - | RBT | 02/11/2025 |
| HUNTER, JULIA | MADISON, WI | - | Speech-Language Pathologist | 09/22/2026 |
| HUNTER, MARELLA | HILLIARD, FL | BCBA | BCBA | 09/21/2026 |
| HUNTER, SHERITA | SALISBURY, NC | MA | Mental Health Counselor | 02/02/2011 |
| HURD, ALICE | FUQUAY VARINA, NC | - | RBT | 09/24/2026 |
| HUSAIN, BADEAH | BROOKLYN, NY | MENTAL HEALTH INTERN | Mental Health Counselor | 09/22/2026 |
| HUSBAND, MILTON | VALLEJO, CA | - | Counselor | 12/18/2007 |
| HUSSAIN, AALIA | SANTA CRUZ, CA | - | RBT | 09/25/2026 |
| HUSSEIN, FADUMO | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| HUSTON, ANNE | PARK RIDGE, IL | NCC, LPC, ALMFT | Mental Health Counselor | 09/21/2026 |
| HUSTON, JEREMY | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 06/24/2026 |
| HUSVAR, MADISON | CLINTON, NY | - | Case Manager/Care Coordinator | 09/21/2026 |
| HUTCHINGS, KAITLIN | CONCORD, NH | MS, LCMHC | Mental Health Counselor | 06/03/2016 |
| HUTCHINGS, PAUL | NASHVILLE, TN | LCSW | Clinical Social Worker | 12/21/2022 |
| HUTCHINS, KATIE | WINSTON SALEM, NC | - | BCBA | 10/16/2017 |
| HUTCHINS, SUE | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| HUTCHINSON-ZINTZUN, SARA | BELLINGHAM, WA | LICSW | Clinical Social Worker | 08/03/2017 |
| HUTCHINSON, JORDAN | DETROIT, MI | - | Case Manager/Care Coordinator | 09/21/2026 |
| HUTCHINSON, MELANCHE | WATERBURY, CT | LPC | Professional Counselor | 05/12/2020 |
| HUTCHISON, AUDREY | TUCSON, AZ | LAC | Mental Health Counselor | 08/24/2026 |
| HUTCHISON, JESSICA | DIXON, IL | - | Mental Health Counselor | 09/24/2026 |
| HUTTERER, MARISA | COON RAPIDS, MN | LICSW | Clinical Social Worker | 02/01/2021 |
| HUYNH, JULIE | GARDEN GROVE, CA | - | Speech-Language Pathologist | 02/03/2021 |
| HUYNH, TRACI | EVERETT, WA | LMHC | Mental Health Counselor | 01/31/2020 |
| HYATT, EMILY | SAINT JOSEPH, MO | - | Professional Counselor | 04/11/2025 |
| HYGIEIA BEHAVIORAL HEALTH FOUNDATION INC.ORG | LAKEWOOD, CA | - | Clinical Social Worker | 10/06/2023 |
| HYNES, SOPHIE | SOUTH BURLINGTON, VT | LCSW | Clinical Social Worker | 01/14/2026 |
| HYPERBARIC CENTERS OF SOUTHERN CALIFORNIAORG | ESCONDIDO, CA | - | Clinic/Center | 09/23/2026 |
| HYPES, JAN | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| I AM HOPE AGENCY LLCORG | DURHAM, NC | - | Community/Behavioral Health Agency | 07/09/2024 |
| I BELIV YOU MATTER 'LLC'ORG | KISSIMMEE, FL | - | BCBA | 04/19/2022 |
| I CARE FAMILY SERVICES LLCORG | AIKEN, SC | - | Mental Health Counselor | 06/13/2025 |
| IBARRA, EMILY | EL PASO, TX | - | RBT | 09/21/2026 |
| IBRAHEAM, MARIAN | LAKE ELSINORE, CA | - | Counselor | 07/03/2024 |
| ICONIC COUNSELING SERVICES, PPLCORG | FRANKFORT, IL | - | Addiction (Substance Use Disorder) Counselor | 09/26/2026 |
| IDA, KYLA | CIRCLEVILLE, OH | - | Mental Health Counselor | 06/21/2023 |
| IDEAL HEALTH CARE AND MEDICAL CLINIC, INC.ORG | LOS ANGELES, CA | - | Specialist | 06/04/2006 |
| IDG SWALLOW AND SPEECH PATHOLOGY PLLCORG | BROOKLYN, NY | - | Speech-Language Pathologist | 09/24/2026 |
| IFTIKHAR, RIJA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| IGNACIO, OLEGARIO | JEFFERSONVILLE, IN | MD | Specialist | 09/19/2005 |
| IHC HEALTH SERVICES, INC.ORG | ST GEORGE, UT | - | Psychologist | 09/22/2026 |
| IKONEN, PAUL | LAKE ORION, MI | LMSW | Clinical Social Worker | 09/24/2026 |
| IMAGE AND LIKENESS COUNSELING LLCORG | OVIEDO, FL | - | Mental Health Counselor | 10/11/2019 |
| IMINSKI, DAWN | MARINE CITY, MI | LLMSW | Clinical Social Worker | 07/01/2019 |
| IMPACT WELLNESS LLCORG | JACKSONVILLE, FL | - | Community/Behavioral Health Agency | 09/24/2026 |
| IMPERIAL VALLEY LGBT RESOURCE CENTER, INC.ORG | EL CENTRO, CA | - | Counselor | 09/23/2026 |
| IMRAN, AMEERA NISHAT | BOSTON, MA | - | Mental Health Counselor | 09/24/2026 |
| IN MARYS HANDS HOME HEALTH LLCORG | FLORISSANT, MO | - | Case Management Agency | 12/11/2024 |
| INCLAN-GARCIA, ADRIANNA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| INCONTROLORG | SAINT PAUL, MN | - | Community/Behavioral Health Agency | 09/24/2026 |
| INGRALDI, GENEVIEVE | LAFAYETTE, LA | MA, PLPC | Counselor | 09/22/2026 |
| INGRAM, CHRISTINE | OMAHA, NE | LIMHP | Mental Health Counselor | 09/15/2023 |
| INGRAM, JULIA | OKEMOS, MI | LPC | Mental Health Counselor | 06/10/2021 |
| INGRAM, MAGGIE | SEATTLE, WA | - | Counselor | 04/02/2018 |
| INNER GROWING COUNSELING & THERAPY PLLCORG | RIO GRANDE CITY, TX | - | Professional Counselor | 03/30/2026 |
| INNER PEACE LLCORG | CINCINNATI, OH | - | Community/Behavioral Health Agency | 09/22/2026 |
| INNER SOL WELLNESS CO., LLCORG | EAGLE RIVER, AK | - | Clinical Social Worker | 09/25/2026 |
| INNER-CIRCLE COMMUNITIESORG | COLUMBUS, OH | - | Clinical Social Worker | 10/14/2010 |
| INNERVENTURE COUNSELING LLCORG | GLENDALE, WI | - | Professional Counselor | 09/23/2026 |
| INOCENCIO, ROVIN ANGELIC | WALNUT CREEK, CA | - | RBT | 09/24/2026 |
| INSIGHT AND EMPOWERMENT, LLCORG | IDAHO FALLS, ID | - | Clinical Social Worker | 10/01/2020 |
| INSIGHT COUNSELING & COACHING SERVICEORG | ROCKVILLE, MD | - | Mental Health Counselor | 01/19/2026 |
| INSIGHTS TO ANXIETY LLCORG | KIRKWOOD, MO | - | Mental Health Counselor | 09/23/2026 |
| INTEGRAL COUNSELINGORG | PORTLAND, OR | - | Mental Health Counselor | 09/22/2026 |
| INTEGRATED SPECTRUM HEALTH LLCORG | RONAN, MT | - | Case Management Agency | 09/23/2026 |
| INTEGRATIVE LICENSED CLINICAL SOCIAL WORK PLLCORG | WADING RIVER, NY | - | Clinical Social Worker | 09/24/2026 |
| INTERCARE THERAPY, INC.ORG | LOS ANGELES, CA | - | BCBA | 05/04/2011 |
| INTERNATIONAL NEUROPSY CONSULTANTS, P.A.ORG | DALLAS, TX | - | Psychologist | 08/13/2014 |
| INTERNET SOLUTIONS LLCORG | STERLING, VA | - | Clinic/Center | 08/12/2026 |
| INTERVENTIONAL SPINE AND PAIN PHYSICIANS, PAORG | MAPLE GROVE, MN | - | Specialist | 09/14/2012 |
| INTRINSIC HEALINGORG | RIALTO, CA | - | Clinical Social Worker | 09/24/2026 |
| INVICTUS MENTAL HEALTH, PLLCORG | FORT WORTH, TX | - | Mental Health Counselor | 09/25/2026 |
| IRIZARRY SANTIAGO, JOSE | MANGONIA PARK, FL | LCSW | Clinical Social Worker | 06/13/2025 |
| IRVINE, PATRICK | KINGS MOUNTAIN, NC | - | Clinical Social Worker | 09/21/2026 |
| IRWIN COUNSELING SERVICE PLLCORG | JACKSON, MI | - | Mental Health Counselor | 07/28/2017 |
| IRWIN, CLINT | JACKSON, MI | MA LPC | Mental Health Counselor | 09/30/2010 |
| IRWIN, CRYSTAN | BIRMINGHAM, AL | LICSW | Clinical Social Worker | 01/31/2024 |
| IRWIN, MARCYAN | JACKSON, MI | MSW, LMSW | Clinical Social Worker | 02/24/2014 |
| ISAAC-DOHERTY, MICHELLE | SALT LAKE CITY, UT | LCSW | Clinical Social Worker | 06/11/2019 |
| ISAAC, CARMELA | OXNARD, CA | - | Clinical Social Worker | 11/06/2018 |
| ISBELL, STEPHANIE | MISSOULA, MT | COUNSELOR | Mental Health Counselor | 03/18/2020 |
| ISI MINISTRIESORG | KANSAS CITY, MO | - | Addiction (Substance Use Disorder) Counselor | 02/22/2019 |
| ISIDORO, GISELLE | HESPERIA, CA | - | RBT | 09/24/2026 |
| ISKANDER, NOORA | DEARBORN, MI | - | Case Manager/Care Coordinator | 07/05/2022 |
| ISKHAKOV, NAAMA | CHESAPEAKE, VA | LPP | Mental Health Counselor | 09/22/2026 |
| ISLER, LEAH | RIDGEWOOD, NJ | PSY.D. | Psychologist | 09/06/2015 |
| ISOLA, MARIA | BLOOMINGTON, MN | MSW, LICSW | Clinical Social Worker | 09/24/2026 |
| ISOM, VONTERIA | HOUSTON, TX | - | RBT | 09/21/2026 |
| ISON, BRITANIA | SUQUAMISH, WA | SUDP; LMFTA; LMHCA | Counselor | 03/27/2020 |
| ISSE, RAHIMA | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| IVANCIC, JESSICA | MERIDIAN, ID | MS, LCPC | Professional Counselor | 04/09/2019 |
| IVERSON, CLAIRE | CAMBRIDGE, MA | - | Clinical Social Worker | 09/23/2026 |
| IVERSON, MARSHAI | FRESNO, CA | - | Mental Health Counselor | 03/25/2013 |
| IVERY, ALEXANDRIA | DURANGO, CO | RBT | RBT | 09/24/2026 |
| IVEY-TURNER, TASIA | TUCSON, AZ | MA, LPC, CRC, NCC | Professional Counselor | 05/17/2022 |
| IVORY, MIKYYA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| IVY, MADISON | VENTURA, CA | - | RBT | 09/24/2026 |
| IZZO, IVANA | FARMINGTON, CT | BCBA, LBA | BCBA | 02/29/2024 |
| J&B HUMAN SERVICESORG | MIDDLEBORO, MA | - | Case Management Agency | 06/06/2026 |
| J&K GROWTHORG | CORNING, NY | - | Clinical Social Worker | 09/21/2026 |
| JABOUR, NED | MONROE, LA | PH.D., LPC | Professional Counselor | 10/05/2015 |
| JACINTO, JAMES | FRESNO, CA | - | Mental Health Counselor | 08/09/2019 |
| JACKS, CHRISTOPHER | ALTON, IL | MA, LPC | Professional Counselor | 05/29/2025 |
| JACKSON LABORATORY LLCORG | GREENWOOD, IN | - | Clinic/Center | 09/01/2026 |
| JACKSON, ALAN | SHREVEPORT, LA | - | Case Manager/Care Coordinator | 09/21/2026 |
| JACKSON, ALEXANDRIA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| JACKSON, ALEXIS | FUQUAY VARINA, NC | - | RBT | 09/24/2026 |
| JACKSON, ALNISHA | SAGINAW, MI | - | Clinical Social Worker | 09/21/2026 |
| JACKSON, ALVIN | DISTRICT HEIGHTS, MD | LPCC | Mental Health Counselor | 07/21/2017 |
| JACKSON, AMBER | COLUMBUS, OH | LPCC-S | Professional Counselor | 05/01/2018 |
| JACKSON, ANSLEY | CHARLESTON, SC | LISW-CP | Clinical Social Worker | 09/22/2026 |
| JACKSON, DIANE | COLUMBUS, OH | LSW | Clinical Social Worker | 09/12/2023 |
| JACKSON, GILLIAN | CORNELIUS, NC | - | Professional Counselor | 09/25/2026 |
| JACKSON, JADAE | ONTARIO, CA | - | RBT | 09/24/2026 |
| JACKSON, JESSICA | PHILADELPHIA, PA | - | BCBA | 09/25/2026 |
| JACKSON, JUANITA | ROUND ROCK, TX | MBA | Case Manager/Care Coordinator | 03/23/2018 |
| JACKSON, KATHERINE | GLASGOW, KY | - | RBT | 10/16/2025 |
| JACKSON, KATHRYN | CAMBRIDGE, MA | PH.D. | Psychologist | 03/25/2007 |
| JACKSON, KELLY | GALLOWAY, NJ | M.S. CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| JACKSON, KELLYE | DAYTON, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| JACKSON, LARISSA | OMAHA, NE | LADC | Addiction (Substance Use Disorder) Counselor | 09/03/2020 |
| JACKSON, LILLIANNE | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| JACKSON, MELISSA | WASHINGTON, DC | MINISTER/CSW | Counselor | 09/23/2026 |
| JACKSON, SAVANNAH | MOBILE, AL | MS, LPC, LCPC | Professional Counselor | 12/11/2018 |
| JACKSON, SHONIECE | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| JACKSON, TATIANNA | CHULA VISTA, CA | - | RBT | 09/21/2026 |
| JACKSON, TAYLOR | GREELEY, CO | LPCC | Professional Counselor | 04/06/2026 |
| JACOBO, DIANA | SANTA PAULA, CA | - | Day Training/Habilitation Specialist | 06/23/2025 |
| JACOBO, GLADYS | OXNARD, CA | - | Case Manager/Care Coordinator | 04/13/2020 |
| JACOBS, ALEXYS | SPOKANE VALLEY, WA | CBT | RBT | 04/10/2024 |
| JACOBS, DANIELLE | WEST PALM BEACH, FL | - | RBT | 09/22/2026 |
| JACOBS, MELISSA | PONTIAC, MI | CMA | RBT | 09/23/2026 |
| JACOBS, PARKER | ST PETERSBURG, FL | MS | Mental Health Counselor | 06/19/2024 |
| JACOBSON, MIRJAM | OVERLAND PARK, KS | - | Professional Counselor | 09/21/2026 |
| JAIME, CYNTHIA | NEW LENOX, IL | - | Speech-Language Pathologist | 09/22/2026 |
| JAIME, MARIA | COLORADO SPRINGS, CO | COUNSELOR | Counselor | 09/25/2026 |
| JAIME, NAYELI | RIVERBANK, CA | - | RBT | 09/21/2026 |
| JAKOBSON, HARRY | CHICO, CA | LCSW | Clinical Social Worker | 09/01/2011 |
| JAMALEDDINE, MAYA | BURLINGTON, VT | MS | Mental Health Counselor | 11/06/2025 |
| JAMBOR-MAY, ISAAC | EDEN PRAIRIE, MN | - | RBT | 09/21/2026 |
| JAMBUNATHAN, DURGA | BROOKLYN, NY | LMHC | Mental Health Counselor | 08/30/2024 |
| JAMERSON, THERESA | MCKINNEY, TX | M.A. LPC-S | Professional Counselor | 07/31/2007 |
| JAMES, CAMERON | INDIANAPOLIS, IN | LCSW | Clinical Social Worker | 06/17/2024 |
| JAMES, MARIE | BUFFALO, NY | - | RBT | 09/25/2026 |
| JAMES, QUINTINA | MENIFEE, CA | - | RBT | 09/22/2026 |
| JAMES, RILDA | MANSFIELD, OH | - | RBT | 09/24/2026 |
| JAMES, TALIA | HOUSTON, TX | - | RBT | 07/29/2026 |
| JAMES, VICTORIA | HANNIBAL, MO | BCBA | BCBA | 09/21/2026 |
| JAMIR, TSUWAINLA | SLIDELL, LA | LPC | Mental Health Counselor | 09/25/2026 |
| JAMISON, ROSEMARY | FOLSOM, CA | LCSW | Clinical Social Worker | 07/01/2022 |
| JAN ULRICH MSW LLCORG | ANN ARBOR, MI | - | Clinical Social Worker | 03/07/2020 |
| JANDA-ORR COUNSELINGORG | BRIGHTON, MI | - | Professional Counselor | 01/06/2026 |
| JANES, CASEY | ROLLINGWOOD, TX | MA LCSW-S | Clinical Social Worker | 11/28/2022 |
| JANICEK, MARGARET | NEW YORK, NY | - | Speech-Language Pathologist | 09/24/2026 |
| JANKA, EMILY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| JANNER, KATHERINE | WICHITA, KS | - | RBT | 09/24/2026 |
| JANSKY, ZURIEL | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| JANUS INTERVENTIONS, LLCORG | GLENSIDE, PA | - | BCBA | 05/20/2024 |
| JAQUESS-WARE, LURA | PAWHUSKA, OK | LCSW | Clinical Social Worker | 12/04/2007 |
| JARA-CHAIDEZ, LYNETTE | COVINA, CA | - | RBT | 05/31/2023 |
| JARABA, LENTNER | GREENSBORO, NC | LCSWA | Clinical Social Worker | 09/24/2026 |
| JARAMILLO OLEA, MARGARITA | PLACENTIA, CA | - | RBT | 09/23/2026 |
| JARMAN, ABIGAIL | SAINT LOUIS, MO | RBT | RBT | 09/23/2026 |
| JARMON, DORIAN | CYPRESS, TX | RBT | RBT | 09/24/2026 |
| JASPER, LEE | BERKELEY, CA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| JASPERSON, ALIA | ABERDEEN, SD | LBSW | Clinical Social Worker | 12/13/2021 |
| JASSO, ELIJAHBEN | BILLINGS, MT | LCPC, NCC | Professional Counselor | 01/01/2025 |
| JAX BEHAVIORAL HEALTH, LLPCORG | MEMPHIS, TN | - | BCBA | 07/13/2021 |
| JAYME, JULIETTE | FREMONT, CA | APCC, PPSC | RBT | 03/11/2019 |
| JEAN, BIANCA | ORLANDO, FL | - | RBT | 09/21/2026 |
| JEAN, JACSONN | LEOMINSTER, MA | BA | Case Manager/Care Coordinator | 09/25/2026 |
| JEAN, KAYLA | TEMECULA, CA | - | RBT | 09/22/2026 |
| JEANTY, NATASHA | PHILADELPHIA, PA | LPC | Mental Health Counselor | 08/01/2026 |
| JEDNAK, AMANDA | PLYMOUTH, MA | - | Clinical Social Worker | 09/21/2026 |
| JEFF MAZZONE COUNSELING & SERVICES, LLCORG | FREDERICKSBURG, VA | - | Counselor | 09/23/2026 |
| JEFFCOAT, JENNIFER | SANTA CRUZ, CA | CST, PPN-P, PPN-E | Specialist | 06/11/2012 |
| JEFFERIES, KAMRYN | SAN ANTONIO, TX | - | BCBA | 11/04/2025 |
| JEHLE, TYLER | BRENTWOOD, NY | LMSW | Clinical Social Worker | 09/24/2026 |
| JEMERSON, DEJIAH | CONWAY, AR | - | RBT | 09/24/2026 |
| JENDRO, JENNIFER | SAINT PAUL, MN | LICSW | Clinical Social Worker | 09/14/2006 |
| JENKINS, AIRYAN | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| JENKINS, MICAHIAH KEYONNA | BELLEVUE, WA | - | RBT | 08/17/2026 |
| JENKINS, TAMIKA | YOUNGSTOWN, OH | - | Clinical Social Worker | 10/25/2023 |
| JENKINS, TRYPHENA | SHREVEPORT, LA | LCSW | Clinical Social Worker | 01/12/2012 |
| JENNIFER JOST THERAPY SERVICES PLLCORG | SEATTLE, WA | - | Community/Behavioral Health Agency | 09/23/2026 |
| JENNINGS, ANNE | NEW YORK, NY | LMSW | Clinical Social Worker | 09/24/2026 |
| JENNINGS, DAWN | SOUTH BEND, IN | - | Addiction (Substance Use Disorder) Counselor | 09/26/2026 |
| JENSEN, ERIN | LORAIN, OH | - | Speech-Language Pathologist | 02/12/2024 |
| JENSEN, MARGARET | ORLAND PARK, IL | LCSW | Clinical Social Worker | 04/30/2026 |
| JERGENS, SARA | DAYTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| JERNIGAN, EMMA | FOUR OAKS, NC | LCSWA | Clinical Social Worker | 09/23/2026 |
| JEROME, KIRA | TACOMA, WA | - | Counselor | 09/19/2022 |
| JERRY, RACHEL | SAN DIEGO, CA | - | RBT | 09/22/2026 |
| JESSE SUNSHINE LLCORG | AURORA, CO | - | Clinical Social Worker | 09/25/2026 |
| JESSICA GLENN THERAPY PLLCORG | WEST CHESTER, PA | - | Clinical Social Worker | 04/02/2019 |
| JEWELL, ALEXANDER | WAYNE, MI | - | Case Manager/Care Coordinator | 09/21/2026 |
| JHP CLINICAL CONSULTING SERVICES LLCORG | NORTH ADAMS, MA | - | Mental Health Counselor | 09/23/2026 |
| JIA, YI | LOS ANGELES, CA | - | RBT | 09/24/2026 |
| JIMENEZ LOPEZ, LUCY | SAN RAMON, CA | - | RBT | 09/23/2026 |
| JIMENEZ, ALEXA | NORTH HILLS, CA | - | BCBA | 09/21/2026 |
| JIMENEZ, BIANCA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| JIMENEZ, CHE | HAYWARD, CA | - | RBT | 09/10/2026 |
| JIMENEZ, NOELLE | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| JIMENEZ, SAMANTHA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| JIMENEZ, SCARLET | DOWNEY, CA | - | RBT | 09/24/2026 |
| JIMENEZ, TRINA | RUIDOSO DOWNS, NM | - | Case Manager/Care Coordinator | 09/25/2026 |
| JIMOH, TOLUWAN | SPRINGFIELD, IL | - | RBT | 09/22/2026 |
| JIN, JENNY | MONTEREY PARK, CA | - | Professional Counselor | 07/20/2022 |
| JIRELE, ABRIELLE | WACONIA, MN | - | Speech-Language Pathologist | 09/24/2026 |
| JK CARE SUPPLIES LLCORG | BROOKLYN, NY | - | Mental Health Counselor | 09/21/2026 |
| JMR MENTAL HEALTH, LLCORG | GAMBRILLS, MD | - | Clinical Social Worker | 11/01/2024 |
| JOEL T PECK COUNSELING LLCORG | ROCKY HILL, CT | - | Professional Counselor | 05/19/2026 |
| JOHN MATHEWS LCSW, LLCORG | MIDLOTHIAN, VA | - | Clinical Social Worker | 10/14/2015 |
| JOHN RAPP, LCSW, LLCORG | CLAYTON, MO | - | Clinical Social Worker | 04/02/2020 |
| JOHN, JISA | ELK GROVE, CA | - | Speech-Language Pathologist | 09/24/2026 |
| JOHN, KATHERINE | EL PASO, TX | LPC | Professional Counselor | 09/23/2026 |
| JOHNER, TINA | MINOT, ND | LBSW | Case Manager/Care Coordinator | 09/25/2026 |
| JOHNSON-KING, MARQUESE | OXON HILL, MD | - | Mental Health Counselor | 09/22/2026 |
| JOHNSON, ALEXIA | FORT WORTH, TX | NCC, LPC-ASSOCIATE | Mental Health Counselor | 09/23/2026 |
| JOHNSON, ALICIA | FARMINGTON HILLS, MI | - | RBT | 09/24/2026 |
| JOHNSON, ANNAKAY | CORAL SPRINGS, FL | - | Psychologist | 09/21/2026 |
| JOHNSON, ARMA | GARY, IN | MSW LCSW ACSW | Clinical Social Worker | 07/17/2006 |
| JOHNSON, ASHLEE | FARMINGTON, UT | ACMHC | Mental Health Counselor | 09/22/2026 |
| JOHNSON, AVIS | NEW ORLEANS, LA | - | Case Manager/Care Coordinator | 03/10/2022 |
| JOHNSON, BRIDGETT | BEAUMONT, TX | - | Community/Behavioral Health Agency | 09/23/2026 |
| JOHNSON, CARLYN | BELLEVUE, WA | - | BCBA | 03/19/2025 |
| JOHNSON, CARNELL | STOCKTON, CA | - | RBT | 09/21/2026 |
| JOHNSON, CHAE | NEWPORT BEACH, CA | - | RBT | 09/23/2026 |
| JOHNSON, CHAVITA | SAGINAW, MI | - | RBT | 09/25/2026 |
| JOHNSON, CHRISTINE | PINE CITY, MN | PSYD LP | Psychologist | 02/07/2007 |
| JOHNSON, DAPHNE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| JOHNSON, DEBORAH | WESTAMPTON, NJ | - | Mental Health Counselor | 12/01/2025 |
| JOHNSON, EBONY | AURORA, CO | LAC, LSW CFPS | Addiction (Substance Use Disorder) Counselor | 01/06/2023 |
| JOHNSON, ELIZABETH | ROSEVILLE, MN | - | RBT | 09/23/2026 |
| JOHNSON, ERICA | CARUTHERSVILLE, MO | - | Case Manager/Care Coordinator | 09/23/2026 |
| JOHNSON, GRACIE | MELBOURNE, FL | - | RBT | 08/25/2026 |
| JOHNSON, HANNAH | GREENWOOD, IN | - | BCBA | 01/15/2025 |
| JOHNSON, HEIDI | SPRINGFIELD, IL | - | Mental Health Counselor | 06/11/2026 |
| JOHNSON, HOLLY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| JOHNSON, JAIDYN | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| JOHNSON, JAIME | VAN NUYS, CA | - | RBT | 09/24/2026 |
| JOHNSON, KACIE | CAROL STREAM, IL | - | Mental Health Counselor | 09/22/2026 |
| JOHNSON, KAREN | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 11/05/2019 |
| JOHNSON, KATELYN | PITTSBURG, KS | - | RBT | 09/22/2026 |
| JOHNSON, KATHERINE | COBURG, OR | CADC II, QMHA II, CR | Addiction (Substance Use Disorder) Counselor | 09/20/2021 |
| JOHNSON, KAYLI | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| JOHNSON, KELSEY | PARKERSBURG, WV | - | Case Manager/Care Coordinator | 09/23/2026 |
| JOHNSON, KENNEDY | ROSEMOUNT, MN | MS CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| JOHNSON, KRISTINA | LOUISA, KY | - | Mental Health Counselor | 09/24/2012 |
| JOHNSON, KYLE | LINCOLNWOOD, IL | - | RBT | 09/22/2026 |
| JOHNSON, LEAH | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| JOHNSON, LESCENIA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| JOHNSON, LINDA | SAN MATEO, CA | LMFT, LAADC | Addiction (Substance Use Disorder) Counselor | 03/21/2007 |
| JOHNSON, LINDSAY | PLYMOUTH, MN | MA | Psychologist | 05/07/2021 |
| JOHNSON, LINDSAY | JUSTIN, TX | MS, CCC-SLP | Speech-Language Pathologist | 06/23/2015 |
| JOHNSON, LISA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| JOHNSON, LOGAN | JEFFERSONVILLE, IN | - | RBT | 09/25/2026 |
| JOHNSON, MACY | VERNAL, UT | - | Case Manager/Care Coordinator | 08/13/2026 |
| JOHNSON, MADISON | JUNCTION CITY, OR | - | Mental Health Counselor | 09/21/2026 |
| JOHNSON, MADISON | PLAINWELL, MI | - | Clinical Social Worker | 09/25/2026 |
| JOHNSON, MARVIN | THE WOODLANDS, TX | - | RBT | 09/21/2026 |
| JOHNSON, MARY | ALBUQUERQUE, NM | - | RBT | 09/23/2026 |
| JOHNSON, MELISSA | STUDIO CITY, CA | LCSW | Clinical Social Worker | 06/15/2018 |
| JOHNSON, MICAH | FAIRFIELD, CA | - | RBT | 03/23/2026 |
| JOHNSON, MICHELLE | EVANSTON, IL | LCPC | Professional Counselor | 07/25/2018 |
| JOHNSON, MONTRELE | AURORA, CO | QBHA | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| JOHNSON, NANCY | LOUISVILLE, KY | MSW, LCSW | Clinical Social Worker | 05/23/2022 |
| JOHNSON, NICHOLAS | TAHLEQUAH, OK | - | Case Manager/Care Coordinator | 09/21/2026 |
| JOHNSON, PAMELA | JUPITER, FL | LCSW | BCBA | 05/24/2013 |
| JOHNSON, PORSHA | MONTGOMERY, AL | LPC | Mental Health Counselor | 07/11/2023 |
| JOHNSON, SANDI | ARLINGTON, TX | LPC | Mental Health Counselor | 03/11/2024 |
| JOHNSON, SANIECE | CHARDON, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| JOHNSON, SAVANNAH | KOKOMO, IN | MA | RBT | 08/19/2020 |
| JOHNSON, SHANELL | NEW ORLEANS, LA | - | RBT | 09/22/2026 |
| JOHNSON, SHERI | FORT LAUDERDALE, FL | RSW, CHT, LCSW | Mental Health Counselor | 08/11/2026 |
| JOHNSON, SHERMAN | OKLAHOMA CITY, OK | C.R.C, LPC | Mental Health Counselor | 10/15/2007 |
| JOHNSON, STEPHANIE | ESCANABA, MI | - | Speech-Language Pathologist | 09/24/2026 |
| JOHNSON, SUZETTE | GAINESVILLE, FL | M.D. | Specialist | 10/23/2006 |
| JOHNSON, SYDNEY | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| JOHNSON, TAYLOR | NEW LENOX, IL | LPC | Mental Health Counselor | 09/23/2026 |
| JOHNSON, TIFFANY | ELKVIEW, WV | - | Counselor | 07/10/2026 |
| JOHNSON, TRACY | FREDERICKSBURG, VA | LPC | Mental Health Counselor | 09/22/2026 |
| JOHNSON, TRACY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| JOHNSTON, EMILY | BIRMINGHAM, AL | - | Counselor | 01/12/2024 |
| JOHNSTON, KACI | WICKENBURG, AZ | LCSW | Clinical Social Worker | 09/21/2026 |
| JOHNSTON, MARY | SAN DIEGO, CA | - | RBT | 02/26/2024 |
| JOHOU TCHAFA, CHRISTELLE LARISSA | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 10/25/2024 |
| JOINER, ALANA | WINDSOR, CT | - | RBT | 09/23/2026 |
| JOKUMSEN STEINLE, JADA | SAINT JAMES, MN | M.A., CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| JOLLY, KELLY | DURHAM, NC | BS, MA, QP | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| JON SHERMAN COUNSELING AND CONSULTATION SERVICES, LLC.ORG | COLUMBUS, OH | - | Clinical Social Worker | 09/25/2026 |
| JONAH O FINCH INCORPORATEDORG | SANDY, UT | - | Mental Health Counselor | 09/23/2026 |
| JONES-SIMPSON, AMANDA | COLUMBUS, OH | LPC | Mental Health Counselor | 09/22/2026 |
| JONES, ALANA | PHENIX CITY, AL | RD | Case Management Agency | 06/27/2019 |
| JONES, ANAYA | TORRANCE, CA | - | RBT | 09/21/2026 |
| JONES, ANGELA | EVANSTON, IL | - | Clinical Social Worker | 09/23/2026 |
| JONES, BRIANA | FORT WORTH, TX | - | Mental Health Counselor | 09/22/2026 |
| JONES, BRITTANY | CLEMENTON, NJ | - | Counselor | 09/23/2026 |
| JONES, CANDY | WESTAMPTON, NJ | - | Mental Health Counselor | 09/22/2026 |
| JONES, CATALENA | ORANGE, CA | - | RBT | 09/22/2026 |
| JONES, CIERRA | REYNOLDSBURG, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| JONES, COURTNEY | ASHLAND, KY | LCSW | Clinical Social Worker | 02/23/2017 |
| JONES, DANAVIAN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| JONES, ETHAN | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| JONES, GENEVIEVE | ATLANTA, GA | - | BCBA | 09/23/2021 |
| JONES, ISAIAH | TAKOMA PARK, MD | - | Psychologist | 09/25/2026 |
| JONES, JANEE | HICKSVILLE, NY | - | Case Manager/Care Coordinator | 09/22/2026 |
| JONES, JASMINE | CONCORD, CA | - | RBT | 09/24/2026 |
| JONES, JEFFREY | DAYVILLE, CT | LCSW | Clinical Social Worker | 09/19/2015 |
| JONES, KARISSA | GILBERT, AZ | - | RBT | 12/13/2019 |
| JONES, KHYIANA | NEWARK, NJ | - | RBT | 09/24/2026 |
| JONES, KIARA | FAYETTEVILLE, AR | - | RBT | 09/25/2026 |
| JONES, KRYSTAL | MIDLAND, TX | LCSW | Clinical Social Worker | 09/22/2026 |
| JONES, LINDSAY | LAKE CHARLES, LA | LPC | Professional Counselor | 11/16/2024 |
| JONES, LISA | WAYLAND, MI | - | Speech-Language Pathologist | 09/24/2026 |
| JONES, MADISON | PORTLAND, OR | QMPH-R | Mental Health Counselor | 06/19/2025 |
| JONES, MARTIANNA | BATON ROUGE, LA | - | Counselor | 01/16/2025 |
| JONES, MICHELLE | BEXLEY, OH | - | BCBA | 09/24/2026 |
| JONES, MYKELL | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| JONES, OLIVIA | CHARLOTTE, NC | - | Clinical Social Worker | 06/19/2025 |
| JONES, PACOYA | SAN ANTONIO, TX | - | RBT | 09/25/2026 |
| JONES, PAULA | PRESTONSBURG, KY | - | Case Manager/Care Coordinator | 09/24/2026 |
| JONES, RICCARDO | EDGEWATER, MD | - | Professional Counselor | 09/23/2026 |
| JONES, RODESSA | CHICAGO, IL | - | RBT | 08/11/2026 |
| JONES, RONAN | AUBURN, WA | - | Counselor | 09/18/2026 |
| JONES, SHARON | CHARLOTTE, NC | - | RBT | 09/22/2026 |
| JONES, TAJA | METAIRIE, LA | - | RBT | 09/24/2026 |
| JONES, TAYLOR | INDIANAPOLIS, IN | - | RBT | 09/21/2026 |
| JONES, TYRA | DUNMORE, PA | BS | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| JONES, TYREK | CONWAY, AR | - | RBT | 09/21/2026 |
| JONES, WAYNE | WILLOWBROOK, IL | LCPC, MA | Professional Counselor | 04/19/2008 |
| JONES, YAKIRA | DANVILLE, VA | - | RBT | 09/25/2026 |
| JORDAN, DOMINIC | GLEN BURNIE, MD | - | RBT | 09/24/2026 |
| JORDAN, HALLY | FAIRBANKS, AK | M.ED. ALC | Mental Health Counselor | 09/23/2026 |
| JORDAN, JOSEPH | JACKSON, MS | MA, LPC | Mental Health Counselor | 09/21/2026 |
| JORDAN, LYNN | ALPENA, MI | - | RBT | 09/21/2026 |
| JORDAN, MELANIE | VISALIA, CA | - | Speech-Language Pathologist | 02/25/2020 |
| JORDAN, RACHEL | AMERICAN FORK, UT | - | RBT | 09/21/2026 |
| JORIANTO, FANNY | CONCORD, CA | - | RBT | 09/21/2026 |
| JORRO, CLAUDIA | PALM BAY, FL | RBT | RBT | 09/21/2026 |
| JOSEPH, ABDUL | MIRAMAR, FL | - | RBT | 09/21/2026 |
| JOSEPH, KRISTA | FAIRFIELD, OH | - | Clinical Social Worker | 10/05/2017 |
| JOSEPH, TRINITY | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| JOSEPH, TYRONE | WHITE PLAINS, NY | - | Specialist | 11/03/2021 |
| JOURNEY BOUND COUNSELING LLCORG | PORT ANGELES, WA | - | Community/Behavioral Health Agency | 08/08/2022 |
| JOURNEY, JAY | ONTARIO, CA | - | RBT | 09/25/2026 |
| JOURNEYS & REFLECTIONS LLCORG | UNIVERSAL CITY, TX | - | Professional Counselor | 03/18/2026 |
| JOVONOVICH, LESLIE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| JOYNER, ALIYYAH | WASHINGTON, DC | - | RBT | 08/31/2020 |
| JOYNER, SUSAN | PIEDMONT, SC | LCSW-C, LCSW | Clinical Social Worker | 05/15/2020 |
| JSPC, INCORG | REDDING, CA | - | Addiction (Substance Use Disorder) Counselor | 09/10/2026 |
| JUAREZ, ASHLEY | HOUSTON, TX | - | RBT | 09/21/2026 |
| JUAREZ, ASHLEY | MATTHEWS, NC | - | RBT | 09/23/2026 |
| JUAREZ, BERNARDO | HONOLULU, HI | - | RBT | 09/22/2026 |
| JUAREZ, EVELYN | GARDEN GROVE, CA | - | RBT | 09/21/2026 |
| JUBILANCE BEHAVIORAL SERVICES LLCORG | SANTA ROSA, CA | - | BCBA | 09/22/2026 |
| JUDGE, JENNIFER | LATHAM, NY | PSY.D, | Psychologist | 01/12/2011 |
| JUDKINS, MARY | SARASOTA, FL | M.S., CCC-SLP | Speech-Language Pathologist | 03/27/2007 |
| JUDY, TERESA | MONROE, NC | MA | Mental Health Counselor | 04/11/2023 |
| JUELICH, CARLY | ARDEN HILLS, MN | - | RBT | 08/25/2020 |
| JUNCAJ, AURRELA | IRVINGTON, NY | - | Speech-Language Pathologist | 09/21/2026 |
| JUNQUERA MARTINEZ, YURIEL | WEST PALM BEACH, FL | - | RBT | 09/24/2026 |
| JUPITER THERAPY LLCORG | RIVIERA BEACH, FL | - | BCBA | 09/21/2026 |
| JURCZYK, TORI | DAYTON, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| JUST IN TIME HOME CARE SERVICES, LLCORG | CHARLOTTE, NC | - | Community/Behavioral Health Agency | 09/10/2024 |
| JUSTICE, LAUREN | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| K BRYANT ENTERPRISES, LLCORG | LAS VEGAS, NV | - | Case Management Agency | 02/03/2025 |
| KABIR, AZIMUL | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/23/2026 |
| KABLER, NICOLE | NAPERVILLE, IL | - | Professional Counselor | 04/17/2026 |
| KAGAN, ERICA | NEW YORK, NY | LCSW | Clinical Social Worker | 07/27/2022 |
| KAHANAOI-NICHOLS, ANELA-LANI | KAPOLEI, HI | - | Mental Health Counselor | 01/21/2021 |
| KAHN, MARGOT | AURORA, CO | LCSW | Clinical Social Worker | 04/12/2023 |
| KAHR, ASHLEY | LAS VEGAS, NV | LCPC | Mental Health Counselor | 10/06/2022 |
| KAHUKU MEDICAL CENTERORG | KAHUKU, HI | - | Specialist | 11/16/2007 |
| KAILEY OGRADY SPEECH PATHOLOGIST PCORG | ROCKAWAY PARK, NY | - | Speech-Language Pathologist | 09/24/2026 |
| KAIROS WELLNESS CENTER, LTDORG | FAIRLAWN, OH | - | Mental Health Counselor | 10/26/2023 |
| KAIZEN COUNSELING LLCORG | GREENSBURG, PA | - | Mental Health Counselor | 09/21/2026 |
| KAIZEN HEALTH VIRGINIA LLCORG | RICHMOND, VA | - | Community/Behavioral Health Agency | 09/14/2026 |
| KALANTARPOUR, SABA | CHICAGO, IL | LCPC | Professional Counselor | 07/30/2022 |
| KALISETTI, AARYA | HAYWARD, CA | - | RBT | 09/25/2026 |
| KALUZA-MURPHY, DANIELLE | PHILADELPHIA, PA | - | Speech-Language Pathologist | 09/26/2019 |
| KAMANDPLLCORG | STERLING, VA | - | Clinic/Center | 06/02/2026 |
| KAMMA, TRAPHINA | JESSUP, MD | - | Case Manager/Care Coordinator | 09/21/2026 |
| KAMP, ALYSSA | KANSAS CITY, MO | MS, CCC-SLP | Speech-Language Pathologist | 07/02/2019 |
| KAMPFF, LAUREN | CHANDLER, AZ | BCBA | BCBA | 11/27/2012 |
| KANE, KEVIN | LOUISVILLE, KY | MD | Counselor | 02/26/2010 |
| KANJ, RAMI | SACRAMENTO, CA | - | RBT | 09/23/2026 |
| KANSAS CITY PSYCHOLOGY, LLCORG | KANSAS CITY, MO | - | Mental Health Counselor | 01/29/2025 |
| KANSAS DIRECTIONS LLCORG | SALINA, KS | - | Professional Counselor | 09/27/2024 |
| KANTER, RANDY | GLENVIEW, IL | L. CSW. | Clinical Social Worker | 08/29/2006 |
| KAPAPI, AMNAZO | FRISCO, TX | - | RBT | 09/23/2026 |
| KAPINOS, TIGRAN | GAITHERSBURG, MD | LCPC | Mental Health Counselor | 01/03/2023 |
| KAPLAN, A.B. | SANDY SPRINGS, GA | M.S., NCC, LPC | Professional Counselor | 05/24/2007 |
| KAPLAN, NICOLE | OXFORD, MI | LLC | Mental Health Counselor | 09/22/2026 |
| KAPLER, MELISSA | SHULLSBURG, WI | M.A., CCC-SLP | Speech-Language Pathologist | 01/06/2022 |
| KAPP, KRISTLE | GRANITE CITY, IL | LCPC | Professional Counselor | 06/14/2016 |
| KAPPES, KENADI | CLINTON, IA | - | RBT | 09/23/2026 |
| KAPSCH, MACKENZIE | NORTHFIELD, MN | MA, LPCC | Professional Counselor | 10/22/2021 |
| KARAM, EMMA KARAM | SYRACUSE, NY | - | Speech-Language Pathologist | 09/22/2026 |
| KARAPETYAN, SIPAN | SANTA CLARITA, CA | - | RBT | 09/21/2026 |
| KARAS, CHRISTINA | MIDDLEBURY, CT | LCSW | Clinical Social Worker | 10/25/2022 |
| KARIMI, LAINEE | PHOENIX, AZ | MED, BCBA, LBA | BCBA | 02/03/2026 |
| KASIM, ARBELLA | PHOENIX, AZ | - | RBT | 09/21/2026 |
| KASTILAHN, BRANDY | NEW BERN, NC | LCSW-A | Clinical Social Worker | 09/21/2026 |
| KATHY JORDAN COUNSELING & PLAY THERAPY PLLCORG | FORT COLLINS, CO | - | Mental Health Counselor | 09/19/2025 |
| KAUFMAN, CASEY | BLUE ASH, OH | MA, LPC, NCC | Mental Health Counselor | 05/27/2026 |
| KAUFMAN, NATALIE | HENDERSON, NV | MS, CPC, LADC, NCC | Addiction (Substance Use Disorder) Counselor | 06/28/2011 |
| KAUFMAN, NICOLE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| KAUFMAN, TAUBE | RALEIGH, NC | MSW, LMFT, LCSW, BCD | Clinical Social Worker | 05/22/2007 |
| KAUP, HANNAH | ANN ARBOR, MI | - | Psychologist | 09/23/2026 |
| KAUR, BALWIN | SACRAMENTO, CA | - | RBT | 09/25/2026 |
| KAUR, HANDESH | SAN JOSE, CA | - | Speech-Language Pathologist | 08/12/2026 |
| KAUR, SATWANT | LANHAM, MD | - | Community/Behavioral Health Agency | 09/22/2026 |
| KAVANAUGH, KERRY ANN | HOMESTEAD, FL | BA, RBT | BCBA | 09/16/2013 |
| KAY BLANKENSHIP COUNSELING & WELLNESS, PLLCORG | EUREKA, IL | - | Professional Counselor | 09/21/2026 |
| KAY, JENNIFER | COLDWATER, KS | LPC | Counselor | 09/24/2026 |
| KAY, SASHA | GRAND RAPIDS, MI | BCBA | BCBA | 11/06/2017 |
| KAYL, ALLISON | THORNTON, CO | LPC | Professional Counselor | 03/07/2023 |
| KAYS, ARON | INDIANAPOLIS, IN | RBT | RBT | 03/10/2025 |
| KAYS, LAUREN | WESTFIELD, IN | - | RBT | 09/21/2026 |
| KAZANDJIAN, JESSICA | TUCSON, AZ | LCSW | Clinical Social Worker | 09/23/2026 |
| KEARNEY, KATHERINE | MILFORD, CT | - | Speech-Language Pathologist | 09/23/2026 |
| KEARNEY, LORANN | SCHENECTADY, NY | - | Clinical Social Worker | 09/11/2023 |
| KEARNS, DALAWNA | AUGUSTA, KY | - | RBT | 09/22/2026 |
| KEATING, JENNIFER | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| KECKEISEN, ASHLEY | COLORADO SPRINGS, CO | - | Professional Counselor | 06/04/2021 |
| KEEFE, MARY E. | JACKSON, NJ | - | BCBA | 09/09/2026 |
| KEEFER, ALLISON | MAUMEE, OH | LISW-S | Clinical Social Worker | 08/30/2011 |
| KEELER, SARA | BEDFORD, MA | - | RBT | 08/01/2018 |
| KEENE, HOLLY | MARTINEZ, CA | - | Clinical Social Worker | 09/04/2018 |
| KEENZE, LACEY | LAFAYETTE, LA | LCSW BACS | Clinical Social Worker | 08/26/2011 |
| KEESEE, ALLISON | DANVILLE, VA | - | RBT | 09/25/2026 |
| KEETER, KIMBERLY | TULSA, OK | LCSW | Clinical Social Worker | 03/17/2006 |
| KEFAUVER, GAELAN | TAOS, NM | - | RBT | 09/24/2026 |
| KEITH, ERICCA | SICKLERVILLE, NJ | LCSW | Clinical Social Worker | 12/01/2023 |
| KEITH, PETER | PIKESVILLE, MD | LCPC | Professional Counselor | 08/12/2019 |
| KEITH, THOMAS | ROSELLE PARK, NJ | - | BCBA | 09/25/2026 |
| KEITHAHN, NIKITA | ROCKLEDGE, FL | - | RBT | 09/22/2026 |
| KEKICH, MEGAN | MATTHEWS, NC | - | Addiction (Substance Use Disorder) Counselor | 02/01/2017 |
| KELL, DANIEL | CHUBBUCK, ID | LMSW | Clinical Social Worker | 09/22/2026 |
| KELLAR, JAYLEE | COLORADO SPRINGS, CO | - | RBT | 06/02/2021 |
| KELLAS, NICOLE | HEPPNER, OR | - | Mental Health Counselor | 09/25/2026 |
| KELLAS, SYDNEY | OKLAHOMA CITY, OK | SLP | Speech-Language Pathologist | 06/08/2023 |
| KELLENBERGER, RUMICKO | SAN JACINTO, CA | - | Professional Counselor | 02/08/2022 |
| KELLER, ALYSSA | FARGO, ND | - | Specialist | 11/04/2020 |
| KELLER, ERIC | SEASIDE, OR | - | Addiction (Substance Use Disorder) Counselor | 07/09/2008 |
| KELLER, ROXANA | EAST STROUDSBURG, PA | - | BCBA | 09/24/2026 |
| KELLERMAN, ALISON | MANCHESTER, NH | - | Mental Health Counselor | 01/24/2025 |
| KELLESVIG, CLAIRE | MADISON, WI | LPC-IT | Mental Health Counselor | 09/24/2026 |
| KELLEY, JAZMINE | INDIANAPOLIS, IN | - | RBT | 09/21/2026 |
| KELLEY, LEAH | TERRE HAUTE, IN | - | RBT | 04/03/2023 |
| KELLEY, MARIANNE | ST PAUL, MN | PSYD LP | Psychologist | 04/22/2006 |
| KELLEY, SAVANNAH | KANSAS CITY, MO | - | RBT | 09/23/2026 |
| KELLY JO BOWLES PLLCORG | FOREST, VA | - | Clinical Social Worker | 10/16/2018 |
| KELLY, DAVID | PLYMOUTH, MA | - | Case Manager/Care Coordinator | 09/22/2026 |
| KELLY, EDNA | MOORE, OK | LPC - CANDIDATE | Counselor | 03/28/2013 |
| KELLY, INDIA | DALLAS, TX | - | Clinical Social Worker | 12/24/2017 |
| KELLY, JACQUELINE | HOUSTON, TX | - | RBT | 09/21/2026 |
| KELLY, KAYLA | MARCO ISLAND, FL | - | RBT | 09/21/2026 |
| KELLY, MELISSA | OCEAN BREEZE, FL | MA,CCC-SLP | Speech-Language Pathologist | 08/05/2011 |
| KELLY, NICOLE | CYPRESS, TX | PSYD | Psychologist | 02/09/2007 |
| KELLY, PATRICK | ANAHEIM, CA | SUDCC2 | Addiction (Substance Use Disorder) Counselor | 11/30/2023 |
| KELLY, SAMARA | STUART, FL | - | RBT | 09/24/2026 |
| KELNER, ANNA | THOUSAND OAKS, CA | - | Clinical Social Worker | 09/24/2026 |
| KELOW, ARAIYONA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| KELSAW, VEANTREA | FORT WAYNE, IN | QMA,CNA | RBT | 09/23/2026 |
| KEMP, CAROL | WINNETKA, IL | MSW | Specialist | 05/22/2007 |
| KEMP, CYNTHIA | HOUSTON, TX | - | Professional Counselor | 05/22/2018 |
| KEMP, KAREN | RED BLUFF, CA | ASW | Mental Health Counselor | 01/07/2016 |
| KEMP, SYLVIA | UNIVERSAL CITY, TX | LPC | Mental Health Counselor | 09/22/2026 |
| KEMPTON, CAROLINE | WILMINGTON, NC | EDS, MS, MA, LCMHCA | Mental Health Counselor | 09/24/2026 |
| KENDRICK, LATISHA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| KENEALLY, ARIANNA | LEAWOOD, KS | - | RBT | 09/24/2026 |
| KENNEDY, ASHLEY | WHEAT RIDGE, CO | - | BCBA | 09/22/2026 |
| KENNEDY, ELLA | HENDERSON, NV | - | RBT | 09/22/2026 |
| KENNEDY, HANNAH | RAVENNA, OH | - | Professional Counselor | 01/29/2026 |
| KENNEDY, ISABELLA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| KENNEDY, LEAH | LAFAYETTE, IN | - | RBT | 09/25/2026 |
| KENNEDY, OLIVIA | HAUPPAUGE, NY | - | RBT | 09/23/2026 |
| KENWORTH, CASSANDRA | LOVELAND, CO | - | RBT | 09/22/2026 |
| KENYON, KARI | SANTA ROSA, CA | AOD COUNSELOR | Addiction (Substance Use Disorder) Counselor | 02/14/2017 |
| KERATISOMPHON, KISTIYAPORN | SANTA ANA, CA | LCSW | Clinical Social Worker | 12/12/2022 |
| KERNER, MONICA | HOWELL, MI | MACCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| KERR, COURTNEY | SAN JOSE, CA | - | Psychologist | 09/24/2026 |
| KERR, KATELYN | GREENSBURG, PA | LPC | Mental Health Counselor | 02/11/2020 |
| KERR, LIDIANE | BILLINGS, MT | BCBA | BCBA | 03/01/2021 |
| KERR, OLIVIA | ROSEBURG, OR | - | Clinical Social Worker | 01/08/2026 |
| KERRIGAN REDWINE, CASSANDRA | LAWTON, OK | - | Case Manager/Care Coordinator | 11/02/2015 |
| KERSTEN, CHRISTI | TOMBALL, TX | M.A., L.P.C. | Professional Counselor | 01/20/2012 |
| KESTELLI, YAZMIN | FREMONT, CA | - | RBT | 09/24/2026 |
| KETCHUM, KELLIE | YAKIMA, WA | - | Mental Health Counselor | 09/24/2026 |
| KETTEL, TRISTAN | NEWARK, OH | CDCA | Clinical Social Worker | 03/07/2023 |
| KETTERMAN WELLBEING CENTERORG | RANCHO CUCAMONGA, CA | - | Psychologist | 09/22/2026 |
| KETTLER, ISABELLA | MARYLAND HEIGHTS, MO | - | RBT | 09/24/2026 |
| KEY ADVANTAGE HOME CARE LLCORG | HOOVER, AL | - | Community/Behavioral Health Agency | 02/07/2020 |
| KEY, CORITA | BERWYN, IL | - | Clinical Social Worker | 05/12/2025 |
| KEYES FOR HOLISTIC LIVING, LLCORG | HOMESTEAD, PA | - | Professional Counselor | 09/22/2026 |
| KEYS, MYA | WAIPAHU, HI | - | RBT | 09/26/2026 |
| KEYSTONE MEDICAL LLCORG | HOUSTON, TX | - | Clinic/Center | 07/09/2026 |
| KEYSTONE SUPPORT SERVICES LLCORG | JACKSONVILLE, FL | - | Case Management Agency | 12/11/2023 |
| KEYSTONE THERAPY SERVICES LLCORG | OWENSBORO, KY | - | Community/Behavioral Health Agency | 12/31/2025 |
| KHADKA, DEVIKA | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| KHAIMOV, ELIZABETH | BROOKLYN, NY | BCBA | BCBA | 09/23/2026 |
| KHALIL, TAYLOR | HAYWARD, CA | - | RBT | 09/25/2026 |
| KHALILI, MUSKAN | GOLD RIVER, CA | - | RBT | 09/25/2026 |
| KHAMSUREE, SUWIMON | IRWIN, PA | - | RBT | 09/22/2026 |
| KHAN, ESHA | THE COLONY, TX | - | Speech-Language Pathologist | 09/21/2026 |
| KHAN, SABIRAH | HUNTINGTON, NY | - | Mental Health Counselor | 05/18/2023 |
| KHAN, SAIRA | CORVALLIS, OR | DPSYCH | Psychologist | 09/21/2026 |
| KHANJANI-OLIVER, MARJAN | SAN ANTONIO, TX | PH.D. | Psychologist | 03/25/2026 |
| KHODADOUST, DARYA | STERLING, VA | M.A. CCC-SLP | Speech-Language Pathologist | 08/11/2023 |
| KIANI, MARJAN | TORRANCE, CA | - | RBT | 09/21/2026 |
| KIDD, CARLEEN | ELIZABETHTOWN, KY | - | Mental Health Counselor | 09/23/2026 |
| KIDNEY, KIMBERLY | MALAKOFF, TX | - | RBT | 06/30/2026 |
| KIDSPEECH, INC.ORG | LAWRENCEVILLE, GA | - | Speech-Language Pathologist | 04/16/2007 |
| KIDSTUFF CHILD AND FAMILY COUNSELING, P.C.ORG | GREELEY, CO | - | Addiction (Substance Use Disorder) Counselor | 04/03/2020 |
| KIEL, CASSIE | WAUKESHA, WI | SAC-IT | Addiction (Substance Use Disorder) Counselor | 08/17/2026 |
| KIESLING, SAMANTHA | PHILLIPSBURG, NJ | - | Mental Health Counselor | 09/25/2026 |
| KILEY, ANNE | BALTIMORE, MD | - | Mental Health Counselor | 10/20/2014 |
| KILLEEN, JILL | PRESCOTT, AZ | MA, LPC | Mental Health Counselor | 10/02/2006 |
| KILLEN, AMBER | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| KIM, ALIYAH | POMONA, CA | - | RBT | 09/25/2026 |
| KIM, CHRISTINA | LUTHERVILLE TIMONIUM, MD | LCSW | Clinical Social Worker | 11/15/2006 |
| KIM, EMMA | NORTHBROOK, IL | - | Mental Health Counselor | 09/22/2026 |
| KIM, INJIN | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| KIM, JOSEPH | CYPRESS, CA | - | BCBA | 09/26/2026 |
| KIM, MIN SEOP | TORRANCE, CA | MS | BCBA | 09/12/2019 |
| KIM, OLIVIA | PHOENIX, AZ | - | RBT | 09/25/2026 |
| KIM, SE-YOUNG | NEWPORT BEACH, CA | - | Specialist | 04/12/2023 |
| KIM, YURAM | WILMINGTON, MA | - | BCBA | 09/23/2026 |
| KIMBALL, TERRI | FOLSOM, CA | - | Speech-Language Pathologist | 09/23/2026 |
| KIMBERLEY RICHARDSON, LLCORG | BROOKLINE, MA | - | Clinical Social Worker | 11/25/2025 |
| KIMBERLY KAISHER, LCSW, LCAC, LLCORG | COLUMBUS, IN | - | Clinical Social Worker | 06/13/2018 |
| KIMBLEY, WENDY | TEMPLE, TX | - | Clinical Social Worker | 09/22/2026 |
| KIMBONG, ANNE | OWINGS MILLS, MD | - | Case Manager/Care Coordinator | 09/23/2026 |
| KIME, TIA | EAGLE RIVER, AK | - | BCBA | 05/20/2020 |
| KIMES, KRISTIN | SUMMERVILLE, SC | LISW-CP | Clinical Social Worker | 02/02/2023 |
| KIMMEL, CAITLIN | POTTSVILLE, PA | - | RBT | 11/29/2022 |
| KIMMICK, ERICA | WESTLAKE, OH | LPCC, CDCA | Professional Counselor | 11/09/2022 |
| KINDER, LIBERTY | WESTERVILLE, OH | PSYD | Psychologist | 10/02/2023 |
| KINDFUL RESTORATIONORG | RIVERSIDE, CA | - | Addiction (Substance Use Disorder) Counselor | 05/03/2024 |
| KINDSETH, JENNIFER | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| KING, ALEXIA | KIHEI, HI | - | BCBA | 02/13/2019 |
| KING, COLTON | CONCORD, CA | - | RBT | 09/21/2026 |
| KING, DIVIA | EL SEGUNDO, CA | - | RBT | 09/03/2024 |
| KING, GENEVE | VALLEY STREAM, NY | LMSW | Case Manager/Care Coordinator | 03/08/2021 |
| KING, JESSICA | ROCHESTER, NY | LCSW | Clinical Social Worker | 09/21/2026 |
| KING, KATHERINE | PORTAGE, UT | - | Case Manager/Care Coordinator | 09/23/2026 |
| KING, KAYLEE | MONTGOMERY, IL | BCABA | Assistant Behavior Analyst | 11/10/2020 |
| KING, KRISTY | LA JOLLA, CA | M.S., CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| KING, MARNIE | OMAHA, NE | LIMHP, LADC | Mental Health Counselor | 11/04/2010 |
| KING, MEGUMI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| KING, OMETRIS | PHOENIX, AZ | DOCTORATE | Professional Counselor | 01/17/2008 |
| KING, RENEE | ROSWELL, NM | - | RBT | 09/22/2026 |
| KING, ROBIN | FARMERSVILLE, TX | LPC - S | Addiction (Substance Use Disorder) Counselor | 12/23/2020 |
| KING, TERRENCE | YOUNGSTOWN, OH | - | RBT | 09/23/2026 |
| KING, TRACIE | INDIANAPOLIS, IN | - | Mental Health Counselor | 09/21/2026 |
| KINGAMKONO, REUBEN | BREMERTON, WA | - | Mental Health Counselor | 06/05/2019 |
| KINGS FORGE PLLCORG | NORTH RICHLAND HILLS, TX | - | Counselor | 09/24/2026 |
| KINNARD, ELIZABETH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| KINNEY, KYLA | DIXON, IL | RBT | RBT | 09/22/2026 |
| KINZER, EMILY | PAOLA, KS | LCP | Mental Health Counselor | 01/30/2024 |
| KIOSKI, ANDREA | BRILLION, WI | M.S. CCC/SLP | Speech-Language Pathologist | 09/21/2026 |
| KIPPENBERGER, SUSAN | ATLANTA, GA | BCBA | BCBA | 12/28/2022 |
| KIPPES, AUDRA | THORNTON, CO | BCBA | BCBA | 12/12/2024 |
| KIPU, LAURABREEZE | MILILANI, HI | - | RBT | 09/22/2026 |
| KIRBY, CAROL | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| KIRK, GABRIEL | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| KIRK, JESSI | SAINT GEORGE, UT | - | RBT | 09/24/2026 |
| KIRKANDER, MARK | GLENDALE, AZ | - | RBT | 03/01/2022 |
| KIRKPATRICK, ELIZABETH | ARLINGTON HEIGHTS, IL | M.S. CCC-SLP | Speech-Language Pathologist | 06/13/2011 |
| KIRVEN, FELIX | VIRGINIA BEACH, VA | MD | Specialist | 05/03/2006 |
| KISH, KIMBERLY | HIGHLAND, NY | LMHC | Mental Health Counselor | 12/12/2013 |
| KISH, SOPHIA | CLEVELAND, OH | - | Professional Counselor | 01/13/2025 |
| KISLYUK, SHELLY | ELIZABETHTOWN, KY | - | Counselor | 09/21/2026 |
| KISTLER, SAVANNAH | READING, PA | - | Mental Health Counselor | 09/25/2026 |
| KITTLE, JOSHUA | HONEY BROOK, PA | - | Counselor | 09/21/2026 |
| KIZER, JUSTIN | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| KLAMA, HALEY | CHARLOTTE, MI | - | Clinical Social Worker | 09/22/2026 |
| KLANN, STELLA | ENGLEWOOD, CO | MHA | Case Manager/Care Coordinator | 09/22/2026 |
| KLASSEN GUTIERREZ, PAMELA | GREENWOOD VILLAGE, CO | LPCC | Professional Counselor | 03/27/2026 |
| KLAUS, KIM | MOUNT LAUREL, NJ | LPC | Mental Health Counselor | 07/13/2009 |
| KLEIN, ABIGAIL | ELLICOTT CITY, MD | - | BCBA | 12/02/2024 |
| KLEIN, MCKENZIE | GLENDALE, WI | MS CCC-SLP | Speech-Language Pathologist | 06/01/2023 |
| KLEINE, BARBARA | SEATTLE, WA | MS | Mental Health Counselor | 10/23/2006 |
| KLEINTOP, CAITLYN | ORLANDO, FL | M.S. | Speech-Language Pathologist | 09/25/2026 |
| KLEMM, EILEEN | ROSEMOUNT, MN | PHD, CCC-SLP | Speech-Language Pathologist | 03/25/2008 |
| KLETT, JORDAN | FAYETTEVILLE, NC | LCSW | RBT | 11/25/2020 |
| KLEYNENBERG, KEIRSTEN | GRAND RAPIDS, MI | - | RBT | 01/29/2026 |
| KLINE, KATELYN | SAGINAW, MI | - | Case Manager/Care Coordinator | 03/23/2022 |
| KLINEBRIEL, MANDY | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| KLING, SARAH | COLORADO SPRINGS, CO | M.A., LPCC | Mental Health Counselor | 09/22/2026 |
| KLIPPER, ANGELA | LOUISVILLE, KY | SLP | Speech-Language Pathologist | 09/25/2026 |
| KLOBUCAR, DANA | ROCKINGHAM, VA | - | BCBA | 09/22/2026 |
| KLOEPFER, ERIN | OREM, UT | - | Mental Health Counselor | 09/23/2026 |
| KLUG, MARNA | GRAND FORKS, ND | LPCC | Professional Counselor | 06/18/2007 |
| KLY THERAPY SERVICES LLCORG | BATON ROUGE, LA | - | Speech-Language Pathologist | 09/21/2026 |
| KNIGHT, CELINA | CHICAGO, IL | MA, LCPC | Professional Counselor | 12/21/2021 |
| KNIGHT, ISABELLE | RIVERSIDE, CA | - | RBT | 09/25/2026 |
| KNIGHT, JADE | BARBOURVILLE, KY | LCSW | Clinical Social Worker | 03/02/2020 |
| KNIGHT, JORDYN | FRISCO, TX | - | RBT | 09/23/2026 |
| KNIGHT, KAILA | PURCELLVILLE, VA | - | RBT | 09/22/2026 |
| KNIGHT, KIRBY | ASHEVILLE, NC | LCSWA, LCAS | Addiction (Substance Use Disorder) Counselor | 08/27/2026 |
| KNOPP, KANDICE | BOTHELL, WA | MS, BCBA, LBA | BCBA | 08/09/2022 |
| KNOWLES, JENNIFER | NEW SHARON, ME | - | Case Manager/Care Coordinator | 09/23/2026 |
| KNOWLES, MAKENZIE | BELLEVUE, WA | - | BCBA | 07/09/2020 |
| KNOX, KANTRELL | GREENSBORO, NC | CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| KNOX, KRISTY | LADSON, SC | - | Professional Counselor | 03/25/2013 |
| KNOX, NICOLE | FORT CARSON, CO | - | Psychologist | 07/25/2012 |
| KNUDSON, JULIE | FARGO, ND | LPCC | Professional Counselor | 04/13/2020 |
| KNUTSON, KORRI | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| KOBSA, CYNTHIA | HICKSVILLE, NY | - | Speech-Language Pathologist | 09/25/2026 |
| KOCH, CHRIS | EUGENE, OR | CRM | Addiction (Substance Use Disorder) Counselor | 04/14/2021 |
| KOCHE, PRIYA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| KOEHLER, AUTUMN | DURHAM, NC | - | Clinical Social Worker | 09/22/2026 |
| KOEHN, CHELSI | BASEHOR, KS | - | RBT | 09/24/2026 |
| KOELLNER, BRAWNWYN | DALLAS, TX | - | RBT | 09/26/2026 |
| KOENIG, JAMIE | SOUTH SIOUX CITY, NE | - | Mental Health Counselor | 09/24/2026 |
| KOHEN, AMIR | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 09/25/2026 |
| KOHLER, ELIZABETH | BELLEVILLE, IL | LPC | Professional Counselor | 12/06/2022 |
| KOHLS, TRACY | WESTLAKE, OH | LISW | Mental Health Counselor | 12/28/2017 |
| KOHN, SARAH | CLEVELAND, OH | QMHS BA | Clinical Social Worker | 06/22/2018 |
| KOHRMANN, ASHLEIGH | GRANITE CITY, IL | - | RBT | 09/25/2026 |
| KOINONIAORG | ST IGNATIUS, MT | - | Mental Health Counselor | 05/05/2026 |
| KOLACIA, OLIVIA | URBANDALE, IA | - | RBT | 09/22/2026 |
| KOLAR, ERIN | GREENVILLE, NC | - | Speech-Language Pathologist | 09/25/2026 |
| KOLB, ERYKAH | GAITHERSBURG, MD | - | RBT | 09/23/2026 |
| KOLI, IDA | COLUMBIA, MD | - | RBT | 09/21/2026 |
| KOLJIAN, JILLIAN | WORCESTER, MA | - | Clinical Social Worker | 09/23/2026 |
| KOMINIS, CADY | ALICE, TX | - | Counselor | 09/23/2026 |
| KONG, EMILEY | HOUSTON, TX | - | RBT | 09/21/2026 |
| KONIEWICZ, AMANDA | MEDIA, PA | PSY.D, LPC | Professional Counselor | 07/05/2016 |
| KONING, AUDRA | COLORADO SPRINGS, CO | SLP | Speech-Language Pathologist | 10/24/2006 |
| KONJA, RAQUEL | CULVER, IN | LCSW | Clinical Social Worker | 08/07/2026 |
| KONZ, MEGAN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 08/21/2026 |
| KOONCE, JAMEEL | SOUTH EUCLID, OH | - | Case Manager/Care Coordinator | 01/31/2023 |
| KOONTZ, TARAMAY | GRAIN VALLEY, MO | - | Assistant Behavior Analyst | 09/21/2026 |
| KOPCHINSKY SIEGAL, MICHELLE | PEMBROKE PINES, FL | RMHCI | Mental Health Counselor | 12/03/2025 |
| KOPPINGER, RACHEL | ROSEMOUNT, MN | - | Speech-Language Pathologist | 07/20/2011 |
| KOPPLIN, HILBERT | AUSTIN, TX | LCSW | Clinical Social Worker | 09/25/2026 |
| KORIS BEHAVIORAL CENTERS, INC.ORG | GLENDALE, CA | - | BCBA | 05/23/2022 |
| KORNAGAY FLETCHER, DAVONNA | MARYSVILLE, CA | - | RBT | 10/25/2022 |
| KORNIICHUK, YULIIA | ALHAMBRA, CA | - | Assistant Behavior Analyst | 01/20/2023 |
| KOROGHLIAN, NAIRI | WEST COVINA, CA | MFT | Professional Counselor | 09/16/2024 |
| KORTE, JESSIE | CHESTERFIELD, MI | LCSW | Clinical Social Worker | 10/24/2014 |
| KOT, ASHLEY | CLINTON TWP, MI | - | Counselor | 04/28/2025 |
| KOT, STEPHEN | SAINT CLAIR SHORES, MI | - | Mental Health Counselor | 09/21/2026 |
| KOTZER, ADI | DEDHAM, MA | - | Mental Health Counselor | 09/23/2026 |
| KOUCHEKI, KIANA | ORLANDO, FL | - | RBT | 09/23/2026 |
| KOUGL, JASON | EDMOND, OK | - | Addiction (Substance Use Disorder) Counselor | 06/25/2025 |
| KOURI-HARMON, KAITLYN | SAN ANTONIO, TX | LCSW | Clinical Social Worker | 12/08/2022 |
| KOUTROULIS, CHELSEA | HOUSTON, TX | LPC | Professional Counselor | 09/10/2026 |
| KOUYATE, KADIATOU | AURORA, CO | - | Case Manager/Care Coordinator | 05/14/2025 |
| KOVACS, LADISLAU | LACEY, WA | - | Addiction (Substance Use Disorder) Counselor | 04/01/2014 |
| KOWAL, KARISSA | MENIFEE, CA | - | RBT | 09/21/2026 |
| KOWALCZYK, MALIKA | SAN FRANCISCO, CA | - | Counselor | 09/25/2026 |
| KOZAK, SETH | TROY, MI | - | RBT | 09/24/2026 |
| KOZIOL, RACHEL | NAPERVILLE, IL | MA, LCPC | Professional Counselor | 09/05/2024 |
| KP CARE HOLDINGS, LLCORG | CHINO, CA | - | BCBA | 09/24/2026 |
| KRAFT, DEVON | PEAKS ISLAND, ME | - | Mental Health Counselor | 09/23/2026 |
| KRAMER, JENNIFER | CANTON, OH | LPCC-S | Professional Counselor | 05/25/2021 |
| KRAMER, KELLEY | CEDAR PARK, TX | LPC, LPCC | Mental Health Counselor | 07/29/2019 |
| KRAMER, SIOBHEAN | ITHACA, NY | LMHC | Mental Health Counselor | 08/08/2023 |
| KRAMER, WILLIAM | FARMINGTON HILLS, MI | - | RBT | 03/17/2026 |
| KRAMPER, EMILY | JACKSONVILLE, FL | - | RBT | 07/15/2024 |
| KRAUEL-PRIVETT, KRISTEN | AUBURN, CA | LCSW | Professional Counselor | 02/09/2011 |
| KREIGER, REBECCA | WENATCHEE, WA | - | Clinical Social Worker | 01/09/2018 |
| KREIS, DANIEL | LOS ANGELES, CA | - | RBT | 09/23/2026 |
| KREITZBERG, MEGAN | LAFAYETTE, CO | - | Mental Health Counselor | 04/13/2026 |
| KREMER, ANDREA | WALTHAM, MA | LMHC | Mental Health Counselor | 08/07/2020 |
| KREMSKI, CARLEE | ADRIAN, MI | - | Addiction (Substance Use Disorder) Counselor | 04/13/2023 |
| KRENIK, KIMBERLI | DALLAS, OR | LPC | Mental Health Counselor | 05/17/2007 |
| KREVH, ANNIE | CLEVELAND, OH | LPCC | Mental Health Counselor | 10/29/2021 |
| KRISMAN, AIDAN | EVERETT, WA | - | Counselor | 07/22/2024 |
| KRISTEN DABBS COUNSLING PLLCORG | MISSOULA, MT | - | Professional Counselor | 09/21/2026 |
| KRISTIN BOTWINICK LCSW-RORG | CAMILLUS, NY | - | Clinical Social Worker | 09/22/2026 |
| KROHN, JENNA | BROKEN ARROW, OK | - | RBT | 09/24/2026 |
| KROKUS, RACHEL | VANCOUVER, WA | LCSW | Clinical Social Worker | 01/26/2016 |
| KROLIKOWSKI, KAITLYNN | PITTSBURGH, PA | - | RBT | 09/25/2026 |
| KRONES, JORDAN | PALATINE, IL | - | Professional Counselor | 05/01/2025 |
| KRUCKEBERG, KELLY | ROSEMOUNT, MN | M.S., CCC-SLP | Speech-Language Pathologist | 11/29/2006 |
| KRUEGER, BRIAN | OREGON CITY, OR | CADC-I, QMHA-I | Counselor | 09/02/2025 |
| KRUEGER, CORAL | MARSHFIELD, MO | MSW, LCSW | Clinical Social Worker | 12/04/2019 |
| KRUEGER, GRACE | PROSPER, TX | LPC | BCBA | 05/10/2019 |
| KRUKOWSKI, DIANNA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| KRULIK, MELISSA | DELRAY BEACH, FL | PH.D. | Psychologist | 11/01/2010 |
| KRYTEN HOLDINGS LLCORG | PHOENIX, AZ | - | BCBA | 02/03/2026 |
| KUBICEK, ANDREA | SAN ANTONIO, TX | LPC | Mental Health Counselor | 08/28/2023 |
| KUCALA, CATHERINE | WINTERSVILLE, OH | LPCC | Counselor | 07/17/2013 |
| KUDRYK, MARIYA | LINCOLN, CA | - | BCBA | 09/11/2026 |
| KUDZY, MARGARET | BROOKLYN, NY | M.S., CCC-SLP | Speech-Language Pathologist | 02/23/2026 |
| KUE, THIA | FRESNO, CA | - | Counselor | 05/24/2016 |
| KUELBS, SHANNON | GAYLORD, MN | SLP | Speech-Language Pathologist | 09/21/2026 |
| KUHANANDHA, JIVANA | LYNNWOOD, WA | - | RBT | 09/21/2026 |
| KUHN, LAURA | BALTIMORE, MD | LMSW | Clinical Social Worker | 01/17/2022 |
| KUHN, NOEL | PORTLAND, OR | - | RBT | 09/22/2026 |
| KUKUK-BOWDEN, ABIGALE | SPOKANE, WA | CERTIFIED PEER SPEC | Counselor | 09/24/2026 |
| KULA-WRIGHT, JULIANNA | MT PLEASANT, SC | - | Assistant Behavior Analyst | 09/21/2026 |
| KUMAR, SHAMILA | CHERRYLAND, CA | - | Day Training/Habilitation Specialist | 06/26/2026 |
| KUNDA, WHITNEY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| KUNT, MELISA | CLEMENTON, NJ | - | Mental Health Counselor | 09/23/2026 |
| KUNZMANN, NORA CLAIRE | DENVER, CO | LCSW | Clinical Social Worker | 08/25/2021 |
| KURAJYAN, ARMENUHI | VAN NUYS, CA | - | RBT | 07/29/2015 |
| KURTZ, BRADLEY | KNOXVILLE, TN | - | Mental Health Counselor | 09/25/2026 |
| KURTZ, DAWN | BAKERSFIELD, CA | - | Mental Health Counselor | 06/20/2023 |
| KUSTER, HAYLEE | BOSSIER CITY, LA | - | RBT | 07/02/2025 |
| KUTLLOVCI, VLERA | FORT COLLINS, CO | - | Counselor | 09/22/2026 |
| KUYKENDALL, AMBER | OVERLAND PARK, KS | LMSW | Clinical Social Worker | 08/01/2007 |
| KUZMA, JILL | ROSEMOUNT, MN | CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| KWAPIK, JILLIAN | SHELBY TOWNSHIP, MI | - | Mental Health Counselor | 06/09/2026 |
| KWITOWSKI, MELISSA | AURORA, CO | PHD | Psychologist | 07/27/2020 |
| KWOK, NATALIE | LOS ANGELES, CA | - | RBT | 09/25/2026 |
| KWON, BO-RAM | CALEDONIA, MI | - | Mental Health Counselor | 09/24/2026 |
| LAAKE, SERINITY | ARDMORE, OK | - | RBT | 09/25/2026 |
| LABANINO, JAIMEE | MIAMI, FL | - | Clinical Social Worker | 09/24/2026 |
| LABASS, SUMMER | CERES, CA | - | Addiction (Substance Use Disorder) Counselor | 08/12/2026 |
| LABORS OF LOVE THERAPYORG | CHICAGO, IL | - | Clinical Social Worker | 03/17/2021 |
| LABYRINTH, PLLC.ORG | RAMONA, CA | - | Clinical Social Worker | 06/20/2022 |
| LACASTRO, SHANA | CAPE CORAL, FL | LCSW | Clinical Social Worker | 04/29/2013 |
| LACEY, LAUREN | JACKSON, MS | - | Mental Health Counselor | 09/23/2026 |
| LACKEY, SHELBY | KRUM, TX | - | Speech-Language Pathologist | 09/25/2026 |
| LACKOW, JULIETTE | NEW YORK, NY | LCSW | Clinical Social Worker | 06/23/2023 |
| LACKS, LYRICK | COLUMBIA, MD | - | RBT | 09/23/2026 |
| LACROSSE, MARY | BEND, OR | LPC-A | Mental Health Counselor | 09/21/2026 |
| LACTAOEN, JADE | LAS VEGAS, NV | - | Speech-Language Pathologist | 09/26/2026 |
| LACUESTA, ELLAINE | CONCORD, CA | - | RBT | 09/24/2026 |
| LACY, CAROLYN | ATLANTA, GA | - | Case Management Agency | 09/23/2026 |
| LADICK, CIARA | EAU CLAIRE, WI | M.S. SLP | Speech-Language Pathologist | 09/22/2026 |
| LAFAYETTE COUNSELING SERVICES LLCORG | OXFORD, MS | - | Clinical Social Worker | 04/25/2023 |
| LAFLEUR, JAYCI | TILLAMOOK, OR | - | Clinical Social Worker | 09/24/2026 |
| LAFOND, LANATHYA | SANDY SPRINGS, GA | - | RBT | 09/23/2026 |
| LAFRANCIS, DANIELE | HOLYOKE, MA | - | Counselor | 09/23/2026 |
| LAGATTUTA II, FRANCIS | SANTA MARIA, CA | PA-C | Addiction (Substance Use Disorder) Counselor | 11/24/2015 |
| LAGUERRE, EMPRESS | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| LAGUNA, JAQUELINE | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| LAI, JESSICA | TORRANCE, CA | - | RBT | 09/21/2026 |
| LAIRD, PRESLEA | JENNINGS, LA | - | Case Manager/Care Coordinator | 09/22/2026 |
| LAJINESS, ASHLEY | PARK RIDGE, IL | - | BCBA | 04/04/2011 |
| LAKAMSANI, HANSA | WATSONVILLE, CA | - | RBT | 09/22/2026 |
| LAKATOS, TINA | CHAMPAIGN, IL | LCSW | Clinical Social Worker | 05/05/2009 |
| LAKE, KARA | ALBANY, NY | MS, CCC-SLP | Speech-Language Pathologist | 04/27/2010 |
| LAKEWOOD COMMUNITY SERVICES CORP.ORG | LAKEWOOD, NJ | - | Case Management Agency | 01/12/2012 |
| LAM, JENNIFER | ZANESVILLE, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| LAMB, AMY | MESA, AZ | - | Professional Counselor | 09/23/2026 |
| LAMB, CRYSTAL | TULSA, OK | - | Case Manager/Care Coordinator | 05/05/2017 |
| LAMBERT, ALYSSA | MIDWEST CITY, OK | - | RBT | 09/22/2026 |
| LAMBERT, GLENDA | GLENROCK, WY | - | Case Manager/Care Coordinator | 09/22/2026 |
| LAMBRO, NIKO | PORTLAND, OR | QMHA | Case Manager/Care Coordinator | 09/22/2026 |
| LAMERS, PHOEBE | DAYTON, OH | LPC | Mental Health Counselor | 09/22/2026 |
| LAMIELLE, DYLAN | AKRON, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| LAMM, GREGORY | COLEBROOK, NH | LCSW | Addiction (Substance Use Disorder) Counselor | 01/30/2007 |
| LAMM, MORGON | CANON CITY, CO | - | Speech-Language Pathologist | 09/25/2026 |
| LAMMEY, ALBANY | DENVER, CO | BS | Case Manager/Care Coordinator | 09/24/2026 |
| LAMONICA, CHRISTINA | NASHVILLE, TN | MD | Specialist | 07/08/2005 |
| LAMPARD, ALEXANDRIA | SAN JOSE, CA | - | Clinical Social Worker | 09/24/2026 |
| LANCASTER SPEECH AND HEARING, LLCORG | EPHRATA, PA | - | Speech-Language Pathologist | 08/22/2021 |
| LAND OF GOSHEN TREATMENT CENTER, INCORG | CATLETTSBURG, KY | - | Community/Behavioral Health Agency | 04/24/2025 |
| LANDA CARMONA, LIANNE | MIAMI, FL | - | Case Manager/Care Coordinator | 05/05/2020 |
| LANDEN, ALEXANDRA | PHILADELPHIA, PA | DO | Mental Health Counselor | 09/23/2008 |
| LANDOLT, GRACE | CHESTERFIELD, VA | - | Mental Health Counselor | 09/23/2026 |
| LANDON, HAILEY | LAKE MARY, FL | - | RBT | 09/21/2026 |
| LANDON, TAYLOR | MIDLOTHIAN, TX | - | Mental Health Counselor | 08/14/2023 |
| LANE, JESSICA | PATASKALA, OH | - | Clinical Social Worker | 12/08/2023 |
| LANE, SAMANTHA | NEWBURGH, IN | - | RBT | 09/23/2026 |
| LANG, KAYDENCE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| LANGE, JAMES | BRAINERD, MN | LADC | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| LANGE, JASON | SPOKANE, WA | MA, LMHCA | Mental Health Counselor | 03/02/2026 |
| LANGHOLTZ, MARYMEGAN | ALBUQUERQUE, NM | - | Counselor | 09/25/2026 |
| LANGILLE, KELSEY | PORTLAND, OR | LCSW | Clinical Social Worker | 09/12/2022 |
| LANGLEY, ASHLY | COLLINSVILLE, AL | LICSW-S | Clinical Social Worker | 09/24/2026 |
| LANGLEY, CAMRYN | MADISON, WI | LPC | Mental Health Counselor | 07/11/2024 |
| LANGLOIS, SUSAN | NASHUA, NH | MS | Counselor | 09/22/2026 |
| LANIER, BIANCA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 03/15/2022 |
| LANNING, MARISSA | HUDSONVILLE, MI | - | Speech-Language Pathologist | 09/24/2026 |
| LANNING, MYLA | COLUMBUS, GA | - | RBT | 09/21/2026 |
| LANOFF, DYLAN | CHICAGO, IL | PSYD | Psychologist | 08/15/2023 |
| LANTERN & STAFF, LLCORG | THOMPSONS STATION, TN | - | BCBA | 09/23/2026 |
| LANTIERI, AMANDA | WALNUT CREEK, CA | - | Psychologist | 01/03/2019 |
| LANTZ, LEONARD | FARMINGTON HILLS, MI | - | RBT | 11/12/2025 |
| LAPAGLIA, KARA | BRIGHTON, MI | LLPC | Mental Health Counselor | 09/21/2026 |
| LAPAILLE, SAVANNAH | MONROVIA, CA | - | RBT | 05/09/2025 |
| LAPIER, CYNTHIA | GREAT BARRINGTON, MA | LMHC | Mental Health Counselor | 04/10/2023 |
| LAPLANTE, COLLEEN | HERKIMER, NY | - | Case Manager/Care Coordinator | 09/22/2026 |
| LAPOINTE, JOSEPH | ALBUQUERQUE, NM | - | RBT | 09/22/2026 |
| LAPOINTE, KALEE | DEARBORN, MI | - | Psychologist | 08/23/2022 |
| LAPORTE, ABIGAIL | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| LARA, CAITLIN | ANACORTES, WA | - | Clinical Social Worker | 09/23/2026 |
| LARA, JACKELINE | SORRENTO, FL | LMHC | Mental Health Counselor | 01/16/2023 |
| LARAWAY, CHARLES | TAYLORSVILLE, UT | - | RBT | 09/21/2026 |
| LARIOS, SAMANTHA | TORRANCE, CA | - | RBT | 09/21/2026 |
| LARKIN, AMY | SHAWNEE, KS | - | RBT | 09/25/2026 |
| LARNED, ELIZABETH | SEATTLE, WA | MA, LMCH-A | Mental Health Counselor | 03/02/2018 |
| LAROCCA, ALLISON | KANSAS CITY, MO | MS. ED., BCBA | BCBA | 10/30/2019 |
| LAROCCA, ANGELINA | SPRING HILL, FL | - | RBT | 09/25/2026 |
| LAROCHE, OLIVIA | BOSTON, MA | - | Clinical Social Worker | 09/21/2026 |
| LAROSE, KHEILBI | MORGAN, VT | - | Mental Health Counselor | 11/04/2025 |
| LARSEN, BRITTANY | SALT LAKE CITY, UT | - | Case Management Agency | 04/10/2024 |
| LARSON, ANNA | NEW YORK, NY | PHD | Psychologist | 07/08/2025 |
| LARSON, ELENA | AUSTIN, TX | - | Mental Health Counselor | 09/22/2026 |
| LARSON, KIRSTEN | CHATSWORTH, GA | MS | Speech-Language Pathologist | 09/23/2026 |
| LASALLE, LISA | MARINA, CA | CCC-SLP, BRFS | Speech-Language Pathologist | 06/25/2007 |
| LASEKAN, KAYODE | WESTAMPTON, NJ | BA.ED (ENGLISH) | Mental Health Counselor | 11/16/2015 |
| LASER, MEGAN | NOVI, MI | BCBA | BCBA | 04/18/2012 |
| LASH-LAIN, CHRISTINA | SPARTA, NJ | LPC | Professional Counselor | 09/24/2026 |
| LASHLEY, TAHJAI | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| LASISI, MARVELLOUS | MENDOTA HEIGHTS, MN | - | RBT | 09/23/2026 |
| LASKEY, CAROL | SHARON, PA | - | Professional Counselor | 11/04/2011 |
| LASTER, LAMYA | TERRE HAUTE, IN | - | RBT | 09/22/2026 |
| LASTON, EMILY | BARRE, VT | BA | Case Manager/Care Coordinator | 09/24/2026 |
| LATCH, TAMARA | FREDERICK, MD | - | RBT | 09/22/2026 |
| LAUER, ALLIE | DOWNERS GROVE, IL | - | Clinical Social Worker | 04/13/2023 |
| LAUER, TANNA | WEATHERFORD, OK | - | RBT | 09/21/2026 |
| LAUK, LLCORG | MIRAMAR, FL | - | BCBA | 04/07/2026 |
| LAURA BROWN-RIVERA, LCSW, P.C.ORG | BAY SHORE, NY | - | Clinical Social Worker | 09/26/2026 |
| LAURA J. HALFORD PLLCORG | BELLEVUE, WA | - | Community/Behavioral Health Agency | 08/15/2007 |
| LAURICH, JENNIFER | AMARILLO, TX | MA, LPC-S | Professional Counselor | 03/18/2011 |
| LAURICHESSE, TANISHA | SANTA CLARITA, CA | LCSW | Clinical Social Worker | 04/15/2024 |
| LAUTURE, MICHAELA | SPRING, TX | - | RBT | 09/21/2026 |
| LAUX, CLAUDIA | LUTZ, FL | - | Mental Health Counselor | 09/23/2026 |
| LAVALLE, SAVANNAH | SIKESTON, MO | LMSW | Clinical Social Worker | 07/09/2026 |
| LAVALLEY, CHELSEA | PORTLAND, OR | - | Counselor | 04/08/2025 |
| LAVAUD, DAHANA | MAITLAND, FL | RCSWI | Clinical Social Worker | 07/17/2025 |
| LAVONG, LEON | HUNTINGTON BEACH, CA | - | RBT | 09/25/2026 |
| LAWLER, FENTON | ARVADA, CO | - | Clinical Social Worker | 09/25/2026 |
| LAWLER, KAITLYN | OXFORD, MI | - | Mental Health Counselor | 09/23/2026 |
| LAWLER, MARJORIE | BETHLEHEM, PA | - | RBT | 09/21/2026 |
| LAWLESS, COURTNEY | TULSA, OK | - | Case Manager/Care Coordinator | 05/03/2023 |
| LAWRIE, CLAYTON | SPOKANE, WA | - | RBT | 08/02/2025 |
| LAWSON, ANDRUSA | COLUMBIA, MD | - | RBT | 11/22/2025 |
| LAWSON, RACHAEL | GEORGETOWN, KY | LCSW | Clinical Social Worker | 09/21/2026 |
| LAWTON, JOSHUA | CLACKAMAS, OR | BCBA | BCBA | 03/26/2019 |
| LAXSON, EMMA | EDMOND, OK | BHCM II | Case Manager/Care Coordinator | 12/17/2024 |
| LAYELL, CHARLES | JEFFERSON CITY, TN | LPC/MHSPT | Professional Counselor | 03/01/2021 |
| LAYMAN, GRACE | CHICAGO, IL | M.S., CF-SLP | Speech-Language Pathologist | 05/15/2026 |
| LAZARO, KEVIN | VANCOUVER, WA | - | Mental Health Counselor | 09/24/2026 |
| LAZO, ISABEL | COSTA MESA, CA | - | RBT | 09/23/2026 |
| LCA PSYCHOLOGICAL ASSOCIATES, LLCORG | WALDORF, MD | - | Counselor | 05/28/2010 |
| LDA MEDICAL CORPORATIONORG | SANTA MONICA, CA | - | Clinic/Center | 09/22/2026 |
| LE, CONNOR | IRVINE, CA | - | RBT | 07/16/2025 |
| LE, MAEGAN | GREENWOOD VILLAGE, CO | LPC | Mental Health Counselor | 06/04/2022 |
| LE, MATTHEW | ORANGE, CA | - | RBT | 09/22/2026 |
| LE, THERESA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| LEACH, SARAH | FERNANDINA BEACH, FL | RCSWI | Clinical Social Worker | 09/25/2026 |
| LEAGUE, AMANDA | LITHIA, FL | - | RBT | 08/07/2024 |
| LEAKE, ANDERSEN | SALT LAKE CITY, UT | - | RBT | 09/21/2026 |
| LEAL, JESSICA | LAPEER, MI | - | Speech-Language Pathologist | 09/22/2026 |
| LEAL, LAWRENCE | MARCO ISLAND, FL | - | RBT | 09/24/2026 |
| LEANON HEALTH SERVICES LLCORG | WASHINGTON, DC | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| LEAP INTO LANGUAGE, INC.ORG | ZEPHYRHILLS, FL | - | Speech-Language Pathologist | 11/09/2017 |
| LEAR, TRENT | MATHER, CA | LCSW | Addiction (Substance Use Disorder) Counselor | 11/01/2006 |
| LEARNING WELLSORG | HUNTINGTON PARK, CA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| LEBEAU, ERIN | AURORA, CO | LCSW | Clinical Social Worker | 06/19/2023 |
| LEBLANC, JASMINE | GULFPORT, MS | - | RBT | 09/22/2026 |
| LEBLANC, SOPHIA | WILMINGTON, NC | - | RBT | 09/23/2026 |
| LECKNER, HAYLEY | MERRILLVILLE, IN | MA, BCBA | BCBA | 05/23/2022 |
| LECLAIR, DAVID | HOLLYWOOD, FL | LCSW | Addiction (Substance Use Disorder) Counselor | 06/13/2014 |
| LEDDY, ROLAND | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| LEDESMA, COURTNEY | GARDENA, CA | - | BCBA | 09/21/2026 |
| LEDFORD, MEGAN | DEL CITY, OK | LPC CANDIDATE | Mental Health Counselor | 06/19/2024 |
| LEE, ALAINA | OMAHA, NE | - | RBT | 04/29/2025 |
| LEE, BETHANY | WASILLA, AK | BCBA | RBT | 09/10/2020 |
| LEE, COHEN | ELK GROVE, CA | - | RBT | 09/24/2026 |
| LEE, DANIEL | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| LEE, DIANA | EVERETT, WA | M.ED.,M.P.A. | Mental Health Counselor | 01/27/2007 |
| LEE, ELIZABETH | MOSCOW, ID | - | Mental Health Counselor | 10/15/2020 |
| LEE, FLAY | CHARLOTTE, NC | LCAS #643 | Professional Counselor | 04/18/2019 |
| LEE, HEIDI | BOSTON, MA | - | Case Manager/Care Coordinator | 09/25/2026 |
| LEE, JASON | CHICAGO, IL | - | Clinical Social Worker | 03/27/2023 |
| LEE, LILY | RICHMOND HILL, GA | - | BCBA | 11/09/2022 |
| LEE, MARGARET | MOUNTAIN BRK, AL | LICSW | Clinical Social Worker | 01/21/2026 |
| LEE, MICHELLE | TORRANCE, CA | - | RBT | 09/21/2026 |
| LEE, MIN JUNG | DENTON, TX | - | BCBA | 09/21/2026 |
| LEE, SHARON | STILLWATER, OK | - | Mental Health Counselor | 11/04/2008 |
| LEE, SHIRLEYJO | CARY, NC | - | BCBA | 07/23/2025 |
| LEEPER, AMANDA | PASADENA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| LEFFELMAN, VICTORIA | ROSEMOUNT, MN | SPEECH PATHOLOGIST | Speech-Language Pathologist | 06/22/2009 |
| LEGACY CARE COMMUNITY SOLUTIONS LLCORG | PORTSMOUTH, VA | - | Community/Behavioral Health Agency | 09/22/2026 |
| LEGACY LANTERN LLCORG | LAVEEN, AZ | - | BCBA | 09/25/2026 |
| LEHMAN, TYLER | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| LEHTOLA, HALEY | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| LEIBA, MATAN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| LEIBRANDT, COURTNEY | MUSKEGON, MI | LLPC | Mental Health Counselor | 09/10/2025 |
| LEICHTENTRITT, AMANDA | PEORIA, AZ | LPC | Mental Health Counselor | 01/05/2019 |
| LEIJA, KARYME | HARLINGEN, TX | - | RBT | 09/21/2026 |
| LEIPZIGER, CHARLES | SANTA MONICA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| LEISCHNER, KEYLEY | BILLINGS, MT | - | RBT | 08/11/2026 |
| LEJA, LOGAN | NORTH ADAMS, MA | - | Counselor | 09/22/2026 |
| LEMAIRE, JOEL | ELLENSBURG, WA | - | Mental Health Counselor | 05/01/2023 |
| LEMKAU, EMILY | HOWELL, MI | - | RBT | 08/26/2024 |
| LEMKE, BLAIR | MCALLEN, TX | - | RBT | 09/21/2026 |
| LEMKE, EMILY | ROCKVILLE, MD | LCSW-C | Clinical Social Worker | 03/06/2020 |
| LEMMEL-HAY, CHLOE | ASHEVILLE, NC | MSW, LCSWA | Clinical Social Worker | 09/10/2026 |
| LEMMON, SARAH | LAKEPORT, CA | - | Day Training/Habilitation Specialist | 11/15/2018 |
| LEMON, ADRIANA | ALAMEDA, CA | - | Case Manager/Care Coordinator | 01/22/2021 |
| LEMONS, CADE | SPRING, TX | PHD | Psychologist | 09/22/2026 |
| LENARZ, MARGARET | SEATTLE, WA | - | Mental Health Counselor | 07/11/2024 |
| LENETSKY, RILEY | OWEGO, NY | LMSW | Clinical Social Worker | 09/21/2026 |
| LENGOMIN, MICHELLE | MIAMI, FL | - | RBT | 09/22/2026 |
| LENMARK, ALLISON | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| LENNEX, NICOLE | FARMINGTON HILLS, MI | RBT | RBT | 07/11/2025 |
| LENNON, CHELSEA | GREENVILLE, NC | - | RBT | 08/21/2020 |
| LENORE, JAWEYA | COLUMBIA, MD | - | RBT | 03/16/2026 |
| LENTZ, KATY | SAINT CLOUD, MN | MSW, LGSW | Clinical Social Worker | 09/23/2026 |
| LEON CERDEIRA, ANA | DORAL, FL | RBT | RBT | 09/17/2021 |
| LEONARD RENGIFO, YASSER | CAPE CORAL, FL | - | RBT | 01/04/2024 |
| LEONARDO CHAVEZ, CAMILA | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| LEONE, CHRISTINE | REISTERSTOWN, MD | LCPC | Mental Health Counselor | 06/14/2007 |
| LEOPOLD, SAUL | SANTA ROSA, CA | M.S.W., PH.D. | Clinical Social Worker | 05/29/2007 |
| LEPAGE, YORGELLYS | BRADENTON, FL | - | RBT | 09/23/2026 |
| LEPPEK, MADELINE | MADISON HEIGHTS, MI | - | Speech-Language Pathologist | 09/24/2026 |
| LESLIE, ALEXIS | VAN NUYS, CA | - | RBT | 09/24/2026 |
| LESLIE, DEMETRICH | PICKERINGTON, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| LESLIE, JACKSON | MEMPHIS, TN | - | RBT | 09/25/2026 |
| LESNE, ALBAN | SAN FRANCISCO, CA | LMFT | Addiction (Substance Use Disorder) Counselor | 03/04/2018 |
| LESTER, LORA | GALLIPOLIS, OH | CRISIS RES SPEC | BCBA | 09/22/2026 |
| LESTER, SYDNEY | JACKSONVILLE, FL | - | RBT | 04/06/2023 |
| LET'S DOULA THISSORG | EUTAW, AL | - | Case Management Agency | 09/21/2026 |
| LEUENBERGER, JESSICA | BEVERLY HILLS, MI | LPC | Mental Health Counselor | 01/23/2024 |
| LEVERT, TRICIA | SIGNAL HILL, CA | - | Mental Health Counselor | 08/17/2017 |
| LEVESQUE, ANDREA | ROCKVILLE CENTRE, NY | MA | Counselor | 03/16/2023 |
| LEVESQUE, BRENDAN | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| LEVIER, BRANDE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| LEVIN, JENNIFER | HILLSBORO, OR | LCSW | Clinical Social Worker | 12/30/2011 |
| LEVINGS, HAILEY | DENTON, TX | LCDC-I | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| LEVITO, JENNIFER | ATLANTA, GA | MS | Professional Counselor | 03/18/2024 |
| LEVITY BEHAVIORAL HEALTH SERVICES, LLCORG | WESTERVILLE, OH | - | Counselor | 09/22/2026 |
| LEVSKY, MIRIAM | NEW YORK, NY | MS, SLP, TSSLD | Speech-Language Pathologist | 09/22/2026 |
| LEVY, IYANA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| LEWIS, ADRIANA | PENSACOLA, FL | MSW | Clinical Social Worker | 09/27/2022 |
| LEWIS, ANGEL | LAFAYETTE, LA | - | Professional Counselor | 05/17/2017 |
| LEWIS, ANNA | FREMONT, CA | - | Mental Health Counselor | 12/22/2019 |
| LEWIS, CHRISTOPHER | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 03/18/2019 |
| LEWIS, D'ANDRA | SAINT JOHNS, FL | RBT | RBT | 09/21/2026 |
| LEWIS, EMILY | BELLEVUE, WA | - | RBT | 06/08/2026 |
| LEWIS, JESSICA | SOUTHFIELD, MI | LPC | Counselor | 10/06/2017 |
| LEWIS, JNAI | TOLEDO, OH | - | Case Manager/Care Coordinator | 05/29/2018 |
| LEWIS, KAILEY | WAYLAND, MI | - | Speech-Language Pathologist | 09/24/2026 |
| LEWIS, KASEY | PITTSBURGH, PA | - | Speech-Language Pathologist | 06/02/2015 |
| LEWIS, KATE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| LEWIS, MEGAN | MORRO BAY, CA | LCSW | Clinical Social Worker | 09/21/2026 |
| LEWIS, RACHEL | NEW YORK, NY | MHC-LP | Mental Health Counselor | 09/23/2026 |
| LEWIS, SABRINA | BIRMINGHAM, AL | PHD, LPC, NCC | Counselor | 09/21/2026 |
| LEWIS, SERRITA | SHREVEPORT, LA | - | Case Manager/Care Coordinator | 09/24/2019 |
| LEWIS, SHANELE | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| LEWIS, WILLIE | HOUSTON, TX | LPC | Professional Counselor | 06/12/2006 |
| LEWIS, ZINIYAH | WHITESTONE, NY | - | RBT | 09/21/2026 |
| LEYVA, JESUS | TORRANCE, CA | - | Counselor | 12/08/2008 |
| LI, CHANGXIN | TORRANCE, CA | - | RBT | 09/21/2026 |
| LI, EMILY | GOOCHLAND, VA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| LI, KEVIN | SAN FRANCISCO, CA | - | Clinical Social Worker | 09/23/2026 |
| LI, MENGCHEN | SAN JOSE, CA | - | RBT | 09/23/2026 |
| LI, WHITNEY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| LIAVAA, BRANDYSAMANTHA | SALT LAKE CITY, UT | - | Case Manager/Care Coordinator | 04/19/2021 |
| LIBERTY EQUINE COUNSELINGORG | RHOME, TX | - | Mental Health Counselor | 09/23/2026 |
| LIBRIE, MICHAEL | SHALLOTTE, NC | LCSW-C | Clinical Social Worker | 05/07/2010 |
| LICEA, LIANNY | MIAMI SPRINGS, FL | - | RBT | 09/24/2026 |
| LIDDLE, KILEY | SACRAMENTO, CA | M.S., BCBA | BCBA | 03/02/2020 |
| LIEBERMAN, ELIZA | CHARLOTTE, NC | LCMHCA | Mental Health Counselor | 09/21/2026 |
| LIEN, BRENNA | MOORHEAD, MN | - | Specialist | 01/03/2020 |
| LIENDO, LOURDES | NASHUA, NH | - | RBT | 09/22/2026 |
| LIEU, VICKY | AUGUSTA, GA | - | Mental Health Counselor | 02/06/2023 |
| LIFE CHANGE PSYCHOTHERAPY INSTITUTE, PCORG | ALBUQUERQUE, NM | - | Professional Counselor | 04/24/2007 |
| LIFE CHANGE THERAPY LLCORG | OKEMOS, MI | - | Mental Health Counselor | 02/17/2025 |
| LIFE HOME THERAPY LLCORG | LIVINGSTON, NJ | - | Speech-Language Pathologist | 12/21/2020 |
| LIFE LAB WELLNESSORG | SAINT JOSEPH, MI | - | Professional Counselor | 09/25/2026 |
| LIFE REFLECTIONS COUNSELING, LLCORG | THE WOODLANDS, TX | - | Mental Health Counselor | 03/27/2023 |
| LIFECARE ABA THERAPY LLCORG | LIVONIA, MI | - | BCBA | 01/28/2025 |
| LIFESTANCE HEALTH - ALABAMA, LLC DBA LIFESTANCE HEALTHORG | BIRMINGHAM, AL | - | Mental Health Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - ALASKA, LLC DBA LIFESTANCE HEALTHORG | ANCHORAGE, AK | - | Counselor | 05/20/2026 |
| LIFESTANCE HEALTH - ARKANSAS, INC. DBA LIFESTANCE HEALTHORG | LITTLE ROCK, AR | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - CONNECTICUT, PC DBA LIFESTANCE HEALTHORG | WEST HARTFORD, CT | - | Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - D.C., PC DBA LIFESTANCE HEALTHORG | WASHINGTON, DC | - | Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - HAWAII, LLC DBA LIFESTANCE HEALTHORG | HONOLULU, HI | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - IDAHO, PC DBA LIFESTANCE HEALTHORG | BOISE, ID | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - IOWA, PC DBA LIFESTANCE HEALTH, P.C.ORG | DES MOINES, IA | - | Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - LOUISIANA, LLC DBA LIFESTANCE HEALTHORG | METAIRIE, LA | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - MISSISSIPPI, LLC DBA LIFESTANCE HEALTHORG | FLOWOOD, MS | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - MONTANA, LLC DBA LIFESTANCE HEALTHORG | BILLINGS, MT | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - NEBRASKA, LLC DBA LIFESTANCE HEALTHORG | OMAHA, NE | - | Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - NEW MEXICO, LLC DBA LIFESTANCE HEALTH LLCORG | ALBUQUERQUE, NM | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - NORTH DAKOTA, PC DBA LIFESTANCE HEALTHORG | FARGO, ND | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - SOUTH DAKOTA, P.C. DBA LIFESTANCE HEALTHORG | SIOUX FALLS, SD | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - VERMONT, LLC DBA LIFESTANCE HEALTHORG | WINOOSKI, VT | - | Counselor | 05/19/2026 |
| LIFESTANCE HEALTH - WEST VIRGINIA, PLLC DBA LIFESTANCE HEALTHORG | CHARLESTON, WV | - | Counselor | 05/28/2026 |
| LIFESTANCE HEALTH - WYOMING, LLC DBA LIFESTANCE HEALTHORG | CHEYENNE, WY | - | Counselor | 05/20/2026 |
| LIFEWISE COUNSELING AND WELLNESS, LLCORG | FORT WORTH, TX | - | Mental Health Counselor | 09/24/2026 |
| LIFTED HANDS HEALTHCAREORG | HOUSTON, TX | - | BCBA | 11/08/2021 |
| LIGHTED PATH SERVICES LLCORG | HENDERSON, KY | - | Clinical Social Worker | 07/26/2025 |
| LIGHTHOUSE COUNSELING, LLCORG | PARMA, OH | - | Professional Counselor | 09/24/2026 |
| LIGHTHOUSE THERAPEUTIC SERVICES-DEBORA RIBAS SANTOS LCSWORG | CHINO, CA | - | Professional Counselor | 07/29/2022 |
| LILAC CENTER LLCORG | KANSAS CITY, MO | - | Mental Health Counselor | 03/23/2010 |
| LILLY, STEVEN | EAST CALAIS, VT | - | Mental Health Counselor | 03/28/2024 |
| LIMAS, ERIC | LOS ANGELES, CA | R1520170823 | Addiction (Substance Use Disorder) Counselor | 03/05/2025 |
| LIMOANCO, ANGELICA MARIE | LOS ANGELES, CA | - | RBT | 09/23/2026 |
| LIN, CHIEN-CHUN | VANCOUVER, WA | - | Professional Counselor | 04/11/2022 |
| LIN, SAMUEL | WATSONVILLE, CA | - | RBT | 09/22/2026 |
| LINCK, KELLY | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| LINCOLN COUNTY PUBLIC HOSPITAL DISTRICT 1ORG | ODESSA, WA | - | Case Management Agency | 04/02/2018 |
| LINDBLOM, NICHOLAS | OVERLAND PARK, KS | - | RBT | 10/09/2023 |
| LINDEN BROOK COUNSELING LLCORG | FOREST PARK, IL | - | Mental Health Counselor | 09/21/2026 |
| LINDEN, MARGARET | WEAVERVILLE, NC | - | BCBA | 09/23/2026 |
| LINDMAN, HAILEY | OWASSO, OK | BCBA | BCBA | 06/08/2020 |
| LINDSAY, ARIANA | BEND, OR | - | Mental Health Counselor | 02/02/2023 |
| LINDSEY, KENDRA | SAINT LOUIS, MO | - | RBT | 09/24/2026 |
| LINDSEY, WILLIAM | HOUSTON, TX | LPC | Mental Health Counselor | 05/16/2019 |
| LINDSTADT, REBECCA | WELLINGTON, FL | LCSW, PHD | Clinical Social Worker | 12/27/2006 |
| LINEBRINK, KATHY | CELINA, OH | - | Case Manager/Care Coordinator | 04/22/2026 |
| LINEHAN, CHERI | MADISON, WI | - | Counselor | 06/25/2007 |
| LINGINFELTER, SHAINA | ROME, GA | LCSW | Clinical Social Worker | 09/22/2026 |
| LINGLE, KACIE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| LINGLE, SOPHIA | HERRIN, IL | - | RBT | 09/24/2026 |
| LINGO, PATRICIA | ALGONQUIN, IL | LCSW | Clinical Social Worker | 12/04/2014 |
| LINK WELLNESS OF FL LLCORG | MIRAMAR, FL | - | Mental Health Counselor | 09/24/2026 |
| LINK, LEIGH | MINOCQUA, WI | LLPC | Professional Counselor | 07/24/2019 |
| LINKS AND PATTERNS PLLCORG | COLUMBIA HEIGHTS, MN | - | Professional Counselor | 09/26/2026 |
| LINN, AVERY | TULSA, OK | - | Counselor | 12/26/2024 |
| LINQUIST, BRUCE | ANCHORAGE, AK | LCSW, CADAC, CDCS | Clinical Social Worker | 09/27/2006 |
| LIPSCOMBE-ADAMS, GENESIS | ALEXANDRIA, VA | - | RBT | 09/21/2026 |
| LIST, CHARLEY | DENTON, TX | - | RBT | 09/23/2026 |
| LISTON, VICTORIA | MARYVILLE, IL | BSW, CADC | Clinical Social Worker | 03/19/2012 |
| LITFIN, LYNN | CARLSBAD, CA | - | RBT | 07/20/2026 |
| LITSEY, LISA | SAN MATEO, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| LITTERAL, CAROLYN | ALEDO, TX | LPC-S, LCDC | Addiction (Substance Use Disorder) Counselor | 07/10/2017 |
| LITTLE BEEGINNINGS, LLCORG | MANASSAS, VA | - | BCBA | 09/21/2026 |
| LITTLE HANDS AT PLAY THERAPY, LLCORG | FORT SMITH, AR | - | Speech-Language Pathologist | 03/02/2017 |
| LITTLE HAVEN BEHAVIORAL HEALTH CT LLCORG | GLASTONBURY, CT | - | BCBA | 09/07/2026 |
| LITTLE KIDS THERAPY CORPORG | VERO BEACH, FL | - | BCBA | 05/30/2025 |
| LITTLE STAR ABA INCORG | VALLEY VILLAGE, CA | - | Community/Behavioral Health Agency | 09/10/2026 |
| LITTLE TEDDY BEARS APPLIED BEHAVIOR ANALYSIS SERVICES PLLCORG | WHITESTONE, NY | - | BCBA | 09/21/2026 |
| LITTLE TREEHOUSE ABA LLCORG | PALMETTO, GA | - | BCBA | 09/21/2026 |
| LITTLE, ERIN | PORTLAND, ME | M.D. | Specialist | 04/05/2015 |
| LITTLES, TANYA | WESTAMPTON, NJ | - | Mental Health Counselor | 09/22/2026 |
| LITTLETON, KACIA | SACRAMENTO, CA | SUDRCI | Addiction (Substance Use Disorder) Counselor | 05/05/2026 |
| LITVINENKO, NATALIIA | SAINT JOHNS, FL | RBT | RBT | 10/29/2025 |
| LIU-SHEIN, BRENDA | PORTLAND, OR | - | Mental Health Counselor | 06/04/2018 |
| LIU, CHANG | SAN JOSE, CA | - | Mental Health Counselor | 09/21/2026 |
| LIU, MEIMEI | DES MOINES, WA | - | Counselor | 08/25/2025 |
| LIV ALIGNED THERAPY PLLCORG | WINSTON SALEM, NC | - | Mental Health Counselor | 08/24/2026 |
| LIV, MELANIE | ORANGE, CA | - | RBT | 09/21/2026 |
| LIVE LIFE FULL LLCORG | MECHANICSVILLE, VA | - | Counselor | 06/30/2017 |
| LIVE WELL THERAPEUTIC COUNSELING AND CONSULTINGORG | KILLEEN, TX | - | Clinical Social Worker | 10/19/2023 |
| LIVSHETZ, MAXIM | LYNNWOOD, WA | PSYD | Psychologist | 09/09/2014 |
| LIZOTTE, KAYLIE | FAYETTEVILLE, NC | - | RBT | 09/14/2026 |
| LLAMAS, ALONDRA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| LLANES, SELENA | CHULA VISTA, CA | - | Speech-Language Pathologist | 09/22/2026 |
| LLOYD, CONNER | ASHEVILLE, NC | LCSWA | Clinical Social Worker | 06/21/2024 |
| LLOYD, LANDON | BOISE, ID | - | Clinical Social Worker | 04/17/2023 |
| LOAM COUNSELING LLCORG | OREGON CITY, OR | - | Mental Health Counselor | 09/23/2026 |
| LOBAN, LAUREN | FAIRFIELD, CA | - | RBT | 09/22/2026 |
| LOBINA, NIYOMBONA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| LOCASCIO, DEBRA | MATTHEWS, NC | MSED. | RBT | 09/25/2026 |
| LOCHA, ALEXANDRA | AUSTIN, TX | MS | Mental Health Counselor | 11/24/2025 |
| LOCKE, SAVANNA | SAGINAW, MI | - | RBT | 09/23/2025 |
| LOCKETT, KIANA | SPRING, TX | - | RBT | 09/22/2026 |
| LOCKETT, TATIYANA | WHITESTONE, NY | - | RBT | 09/25/2026 |
| LOCKHEART, SYDNEE | ONTARIO, CA | AA | RBT | 04/22/2024 |
| LOCKLEAR, LINDSAY | KERNERSVILLE, NC | MS, LCMHC-A | Mental Health Counselor | 12/05/2023 |
| LOCKWOOD, JENNA | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| LOFASO, BRIANNA | PORT ST LUCIE, FL | - | Mental Health Counselor | 09/21/2026 |
| LOGAN HEIGHTS COMMUNITY DEVELOPMENT CORPORATION (CDC)ORG | SAN DIEGO, CA | - | Community/Behavioral Health Agency | 09/21/2026 |
| LOGUE, HEATH | GRAYSON, KY | LCSW | Clinical Social Worker | 04/10/2023 |
| LOHR, SUZETTE | LITTLE EGG HARBOR TWP, NJ | - | Clinical Social Worker | 09/21/2026 |
| LOMAX, STEPHANIE | BROOKLYN, NY | LCSW-R, CASAC, SAP | Clinical Social Worker | 05/14/2007 |
| LOMBARDI, DEBBIE | EPHRATA, PA | M.S. | Speech-Language Pathologist | 11/06/2006 |
| LOMIS, AMY | MENTOR, OH | MSSA, LISW-S | Clinical Social Worker | 09/11/2017 |
| LONDON, SJAEDAH | WILMINGTON, DE | - | Assistant Behavior Analyst | 09/23/2026 |
| LONE WOLF COUNSELING SERVICES LLCORG | ANCHORAGE, AK | - | Clinical Social Worker | 09/21/2026 |
| LONG, BREETA | SALEM, UT | - | RBT | 09/23/2026 |
| LONG, MICHELLE | WARWICK, NY | - | Case Manager/Care Coordinator | 09/23/2026 |
| LONG, PENNY | ELKHORN, NE | - | Case Manager/Care Coordinator | 09/22/2026 |
| LONGWORTH, VALORIE | RURAL HALL, NC | - | Professional Counselor | 10/09/2024 |
| LOONEY, ROLECIA | PRUDENVILLE, MI | - | RBT | 09/25/2026 |
| LOOPER, DAISY | DALLAS, TX | M.A. | Mental Health Counselor | 09/24/2026 |
| LOOSER, COURTNEY | ENGLEWOOD, CO | - | BCBA | 09/22/2026 |
| LOPATIN, REBECCA | PHOENIX, AZ | LCSW | Clinical Social Worker | 11/13/2024 |
| LOPES, CARINA | LONG BEACH, CA | - | RBT | 09/22/2026 |
| LOPEZ RAMIREZ, ELVIRA | YAKIMA, WA | - | Case Manager/Care Coordinator | 09/19/2019 |
| LOPEZ-COREAS, JENNIFER | HOLYOKE, MA | - | Counselor | 09/23/2026 |
| LOPEZ-MCLEAN, MARA | LOS ANGELES, CA | LCSW | Clinical Social Worker | 02/21/2020 |
| LOPEZ, ALEJANDRA | YAKIMA, WA | MSW | Counselor | 02/02/2017 |
| LOPEZ, ANAHI | SACRAMENTO, CA | - | RBT | 09/25/2026 |
| LOPEZ, ARIAN | ROSEVILLE, CA | - | RBT | 10/24/2022 |
| LOPEZ, BERTHA | DENTON, TX | MS,CCC-SLP | Speech-Language Pathologist | 05/05/2009 |
| LOPEZ, CARMEN | ORANGE, CA | - | RBT | 09/22/2026 |
| LOPEZ, CATHARYNE | COVINA, CA | - | RBT | 09/23/2026 |
| LOPEZ, DINA | COLTON, CA | - | Clinical Social Worker | 04/20/2022 |
| LOPEZ, ERIC | FRESNO, CA | - | Counselor | 11/25/2019 |
| LOPEZ, HEATHER | LARGO, FL | - | RBT | 09/25/2026 |
| LOPEZ, JACLYN | COLORADO SPRINGS, CO | - | Case Manager/Care Coordinator | 09/24/2026 |
| LOPEZ, JORGE | CAPE CORAL, FL | - | RBT | 10/13/2022 |
| LOPEZ, KAITLYN | ASHEVILLE, NC | - | BCBA | 10/20/2025 |
| LOPEZ, LEONARDO | RALEIGH, NC | LCSW-A | Clinical Social Worker | 09/19/2026 |
| LOPEZ, LIANE | LOS ANGELES, CA | - | RBT | 09/22/2026 |
| LOPEZ, MANUEL | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| LOPEZ, MARIA | BAKERSFIELD, CA | ASW | Clinical Social Worker | 03/23/2015 |
| LOPEZ, MARISOL | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| LOPEZ, NANCY | MODESTO, CA | - | RBT | 09/21/2026 |
| LOPEZ, PAUL | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| LOPREATO, ELIZABETH | POUGHKEEPSIE, NY | MHC-LP | Mental Health Counselor | 09/23/2026 |
| LORD DENNIS, TIFFANY | MARY ESTHER, FL | - | RBT | 09/21/2026 |
| LORINO, MARY | HUNTSVILLE, AL | - | Clinical Social Worker | 09/22/2026 |
| LORTON, ASHTEN | AURORA, IN | LMHCA | Mental Health Counselor | 09/25/2026 |
| LOSEY, BROOKE | WINSTON SALEM, NC | - | Mental Health Counselor | 05/25/2026 |
| LOUDERBACK, MADISON | COLUMBUS, NE | PLDAC | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| LOUIS, AKIAH | LAS VEGAS, NV | RBT | RBT | 09/23/2026 |
| LOUIS, JESSICA | CORAL SPRINGS, FL | - | RBT | 09/22/2026 |
| LOVATO, CAMERAN | COLUMBIA, SC | - | RBT | 09/19/2026 |
| LOVE, CORBY | NORCROSS, GA | - | RBT | 09/25/2026 |
| LOVE, DINA | SEATTLE, WA | LMHC | Mental Health Counselor | 09/22/2026 |
| LOVE, LARRY | MONROE, MI | MA LPC | Mental Health Counselor | 05/15/2007 |
| LOVELACE, NIA | FARMINGTON HILLS, MI | - | RBT | 07/14/2021 |
| LOVELY DAYS LLCORG | WINDSOR HEIGHTS, IA | - | BCBA | 09/24/2026 |
| LOVERICH, KATHRYN | PITTSBURGH, PA | - | RBT | 05/18/2021 |
| LOWE, CAROLYN | CLARKSVILLE, TN | - | BCBA | 02/19/2024 |
| LOWE, SARAH | LENEXA, KS | - | RBT | 09/24/2026 |
| LOWMACK, MCKENZIE | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| LOWNEY, MADELYN | ROYAL OAK, MI | - | Psychologist | 11/07/2022 |
| LOWRY, ELIZABETH | WEST VALLEY, UT | - | RBT | 09/21/2026 |
| LOYA, MARIA | LOS LUNAS, NM | - | RBT | 09/22/2026 |
| LOYAL BEGINNINGSORG | 19 N TEJON, CO | - | Addiction (Substance Use Disorder) Counselor | 07/30/2026 |
| LOZA, SOFIA | HAYWARD, CA | - | RBT | 09/25/2026 |
| LOZANO, ANNELIESE | ORLAND PARK, IL | - | Clinical Social Worker | 09/26/2026 |
| LU, JENNIE | DUBLIN, CA | - | RBT | 09/03/2026 |
| LUBIN, QNIYAH | FOLSOM, CA | - | RBT | 09/21/2026 |
| LUCAS, ALYSSA | MYRTLE BEACH, SC | - | Speech-Language Pathologist | 04/12/2025 |
| LUCAS, ALYSSA | JEFFERSONVILLE, IN | - | RBT | 09/23/2026 |
| LUCAS, CHRISTOPHER | HUNTINGTON, WV | LICSW | Clinical Social Worker | 02/24/2021 |
| LUCAS, JANET | GLENDALE, CA | LCSW | Mental Health Counselor | 09/23/2026 |
| LUCAS, JESSICA | PUNTA GORDA, FL | MA, LMHC | Mental Health Counselor | 05/10/2023 |
| LUCIANO, JAMES | HARLINGEN, TX | - | RBT | 09/23/2026 |
| LUCIOW, JENNIFER | MONROE, MI | MS CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| LUCKE, TAMMY | BEDFORD, NH | - | Clinical Social Worker | 02/08/2022 |
| LUCKERT PAOLONE, ALEXANDRA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| LUCKEY, KELLY | BLOOMINGTON, IL | LCPC | Mental Health Counselor | 12/19/2023 |
| LUDWIG, ELLEN | MAULDIN, SC | - | RBT | 09/25/2026 |
| LUDWIG, SARAH | WOODBURY, MN | LPCC | Professional Counselor | 11/07/2015 |
| LUEA, JACQUELINE | NORTH BRANCH, MI | MS CCC-SLP | Speech-Language Pathologist | 09/24/2026 |
| LUERA, ELEAZAR | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| LUERAS, KYLEA | ALAMOGORDO, NM | - | RBT | 12/23/2024 |
| LUETKENS, MICHAEL | CHICAGO, IL | LPC | Professional Counselor | 09/09/2020 |
| LUGGIE, RITA | WALLA WALLA, WA | - | Case Manager/Care Coordinator | 12/16/2015 |
| LUGO, AIMEE | OMAHA, NE | - | Speech-Language Pathologist | 10/03/2023 |
| LUISI, GIANNA | HAMILTON, NJ | MS | Speech-Language Pathologist | 09/25/2026 |
| LUKENDA, TIFFANY | SEATTLE, WA | - | Counselor | 08/23/2024 |
| LUKER, MEGAN | STUART, OK | - | Case Manager/Care Coordinator | 09/24/2026 |
| LUMAR, BRIAN | HARVEY, LA | - | Case Manager/Care Coordinator | 09/23/2026 |
| LUMINA FOX HEALTHCAREORG | LAKE FOREST, CA | - | Community/Behavioral Health Agency | 09/21/2026 |
| LUMORA MENTAL HEALTH & WELLNESS SPA LLCORG | HAMMOND, IN | - | Clinical Social Worker | 09/18/2026 |
| LUMOS THERAPY, LLCORG | NORFOLK, NE | - | Mental Health Counselor | 04/30/2026 |
| LUMPUY, LILIANA | MIAMI, FL | - | Counselor | 09/25/2026 |
| LUNA DELGADO, MARIA | SANTA ROSA, CA | - | RBT | 09/21/2026 |
| LUNA, EMILIANO | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| LUNA, ERICA | DEARBORN, MI | - | RBT | 09/21/2026 |
| LUNA, FRANK | VISALIA, CA | ASW | Clinical Social Worker | 09/24/2026 |
| LUNA, ILISHA | GREENVILLE, SC | - | RBT | 09/25/2026 |
| LUNA, RAYMOND | COVINA, CA | - | Day Training/Habilitation Specialist | 08/14/2025 |
| LUND-RICHARDSON, ASHLIE | DENVER, CO | LCSW, LAC | Addiction (Substance Use Disorder) Counselor | 05/20/2008 |
| LUND, AMY | COLORADO SPRINGS, CO | BS | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| LUNDBORG, ANNA | SANTA ROSA, CA | - | Speech-Language Pathologist | 09/25/2026 |
| LUNDER, CHRISTOPHER | MADISON, WI | - | Professional Counselor | 09/21/2026 |
| LUNDGREN, HAILEY | ONTARIO, CA | - | RBT | 10/10/2024 |
| LUNDIN, FILIPPA | FORT LAUDERDALE, FL | - | Mental Health Counselor | 06/01/2022 |
| LUNETTA, SIENNA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| LUPARDUS, JOSHUA | ALTON, IL | MA, LPC | Mental Health Counselor | 03/31/2021 |
| LUPELOW, ABBIE | EDEN PRAIRIE, MN | - | Mental Health Counselor | 12/08/2025 |
| LUSANE, MAKAYLA | FAYETTEVILLE, NC | - | RBT | 09/23/2026 |
| LUSK, RYLIE | DENVER, CO | - | RBT | 08/01/2022 |
| LUSKY, KARI | IDA, MI | - | Speech-Language Pathologist | 09/24/2026 |
| LUU, TRANG | SAN JOSE, CA | - | Clinical Social Worker | 05/26/2022 |
| LUV AT HOME CARE AND BETTERMENT LLC.ORG | LEHI, UT | - | Day Training/Habilitation Specialist | 01/17/2023 |
| LY, ARIELLE | SACRAMENTO, CA | - | RBT | 09/25/2026 |
| LY, MADELINE | FALLS CHURCH, VA | - | Speech-Language Pathologist | 05/05/2025 |
| LYALL, NADIA | NEW YORK, NY | - | Mental Health Counselor | 02/05/2024 |
| LYKINS, LINDSEY | GREENSBORO, NC | LCSW, MSW | Clinical Social Worker | 06/26/2023 |
| LYNCH, ALEXANDRA | PINE MOUNTAIN, GA | - | Professional Counselor | 09/24/2026 |
| LYNCH, ANA | NAPA, CA | - | BCBA | 05/09/2018 |
| LYNCH, MOLLY | BROOKLINE, MA | LCSW | Clinical Social Worker | 09/21/2026 |
| LYNCH, ROBERT | WILMINGTON, DE | - | RBT | 09/25/2026 |
| LYNETTE KIRK, PLLCORG | DAVENPORT, IA | - | Clinical Social Worker | 07/18/2025 |
| LYNN, ALEXA | FLAGSTAFF, AZ | - | Speech-Language Pathologist | 09/22/2026 |
| LYNN, BARBARA | MIDLOTHIAN, VA | - | Case Manager/Care Coordinator | 09/26/2026 |
| LYNT, MEREDITH | CAMDEN, ME | LCPC-C | Professional Counselor | 02/04/2025 |
| LYON, LISA | BURLINGTON, CT | - | Mental Health Counselor | 06/04/2007 |
| LYONS-SWORD, MOLLY | COLUMBIA, MO | NCC, LPC | Counselor | 05/29/2020 |
| LYONS, BRIDGET | FORT MYERS, FL | LCSW | Clinical Social Worker | 01/02/2015 |
| LYONS, EMMA | MAITLAND, FL | - | RBT | 09/22/2026 |
| LYONS, SACHAE | DENVER, CO | - | Mental Health Counselor | 09/24/2026 |
| M A C T HEALTH BOARD, INCORPORATEDORG | JACKSON, CA | - | Clinic/Center | 09/24/2026 |
| M A C T HEALTH BOARD, INCORPORATEDORG | JACKSON, CA | - | Clinic/Center | 09/24/2026 |
| M A C T HEALTH BOARD, INCORPORATEDORG | SONORA, CA | - | Clinic/Center | 09/24/2026 |
| M S BROWN COUNSELING SERVICES LLCORG | BALTIMORE, MD | - | Clinical Social Worker | 09/11/2020 |
| MAAMO, JENNIFER | TRACY, CA | - | Professional Counselor | 08/09/2022 |
| MAAS, CHARLES | OMAHA, NE | PCMSW | Mental Health Counselor | 01/08/2025 |
| MABE, MYLEIGH | SPRINGFIELD, IL | RBT | RBT | 09/22/2026 |
| MAC FARLANE, DANA | PUEBLO, CO | - | Mental Health Counselor | 09/14/2026 |
| MACDONALD, KATHERINE | BURLINGTON, VT | - | Case Manager/Care Coordinator | 09/24/2026 |
| MACDONALD, LAURA | GLENDALE, AZ | LMSW | Clinical Social Worker | 01/29/2025 |
| MACDOUGALL, EMMA | GRAYSLAKE, IL | LCPC, ATR-BC | Professional Counselor | 08/17/2016 |
| MACE, SIERRA | WEST VALLEY, UT | - | RBT | 09/24/2026 |
| MACEO, PATRICIA | NEW YORK, NY | - | Speech-Language Pathologist | 03/19/2016 |
| MACGREGOR, JENNIFER | CHICOPEE, MA | - | Psychologist | 09/21/2010 |
| MACHADO STEWARD, ARLETIS | DELTONA, FL | - | RBT | 09/26/2026 |
| MACHARIA, ESTHER | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MACHRIS HOME HEALTH SERVICES, INCORG | DALLAS, TX | - | Case Management Agency | 12/28/2006 |
| MACIAS, ALINA | SAN DIEGO, CA | - | RBT | 09/22/2026 |
| MACK, ERICA | PENSACOLA, FL | - | Clinical Social Worker | 06/14/2024 |
| MACK, KATIE | SAINT CLOUD, MN | LICSW | Clinical Social Worker | 03/25/2024 |
| MACK, LAWRENCE | SAN ANTONIO, TX | LPC | Professional Counselor | 08/05/2009 |
| MACK, NIKECIA | FAYETTEVILLE, NC | - | RBT | 09/25/2026 |
| MACK, RICHARD | NEW YORK, NY | LCSW | Clinical Social Worker | 06/16/2006 |
| MACKENDRICK, LOGAN | DAYTON, OH | - | RBT | 09/23/2026 |
| MACKIN, CASSANDRA | GRANITE CITY, IL | MSW | Counselor | 11/14/2022 |
| MACKLIN, LATOYA | LAS VEGAS, NV | - | RBT | 09/22/2026 |
| MACLEOD, TINA | KINGSTON, PA | - | BCBA | 09/23/2026 |
| MACWHORTER, SEAN | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| MADDEN, BRIONNA | BROOKLYN, NY | - | RBT | 09/24/2026 |
| MADDEN, JENNIE | PINEHURST, NC | BCBA | BCBA | 04/01/2025 |
| MADDEN, MALYIA | MONCKS CORNER, SC | - | Counselor | 09/22/2026 |
| MADER, JENNIFER | WAKARUSA, KS | - | Speech-Language Pathologist | 09/24/2026 |
| MADIGAN - PEREA, MIA | ALCALDE, NM | BT | RBT | 05/25/2023 |
| MADISON, TAMARA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MADORCARE LLCORG | FORT WORTH, TX | - | Clinical Social Worker | 02/15/2024 |
| MADRID, TAYLOR | APPLE VALLEY, CA | - | BCBA | 09/24/2026 |
| MADRIGAL, DAVID | TACOMA, WA | - | Clinical Social Worker | 09/22/2026 |
| MADSON, MELIA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MADUENA, MARIA | INDIO, CA | LCSW | Clinical Social Worker | 09/26/2006 |
| MAERTENS, LEVANDER | SEATAC, WA | - | Mental Health Counselor | 06/07/2023 |
| MAESTAS, KORINA | FLAGSTAFF, AZ | M.ED, BCBA, LBA | BCBA | 11/27/2017 |
| MAFI, JESSICA | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| MAGANA CAMACHO, ALEXIS | GRANITE BAY, CA | - | RBT | 09/21/2026 |
| MAGAR, BOB | OKLAHOMA CITY, OK | - | Addiction (Substance Use Disorder) Counselor | 08/19/2021 |
| MAGDALENO, JESSE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MAGEE, CORIN | YPSILANTI, MI | - | Psychologist | 09/22/2026 |
| MAGEE, LEHMONIQUE | MINOT, ND | - | Case Manager/Care Coordinator | 09/25/2026 |
| MAGEE, ROXANA | SAN DIEGO, CA | MS, CCC-SLP | Speech-Language Pathologist | 11/28/2019 |
| MAGGI, MARCO | LOS ALAMITOS, CA | AMFT, APCC | Counselor | 04/03/2024 |
| MAGHAM, SUNEETHA | SAN RAMON, CA | - | RBT | 09/21/2026 |
| MAGLIARI, RACHEL | BOISE, ID | LPC | Professional Counselor | 05/16/2017 |
| MAGLOIRE, MIKEL | KILLEEN, TX | - | RBT | 08/31/2026 |
| MAGNOLIA GROVE BEHAVIORAL SERVICES LLCORG | FAIRFAX, VA | - | BCBA | 09/21/2026 |
| MAGSAYO, NORIEL | MANTECA, CA | - | RBT | 09/25/2026 |
| MAHADY, KARI | LAKEWOOD, CO | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| MAHARG, ANGELA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| MAHARJAN, ANANYA | THORNTON, CO | - | RBT | 09/23/2026 |
| MAHATHRE, VERONICA | ATLANTA, GA | LPC | Mental Health Counselor | 09/22/2026 |
| MAHER, MATTHEW | KINGSTON, NY | PHD, LMHC | Mental Health Counselor | 03/24/2014 |
| MAHER, MEGHAN | DENVER, CO | - | BCBA | 11/04/2020 |
| MAHONEY, AMBER | CONCORD, CA | - | Speech-Language Pathologist | 09/25/2026 |
| MAHONEY, COLLIN | CLEVELAND, OH | CT | Mental Health Counselor | 09/24/2026 |
| MAHONEY, JENNIFER | SALISBURY, MD | LGPC | Counselor | 09/23/2026 |
| MAI HEAVEN LLCORG | DURHAM, NC | - | Community/Behavioral Health Agency | 09/22/2026 |
| MAI, JACQUELINE | PORTLAND, OR | - | Mental Health Counselor | 04/26/2021 |
| MAIN, EMILY | OKMULGEE, OK | - | Speech-Language Pathologist | 09/21/2026 |
| MAINI, ABHINEET | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MAINKA TELETHERAPY SERVICES, LLCORG | VICKSBURG, MS | - | Mental Health Counselor | 01/25/2024 |
| MAIO, KAMERYN | FREEHOLD, NJ | - | Mental Health Counselor | 09/22/2026 |
| MAJIDAH AMEERA HOSEIN LLCORG | AURORA, CO | - | Mental Health Counselor | 09/25/2026 |
| MAJOR, CHANTELLE | CHARLOTTE, NC | LCMHC-A | Mental Health Counselor | 09/30/2022 |
| MAKIN, JOEL | LA FONTAINE, IN | LMHC | Mental Health Counselor | 07/28/2011 |
| MAKOWSKI, LORI | BRIGHTON, MI | - | Speech-Language Pathologist | 09/25/2026 |
| MAKSIMAVA, KATSIARYNA | COLUMBIA HEIGHTS, MN | LPCC | Professional Counselor | 12/13/2021 |
| MALACINA, MARSHA | LAFAYETTE, IN | - | BCBA | 09/22/2026 |
| MALARICH, TAMMIE | YOUNGSTOWN, OH | LCMHCA | Mental Health Counselor | 09/22/2026 |
| MALDONADO ALONZO, JOHN | COSTA MESA, CA | - | RBT | 09/23/2026 |
| MALDONADO, BRANDY | TUSCUMBIA, AL | - | RBT | 12/19/2025 |
| MALDONADO, JULIE | THORNTON, CO | - | Counselor | 11/10/2021 |
| MALDONADO, JULISA | TURLOCK, CA | - | Clinical Social Worker | 09/24/2026 |
| MALDONADO, MARRYAH | WINTON, CA | - | RBT | 09/24/2026 |
| MALDONADO, MYA | MISSION, KS | - | RBT | 09/25/2026 |
| MALDONADO, VIVICA | SANDY, UT | RBT | RBT | 01/31/2023 |
| MALIK, FARAZ | WEST CHESTER, OH | - | Mental Health Counselor | 09/24/2026 |
| MALIK, MAHA | AUGUSTA, NJ | - | RBT | 09/22/2026 |
| MALMAN, ERIN | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MALONE, KATIE | NEWTON, MA | - | RBT | 02/10/2025 |
| MALONE, SARFINA | HUNTSVILLE, AL | - | RBT | 09/22/2026 |
| MALONEY, ADAM | ASHBY, MA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| MALPICA RAMIREZ, ISRAEL | LITTLETON, CO | - | Mental Health Counselor | 09/23/2026 |
| MALTA, JOSE | NORTH HOLLYWOOD, CA | - | Mental Health Counselor | 09/21/2026 |
| MANCEBO DIAZ, LIANET | TAMPA, FL | - | RBT | 09/15/2025 |
| MANCERA, KATHERINE | OAKLAND, CA | LMFT | Mental Health Counselor | 05/20/2020 |
| MANCL, LACEY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MANDALA CLINICAL, LLC.ORG | WICHITA, KS | - | Clinical Social Worker | 08/07/2024 |
| MANDELBAUM, OLIVIA | NORWALK, CT | PH.D. | Psychologist | 08/06/2019 |
| MANFRE, SAMUEL | GREENVILLE, NC | - | Clinical Social Worker | 09/21/2026 |
| MANGUS, KATIE | FARMINGTON HILLS, MI | CCC-SLP/L | Speech-Language Pathologist | 09/23/2026 |
| MANISCALCO, LARAE | LOS LUNAS, NM | - | RBT | 09/25/2026 |
| MANITEAU, CARI | MOUNT PLEASANT, MI | MA, LPC, CAADC | Professional Counselor | 04/26/2015 |
| MANIU, KRYSTINA | PALM DESERT, CA | MS | Counselor | 06/18/2017 |
| MANLEY, JOLINA | OMAHA, NE | - | Case Manager/Care Coordinator | 06/04/2025 |
| MANNING, KALANI | SACRAMENTO, CA | - | RBT | 07/07/2026 |
| MANNIX, PETER | FREDERICK, MD | - | RBT | 09/21/2026 |
| MANON DEL ROSARIO, ROOSBERT | EL PASO, TX | - | RBT | 09/21/2026 |
| MANRIQUEZ, JHONATAN | MODESTO, CA | - | RBT | 09/25/2026 |
| MANZO, TRISHIA | ANCHORAGE, AK | CCM | Counselor | 03/22/2017 |
| MAO, ABBYELLA | LAKE FOREST, CA | - | RBT | 09/23/2026 |
| MAPLE COUNSELING & WELLNESS LLCORG | WINDSOR LOCKS, CT | - | Professional Counselor | 08/05/2026 |
| MAPLES, CHRISTINA | MILWAUKIE, OR | - | Clinical Social Worker | 09/24/2020 |
| MAR, ITZEL | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| MARANTO, ELIZABETH | CHICAGO, IL | LCPC | Professional Counselor | 04/12/2021 |
| MARATHON HEALTH, LLCORG | INDIANAPOLIS, IN | - | Clinic/Center | 09/22/2026 |
| MARBURGER, ANDREA | RICHMOND, VA | LCSW | Clinical Social Worker | 08/13/2018 |
| MARCANO RIVERA, ANDREA | CLERMONT, FL | SLP | Speech-Language Pathologist | 09/23/2026 |
| MARCELIN, ANAELLE | MIRAMAR, FL | - | Clinical Social Worker | 05/15/2013 |
| MARCHAND, JESSICA | MONROE, LA | LPC-S, LMFT-S | Professional Counselor | 09/30/2015 |
| MARCHETERRE, JULIA | FRAMINGHAM, MA | LCSW | Clinical Social Worker | 06/11/2026 |
| MARCHETTI, MEGAN | GREENWOOD VILLAGE, CO | LPC | Professional Counselor | 09/14/2019 |
| MARCHIOL, LOGAN | PARKER, CO | LPC | Counselor | 07/31/2024 |
| MARCIAL, GLADYS | SANGER, CA | - | Clinical Social Worker | 05/16/2024 |
| MARCIAL, MARIA | FULLERTON, CA | - | RBT | 09/24/2026 |
| MARCIANO, DANIELA | DURHAM, NC | LCSWA | Clinical Social Worker | 09/21/2026 |
| MARCOUILLER, NICOLE | MAPLE GROVE, MN | MSW, LICSW | Clinical Social Worker | 01/10/2018 |
| MARCUM, JAMIE | LOGAN, WV | - | Case Manager/Care Coordinator | 01/06/2023 |
| MARDINI, RASHA | TARZANA, CA | PSYD | Psychologist | 08/27/2015 |
| MARHEFKE, RAQUEL | NEENAH, WI | - | Professional Counselor | 05/15/2024 |
| MARIANNE POTVIN, LICSW, PCORG | CAMBRIDGE, MA | - | Clinical Social Worker | 09/14/2026 |
| MARIE CAREY COUNSELING & CONSULTATION, PLLCORG | MORGANTON, NC | - | Mental Health Counselor | 09/21/2026 |
| MARIE, KACIE | SEATTLE, WA | MS, MA, LMHCA | Mental Health Counselor | 04/09/2020 |
| MARIGOLD MENTAL WELLNESSORG | WILMINGTON, DE | - | Mental Health Counselor | 03/11/2026 |
| MARINELLI, ELYSE | LOUISVILLE, CO | LCSW | Clinical Social Worker | 09/23/2026 |
| MARING-HEW, ALYSSA | KAPOLEI, HI | - | Mental Health Counselor | 09/21/2026 |
| MARINO PEREZ, LILIBETH | MIAMI, FL | - | RBT | 08/06/2021 |
| MARIS, ANNE | SPRING, TX | LPC-ASSOCIATE | Professional Counselor | 09/24/2026 |
| MARISCAL, JAMIE | SANTA ROSA, CA | - | Speech-Language Pathologist | 09/21/2026 |
| MARK DEAN LOVING PLACE HCS INCORG | RED OAK, TX | - | Community/Behavioral Health Agency | 08/24/2020 |
| MARK MCDONALD P.T., P.C.ORG | STERLING, CO | - | Speech-Language Pathologist | 10/04/2006 |
| MARKHAM, DJORDIN | PHOENIX, AZ | - | RBT | 09/21/2026 |
| MARKING, ELENA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| MARKINS, DONALD | PARKERSBURG, WV | PRSS | Counselor | 07/28/2022 |
| MARKS, KAREN | ORANGE, CA | LCSW | Clinical Social Worker | 10/13/2006 |
| MARKUMAS-VIERA, OLGA | SCARSDALE, NY | LMHC | Mental Health Counselor | 08/20/2020 |
| MARLA V. CLOUSE CORPORG | WICHITA, KS | - | Clinical Social Worker | 04/18/2023 |
| MARQUEZ-GONZALEZ, ABIGAIL | MIDVALE, UT | CSWI | Mental Health Counselor | 05/03/2013 |
| MARQUEZ, ALEXIS | EL PASO, TX | - | Mental Health Counselor | 09/23/2026 |
| MARQUEZ, ASHLEY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| MARQUEZ, VALENTINA | LA PALMA, CA | - | BCBA | 09/22/2026 |
| MARQUINEZ, NICOLE | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| MARRA, ALYSSA | STATEN ISLAND, NY | - | Addiction (Substance Use Disorder) Counselor | 12/17/2018 |
| MARRERO TOLEDO, ERNESTO | PORT SAINT LUCIE, FL | - | RBT | 07/24/2023 |
| MARRIAGE RESOURCE CENTER, LLCORG | CLARKS SUMMIT, PA | - | Counselor | 09/24/2026 |
| MARRIOTT, LANDON | BERKELEY, CA | - | Clinical Social Worker | 07/10/2017 |
| MARRON, SERGIO | FRENCH CAMP, CA | LCSW | Clinical Social Worker | 08/22/2013 |
| MARROQUIN, KAYLA | DOWNEY, CA | - | RBT | 09/24/2026 |
| MARROW, CHRISTINA | TYLER, TX | LPC | Professional Counselor | 10/10/2018 |
| MARSH, JUSTIN | LAS CRUCES, NM | LCSW | Clinical Social Worker | 02/21/2025 |
| MARSH, KELLIE | TULLAHOMA, TN | APRN | Assistant Behavior Analyst | 05/05/2017 |
| MARSHALL-BOGDAN, LORI | LA VISTA, NE | CNA, MEDICATION AIDE | RBT | 04/14/2025 |
| MARSHALL, ISHANI | CYPRESS, TX | - | RBT | 09/24/2026 |
| MARSTON, KALA | BROOKLYN, NY | - | RBT | 09/23/2026 |
| MARSTON, MADELYN | ST CHARLES, IL | - | Speech-Language Pathologist | 08/07/2023 |
| MARTIN DEL CAMPO GARCIA, ELVIA | SANTA ANA, CA | - | Day Training/Habilitation Specialist | 08/06/2025 |
| MARTIN, ADRIANNA | HENDERSONVILLE, TN | - | RBT | 09/21/2026 |
| MARTIN, ALI | IRONTON, OH | CDCA | Case Manager/Care Coordinator | 07/15/2022 |
| MARTIN, AMAYA | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| MARTIN, AMBER | BROOKHAVEN, MS | LPC | Professional Counselor | 10/02/2014 |
| MARTIN, ASHILI | PINEHURST, NC | - | RBT | 09/22/2026 |
| MARTIN, ASHLEY | FORT WAYNE, IN | RBT | RBT | 09/03/2020 |
| MARTIN, AZJAYA | COON RAPIDS, MN | - | RBT | 09/25/2026 |
| MARTIN, BAILEY | SPRING HOPE, NC | - | Clinical Social Worker | 09/22/2026 |
| MARTIN, BROOKLYN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MARTIN, CHRIS | POPLAR BLUFF, MO | LCSW | Clinical Social Worker | 01/10/2014 |
| MARTIN, COURTENEY | LIHUE, HI | - | Clinical Social Worker | 10/12/2022 |
| MARTIN, DEVON | SANTA ANA, CA | - | RBT | 09/21/2026 |
| MARTIN, DIAMOND | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MARTIN, HAILEY | PLYMOUTH, MI | - | RBT | 09/24/2026 |
| MARTIN, HANNAH | CHATTANOOGA, TN | LCSW | Clinical Social Worker | 08/05/2021 |
| MARTIN, JACI | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MARTIN, JANET | SANTA CRUZ, CA | - | Mental Health Counselor | 04/18/2007 |
| MARTIN, KALLI | ROSCOMMON, MI | - | Speech-Language Pathologist | 09/22/2026 |
| MARTIN, KEITH | WASHINGTON, DC | - | Counselor | 10/08/2025 |
| MARTIN, KIARA | GREENVILLE, NC | - | BCBA | 12/16/2021 |
| MARTIN, MAUREEN | ARDEN, NC | LCAS | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| MARTIN, MISHAIUEL | TORRANCE, CA | - | Day Training/Habilitation Specialist | 09/14/2018 |
| MARTIN, NATHAN | SPOKANE, WA | - | Mental Health Counselor | 01/12/2026 |
| MARTIN, NICHOLAS | PHOENIX, AZ | - | BCBA | 07/14/2026 |
| MARTIN, NIVIA | KENAI, AK | - | Mental Health Counselor | 09/23/2026 |
| MARTIN, RILEY | HUNTINGTON BEACH, CA | - | RBT | 09/25/2026 |
| MARTIN, SKYLAR | BROKEN ARROW, OK | - | Case Manager/Care Coordinator | 09/25/2026 |
| MARTIN, TERI | APPLE VALLEY, CA | - | Mental Health Counselor | 07/01/2010 |
| MARTINEZ HERNANDEZ, BRENDA | RIVERBANK, CA | - | RBT | 09/24/2026 |
| MARTINEZ MARRERO, AMANDA | LAKELAND, FL | - | RBT | 09/21/2026 |
| MARTINEZ RAMIREZ, BRENDA | CALABASAS, CA | - | BCBA | 09/25/2026 |
| MARTINEZ, ALAYNA | WYOMISSING, PA | - | RBT | 09/23/2026 |
| MARTINEZ, ALICE | BARTLESVILLE, OK | - | Case Manager/Care Coordinator | 05/19/2025 |
| MARTINEZ, ANGELINA | LAKEWOOD, CO | - | RBT | 07/27/2026 |
| MARTINEZ, ANTOINETTE | ALBUQUERQUE, NM | CCC-SLP | Speech-Language Pathologist | 03/28/2007 |
| MARTINEZ, BRENDA | OXNARD, CA | - | Case Manager/Care Coordinator | 12/27/2017 |
| MARTINEZ, CARLOS | PUEBLO, CO | - | RBT | 09/23/2026 |
| MARTINEZ, CYNTHIA | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| MARTINEZ, CYNTHIA | SACRAMENTO, CA | - | Mental Health Counselor | 08/18/2014 |
| MARTINEZ, DAMARIS | ANAHEIM, CA | - | RBT | 09/23/2026 |
| MARTINEZ, ELYSSA | IMPERIAL, CA | ASSOCIATE'S DEGREE | RBT | 09/21/2026 |
| MARTINEZ, EVAN | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MARTINEZ, EVELYN | VICTORVILLE, CA | - | RBT | 09/22/2026 |
| MARTINEZ, GERZAIN | HENDERSON, NV | - | RBT | 09/21/2026 |
| MARTINEZ, JACKLYN | NAPERVILLE, IL | LPC | Professional Counselor | 07/25/2024 |
| MARTINEZ, JENNIFER | FRESNO, CA | - | Addiction (Substance Use Disorder) Counselor | 01/24/2024 |
| MARTINEZ, KAYLA | COVINA, CA | - | RBT | 04/30/2024 |
| MARTINEZ, KYRI | YUCCA VALLEY, CA | - | Day Training/Habilitation Specialist | 02/09/2024 |
| MARTINEZ, LIBERTY | CONCORD, CA | - | RBT | 09/23/2026 |
| MARTINEZ, MORGAN | LA PALMA, CA | - | RBT | 05/05/2025 |
| MARTINEZ, MYA | PUEBLO, CO | - | RBT | 09/22/2026 |
| MARTINEZ, NIKOLAS | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MARTINEZ, NINA | EL CAJON, CA | - | RBT | 09/21/2026 |
| MARTINEZ, RAUL | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| MARTINEZ, SILVIA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| MARTINEZ, SOPHIA | MONTEREY PARK, CA | - | RBT | 09/21/2026 |
| MARTINEZ, SORPRISELA | MODESTO, CA | - | RBT | 01/10/2024 |
| MARTINEZ, VINCENT | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MARTINEZ, XITLHALY | LYNN, MA | - | RBT | 05/14/2024 |
| MARTINEZ, YADIRA | PASADENA, CA | - | Case Manager/Care Coordinator | 11/04/2016 |
| MARTINS, TIA | LOMBARD, IL | - | BCBA | 07/02/2019 |
| MARTUS, MACKENZIE | DANVILLE, VA | - | RBT | 09/25/2026 |
| MARVA C WILLIAMS, LPC & ASSOCIATESORG | KNOXVILLE, TN | - | Professional Counselor | 09/25/2026 |
| MARY T HOME HEALTH INCORG | COON RAPIDS, MN | - | Speech-Language Pathologist | 02/13/2008 |
| MARZ, JOHN | WEST PALM BEACH, FL | LMHC, MCAP | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MARZULLA, AMY | ANN ARBOR, MI | LMSW | Clinical Social Worker | 11/24/2013 |
| MAS, AMANDA | MIAMI, FL | - | Assistant Behavior Analyst | 09/07/2023 |
| MASELLI, NANCYLYNN | CLINTON, CT | LADC | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| MASKING GREATNESS PLLCORG | MAGNOLIA, TX | - | Mental Health Counselor | 09/25/2026 |
| MASON, JESSICA | ISHPEMING, MI | MA CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| MASON, LORIEN | DAYTON, OH | LPCC | Professional Counselor | 03/03/2014 |
| MASON, NATASHA | BLYTHEWOOD, SC | - | BCBA | 09/22/2026 |
| MASON, OLIVIA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| MASONIS, NICOLAS | NEWPORT BEACH, CA | SUDRC | RBT | 09/23/2026 |
| MASONIS, ROBERT | NEWPORT BEACH, CA | - | RBT | 09/23/2026 |
| MASRI, BRANDON | BROOKLYN, NY | LMSW | Clinical Social Worker | 09/25/2026 |
| MASSO, SANDRA | WESLACO, TX | - | BCBA | 12/14/2022 |
| MASSON, JOCELYN | EASTHAMPTON, MA | LMHC | Counselor | 08/28/2016 |
| MAST, CARLYN | BALTIMORE, MD | LCSW | Clinical Social Worker | 08/09/2019 |
| MASTON, ALYSSA | KOKOMO, IN | - | RBT | 09/24/2026 |
| MASTRAPA SABATER, YANICEL | MIAMI, FL | - | RBT | 09/16/2021 |
| MATEOS, LUIS | LA MESA, CA | - | RBT | 09/23/2026 |
| MATHENY, ADRIENNE | VALLEY CITY, ND | - | Professional Counselor | 05/07/2026 |
| MATHEW, RYAN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MATHEWS, COURTNEY | FRANKLIN, IN | LCSW, LCAC | Clinical Social Worker | 07/30/2020 |
| MATHEWS, JOHN | MIDLOTHIAN, VA | LCSW | Clinical Social Worker | 04/03/2015 |
| MATHIESON, BRADY | SEATTLE, WA | LMHCA | Professional Counselor | 04/13/2026 |
| MATHURA, DAVINA | BRONX, NY | M.S.CCC-SLP | Speech-Language Pathologist | 06/08/2017 |
| MATOS, TAMIRES | LOWELL, MA | LCSW | Clinical Social Worker | 03/24/2020 |
| MATOUSEK, MELISSA | BONITA SPRINGS, FL | LCSW | Clinical Social Worker | 05/14/2018 |
| MATSCH, CHERYL | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MATTHEWS, ADRIENNE | BURLESON, TX | - | Mental Health Counselor | 09/24/2026 |
| MATTHEWS, EMILY | PROVIDENCE, RI | - | Mental Health Counselor | 07/14/2016 |
| MATTHEWS, JESSICA | STILWELL, OK | - | Case Manager/Care Coordinator | 09/24/2026 |
| MATTHEWS, KIMBERLY | LA PINE, OR | - | Mental Health Counselor | 05/07/2025 |
| MATTHEWS, LISA | HERSHEY, PA | - | Professional Counselor | 09/21/2026 |
| MATTHEWS, MCKAYLA | GREENWOOD VILLAGE, CO | - | RBT | 09/24/2026 |
| MATTHEWS, NYKESHA | CONCORD, NC | - | BCBA | 11/16/2020 |
| MATTHEWS, RICHANNE | TINLEY PARK, IL | - | Psychologist | 09/21/2026 |
| MATTHEWS, ROOSEVELT | BATON ROUGE, LA | - | Case Manager/Care Coordinator | 04/17/2023 |
| MATTICE, JULIA | SAINT JOSEPH, MI | - | RBT | 09/23/2026 |
| MATTICK, QUINCIE | POCATELLO, ID | LMSW | Clinical Social Worker | 09/25/2026 |
| MAUCH, CAROLYN | PAHRUMP, NV | - | BCBA | 03/19/2015 |
| MAUFF, LEAH | AURORA, CO | LAC | Professional Counselor | 11/11/2021 |
| MAUGER, DEZERAY | NORTH PORT, FL | - | RBT | 01/23/2026 |
| MAULANA, SHALE | BROOKLYN, NY | MPH | Clinical Social Worker | 09/16/2022 |
| MAURER, AUDREY | SANTA ANA, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| MAURICIO, DIANA | ADDISON, TX | - | Professional Counselor | 09/24/2026 |
| MAUSE HOME & COMMUNITY HEALTHCARE LLCORG | CANTON, MA | - | Case Manager/Care Coordinator | 09/24/2026 |
| MAUTHE, MALLORY | EUGENE, OR | - | Counselor | 09/22/2026 |
| MAXIM HEALTHCAREORG | LAKE ELSINORE, CA | - | RBT | 09/21/2026 |
| MAXWELL, JACKSON | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MAXWELL, MOLLY | SILVER SPRING, MD | - | RBT | 09/22/2026 |
| MAY, ALEXANDRIA | LAKEVILLE, MN | - | Mental Health Counselor | 09/21/2026 |
| MAY, JOHN | STANTON, CA | - | Addiction (Substance Use Disorder) Counselor | 03/27/2024 |
| MAY, KATELYN | CROFTON, MD | - | RBT | 09/21/2026 |
| MAY, MARCELLUS | LAKEWOOD, WA | - | Mental Health Counselor | 06/23/2025 |
| MAY, MELISSA | BANGOR, ME | LCPC-C | Professional Counselor | 09/22/2026 |
| MAY, NICOLE | SPRINGFIELD, MO | MS, LPC | Professional Counselor | 05/30/2024 |
| MAY, PIPER | HUNTINGTON, WV | - | RBT | 09/23/2026 |
| MAYER, CHRISTINE | CHAMPAIGN, IL | LCSW | Clinical Social Worker | 08/12/2006 |
| MAYER, LAUREN | ROCK SPRINGS, WY | - | Clinical Social Worker | 02/20/2019 |
| MAYFIELD, CASEY | COLTON, CA | - | Case Manager/Care Coordinator | 09/24/2026 |
| MAYNARD, BAILEY | MORRISTOWN, TN | - | Speech-Language Pathologist | 09/23/2026 |
| MAYNARD, SAMANTHA | NORMAN, OK | - | Speech-Language Pathologist | 09/21/2026 |
| MAYORAL, CLARA | ROCKVILLE CENTRE, NY | MD | Specialist | 03/23/2006 |
| MAYORGA, JACQUELINE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MAYS, RECHELE | LITTLE ROCK, AR | LCSW | Clinical Social Worker | 09/03/2010 |
| MAYS, SALLY | PANAMA CITY, FL | - | RBT | 09/25/2026 |
| MAZELIN, ESPERANZA | MISHAWAKA, IN | - | RBT | 09/22/2026 |
| MBUGUA, IRENE | LYNNWOOD, WA | - | RBT | 09/25/2026 |
| MC CARGO, SELINA | BALTIMORE, MD | - | RBT | 09/22/2026 |
| MC CREATH, JAMES | JERSEY CITY, NJ | MSW | Clinical Social Worker | 10/18/2006 |
| MCANINCH, FIONA | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| MCAULEY, JESSICA | MAHOPAC, NY | M.A., CCC-SLP, TSSLD | Speech-Language Pathologist | 10/26/2008 |
| MCBRIDE, LAUREN | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MCCALL, ORION | DENVER, CO | - | RBT | 09/21/2026 |
| MCCALLISTER, KLOWIE | ROSEVILLE, CA | - | Speech-Language Pathologist | 09/22/2026 |
| MCCAMMON, RACHEL | FARMINGTON, UT | RBT | RBT | 09/24/2026 |
| MCCARNEY, CHRISTINE | SANDWICH, IL | MS | Speech-Language Pathologist | 09/25/2026 |
| MCCARTER, ADRIEN | LEHIGH ACRES, FL | - | RBT | 09/21/2026 |
| MCCARTHY, MEGAN | MATHER, CA | PH.D. | Psychologist | 08/18/2008 |
| MCCARTHY, RIKKI LYN | HILLSBOROUGH, NJ | DBH, LCSW | Clinical Social Worker | 02/25/2019 |
| MCCARTHY, SANDRA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MCCARTY, SYLVIA | LOUISVILLE, KY | LCSW | Clinical Social Worker | 07/28/2006 |
| MCCASLAND, CAYCE | CHARLESTON, WV | - | Case Manager/Care Coordinator | 09/22/2026 |
| MCCLAIN, GENESIS | STOCKBRIDGE, GA | - | RBT | 09/21/2026 |
| MCCLOY, HOLLY | MARTINSBURG, WV | MA, NCC | Mental Health Counselor | 07/23/2024 |
| MCCLURE, DIANA | NEW CASTLE, PA | LCSW | Clinical Social Worker | 08/22/2022 |
| MCCLURE, MOLLY | VANDERBILT, PA | - | Speech-Language Pathologist | 09/21/2026 |
| MCCOLLOUGH, SHIANN | WASHINGTON, DC | LPC, NCC | Professional Counselor | 02/21/2024 |
| MCCOLLUM, TAJAI | BATON ROUGE, LA | - | Professional Counselor | 07/24/2023 |
| MCCOLM, AUTUMN | MONUMENT, CO | - | RBT | 09/21/2026 |
| MCCOMAS, GRACIE | BATESVILLE, AR | - | Day Training/Habilitation Specialist | 09/22/2026 |
| MCCORMACK, ISABELLA | VALLEY STREAM, NY | - | Mental Health Counselor | 09/22/2026 |
| MCCORMICK, CHRISTY | CRESWELL, OR | - | Mental Health Counselor | 03/24/2025 |
| MCCORMICK, JENNA | WEST POINT, VA | LCSW | Clinical Social Worker | 03/28/2025 |
| MCCORMICK, MACY | EAU CLAIRE, WI | - | Speech-Language Pathologist | 08/13/2026 |
| MCCORMICK, MELODY | TAR HEEL, NC | - | RBT | 09/23/2026 |
| MCCOWIN, MICAH | ROMULUS, MI | - | RBT | 09/21/2026 |
| MCCOY PSYCHOLOGICAL SERVICESORG | GRUNDY CENTER, IA | - | Psychologist | 09/25/2026 |
| MCCOY, MARKITA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| MCCOY, MOLLY | WOODBURY, MN | - | RBT | 09/25/2026 |
| MCCOY, SHAYDA | GLENDALE, CA | - | RBT | 09/23/2026 |
| MCCOY, TAMATHA | MARIETTA, GA | LCSW | Clinical Social Worker | 09/22/2026 |
| MCCULLAGH, ELLIE | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MCCULLOCH, BRITTNEY | SAN ANGELO, TX | LPC-A | Professional Counselor | 09/01/2022 |
| MCCULLOCH, JENNIFER | BLACK DIAMOND, WA | - | RBT | 09/25/2026 |
| MCCULLY, ELIZABETH | SEATTLE, WA | LICSW | Clinical Social Worker | 09/25/2024 |
| MCCURDY, MARSHA | HAYDEN, ID | LCPC-8208 | Mental Health Counselor | 05/16/2018 |
| MCCUTCHEON, SARAH | EAU CLAIRE, WI | MS | Professional Counselor | 07/24/2023 |
| MCDAID, JAMIE | LEXINGTON, MA | - | Mental Health Counselor | 09/25/2026 |
| MCDANIEL, CAMILLE | MARIETTA, GA | LPC | Professional Counselor | 05/27/2009 |
| MCDANIEL, ERIN | CORBIN, KY | - | Case Manager/Care Coordinator | 09/22/2026 |
| MCDANIEL, HANNAH | SALT LAKE CITY, UT | PHD, MS | Psychologist | 05/26/2026 |
| MCDANIEL, MADELINE | RALEIGH, NC | - | Clinical Social Worker | 07/23/2024 |
| MCDANIEL, PAMELA | MENIFEE, CA | - | RBT | 09/21/2026 |
| MCDERMID, DARYN | BEAVERTON, OR | MS, NCC | Mental Health Counselor | 01/17/2024 |
| MCDERMOTT, SARAH | LORAIN, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MCDONALD, CYNTHIA | CAMAS, WA | - | Mental Health Counselor | 09/22/2026 |
| MCDONALD, DUSTIN | PARKERSBURG, WV | - | Counselor | 09/21/2026 |
| MCDONALD, EMILY | FREMONT, CA | - | Mental Health Counselor | 09/05/2013 |
| MCDONALD, HOLLY | ASHEVILLE, NC | LCSW | Clinical Social Worker | 03/10/2010 |
| MCDONALD, JARIA | WACO, TX | - | RBT | 09/21/2026 |
| MCDONALD, JORDAN | MOORE, OK | - | RBT | 09/23/2026 |
| MCDONOUGH, JAIMI | CHAPEL HILL, NC | PHD | Psychologist | 08/22/2017 |
| MCDOWELL, PATRICK | NORTH HOLLYWOOD, CA | CADC-II | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| MCELFRESH, MARIEL | DYER, IN | LCSW | Clinical Social Worker | 02/04/2026 |
| MCELROY, CRAIG | SPOKANE, WA | LMHC, SUDP, BACC | Mental Health Counselor | 04/19/2017 |
| MCFADDEN, COREY | FLORENCE, SC | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MCFARLAND, BETH | CENTRALIA, IL | - | Counselor | 09/25/2026 |
| MCFARLIN, SHEEVA | CLINTON, SC | LISW | Clinical Social Worker | 10/18/2012 |
| MCFARLIN, TANYA | OMAHA, NE | - | Mental Health Counselor | 09/24/2026 |
| MCGEE, DIANA | CARDIFF, CA | SUDCC II | Addiction (Substance Use Disorder) Counselor | 02/06/2019 |
| MCGEE, EMMA | ROUND ROCK, TX | - | Counselor | 09/23/2026 |
| MCGEE, JOLAILA | METAIRIE, LA | - | BCBA | 09/25/2026 |
| MCGEE, RIKIYAH | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| MCGILL, LILY | WICHITA, KS | - | RBT | 09/22/2026 |
| MCGINNIS-COOPER, J'AIME | SHELTON, WA | LICSW | Clinical Social Worker | 01/09/2025 |
| MCGIVERN, JACQUELINE | PORTLAND, OR | - | Professional Counselor | 10/13/2022 |
| MCGOUGH, JENNIFER | ALBUQUERQUE, NM | LPCC, LADAC | Professional Counselor | 10/10/2011 |
| MCGOVERN, HANNAH | HARRISON, NY | - | Counselor | 09/21/2026 |
| MCGOWAN, ANNA | EL CAJON, CA | - | Speech-Language Pathologist | 09/22/2026 |
| MCGOWAN, JULIE | SEATTLE, WA | LSWAIC | Clinical Social Worker | 11/06/2020 |
| MCGOWAN, RAVYN | FORT WAYNE, IN | - | RBT | 09/24/2026 |
| MCGRAW, MALORIE | MARQUETTE, MI | CCC-SLP | Speech-Language Pathologist | 06/25/2009 |
| MCGREEVY, BRIDGET | GREENWOOD VILLAGE, CO | - | Mental Health Counselor | 08/02/2025 |
| MCGREW, REBEKAH | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| MCGUIRE, CASSANDRA | BARSTOW, CA | - | Assistant Behavior Analyst | 09/26/2026 |
| MCGUIRE, EMILY | ANN ARBOR, MI | MA, CCC-SLP | Speech-Language Pathologist | 02/22/2025 |
| MCGUIRE, JENNIFER | STRONGSVILLE, OH | - | Case Manager/Care Coordinator | 04/10/2026 |
| MCHENRY, ELLA | FEDERAL WAY, WA | CDP | Addiction (Substance Use Disorder) Counselor | 08/15/2007 |
| MCHENRY, LAUREN | MERRIAM, KS | M. ED, BCBA, LBA | BCBA | 07/21/2016 |
| MCHUGH AKBAR, KATHLEEN | WILMETTE, IL | LCSW | Clinical Social Worker | 03/28/2020 |
| MCHUGH MULLANE, SIOBHAN | BRIDGEWATER, MA | - | Clinical Social Worker | 12/02/2015 |
| MCINTYRE COUNSELING SERVICES, LLCORG | CARMEL, IN | - | Mental Health Counselor | 09/21/2026 |
| MCINTYRE, JAMES | HAYWARD, CA | - | RBT | 08/07/2023 |
| MCINTYRE, LISA | HOWELL, MI | - | Clinical Social Worker | 09/25/2026 |
| MCINTYRE, LYDIA | WAUSAU, WI | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| MCKEE, RHIANNON | NORTH RIDGEVILLE, OH | - | Clinical Social Worker | 07/25/2023 |
| MCKEEHAN, TIFFINEY | METLAKATLA, AK | L.C.S.W. | Clinical Social Worker | 04/30/2021 |
| MCKELLER, DARNELL | MALONE, NY | - | Case Manager/Care Coordinator | 09/23/2026 |
| MCKENNA, CRISTEN | DANVILLE, VA | BSW, CSAC-SUPERVISEE | Addiction (Substance Use Disorder) Counselor | 08/09/2024 |
| MCKENZIE, ALYSSA | FLORAL PARK, NY | - | Case Manager/Care Coordinator | 09/22/2026 |
| MCKENZIE, TAMARA | JACKSONVILLE, FL | - | Mental Health Counselor | 01/12/2017 |
| MCKENZIE, VIVIENNE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| MCKERNAN, MAGGIE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MCKINNEY, ALYSSA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MCKINNEY, BRITTNEY | MAITLAND, FL | - | Mental Health Counselor | 11/16/2018 |
| MCKINNON, ABIGAIL | BATTLE CREEK, MI | - | Clinical Social Worker | 03/19/2024 |
| MCKIRRYHER, KYLE | RUTLAND, VT | - | Case Manager/Care Coordinator | 09/21/2026 |
| MCKNIGHT, ASHLEY | JACKSONVILLE, FL | BEHAVIOR TECHNICIAN | RBT | 09/23/2026 |
| MCLAUGHIN, ELLA | ST LOUIS PARK, MN | - | RBT | 09/22/2026 |
| MCLAUGHLIN, ALEC | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MCLAUGHLIN, CAROL | PAWNEE, OK | - | Case Manager/Care Coordinator | 09/24/2026 |
| MCLAUGHLIN, EMORY | KNOXVILLE, TN | - | RBT | 09/23/2026 |
| MCLEAN, KAYLA | HUNTINGTON, NY | LMHC | Mental Health Counselor | 04/17/2023 |
| MCLEAN, MATTHEW | EAST HAMPTON, NY | LMSW | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| MCLEOD, KELLI | LAWRENCEVILLE, GA | M.ED CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| MCMAHON, ANGELA | COON RAPIDS, MN | - | RBT | 09/23/2026 |
| MCMANUS, INGRID | MANCHESTER, CT | - | Counselor | 09/22/2026 |
| MCMANUS, JOHN | WOODBURY, MN | MA,CCC-SLP | Speech-Language Pathologist | 05/22/2007 |
| MCMULLAN, TESHA | NASHVILLE, AR | - | Case Manager/Care Coordinator | 09/25/2026 |
| MCMULLIN, MATTHEW | MCMINNVILLE, OR | - | Case Management Agency | 09/25/2026 |
| MCMURRAY, LATISHA | COMMERCE, TX | - | Counselor | 09/05/2008 |
| MCNAIRY, TEOLIN | SACRAMENTO, CA | - | RBT | 09/22/2026 |
| MCNALLY, ELLISE | BLOOMINGTON, IL | - | RBT | 09/24/2026 |
| MCNAMEE, BRENDAN | PORT WASHINGTON, NY | - | Clinical Social Worker | 09/24/2026 |
| MCNEILL, KAYDEN | SALISBURY, NC | - | RBT | 09/23/2026 |
| MCNELLY, AMBER | CHESAPEAKE, OH | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| MCQUADE, BRIAN | AUBURN, WA | LICSW/CDPT | Addiction (Substance Use Disorder) Counselor | 03/28/2018 |
| MCREYNOLDS, KADE | MAPLE VALLEY, WA | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| MCREYNOLDS, SHEENA | HYATTSVILLE, MD | - | Counselor | 09/25/2026 |
| MCSHANE, SHANTELL | LITTLETON, CO | NCACII, CAS | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MCSWAIN, SHARON | HICKORY, NC | - | RBT | 09/23/2026 |
| MCTHORN, CARLEY | MODESTO, CA | M.A., CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| MCVICKER, SEAN | COLUMBUS, OH | - | RBT | 09/21/2026 |
| MCWHORTER, CICELY | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| MCWILLIAMS, SHAUNA | HOPEWELL JCT., NY | - | Clinical Social Worker | 10/10/2014 |
| MDL LIFE TRANSFORMATION GROUP LLCORG | BROOKLYN, NY | - | Clinical Social Worker | 08/29/2026 |
| ME, MYSELF, AND FAMILY THERAPY LLCORG | CLIFTON, NJ | - | Community/Behavioral Health Agency | 09/23/2026 |
| MEACHEM COUNSELING LLCORG | CHILLICOTHE, OH | - | Counselor | 09/21/2026 |
| MEAGHER, BAILEY | AURORA, CO | - | Speech-Language Pathologist | 09/24/2026 |
| MEANS, LOGAN | AUSTIN, TX | - | Mental Health Counselor | 09/24/2026 |
| MEAS, MELANIE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MECHANIK, MEREDITH | TAMPA, FL | LCSW | Clinical Social Worker | 09/21/2026 |
| MECHLING, ALEXIA | COLUMBIA, MD | - | RBT | 07/14/2026 |
| MEDICAL AESTHETIC ARTSORG | RALEIGH, NC | - | Clinic/Center | 09/21/2026 |
| MEDICAL ARTS GROVES INCORG | RALEIGH, NC | - | Specialist | 09/21/2026 |
| MEDICAL PHARMA LIFE INCORG | LEBANON, TN | - | Case Management Agency | 09/21/2026 |
| MEDICAL SERVICES OF PENNSYLVANIA, PLLCORG | PHILADELPHIA, PA | - | Specialist | 03/27/2026 |
| MEDINA MARTINEZ, LUIS | REDWOOD CITY, CA | - | Professional Counselor | 05/23/2019 |
| MEDINA, ADAM | CLOVIS, CA | - | RBT | 09/23/2026 |
| MEDINA, ANISSA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MEDINA, ARIANA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MEDINA, EDGAR | SANTA ROSA, CA | - | RBT | 09/24/2026 |
| MEDINA, FRANCES | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MEDINA, JONATHAN | BROWNSVILLE, TX | LPCA | Professional Counselor | 09/26/2026 |
| MEDINA, MANUELA | INDIO, CA | - | Case Manager/Care Coordinator | 11/18/2021 |
| MEDINA, NICOLE | SOUTH PASADENA, CA | - | Clinical Social Worker | 09/23/2026 |
| MEDINA, XIMENA | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| MEDLIN, AMY | AURORA, IL | LCPC | Mental Health Counselor | 09/04/2014 |
| MEDLIN, TAE'LA | WINDSOR, CT | - | RBT | 09/21/2026 |
| MEDVORA BILLING LLCORG | SAN JOSE, CA | - | Clinic/Center | 09/22/2026 |
| MEEKER, AVA | GRAND RAPIDS, MI | - | RBT | 09/22/2026 |
| MEEKINS, JAMAL | WILLIAMSBURG, VA | - | RBT | 09/24/2026 |
| MEENGS, BRIANNA | GRAND RAPIDS, MI | - | Clinical Social Worker | 07/18/2024 |
| MEGAHAN, JAIANNA | GARLAND, TX | - | Mental Health Counselor | 09/21/2026 |
| MEGARGEL, CAROLINE | CHARLOTTESVILLE, VA | LCSW | Clinical Social Worker | 08/18/2016 |
| MEHER, SAHAR | BROOKLYN, NY | PSY.D. | Psychologist | 11/17/2016 |
| MEHRALIYEVA, KHADIJA | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 12/18/2023 |
| MEHTA, ESHA | GREENWOOD VILLAGE, CO | MSW, LCSW | Clinical Social Worker | 10/31/2022 |
| MEIER, ANIKA | REDMOND, WA | - | Counselor | 09/21/2026 |
| MEIJER, EMILIA | LAFAYETTE, LA | LPC | Mental Health Counselor | 09/22/2026 |
| MEISINGER, JESSICA | COMPTON, IL | - | Clinical Social Worker | 01/14/2021 |
| MEJIA-MILLER, VANESSA | LANSING, MI | - | RBT | 12/18/2018 |
| MEJIA, ADOLFO | PORTLAND, OR | - | BCBA | 01/09/2017 |
| MEJIA, FAITH | EL SEGUNDO, CA | - | RBT | 01/26/2026 |
| MEJIA, KIMBERLI | CONCORD, CA | - | RBT | 09/24/2026 |
| MEJIA, VANESSA | VISALIA, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| MEKIEGE NJAH, MERVEILLE | COVINA, CA | - | RBT | 09/24/2026 |
| MELA COUNSELING SERVICES CENTER, INC.ORG | MONTEBELLO, CA | - | Community/Behavioral Health Agency | 04/10/2008 |
| MELAKU, LUDE | PIKESVILLE, MD | - | RBT | 09/24/2026 |
| MELENDEZ, KARINA | EDINBURG, TX | - | Speech-Language Pathologist | 06/27/2019 |
| MELENDEZ, MARIEL ALEXANDRA | MAUNABO, PR | - | Speech-Language Pathologist | 09/22/2026 |
| MELGAR, MONICA | NORMAN, OK | - | RBT | 09/22/2026 |
| MELHEM, ALI | BELLAIRE, OH | M.D. | Specialist | 01/23/2007 |
| MELIN, LINDSEY | WHEATON, IL | MS CCC-SLP | Speech-Language Pathologist | 11/17/2014 |
| MELINDA COLE COUNSELING LLCORG | EXETER, NH | - | Community/Behavioral Health Agency | 09/04/2026 |
| MELISSA LOU KOERNER LCSW LLCORG | VENICE, FL | - | Clinical Social Worker | 08/26/2026 |
| MELKOTE NAGEGOWDA, DASHALAKSHMI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MELNICK, NOGA | CREVE COEUR, MO | MSW, LCSW | Clinical Social Worker | 09/21/2026 |
| MELO, CLAUDIA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MELTON, AUTUMN | LEXINGTON, SC | - | Mental Health Counselor | 09/18/2026 |
| MEME, DE ANGELE | QUINCY, MA | - | RBT | 09/23/2026 |
| MENCHEL, TALIA | NEW YORK, NY | - | Clinical Social Worker | 03/08/2022 |
| MENDEZ GARCIA, JENNIFER | FRESNO, CA | - | RBT | 09/23/2026 |
| MENDEZ, DEBORAH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MENDEZ, FRANCIS | EL SEGUNDO, CA | - | RBT | 04/16/2024 |
| MENDEZ, SIMON | LONG BEACH, CA | CADC II | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| MENDEZ, YESENIA | GILROY, CA | - | Professional Counselor | 05/19/2025 |
| MENDIETA-LILES, ARIELLE | DIXON, CA | - | Speech-Language Pathologist | 09/22/2026 |
| MENDIVIL, ALEXANDRA | GARDEN GROVE, CA | - | RBT | 09/24/2026 |
| MENDOZA GARCIA, ROSANGELINA | ORLANDO, FL | - | RBT | 09/25/2026 |
| MENDOZA, ANA | OTHELLO, WA | LMHC | Mental Health Counselor | 12/10/2019 |
| MENDOZA, CAMILLE | RIVERSIDE, CA | M.S.,CCC-SLP | Speech-Language Pathologist | 04/03/2019 |
| MENDOZA, DANIEL | OKLAHOMA CITY, OK | - | Mental Health Counselor | 04/22/2019 |
| MENDOZA, JAZMINE | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MENDOZA, MARY JO IZABEL | DALY CITY, CA | - | RBT | 09/25/2026 |
| MENDOZA, NICOLE | AURORA, IL | - | RBT | 09/24/2026 |
| MENDOZA, SAMANTHA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MENDOZA, SAMANTHA | MONROVIA, CA | - | RBT | 02/26/2024 |
| MENDZEF CLINICAL SERVICES PLLCORG | RALEIGH, NC | - | Clinical Social Worker | 09/24/2026 |
| MENENDEZ-PRICE, MARIA | BAKERSFIELD, CA | BCBA | BCBA | 11/23/2021 |
| MENGHEANG, MARISSA | SANTA CRUZ, CA | - | RBT | 09/24/2026 |
| MENJIVAR, MARIA | MODESTO, CA | - | RBT | 09/25/2026 |
| MENNA, AUBREY | CHICAGO, IL | - | Professional Counselor | 05/01/2023 |
| MENSAH, ELIZABETH | GLENN DALE, MD | - | Case Management Agency | 05/11/2026 |
| MENSAH, NICOLE | PIKESVILLE, MD | - | RBT | 09/25/2026 |
| MENTINK, ELIZABETH | KENOSHA, WI | LPC | Mental Health Counselor | 12/09/2024 |
| MENTISORG | NAPA, CA | - | Community/Behavioral Health Agency | 10/30/2007 |
| MERCADO, GABRIELA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MERCADO, GENNESYS | MONROVIA, CA | - | RBT | 09/24/2026 |
| MERCADO, JOSUE | ALHAMBRA, CA | - | RBT | 09/25/2026 |
| MERCADO, YANITA | CHARLOTTE, NC | - | Mental Health Counselor | 09/24/2026 |
| MERCHAN, JENNIFER | ALLENTOWN, PA | MS | RBT | 09/22/2026 |
| MERCHANT-TREJO, TZITLALI | THE DALLES, OR | - | Case Manager/Care Coordinator | 06/30/2025 |
| MERCHISON, TRACY | MIAMI GARDENS, FL | - | Clinical Social Worker | 09/26/2026 |
| MERCURY, RHETT | LEWISTON, ME | LMSW-CC | Clinical Social Worker | 09/22/2026 |
| MEREDITH, TED | MONROE, NC | - | RBT | 09/22/2026 |
| MERGENTHAL, ASHLEY | LINCOLN, NE | - | BCBA | 04/17/2023 |
| MERIDITH, DARCEY | RICHMOND, IN | - | Clinical Social Worker | 08/11/2006 |
| MERINO, OSCAR | CONCORD, CA | - | RBT | 07/31/2026 |
| MERINO, YVETTE | SARATOGA SPRINGS, UT | - | RBT | 09/21/2026 |
| MERLOS FLORES, JENNIFER | RENO, NV | - | Clinical Social Worker | 09/22/2026 |
| MERNAGH, RACHEL | NEW YORK, NY | - | Mental Health Counselor | 12/13/2025 |
| MERRIAM, PATRICIA | BATH, NY | - | Clinical Social Worker | 05/29/2014 |
| MERRIMENT ABA LLCORG | FISHERS, IN | - | BCBA | 11/30/2023 |
| MERRIN, JACOB | NEW YORK, NY | - | Psychologist | 10/15/2018 |
| MERRITT BATES, YMANI | IRWIN, PA | - | RBT | 09/22/2026 |
| MERRITT, CHYNNA | LOS ANGELES, CA | - | Clinical Social Worker | 02/04/2025 |
| MERSEGUEL, ISABELLE | ORLANDO, FL | - | RBT | 09/22/2026 |
| MERSINGER, KAIA | FOUNTAIN, CO | - | RBT | 09/21/2026 |
| MERSON, CASSIE | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MESA, ASHLIE | EMERYVILLE, CA | - | RBT | 09/24/2026 |
| MESA, LISBET | SAINT CLOUD, FL | - | BCBA | 10/23/2023 |
| MESERVE, ALICIA | SAN JOSE, CA | - | RBT | 09/21/2026 |
| MESERVE, KAYLA | NEWPORT, NH | - | RBT | 09/22/2026 |
| MESHAW, AMANDA | WAKE FOREST, NC | BCBA | BCBA | 02/14/2020 |
| MESSA, JENNIFER | BELLE CHASSE, LA | PLPC | Mental Health Counselor | 09/21/2026 |
| MESSERSMITH, JACOBY | MC COOK, NE | - | Day Training/Habilitation Specialist | 09/23/2026 |
| MESSICK, SKYLAR | NAPERVILLE, IL | - | RBT | 09/24/2026 |
| MESSIER, MARTHE | HOLYOKE, MA | - | Mental Health Counselor | 12/01/2022 |
| MESSNER, DAWN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MESY, JOAN | ALBANY, NY | - | Mental Health Counselor | 09/23/2026 |
| METAMORPHOSIS SERVICES, LLCORG | DOTHAN, AL | - | Clinical Social Worker | 09/21/2026 |
| METCALF, HUNTER | MURRAY, UT | - | Mental Health Counselor | 09/23/2026 |
| METHOD PEDIATRIC THERAPY AND WELLNESS, LLCORG | PRAIRIE VILLAGE, KS | - | Speech-Language Pathologist | 09/25/2026 |
| METRO TREATMENT OF NEW HAMPSHIRE, LPORG | MANCHESTER, NH | - | Community/Behavioral Health Agency | 05/15/2007 |
| METSCH, MADELYN | LAKEWOOD, CO | LCSW | Clinical Social Worker | 06/04/2024 |
| METTLE WORKS BEHAVIORAL SERVICES, LLCORG | KINGSTON, NY | - | Clinical Social Worker | 12/22/2020 |
| METU, LADON | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| METZGER, ERIN | AKRON, OH | - | Addiction (Substance Use Disorder) Counselor | 01/13/2021 |
| MEULENER, GIANNELLA | MIAMI, FL | - | RBT | 03/01/2022 |
| MEYER, CHARLOTTE | DULUTH, MN | LPCC | Professional Counselor | 12/12/2017 |
| MEYER, GREG | LITTLETON, CO | - | Mental Health Counselor | 09/22/2026 |
| MEYER, KRISTINA | AURORA, CO | LCSW | Clinical Social Worker | 04/05/2021 |
| MEYER, LINDA | HALF MOON BAY, CA | - | Clinical Social Worker | 02/10/2020 |
| MEYER, MYLA | OREM, UT | - | RBT | 09/21/2026 |
| MEYER, SAGE | RANCHO CUCAMONGA, CA | - | RBT | 07/02/2026 |
| MEYERING-ZERNS, NANCY | GRANT, MI | LMSW | Clinical Social Worker | 11/23/2020 |
| MEYERS, AMANDA | DEARBORN, MI | LPC | Professional Counselor | 09/29/2020 |
| MEYERS, RAPHAEL | TAMPA, FL | - | RBT | 08/02/2022 |
| MEZA RAMOS, ALFONSO | IRVINE, CA | - | RBT | 10/12/2023 |
| MFM INTERNAL MEDICINE LLCORG | ANASCO, PR | - | Clinic/Center | 04/03/2025 |
| MIATA, KAYLA | HICKSVILLE, NY | - | Clinical Social Worker | 10/15/2015 |
| MICELI-LAYTON, AMIE | JEROMESVILLE, OH | LPC | Professional Counselor | 11/14/2024 |
| MICELI, JONATHAN | CHICAGO, IL | - | BCBA | 12/21/2018 |
| MICHAEL RUSSELL LCSW, PLLCORG | WHITE PLAINS, NY | - | Clinical Social Worker | 03/28/2022 |
| MICHAELIS, MADISON | KANSAS CITY, MO | LMSW | Mental Health Counselor | 09/25/2026 |
| MICHAELS, EMILY | BETHESDA, MD | MS, MA, LPC | Community/Behavioral Health Agency | 01/26/2022 |
| MICHAELS, LAURA | FORT WASHINGTON, PA | LPC | Professional Counselor | 09/26/2007 |
| MICHALOWSKI, DAVID | NEW YORK, NY | LCPC | Mental Health Counselor | 02/17/2014 |
| MICHALSKI, JORDANNE | TRAVERSE CITY, MI | - | RBT | 09/24/2026 |
| MICHINOCK, STEPHANIA | UPPER ARLINGTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| MICKLE, ASHLEY | RICHMOND, VA | LCSW | Clinical Social Worker | 08/04/2022 |
| MICLAT, JOHANNA | OOLTEWAH, TN | - | Mental Health Counselor | 09/22/2026 |
| MIDDLEBY, NICOLAS | MENIFEE, CA | - | RBT | 09/21/2026 |
| MIDKIFF, BRIAN | COCONUT CREEK, FL | - | BCBA | 09/26/2026 |
| MIELE, MARIELLA | JERSEY CITY, NJ | - | Speech-Language Pathologist | 09/23/2026 |
| MIELKE, MEAGAN | VACAVILLE, CA | - | Mental Health Counselor | 12/21/2020 |
| MIGUEL RUIZ, KEILY | JEFFERSONVILLE, IN | - | RBT | 09/23/2026 |
| MIGUEL TORRES, LICENSED CLINICAL SOCIAL WORKER, APCORG | REDONDO BEACH, CA | - | Clinical Social Worker | 09/24/2026 |
| MIHAI, ANNASTASIA | BELLEVUE, WA | - | RBT | 09/23/2026 |
| MIHAILESCU, CORINA | THORNTON, CO | LPC,PSY.D | Mental Health Counselor | 01/11/2010 |
| MIJALLI, ABEER | DETROIT, MI | - | RBT | 09/21/2026 |
| MIKE CHOI DO PAORG | HIALEAH, FL | - | Specialist | 04/23/2007 |
| MILAM, MARGARET | AUSTIN, TX | LCSW | Mental Health Counselor | 12/31/2015 |
| MILAN FERRER, MELISSA | BOCA RATON, FL | - | RBT | 04/28/2021 |
| MILAN, TINA | SHASTA LAKE, CA | LCSW | Mental Health Counselor | 07/22/2013 |
| MILBAUER, LARA | CHICAGO, IL | LSW | Clinical Social Worker | 06/21/2022 |
| MILES, AMANDA | SAN ANTONIO, TX | LPC-S | Professional Counselor | 09/08/2017 |
| MILES, BRANDY | LATTA, SC | - | Clinical Social Worker | 09/21/2026 |
| MILES, REBECCA | OLATHE, KS | PH.D. | Psychologist | 06/14/2006 |
| MILLER MURPHY, REBECCA | LINWOOD, NJ | LCSW | Clinical Social Worker | 05/08/2008 |
| MILLER-FLEMING, KATHLEEN | FREMONT, NE | LIMHP | Mental Health Counselor | 02/12/2007 |
| MILLER-JOSSELYN, SUSAN | PORTLAND, OR | LCSW | Clinical Social Worker | 09/24/2026 |
| MILLER, ALICIA | DERWOOD, MD | - | BCBA | 02/08/2021 |
| MILLER, ARIANA | SPRING HILL, FL | RBT | RBT | 09/25/2026 |
| MILLER, AUDRA | SPRINGFIELD, MA | - | RBT | 09/23/2026 |
| MILLER, AUSTIN | SAVANNAH, GA | RBT | RBT | 11/03/2021 |
| MILLER, BRANDON | SUMTER, SC | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| MILLER, BRENDA | GRANTS PASS, OR | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| MILLER, BROOKLYNN | OREM, UT | - | RBT | 09/25/2026 |
| MILLER, CALLIE | BUTLER, PA | MS, NCC | Mental Health Counselor | 04/03/2025 |
| MILLER, DANIELLE | BALTIMORE, MD | LMSW | Clinical Social Worker | 11/05/2025 |
| MILLER, DERRICK | RAMONA, CA | - | Clinical Social Worker | 03/29/2017 |
| MILLER, DYLAN | KENT, WA | - | RBT | 09/11/2026 |
| MILLER, ELAINE | CEDAR PARK, TX | LPC | Professional Counselor | 06/26/2019 |
| MILLER, ELIZABETH | LONGMONT, CO | - | Mental Health Counselor | 09/21/2026 |
| MILLER, ETHAN | SPOKANE, WA | - | RBT | 09/25/2026 |
| MILLER, HEATHER | WARMINSTER, PA | L.C.S.W. | Clinical Social Worker | 06/16/2005 |
| MILLER, JASMIN | WASHINGTON, DC | LICSW | Clinical Social Worker | 09/30/2024 |
| MILLER, JASMINE | TIGARD, OR | - | Mental Health Counselor | 09/23/2026 |
| MILLER, JORDYN | KNOXVILLE, TN | - | RBT | 09/17/2026 |
| MILLER, JOSEPHINE | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| MILLER, KAITLYN | BETHLEHEM, PA | - | RBT | 09/24/2026 |
| MILLER, KAYLEY | GARDENA, CA | - | RBT | 09/24/2026 |
| MILLER, LEAH | SANTA MONICA, CA | MA, LPCC | Professional Counselor | 02/21/2020 |
| MILLER, MADISON | ANN ARBOR, MI | - | Clinical Social Worker | 09/21/2026 |
| MILLER, MADISYN | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| MILLER, MICHELLE | CARY, NC | - | Speech-Language Pathologist | 08/19/2026 |
| MILLER, ROXANNE | PRINCETON, NJ | LCSW | Clinical Social Worker | 09/01/2017 |
| MILLER, SAM | MIDDLEBURG HEIGHTS, OH | - | Clinical Social Worker | 08/30/2023 |
| MILLER, SUZANNE | CHICO, CA | PHD, CCC-A/SLP | Speech-Language Pathologist | 09/24/2026 |
| MILLER, TONI | IDAHO FALLS, ID | LPC, ACADC (ID), LAC | Addiction (Substance Use Disorder) Counselor | 03/26/2024 |
| MILLER, TYESHA | AUGUSTA, GA | - | RBT | 09/22/2026 |
| MILLETT, KINLEY | SALT LAKE CITY, UT | - | Clinical Social Worker | 07/23/2020 |
| MILLETTE, ALLISON | HOUSTON, TX | LCSW-S | Clinical Social Worker | 12/22/2021 |
| MILLNER, MICHELLE | JACKSON, MI | MS, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| MILLS, ANTONIO | SAN ANTONIO, TX | LCDC-I | Addiction (Substance Use Disorder) Counselor | 02/28/2025 |
| MILLS, PAULA | APEX, NC | - | Speech-Language Pathologist | 04/09/2026 |
| MILNE, SHELBY | CHESTER SPRINGS, PA | B.S., M.S., M.S., AT | Mental Health Counselor | 08/04/2022 |
| MILONE, MARISA | PORTSMOUTH, NH | - | RBT | 09/26/2026 |
| MILTON, ANNA | MINNEAPOLIS, MN | - | RBT | 02/02/2026 |
| MILTON, KHAB SEEB | PITTSBURGH, PA | - | RBT | 09/24/2026 |
| MILTON, TERRI | GRANITE CITY, IL | LPC | Counselor | 07/16/2024 |
| MILWAUKIE RESIDENTIAL CARE LLCORG | MILWAUKIE, OR | - | Mental Health Counselor | 09/22/2026 |
| MIMS, DEMI | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MIND BODY SPEECH WELLNESS P.C.ORG | MERRICK, NY | - | Speech-Language Pathologist | 08/28/2026 |
| MIND BODY WELLNESS GROUP LLCORG | ST PETERSBURG, FL | - | Mental Health Counselor | 08/24/2018 |
| MIND INSIGHT PSYCHOLOGYORG | MIAMI, FL | - | Psychologist | 09/23/2026 |
| MIND MAP LLCORG | WELDON SPRING, MO | - | Professional Counselor | 09/25/2026 |
| MIND SPRING PSCORG | GREENWOOD, IN | - | Mental Health Counselor | 02/10/2026 |
| MIND WORKS HOPE & HEALINGORG | COTTAGE GROVE, MN | - | Clinical Social Worker | 07/29/2026 |
| MINDFUL BLOSSOM COUNSELING LLCORG | BERKLEY, MI | - | Professional Counselor | 09/25/2026 |
| MINDFUL MOTION THERAPY COORG | NORTH LITTLE ROCK, AR | - | Case Management Agency | 09/22/2026 |
| MINDFUL SOLUTION SERVICES LLCORG | FARMINGTON, MN | - | Addiction (Substance Use Disorder) Counselor | 03/30/2026 |
| MINDFUL SOLUTION SERVICES LLCORG | FARMINGTON, MN | - | Addiction (Substance Use Disorder) Counselor | 03/30/2026 |
| MINDFULWAYZORG | SAN ANGELO, TX | - | Addiction (Substance Use Disorder) Counselor | 08/10/2026 |
| MINDWELL HEALTH & WELLNESS, LLCORG | HOMOSASSA SPRINGS, FL | - | Clinical Social Worker | 09/21/2026 |
| MINEAR, KACEE | LAKE MARY, FL | - | BCBA | 11/30/2020 |
| MINET, HANNAH | MINNETONKA, MN | CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| MINGO, LORETTA | PLYMOUTH, MI | - | RBT | 09/25/2026 |
| MINNIS, LAURA | OWOSSO, MI | LMSW | Clinical Social Worker | 05/23/2024 |
| MINOR, PHOEBE | LANCASTER, CA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| MINOR, TIA | NE, DC | - | Case Manager/Care Coordinator | 05/02/2012 |
| MINSHEW, AVA | CEDAR CITY, UT | - | RBT | 09/21/2026 |
| MINTA, KIRA | OAK HARBOR, WA | - | Speech-Language Pathologist | 09/08/2026 |
| MINTER, SARAH | DALTON, GA | - | RBT | 09/22/2026 |
| MINTON, DANIELLE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MINTZ, APRIL | JACKSON, MI | - | RBT | 12/02/2021 |
| MIR, AMRIT | BUFFALO, NY | DR | Specialist | 01/05/2024 |
| MIRAMONTES, CRISTINA | BONNEY LAKE, WA | - | Clinical Social Worker | 02/25/2021 |
| MIRAMONTES, MYRIAM | COLORADO SPRINGS, CO | - | RBT | 09/23/2026 |
| MIRANDA CORTES, ASTRID | ORLANDO, FL | - | RBT | 09/25/2026 |
| MIRANDA, ELIZABETH | CONCORD, NC | - | RBT | 09/25/2026 |
| MIRELES, JUAN | EL SEGUNDO, CA | - | RBT | 12/11/2024 |
| MIRONOVA, ALENA | STATEN ISLAND, NY | LMSW | Clinical Social Worker | 10/14/2022 |
| MIROSHNICHENKO, NIKOLAS | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MIRZA, ZOYA | LAKE FOREST, IL | LCPC, MDIV | Professional Counselor | 08/22/2022 |
| MISCIAGNA, ASHLEY | VICTOR, NY | - | Speech-Language Pathologist | 09/12/2023 |
| MISCO, ALEXIS | HUDSON, WI | LPC-IT | Professional Counselor | 10/07/2024 |
| MISTY HAVEN COUNSELING LLCORG | CHATTANOOGA, TN | - | Clinical Social Worker | 08/17/2026 |
| MITCHELL LPCC, JOHANNA | SANTA FE, NM | - | Professional Counselor | 06/07/2010 |
| MITCHELL, ALAYA | SPRINGFIELD, VA | - | RBT | 09/21/2026 |
| MITCHELL, BRIAN | SAGINAW, MI | - | Case Manager/Care Coordinator | 08/11/2025 |
| MITCHELL, BRIANNA | CHARLOTTESVILLE, VA | - | RBT | 09/22/2026 |
| MITCHELL, CHELSEA | COLUMBUS, OH | - | BCBA | 08/26/2020 |
| MITCHELL, CREELYN | CONCORD, CA | - | BCBA | 10/17/2023 |
| MITCHELL, DOROTHY | COLLINSVILLE, IL | - | Professional Counselor | 09/21/2026 |
| MITCHELL, HAYLEE | CLEVELAND, TN | BT | RBT | 09/22/2026 |
| MITCHELL, JENNICA | EAGLE, ID | LCSW | Clinical Social Worker | 07/23/2018 |
| MITCHELL, LETICIA | COVINA, CA | - | RBT | 09/23/2026 |
| MITCHELL, MICHAEL | SPRINGFIELD, MA | - | RBT | 09/24/2026 |
| MITCHELL, TAZHNEA | SOUTHFIELD, MI | - | RBT | 09/21/2026 |
| MITCHELL, TIFFANY | CEDAR HILL, TX | LCSW | Clinical Social Worker | 06/01/2022 |
| MITRA SHAHRYARY LCSW, INCORG | VIENNA, VA | - | Clinical Social Worker | 06/11/2025 |
| MITZE ALEXANDER LMSW PLLCORG | MUSKEGON HEIGHTS, MI | - | Clinical Social Worker | 09/22/2026 |
| MIZELL, PEYTON | AUSTIN, TX | - | Mental Health Counselor | 09/23/2026 |
| MIZYED, ISLAM | WORTH, IL | LPC | Professional Counselor | 09/22/2026 |
| MMT COUNSELING SERVICES LLCORG | LUBBOCK, TX | - | Professional Counselor | 05/08/2019 |
| MOBLEY, AMIRAH | NORTH CHESTERFIELD, VA | RESIDENT IN COUN | Mental Health Counselor | 09/22/2026 |
| MODLIN, DAVID | WINSTON SALEM, NC | MSW, LCSW | Clinical Social Worker | 10/11/2022 |
| MOECKLER, NEALY | CALABASAS, CA | MA, LMFT#164730 | Mental Health Counselor | 11/22/2010 |
| MOEDL, AUBREY | COTTONWOOD HEIGHTS, UT | - | RBT | 05/13/2020 |
| MOGES, BETHEL | DALLAS, TX | - | Addiction (Substance Use Disorder) Counselor | 04/18/2022 |
| MOHAMED, ASMO | ROSEVILLE, MN | - | RBT | 09/23/2026 |
| MOHAMMED, MUTAAS | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| MOHAMMED, NILOUFER | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MOHAMUD, SUCDI | SAINT PAUL, MN | - | RBT | 11/07/2024 |
| MOHAN, NANDITHA | ORLANDO, FL | - | RBT | 11/03/2025 |
| MOHTASHEMI, AVA | ANAHEIM, CA | - | Clinical Social Worker | 12/09/2022 |
| MOJEKWU, FRANKIE | MILWAUKEE, WI | - | Psychologist | 09/22/2022 |
| MOK, CAROLINE | BERKELEY, CA | - | Mental Health Counselor | 09/07/2010 |
| MOLAND, JANINA | ROSEVILLE, CA | - | BCBA | 09/24/2026 |
| MOLES, CHARITY | MAXWELTON, WV | - | Case Manager/Care Coordinator | 03/19/2020 |
| MOLEY, SHERRY | OVERLAND PARK, KS | RBT | RBT | 09/23/2026 |
| MOLINA, BRITTANY | JACKSONVILLE, FL | - | Specialist | 09/25/2026 |
| MOLINA, STEVEN | TORRANCE, CA | - | RBT | 09/21/2026 |
| MOLLY DURAN COUNSELING, PLLCORG | SAVOY, IL | - | Clinical Social Worker | 02/04/2026 |
| MOLLY FRECHETTE COUNSELINGORG | PORTLAND, OR | - | Mental Health Counselor | 09/21/2026 |
| MOLZON, RENEE | CHARDON, OH | MSSA, LISW | Clinical Social Worker | 05/10/2016 |
| MOMENTUM COUNSELING AND CONSULTING LLCORG | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| MONACELLI, NICOLE | HILLSBORO, OR | - | RBT | 09/10/2021 |
| MONAGHAN, ALIVIA | RIVERVIEW, FL | - | RBT | 09/21/2026 |
| MONCADA, AMARIEA | BROOKFIELD, WI | - | RBT | 09/25/2026 |
| MONDITHOKA, SHAMUEL | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MONGA, ANISHA | ARLINGTON HEIGHTS, IL | - | Professional Counselor | 10/30/2024 |
| MONGOVAN, KAIA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MONICO, STEPHANIE | BROOKLYN, NY | MED | Assistant Behavior Analyst | 09/23/2026 |
| MONIZ, FELIX | CONCORD, NH | - | Clinical Social Worker | 08/10/2026 |
| MONSALVE, NICOLL | ORLANDO, FL | - | RBT | 09/21/2026 |
| MONTANO GONZALEZ, JAHAIRA | SYLMAR, CA | - | RBT | 09/24/2026 |
| MONTANO, ANDREA | BRAWLEY, CA | - | Professional Counselor | 10/19/2012 |
| MONTANO, MARIA | IRVINE, CA | - | RBT | 09/21/2026 |
| MONTEIRO, DESTINY | NEW BEDFORD, MA | - | BCBA | 09/23/2026 |
| MONTEIRO, JOSHUA | SACRAMENTO, CA | - | RBT | 09/22/2026 |
| MONTERO, KENIA | MIAMI, FL | - | Mental Health Counselor | 11/20/2020 |
| MONTERO, NINETTE | LECANTO, FL | BA | Mental Health Counselor | 12/23/2015 |
| MONTES, ANNEL | LAS VEGAS, NV | CPC-I | Mental Health Counselor | 08/19/2017 |
| MONTES, VICTORIA | SEDRO WOOLLEY, WA | - | Counselor | 09/22/2026 |
| MONTESINO, PAOLA | FORT WAYNE, IN | LMHC | Mental Health Counselor | 10/04/2023 |
| MONTGOMERY RADIOLOGY ASSOCIATES, PAORG | MONTGOMERY, AL | - | Specialist | 06/30/2006 |
| MONTGOMERY, LATISHA | SAINT ALBANS, VT | - | Case Manager/Care Coordinator | 09/23/2026 |
| MONTGOMERY, MEGAN | BRIGHTON, MA | LCSW | Clinical Social Worker | 11/30/2022 |
| MONTGOMERY, QUANITA | SOUTHFIELD, MI | - | RBT | 09/25/2026 |
| MONTGOMERY, SARAH | STATESVILLE, NC | M.ED. | Speech-Language Pathologist | 05/25/2021 |
| MONTIEL, AMY | GLENDALE, AZ | - | RBT | 09/21/2026 |
| MONTIEL, DAMARIZ | MILWAUKIE, OR | - | Addiction (Substance Use Disorder) Counselor | 11/15/2017 |
| MONTILLIANO, MONTI | REDWOOD CITY, CA | - | Mental Health Counselor | 04/28/2020 |
| MONTOYA, JONAH | LITTLETON, CO | - | Case Manager/Care Coordinator | 09/25/2026 |
| MONTOYA, VICTORIA | HOUSTON, TX | LCSW | Clinical Social Worker | 09/25/2026 |
| MONTS, DEVONE | EAST HARTFORD, CT | - | Clinical Social Worker | 01/20/2018 |
| MONZELLE, LISA | SWANSEA, IL | - | Professional Counselor | 08/11/2018 |
| MOOBED, FARNOOSH | SAN JUAN CAPISTRANO, CA | - | Speech-Language Pathologist | 09/23/2026 |
| MOOCHOON, ANNA | ROCKVILLE, MD | MA | Professional Counselor | 02/23/2022 |
| MOODY, SABRINA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| MOONEY, FAITH | WEST FRANKFORT, IL | - | Clinical Social Worker | 09/24/2026 |
| MOONEY, MARISA | BINGHAMTON, NY | MS CCC-SLP | Speech-Language Pathologist | 07/02/2018 |
| MOONLIGHT MOUNTAIN RECOVERY, INCORG | POCATELLO, ID | - | Counselor | 05/18/2018 |
| MOORE, ALIVIA | NEWTOWN, PA | - | BCBA | 04/05/2022 |
| MOORE, ASHLEY | ALBANY, GA | - | Professional Counselor | 09/24/2026 |
| MOORE, CAROLYN | TAMPA, FL | MSW, LCSW | Clinical Social Worker | 01/27/2021 |
| MOORE, CARRIE | HEBER CITY, UT | LMHC | Mental Health Counselor | 11/01/2016 |
| MOORE, CONNIE | GUTHRIE, OK | PHD, LPC | Professional Counselor | 06/16/2006 |
| MOORE, DIAMOND | HUNTSVILLE, AL | - | RBT | 09/25/2026 |
| MOORE, DIANNA | CHARLESTON, SC | BCBA | RBT | 09/19/2019 |
| MOORE, DORIS | MARTINEZ, CA | PHD, MSW, RAS | Clinical Social Worker | 02/01/2007 |
| MOORE, EMILY | CHICAGO, IL | CT | Mental Health Counselor | 06/14/2021 |
| MOORE, GREGORY | PARKERSBURG, WV | P.R.S.S | Case Manager/Care Coordinator | 07/28/2022 |
| MOORE, JORDAN | SAN DIEGO, CA | - | Mental Health Counselor | 06/24/2025 |
| MOORE, JOSHUA | JACKSONVILLE, FL | - | RBT | 09/24/2026 |
| MOORE, KATHERINE | MALDEN, MA | - | Counselor | 09/23/2026 |
| MOORE, KELSEY | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| MOORE, LAWANDA | WARSAW, NC | - | Addiction (Substance Use Disorder) Counselor | 07/17/2024 |
| MOORE, MALIYAH | BAY CITY, MI | - | RBT | 09/24/2026 |
| MOORE, MARY | STERLING, VA | MSW, LCSW | Clinical Social Worker | 09/23/2026 |
| MOORE, MATTHEW | ROSEMOUNT, MN | - | Speech-Language Pathologist | 07/25/2007 |
| MOORE, NAHEMA | CHERRY HILL, NJ | - | Clinical Social Worker | 04/12/2024 |
| MOORE, RACHEL | MAUMEE, OH | - | Professional Counselor | 08/26/2025 |
| MOORE, ROBERT | COLORADO SPRINGS, CO | - | Professional Counselor | 08/29/2024 |
| MOORE, ROBERT | ROCHESTER HILLS, MI | M.S | RBT | 06/13/2017 |
| MOORE, SARAH | LANCASTER, CA | - | RBT | 09/24/2026 |
| MOORE, TATUM | AURORA, CO | LCSW | Clinical Social Worker | 09/24/2026 |
| MOORE, TRINITY | BARTLESVILLE, OK | - | Case Manager/Care Coordinator | 09/22/2026 |
| MOORE, YANAIZA | FALL RIVER, MA | - | RBT | 09/23/2026 |
| MORA BASART, EDUARDO | CORAL GABLES, FL | - | BCBA | 04/21/2022 |
| MORA PEREZ, JOHNNY | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MORA, CINDY | FARMERS BRANCH, TX | - | RBT | 09/22/2026 |
| MORA, LYLAH | NEWPORT BEACH, CA | - | RBT | 09/22/2026 |
| MORALES DAVILA, ELIZABETH | THE DALLES, OR | - | RBT | 04/27/2026 |
| MORALES FLEITES, JOSE | TAMPA, FL | - | RBT | 09/26/2026 |
| MORALES, JAEDON | RICHMOND HILL, GA | - | RBT | 09/22/2026 |
| MORALES, JAZMINE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MORALES, JENNIFER | EUGENE, OR | M.A., LMHC | Mental Health Counselor | 01/13/2011 |
| MORALES, LINDSAY | GREER, SC | - | RBT | 09/25/2026 |
| MORALES, SHARON | PASADENA, CA | - | RBT | 03/11/2025 |
| MORAN ALFARO, MAYRA | ROCKVILLE, MD | - | RBT | 09/21/2026 |
| MORAN, AMANDA | CRANSTON, RI | LICSW | Clinical Social Worker | 08/23/2023 |
| MORAN, SARAH | CONCORD, NC | - | RBT | 09/24/2026 |
| MORBLEY, KAYLIN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| MORE THAN WORDS PLLCORG | FORT WORTH, TX | - | Speech-Language Pathologist | 09/24/2026 |
| MOREAU, NATASIA | PARSIPPANY, NJ | - | RBT | 09/18/2026 |
| MORELAND, AUTUMN | FEDERAL WAY, WA | - | RBT | 09/24/2026 |
| MORELAND, MEGAN | ALEXANDRIA, VA | MED, NCC | Mental Health Counselor | 08/21/2025 |
| MORELAND, MICAH | BATON ROUGE, LA | - | RBT | 09/23/2026 |
| MORENO PORTONI, PALOMA | QUINCY, MA | - | Mental Health Counselor | 09/22/2026 |
| MORENO RODRIGUEZ, JOANNA | MURRIETA, CA | - | RBT | 05/19/2026 |
| MORENO, ADELA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MORENO, ANTHONY | LOWELL, IN | - | Mental Health Counselor | 09/22/2026 |
| MORENO, CHARLI | ANAHEIM, CA | - | RBT | 09/24/2026 |
| MORENO, DANIELA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| MORENO, KAYLA | COVINA, CA | - | RBT | 09/22/2026 |
| MORENO, MARCO | CHULA VISTA, CA | - | RBT | 09/22/2026 |
| MORENO, MERCEYDES | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| MORENO, STEVEN | PORTLAND, OR | - | Clinical Social Worker | 04/22/2025 |
| MORENO, THEDA | EL RENO, OK | - | Case Manager/Care Coordinator | 03/12/2025 |
| MOREY, CRYSTAL | HURRICANE, UT | ACMHC | Mental Health Counselor | 09/21/2026 |
| MORGAN NICHELSON THERAPYORG | LINCOLN, NE | - | Clinical Social Worker | 06/03/2026 |
| MORGAN, ALLISON | MONTEREY, CA | - | Speech-Language Pathologist | 09/21/2026 |
| MORGAN, ARTHUR | WASHINGTON, DC | - | Addiction (Substance Use Disorder) Counselor | 11/18/2025 |
| MORGAN, DEIRDRE | KENNESAW, GA | - | Psychologist | 09/24/2026 |
| MORGAN, ERIN | GREENACRES, FL | LMHC | Mental Health Counselor | 08/29/2022 |
| MORGAN, GRACE | WESTFORD, MA | BCBA | BCBA | 04/18/2023 |
| MORGAN, GRANT | PEORIA, AZ | - | RBT | 08/14/2023 |
| MORGAN, JESSICA | MODESTO, CA | - | Addiction (Substance Use Disorder) Counselor | 09/12/2026 |
| MORGAN, KEEVA | PIKESVILLE, MD | - | RBT | 09/25/2026 |
| MORGAN, LAURA | COLORADO SPRINGS, CO | LCSW | Clinical Social Worker | 06/25/2021 |
| MORGAN, RAASHEEMA | SAVANNAH, GA | - | RBT | 09/24/2026 |
| MORGAN, SHAKIRAH | HISTORIC NEW CASTLE, DE | - | Clinical Social Worker | 04/24/2019 |
| MORGAN, SHARDE | EUCLID, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| MORI, JORDAN | SAN DIEGO, CA | - | Speech-Language Pathologist | 09/22/2026 |
| MORICE, AMANDA | CONCORD, CA | - | BCBA | 01/28/2022 |
| MORIN, REBECCA | SACO, ME | LMSW-CC | Clinical Social Worker | 09/25/2026 |
| MORING, JASON | MAUMEE, OH | MSW, LSW, LICDC | Addiction (Substance Use Disorder) Counselor | 05/25/2015 |
| MORLEY, JENNIFER | BURLINGTON, NC | BCBA | BCBA | 04/04/2012 |
| MORMANDO, ALYSSA | HONOLULU, HI | - | Mental Health Counselor | 09/25/2026 |
| MORNING LIGHT COUNSELING, PLLCORG | EAST FALMOUTH, MA | - | Mental Health Counselor | 09/21/2026 |
| MOROLES, OVIDIO | WESLACO, TX | LCSW | Clinical Social Worker | 08/10/2024 |
| MORPHO BEHAVIORAL SERVICESORG | ONTARIO, CA | - | BCBA | 04/23/2021 |
| MORRIS, ALEXIS | SUN CITY, AZ | - | RBT | 09/24/2026 |
| MORRIS, ANNA | LOS ANGELES, CA | - | RBT | 09/22/2026 |
| MORRIS, AUBREY | BRYANT, AR | - | RBT | 09/23/2026 |
| MORRIS, BRITTNEY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MORRIS, DANIELLE | CLARKSVILLE, TN | RBT | RBT | 06/17/2019 |
| MORRIS, DAWN | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| MORRIS, GABRIEL | WALNUT CREEK, CA | - | RBT | 09/23/2026 |
| MORRIS, HARRISON | LAWRENCEVILLE, GA | BCBA | BCBA | 09/21/2026 |
| MORRIS, KENNEDI | HUNTSVILLE, AL | - | Mental Health Counselor | 09/21/2026 |
| MORRIS, KYA | SPOKANE, WA | - | RBT | 09/21/2026 |
| MORRIS, MYA | CONWAY, AR | - | RBT | 09/24/2026 |
| MORRIS, SAVANNA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| MORRISON CENTERORG | SCARBOROUGH, ME | - | Speech-Language Pathologist | 10/08/2009 |
| MORRISON, LACALA | GREENSBORO, NC | - | RBT | 09/25/2026 |
| MORRONE, TIFFANY | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MORROW, JOSEPH | GRAND ISLAND, NE | LIMHP | Mental Health Counselor | 09/02/2021 |
| MORROW, OLIVIA | WEST DES MOINES, IA | - | RBT | 09/22/2026 |
| MORTON, AMBER | COLUMBIA, MD | - | RBT | 05/08/2026 |
| MORTON, CHARITY | MONKTON, MD | - | Mental Health Counselor | 09/24/2026 |
| MORVAY, JULIANA | FORT WAYNE, IN | - | RBT | 09/22/2026 |
| MOSCATO, CHRISTINA | RIVERBANK, CA | BCBA | BCBA | 10/16/2018 |
| MOSES-BOWMAN, NAJAI | TOBYHANNA, PA | - | RBT | 09/26/2026 |
| MOSHER, HANNAH | MENIFEE, CA | - | Clinical Social Worker | 09/21/2026 |
| MOSHOOD, ADEOLA | WOOSTER, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| MOSKAL, ANDREA | VIRGINIA BEACH, VA | - | Professional Counselor | 04/08/2024 |
| MOSKOWITZ, MARIANNE | ARLINGTON, MA | LMHC | Mental Health Counselor | 01/06/2012 |
| MOSKVINA, EKATERINA | HOLLYWOOD, FL | - | RBT | 03/10/2025 |
| MOSQUEDA, DENA | MORENO VALLEY, CA | RADT1 | Addiction (Substance Use Disorder) Counselor | 08/21/2023 |
| MOSS, DAVIDA | ELMIRA, NY | - | Case Manager/Care Coordinator | 05/29/2019 |
| MOSS, MADISON | NORCROSS, GA | - | RBT | 09/25/2026 |
| MOSSING, KANDACE | BOSTON, MA | - | Psychologist | 04/08/2024 |
| MOSTELLER, KRISTEN | DUBLIN, OH | - | Case Manager/Care Coordinator | 06/02/2025 |
| MOTE, MORGAN | COLORADO SPRINGS, CO | MSW, LSW | Clinical Social Worker | 09/22/2026 |
| MOTEN, HIBA | PLANO, TX | LPC | Professional Counselor | 08/28/2023 |
| MOTEN, LATRAVEN | HOUSTON, TX | - | RBT | 09/23/2026 |
| MOTION ENTERPRISE LLCORG | GREENSBORO, NC | - | Community/Behavioral Health Agency | 12/29/2023 |
| MOTONI, OLUWAFERANMI | DALLAS, TX | MPH, RBT | RBT | 09/25/2026 |
| MOULTON, ETHAN | CEDAR CITY, UT | - | RBT | 09/22/2026 |
| MOULTON, MARY | TULSA, OK | M.S. | Counselor | 06/03/2008 |
| MOUNDAY, JAIDEN | TACOMA, WA | - | Clinical Social Worker | 09/23/2026 |
| MOUNNI, ASMAA | VIRGINIA BEACH, VA | - | RBT | 09/22/2026 |
| MOUNTAIN HEALING COUNSELING LLCORG | POCATELLO, ID | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| MOUNTAIN HEALTH AND WELLNESSORG | REXBURG, ID | - | Professional Counselor | 06/07/2021 |
| MOUNTAIN LAND REHABILITATION LLCORG | SALT LAKE CITY, UT | - | Speech-Language Pathologist | 08/24/2006 |
| MOUSAVI, SARAH | BELLEVUE, WA | - | Counselor | 09/22/2023 |
| MOUSSEAU, MADELYN | SAINT CLAIR SHORES, MI | - | RBT | 09/22/2026 |
| MOWERY, ALLISON | IRONTON, OH | LICDC/LSW | Addiction (Substance Use Disorder) Counselor | 02/19/2018 |
| MOY, ERIN | SANTA BARBARA, CA | - | Clinical Social Worker | 09/25/2026 |
| MOYANO, ALEJANDRA | MURRIETA, CA | - | Clinical Social Worker | 08/26/2021 |
| MOYAO, EVELYN | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 03/04/2025 |
| MOYER, MOLLY | MERIDIAN, ID | LPC | Counselor | 07/05/2022 |
| MRH COUNSELING, DBAORG | SOUTH SETAUKET, NY | - | Mental Health Counselor | 09/23/2026 |
| MSH ORGANIZATIONORG | CALABASAS, CA | - | Case Management Agency | 09/21/2026 |
| MT. MEDICAL CENTER AND REHABORG | ALBUQUERQUE, NM | - | Case Management Agency | 09/21/2026 |
| MUCK, MARY | LITTLE RIVER, SC | L.P.C. | Mental Health Counselor | 07/22/2008 |
| MUHAMMAD, AQSA | FOREST HILLS, NY | - | BCBA | 09/21/2026 |
| MUHAMMAD, WALIYAH | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| MUHAMMADI, RAZIA | BRIGHTON, MI | LMSW | Clinical Social Worker | 01/26/2022 |
| MUHSIN, NAIMA | SAINT CLOUD, MN | - | RBT | 09/23/2024 |
| MUJAWAYEZU, JUDITHE | AURORA, CO | RBT | RBT | 09/24/2026 |
| MUKHTAR, ABDIRAHMAN | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| MULINA, JESSICA | BOGALUSA, LA | LCSW | Clinical Social Worker | 09/22/2026 |
| MULIOLIS, ANIKA | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| MULLEN, JACKSON | ARLINGTON HEIGHTS, IL | - | Mental Health Counselor | 09/21/2026 |
| MULLEN, MELAINA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| MULLIN, AMANDA | OLATHE, KS | LPC | Counselor | 10/13/2020 |
| MULLON, DANIELLE | DURHAM, NC | LCSW | Clinical Social Worker | 08/31/2012 |
| MULNICK, RYAN | TAOS, NM | - | Professional Counselor | 08/28/2024 |
| MUMGAARD, LAYLA | GARDEN CITY, KS | LSCSW | Clinical Social Worker | 06/12/2012 |
| MUNDER, AURORA | SPRINGFIELD, MO | MSW, LCSW | Clinical Social Worker | 09/18/2024 |
| MUNGUIA, LORENA | LEHIGH ACRES, FL | - | RBT | 09/21/2026 |
| MUNN, ANDRE | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| MUNOZ SOTO, GIANINNA | WINTER PARK, FL | - | Clinical Social Worker | 09/23/2026 |
| MUNOZ, DAVE | CUTLER BAY, FL | - | RBT | 09/23/2026 |
| MUNOZ, GENESIS | FLOWER MOUND, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/22/2026 |
| MUNRO, STEPHANIE | CORAL GABLES, FL | MSW, LCSW | Clinical Social Worker | 12/29/2022 |
| MUNRO, THOMAS | KENAI, AK | - | Mental Health Counselor | 06/03/2026 |
| MUNSCHE, HEATHER | CLINTON TWP, MI | LLP | Psychologist | 06/27/2014 |
| MUNSON, KAYLA | YOUNGSTOWN, OH | - | RBT | 09/23/2026 |
| MUNUNULE, HADASSAH | ARDEN HILLS, MN | - | RBT | 09/21/2026 |
| MURATALLA, JAZMIN | TORRANCE, CA | - | RBT | 09/22/2026 |
| MURGA, TANIA | BUFORD, GA | MS, APC | Professional Counselor | 02/26/2026 |
| MURILLO, ERIKA | TEMECULA, CA | - | RBT | 09/18/2026 |
| MURILLO, FRANCIS | JOHNSON CITY, TN | - | Professional Counselor | 05/04/2026 |
| MURO, KARINA | WINDSOR, CO | - | Clinical Social Worker | 08/15/2022 |
| MURPHREY, JESSICA | APEX, NC | - | Counselor | 09/22/2026 |
| MURPHY, ASHLEY | RALEIGH, NC | - | RBT | 09/24/2026 |
| MURPHY, CAITLIN | SAN CLEMENTE, CA | SLP | Speech-Language Pathologist | 09/23/2026 |
| MURPHY, CHELSEA | PHILADELPHIA, PA | LSW | Clinical Social Worker | 04/02/2024 |
| MURPHY, CLIFF | PITTSBURGH, PA | LSW | Clinical Social Worker | 09/21/2026 |
| MURPHY, EMERSON | JEMEZ SPRINGS, NM | - | RBT | 09/23/2026 |
| MURPHY, KIARA | NORFOLK, VA | - | RBT | 08/09/2023 |
| MURPHY, MADELYNN | CHICAGO, IL | LCSW | Clinical Social Worker | 11/17/2021 |
| MURPHY, ROBERT | EDINA, MN | LADC, LPCC | Addiction (Substance Use Disorder) Counselor | 11/30/2021 |
| MURPHY, SHAWNTAVIOUS | GAINESVILLE, FL | - | Addiction (Substance Use Disorder) Counselor | 07/05/2016 |
| MURPHY, TESSA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| MURR, JESSICA | KNOXVILLE, TN | LCSW | Clinical Social Worker | 02/15/2017 |
| MURRAY, AALIYAH | HINESVILLE, GA | - | RBT | 09/26/2026 |
| MURRAY, AMANDA | KLAMATH FALLS, OR | MS, QMHP, CADC-II | Mental Health Counselor | 08/31/2023 |
| MURRAY, BONNIE | BROOKLYN, NY | - | Speech-Language Pathologist | 08/24/2015 |
| MURRAY, JOHN | CLINTON, MD | - | Professional Counselor | 09/25/2026 |
| MURRAY, KELLY | BRANDON, FL | - | Speech-Language Pathologist | 09/22/2026 |
| MURRAY, KRISTEN | YOUNGSTOWN, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| MURRELD, SHAQUEENA | BROOKLYN, NY | - | Speech-Language Pathologist | 04/12/2018 |
| MURRIETA, DESTINEE | RIVERBANK, CA | - | RBT | 09/21/2026 |
| MURTAGH, ASHLEY | PORTLAND, OR | MA | Professional Counselor | 12/03/2017 |
| MUSCADIN, CATRIUCHA | PHILLIPSBURG, NJ | LAC | Mental Health Counselor | 09/25/2026 |
| MUSE, JENISE | METAIRIE, LA | - | BCBA | 09/25/2026 |
| MUSEGUEZ-TORRES, ADAMARIS | CUTLER BAY, FL | - | RBT | 01/12/2026 |
| MUSHFIQUE, ALVINA | GARDEN GROVE, CA | - | RBT | 01/21/2026 |
| MUSKWE, DEBBIE | TAMPA, FL | LCSW | Clinical Social Worker | 02/21/2013 |
| MUTURI, SAMUEL | JAMAICA PLAIN, MA | MS, CF-SLP | Speech-Language Pathologist | 09/21/2026 |
| MY FAVORITE THERAPISTS, LLCORG | DEERFIELD BEACH, FL | - | BCBA | 05/26/2016 |
| MY JOURNEY PLLCORG | AUSTIN, TX | - | Mental Health Counselor | 05/06/2024 |
| MY LIFE COUNSELING LLCORG | MOUNT CLEMENS, MI | - | Community/Behavioral Health Agency | 04/14/2017 |
| MY MINDFUL COUNSELORORG | PORT SAINT LUCIE, FL | - | Clinical Social Worker | 09/24/2026 |
| MY THERAPY NYC LCSW PCORG | NEW YORK, NY | - | Mental Health Counselor | 12/30/2013 |
| MYERS-GORDON, JAMEIA | ALPHARETTA, GA | - | RBT | 09/22/2026 |
| MYERS, DEJAH | NEW YORK, NY | LMSW | Clinical Social Worker | 07/06/2022 |
| MYERS, GRACE | GREENWOOD VILLAGE, CO | LPCC | Mental Health Counselor | 06/30/2025 |
| MYERS, PAMELA | BANNOCKBURN, IL | M.S. | Mental Health Counselor | 01/23/2015 |
| MYERS, TAMMY | MALTA, NY | LMHC, CASAC | Addiction (Substance Use Disorder) Counselor | 05/07/2013 |
| MYRIAD HOUSE PLLCORG | SOUTH SALT LAKE, UT | - | Clinical Social Worker | 09/25/2026 |
| MYRICK, TRINITY | BALTIMORE, MD | - | RBT | 09/24/2026 |
| N. MACIAS LICENSED CLINICAL SOCIAL WORKER, A PROFESSIONAL CORPORATIONORG | RANCHO CUCAMONGA, CA | - | Clinical Social Worker | 09/25/2026 |
| N'DA, NEBTOM | NORMAN, OK | - | RBT | 09/21/2026 |
| N'DOUR, SOKHNA | LEXINGTON, KY | - | RBT | 09/24/2026 |
| NACHTIGALL, AUSTIN | SIOUX FALLS, SD | - | Professional Counselor | 07/11/2024 |
| NADAL, KATHERINE | GREENWOOD VILLAGE, CO | M.S. CCC-SLP | Speech-Language Pathologist | 06/20/2017 |
| NADOLNY, WENDY | CRAIG, CO | L.C.S.W. | Clinical Social Worker | 03/21/2006 |
| NADON, KARL | WASILLA, AK | LCSW | Clinical Social Worker | 07/25/2019 |
| NADRASIK, RACHEAL | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| NAGARAJU, HARI PRIYA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| NAGLE, NICOLINA | WASHINGTON, MI | - | BCBA | 12/04/2018 |
| NAHIYAN, SANJIDA | RALEIGH, NC | - | BCBA | 09/06/2019 |
| NAHMIAS, NAOMI | BELLINGHAM, WA | - | Mental Health Counselor | 09/21/2026 |
| NAHUELPAN PEREZ, CONSTANZA | MODESTO, CA | SLP | Speech-Language Pathologist | 09/22/2026 |
| NAHYAMA, GAFOBEA | HYATTSVILLE, MD | - | Case Manager/Care Coordinator | 01/10/2026 |
| NAILS, DAMON | CASTRO VALLEY, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| NAJAR, BLANCA | POMONA, CA | - | RBT | 09/22/2026 |
| NAJERA-KELLY, FLORA | CHULA VISTA, CA | MA, LPCC | Mental Health Counselor | 10/26/2015 |
| NAJERA, NANCY | ONTARIO, CA | - | RBT | 09/22/2026 |
| NAKISHER, STEVEN | HUNTINGTON WOODS, MI | PSYD | Psychologist | 06/08/2006 |
| NALE, REBECCA | COLUMBUS, IN | BS | Case Manager/Care Coordinator | 09/23/2026 |
| NAMUGABO, SUZAN | CORONA, CA | - | RBT | 09/23/2026 |
| NANA, CONCILIA | WASHINGTON, DC | - | Case Manager/Care Coordinator | 03/18/2020 |
| NANCY ANDERSON INCORG | MONUMENT, CO | - | Mental Health Counselor | 11/08/2011 |
| NANDISH, SHAILESH | CHICO, CA | M.D. | Specialist | 12/13/2005 |
| NAPLES, MATTHEW | BOISE, ID | LCSW | Clinical Social Worker | 05/20/2022 |
| NARANJO ALVAREZ, DAILIS | KISSIMMEE, FL | - | RBT | 09/24/2026 |
| NARDELLA, AUDREY | SCHAUMBURG, IL | - | RBT | 09/21/2026 |
| NARVAEZ, TALINA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| NASH, TYLER | VENTURA, CA | - | Addiction (Substance Use Disorder) Counselor | 08/03/2017 |
| NATIONAL MENTOR HEALTHCARE, LLCORG | OPELIKA, AL | - | Community/Behavioral Health Agency | 01/02/2023 |
| NATIONAL MENTOR HEALTHCARE, LLCORG | OPELIKA, AL | - | BCBA | 01/02/2023 |
| NATURAL SPRINGS COUNSELING, PLLCORG | DENVER, CO | - | Mental Health Counselor | 09/28/2022 |
| NAULT, KATHRYN | FORT WORTH, TX | MS, LPC-ASSOCIATE | Professional Counselor | 02/08/2023 |
| NAVA MOJICA, ANGEL | CENTRALIA, WA | BAS, R-AAC | Counselor | 09/21/2026 |
| NAVA, AURORA | CASTRO VALLEY, CA | - | Mental Health Counselor | 09/14/2026 |
| NAVARRE, NICOLE | TOLEDO, OH | CCC-SLP | Speech-Language Pathologist | 06/27/2022 |
| NAVARRETE, CASSANNDRA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| NAVARRETE, JASMIN | LOS ANGELES, CA | - | RBT | 09/21/2026 |
| NAVARRETE, ROSARIO | LONG BEACH, CA | LCSW | Clinical Social Worker | 06/29/2011 |
| NAVARRO GONZALEZ, RAQUEL | HAYWARD, CA | - | Psychologist | 05/09/2023 |
| NAVARRO KING, ARIANA | FARMINGTON HILLS, MI | - | RBT | 11/04/2024 |
| NAVARRO, ALMA | CHICAGO, IL | LPC | Professional Counselor | 07/15/2025 |
| NAVARRO, ANDREA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| NAVARRO, BRIZA | BELEN, NM | - | RBT | 09/24/2026 |
| NAVARRO, DANIEL | LINCOLN, CA | LCSW | Clinical Social Worker | 05/14/2021 |
| NAVARRO, EMANUEL | RICHMOND, CA | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| NAVARRO, FATIMA | KISSIMMEE, FL | RBT | RBT | 09/22/2026 |
| NAVOR, VANESSA | SAN GABRIEL, CA | - | RBT | 09/22/2026 |
| NAYLOR, ADAM | MEMPHIS, TN | LPC-MHSP, NCC | Professional Counselor | 03/29/2018 |
| NAZCARE - SERENITY CIRCLE WELLNESS CENTERORG | COTTONWOOD, AZ | - | Mental Health Counselor | 06/30/2021 |
| NAZCARE - SERENITY CIRCLE WELLNESS CENTERORG | COTTONWOOD, AZ | - | Mental Health Counselor | 04/22/2008 |
| NAZCARE, INCORG | PRESCOTT VALLEY, AZ | - | Mental Health Counselor | 12/13/2012 |
| NAZCARE, INCORG | CASA GRANDE, AZ | - | Mental Health Counselor | 10/10/2023 |
| NAZCARE, INCORG | KINGMAN, AZ | - | Mental Health Counselor | 04/22/2008 |
| NAZCARE, INC. - CASA GRANDE WELLNESS CENTERORG | CASA GRANDE, AZ | - | Mental Health Counselor | 06/26/2013 |
| NAZCARE, INC. - EATON CENTER FOR JOYFUL HEALTHORG | PRESCOTT VALLEY, AZ | - | Mental Health Counselor | 05/18/2016 |
| NAZCARE, INC. - RISING STAR WELLNESS CENTERORG | APACHE JUNCTION, AZ | - | Mental Health Counselor | 06/26/2013 |
| NAZCO, EMILY | MIAMI LAKES, FL | - | RBT | 09/23/2026 |
| NAZERI, FARIMAH | ELK GROVE, CA | - | RBT | 09/24/2026 |
| NDISANZE, BEN | BOISE, ID | - | Case Manager/Care Coordinator | 12/11/2025 |
| NDOBEGANG, SUSAN | BOWIE, MD | - | Case Manager/Care Coordinator | 10/17/2019 |
| NEACSU, DANA | EDMOND, OK | - | RBT | 09/23/2026 |
| NEAL, FRANCES | BATON ROUGE, LA | - | Mental Health Counselor | 05/23/2018 |
| NEAL, LILLIAN | KNOXVILLE, TN | - | Speech-Language Pathologist | 09/21/2026 |
| NEASON, ALIYAH | AUSTIN, TX | - | RBT | 09/22/2026 |
| NEELLEY, REIA | CALHOUN, GA | LPC | Mental Health Counselor | 09/24/2026 |
| NEESE, KIM | LAGRANGE, GA | LPC, BCCC, CADC II, | Addiction (Substance Use Disorder) Counselor | 10/29/2014 |
| NEGRIN GARCIA, GISELA | SAN JUAN, PR | MD | Specialist | 09/13/2005 |
| NEGRON, WILLIAM | NEW YORK, NY | - | Mental Health Counselor | 09/23/2026 |
| NEH, VANNESSA | CHEVERLY, MD | - | Case Manager/Care Coordinator | 09/24/2026 |
| NEHEMIAH COMMUNITY SERVICESORG | HAMPTON, VA | - | Case Management Agency | 09/26/2026 |
| NEIGHBORHOOD NETWORK ABA, LLCORG | OWINGS MILLS, MD | - | Community/Behavioral Health Agency | 03/21/2026 |
| NEIMAN, TINA | SPEARFISH, SD | - | Mental Health Counselor | 09/22/2026 |
| NEITZERT, ALIXANDRA | QUINCY, MI | M.A. | Speech-Language Pathologist | 09/22/2026 |
| NEITZEY, HANNAH | MARION, NC | LCSW-A, LCAS-A | Clinical Social Worker | 06/14/2023 |
| NELKIE, CHRISTINE | OSCODA, MI | - | RBT | 09/25/2026 |
| NELMS, KAYLEA | HOXIE, AR | - | RBT | 09/21/2026 |
| NELSON, ALEXIS | CLINTON, MO | PBA | BCBA | 09/22/2026 |
| NELSON, BONICE | MIAMI, FL | - | Clinical Social Worker | 03/22/2021 |
| NELSON, CRYSTAL | REDDING, CA | - | Mental Health Counselor | 09/26/2026 |
| NELSON, JADA | WESTBURY, NY | - | Specialist | 09/21/2026 |
| NELSON, MEGAN | MINNETONKA, MN | LICSW | Clinical Social Worker | 08/30/2021 |
| NELSON, MICHELE | CARTERSVILLE, GA | MS | Counselor | 12/14/2017 |
| NELSON, PARKER | PUEBLO, CO | RBT | RBT | 09/21/2026 |
| NELSON, SYDNEY | LEBANON, PA | LCSW | Clinical Social Worker | 07/12/2022 |
| NEMETZ, JONAH | BROOKLYN, NY | - | Mental Health Counselor | 04/09/2026 |
| NENNY COMMUNITY SUPPORT SERVICES, INCORG | BALTIMORE, MD | - | Clinic/Center | 08/10/2026 |
| NEPHEW, AMANDA | LUKE AFB, AZ | PSYD | Psychologist | 04/14/2025 |
| NEPOMUCENO, AIMEE | SNOQUALMIE, WA | LMHCA | Mental Health Counselor | 09/21/2026 |
| NEPSTAD, ALEXANDRA | ARVADA, CO | - | Mental Health Counselor | 09/22/2026 |
| NESBIT, LAUREN | MARINA DEL REY, CA | LCSW | Clinical Social Worker | 08/17/2020 |
| NESBITT-ERBY, BRIDNEY | SPARTANBURG, SC | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| NESBITT, DAMIEN | FORT WAYNE, IN | - | RBT | 09/25/2026 |
| NESTOR, DEVYN | CANONSBURG, PA | LCSW | Clinical Social Worker | 07/01/2019 |
| NETHING, MERRIELLE | GREENVILLE, SC | - | RBT | 09/25/2026 |
| NETTLES, AMEERIA | GULFPORT, MS | - | RBT | 09/22/2026 |
| NETTO, CELESTE | MIAMI, FL | - | RBT | 09/21/2026 |
| NEUHART, MORGAN | MCCONNELSVILLE, OH | - | Case Manager/Care Coordinator | 01/29/2024 |
| NEULS, JOANIE | SAINT LOUIS, MO | - | RBT | 09/25/2026 |
| NEUMANN, CLAIRE | OAKLAND, CA | - | Clinical Social Worker | 09/28/2017 |
| NEUMILLER, MARCIA | CASPER, WY | - | Case Manager/Care Coordinator | 09/24/2026 |
| NEUROBLOOM BEHAVIORAL HEALTH, LLCORG | FAYETTEVILLE, NC | - | Counselor | 12/15/2025 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | WILSONVILLE, OR | - | Counselor | 12/02/2016 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | MCMINNVILLE, OR | - | Counselor | 11/30/2016 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | PORTLAND, OR | - | Counselor | 11/30/2016 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | CLACKAMAS, OR | - | Counselor | 05/06/2020 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | OREGON CITY, OR | - | Counselor | 09/21/2007 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | MEDFORD, OR | - | Counselor | 11/30/2016 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | HILLSBORO, OR | - | Counselor | 11/30/2016 |
| NEUROTHERAPEUTIC PEDIATRIC THERAPIES INCORG | HILLSBORO, OR | - | Counselor | 05/26/2023 |
| NEVIL, GEANELLE | WORCESTER, MA | - | RBT | 09/22/2026 |
| NEW ADULTHOOD COUNSELING PLLCORG | SPOKANE, WA | - | Mental Health Counselor | 01/08/2026 |
| NEW ARROWS COUNSELING, PLLCORG | STATESVILLE, NC | - | Mental Health Counselor | 02/09/2023 |
| NEW CREATION COUNSELING OF ACADIANA, LLCORG | CROWLEY, LA | - | Clinical Social Worker | 05/27/2026 |
| NEW HOPE CHARTER SCHOOLORG | SACRAMENTO, CA | - | Mental Health Counselor | 09/25/2026 |
| NEW HORIZON MEDICAL & DIAGNOSTIC CENTER CORPORG | NORTH MIAMI BEACH, FL | - | Mental Health Counselor | 08/20/2024 |
| NEW PATTERNS COUNSELINGORG | BOCA RATON, FL | - | Clinical Social Worker | 09/21/2026 |
| NEW REFLECTIONS COUNSELING, P.A.ORG | PRINCETON, NJ | - | Mental Health Counselor | 08/20/2024 |
| NEWCOMB, LAUREN | PITTSBURGH, PA | - | RBT | 09/25/2026 |
| NEWELL, SARAH | BARRINGTON, IL | LCSW | Clinical Social Worker | 05/26/2021 |
| NEWLIN, MELISSA | SOUTH EUCLID, OH | LPCC-S, LPAT, ATR-BC | Professional Counselor | 03/28/2017 |
| NEWMAN, ANDREA | WESTMINSTER, CO | - | Counselor | 09/23/2026 |
| NEWMAN, JESSICA | AUSTIN, TX | RBT V, BAT | RBT | 09/23/2026 |
| NEWMAN, KAIA | FORT WAYNE, IN | - | RBT | 08/10/2026 |
| NEWMAN, MARY | SMYRNA, TN | - | RBT | 09/21/2026 |
| NEWMAN, MATTHEW | ALBUQUERQUE, NM | LMHC | Mental Health Counselor | 09/22/2026 |
| NEWSOME, ALYSSA | GRAND RAPIDS, MI | - | RBT | 07/15/2024 |
| NEWTON, KAITLYN | GOOCHLAND, VA | - | Clinical Social Worker | 09/25/2026 |
| NEWTON, LAURA | BRYANT, AR | - | BCBA | 01/21/2019 |
| NEXRCM LLCORG | SAN JOSE, CA | - | Clinic/Center | 09/23/2026 |
| NEXT BREATH PSYCHOLOGY LLPORG | GLENWOOD SPRINGS, CO | - | Specialist | 11/26/2025 |
| NEXT CHAPTER RESTORED INC.ORG | NORTH LAS VEGAS, NV | - | Case Management Agency | 09/21/2026 |
| NEXT IMPRESSIONS SPEECH & LANGUAGE SERVICES PLLCORG | FAYETTEVILLE, NC | - | Speech-Language Pathologist | 09/22/2026 |
| NEXT LEVEL THERAPY AND SUPERVISION, LLCORG | CHICAGO, IL | - | Addiction (Substance Use Disorder) Counselor | 03/04/2025 |
| NEXUMHC CONSULTANTS, PLLCORG | LINCOLNWOOD, IL | - | Clinical Social Worker | 05/15/2023 |
| NEXUS HEALTHCARE STAFFING, LLC.ORG | WESTTOWN, NY | - | Case Manager/Care Coordinator | 09/23/2026 |
| NEXUS SOLUTIONS FOR AUTISM OF OKLAHOMA LLCORG | OKLAHOMA CITY, OK | - | BCBA | 08/20/2018 |
| NG, CHI WING | PORTLAND, OR | PH.D. | Psychologist | 07/10/2025 |
| NG, YEE TING | AUSTIN, TX | BCBA | BCBA | 08/20/2026 |
| NGEP, SOPHIA | MINNEAPOLIS, MN | - | Speech-Language Pathologist | 01/04/2023 |
| NGO, TINH | ROSEMEAD, CA | LCSW | Clinical Social Worker | 08/12/2019 |
| NGUYEN, ANDREW | OAKLAND, CA | - | Counselor | 07/17/2018 |
| NGUYEN, AURYLINA | ORANGE, CA | - | RBT | 09/23/2026 |
| NGUYEN, GRACE | SAN DIEGO, CA | - | Speech-Language Pathologist | 09/22/2026 |
| NGUYEN, HONG | KISSIMMEE, FL | - | Speech-Language Pathologist | 07/21/2022 |
| NGUYEN, JUSTIN | FORT CARSON, CO | LCSW | Clinical Social Worker | 01/19/2022 |
| NGUYEN, MANDY | TAMPA, FL | RBT | RBT | 09/24/2026 |
| NGUYEN, NICHOLE | TRACY, CA | - | RBT | 08/02/2025 |
| NGUYEN, PHI | WESTMINSTER, CA | - | BCBA | 09/26/2026 |
| NGUYEN, PHUONG NGHI | ANN ARBOR, MI | - | RBT | 09/08/2026 |
| NGUYEN, RACHEL | DALY CITY, CA | - | RBT | 09/25/2026 |
| NGUYEN, SHAYNA | LIBERTY, MO | - | RBT | 09/25/2026 |
| NGUYEN, TIFFANY | PORTLAND, OR | - | Mental Health Counselor | 07/02/2025 |
| NGUYEN, YENNY | ORANGE, CA | - | RBT | 09/21/2026 |
| NICHELSON, MORGAN | LINCOLN, NE | - | Mental Health Counselor | 08/12/2024 |
| NICHOLAS, ABIGAIL | PORT ORANGE, FL | RBT | RBT | 09/24/2026 |
| NICHOLLS, ZHENYA | TARPON SPRINGS, FL | - | RBT | 09/22/2026 |
| NICHOLS, CHINA | APPLE VALLEY, CA | - | RBT | 09/24/2026 |
| NICHOLS, CHRISTINA | NEW YORK, NY | PH.D. | Psychologist | 04/19/2007 |
| NICHOLS, KELSEY | PORTLAND, ME | LCSW | Clinical Social Worker | 08/20/2026 |
| NICHOLS, TAKIYLAH | MEMPHIS, TN | - | RBT | 09/23/2026 |
| NICHOLSON, MADELINE | COLUMBUS, GA | RBT | RBT | 01/20/2026 |
| NICHOLSON, MICHELLE | GROVE CITY, OH | - | Case Manager/Care Coordinator | 04/14/2026 |
| NICHOLSON, TAYLOR | BRIGHTON, MI | - | Speech-Language Pathologist | 08/24/2022 |
| NICHOLSON, TIFFANY | TALLMADGE, OH | MA CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| NICKELSON, DIAMOND | NEW ORLEANS, LA | - | Case Manager/Care Coordinator | 09/22/2026 |
| NICKS, ADDISON | SANTA ROSA, CA | - | RBT | 09/22/2026 |
| NICOLAS, BETSY | NORTH PORT, FL | - | RBT | 09/24/2026 |
| NIEDERMAN, LISA | GASTONIA, NC | LCSW | Clinical Social Worker | 08/04/2006 |
| NIELSEN, NINA | AURORA, IL | - | RBT | 06/06/2019 |
| NIELSON, MACIE | SPANISH FORK, UT | - | RBT | 09/23/2026 |
| NIEMEYER, JOHAN | NEW ORLEANS, LA | LCSW | Clinical Social Worker | 09/23/2026 |
| NIEVES SANTIAGO, JOSMARY | COLUMBUS, GA | - | RBT | 09/24/2026 |
| NIEVES, RAQUEL | PHILADELPHIA, PA | - | Speech-Language Pathologist | 09/26/2026 |
| NIKONIUK, PREMLATA | ELGIN, IL | LPC, LCPC, CCMHC CLC | Professional Counselor | 05/12/2011 |
| NINA, NICOLE | DENVER, CO | - | Clinical Social Worker | 08/22/2021 |
| NISSEN, MEGAN | FREMONT, NE | SLP | Speech-Language Pathologist | 09/24/2026 |
| NISTICO, SHARON | NEW WINDSOR, NY | LMHC, LPC | Counselor | 10/19/2022 |
| NIUSUAMALIE, JOCELYN | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| NJINDANGAM, FRANK | BOWIE, MD | - | RBT | 03/24/2025 |
| NJUGUNA, ALANA | ELK GROVE, CA | - | RBT | 09/24/2026 |
| NM COUNSELING INCORG | NAPERVILLE, IL | - | Mental Health Counselor | 10/25/2024 |
| NOC CLINICAL COUNSELING AND CONSULTING, PLLCORG | MCKINNEY, TX | - | Professional Counselor | 03/04/2017 |
| NOEL, RONALD | SACRAMENTO, CA | M.A. RAS | Addiction (Substance Use Disorder) Counselor | 03/22/2011 |
| NOFAL, ISRAA | ORLAND PARK, IL | - | RBT | 09/24/2026 |
| NOFLIN, WADE | SALINAS, CA | - | RBT | 05/24/2021 |
| NOH, HYEMIN | NEW YORK, NY | - | Clinical Social Worker | 09/22/2026 |
| NON-SURGICAL ORTHOPAEDICS PCORG | MARIETTA, GA | - | Specialist | 12/18/2006 |
| NOO, SIMON | ADELPHI, MD | - | Case Manager/Care Coordinator | 10/07/2025 |
| NOOR CLINICAL ASSOCIATES PLLCORG | TAMPA, FL | - | Mental Health Counselor | 09/21/2026 |
| NOOR PSYCHOLOGY & WELLNESS, LLCORG | ORLAND PARK, IL | - | Mental Health Counselor | 02/16/2022 |
| NOOR PSYCHOTHERAPYORG | NOVI, MI | - | Psychologist | 04/17/2024 |
| NORDEN, MICHELLE | WILBRAHAM, MA | BCBA/LABA | BCBA | 11/07/2017 |
| NORMAN-DIAMOND, ELISABETH | PROVIDENCE, RI | - | Clinical Social Worker | 08/17/2026 |
| NORMANLEIER, SALEENA | EVERGREEN, CO | - | BCBA | 10/25/2021 |
| NORRIS-ROCABERTE, RICHARD | CANTON, GA | - | Clinical Social Worker | 09/23/2026 |
| NORRIS, JAMES | VAN NUYS, CA | MH COUNSELOR | Professional Counselor | 08/06/2018 |
| NORRIS, TY | MARIETTA, GA | - | Mental Health Counselor | 09/21/2026 |
| NORTH CENTRAL BEHAVIORAL HEALTH CLINICORG | MINOT, ND | - | Specialist | 06/29/2017 |
| NORTH COLORADO MEDICAL CENTERORG | GREELEY, CO | - | Clinic/Center | 07/14/2006 |
| NORTH SUNFLOWER MEDICAL CENTERORG | BOYLE, MS | - | Clinic/Center | 12/31/2025 |
| NORTH, HOLLY | PFLUGERVILLE, TX | LCSW | Clinical Social Worker | 09/21/2026 |
| NORTH, TIMISHIA | CYPRESS, TX | RBT | RBT | 06/09/2021 |
| NORTHEAST PSYCHOLOGICAL WELLNESS, PLLCORG | NEW YORK, NY | - | Psychologist | 07/08/2019 |
| NORTHERN COMPASS CARE LLCORG | NAUKATI BAY, AK | - | Community/Behavioral Health Agency | 07/21/2026 |
| NORTHERN MEDICAL CARE PCORG | CORONA, NY | - | Clinic/Center | 07/03/2015 |
| NORTHRIP, HATTIE | DENVER, CO | - | Case Manager/Care Coordinator | 09/23/2026 |
| NORTHSTAR BEHAVIORAL HEALTH & ABA THERAPY LLCORG | WAUKEGAN, IL | - | BCBA | 09/25/2026 |
| NORTHWEST SOLSTICE COUNSELING, PLLCORG | BELLEVUE, WA | - | Mental Health Counselor | 09/25/2026 |
| NORTON, SUSAN | LONDONDERRY, NH | LICSW | Clinical Social Worker | 10/10/2006 |
| NOSANOV, MICHAEL | MARSHALL, MI | MD | Specialist | 04/12/2006 |
| NOVA DMV NURSES AND CAREGIVERS LLCORG | BROADLANDS, VA | - | Case Manager/Care Coordinator | 08/01/2024 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 07/17/2009 |
| NOVA IC, INC.ORG | GREENVILLE, NC | - | Psychologist | 12/08/2009 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 04/12/2011 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Case Management Agency | 04/12/2011 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 01/08/2011 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Case Management Agency | 08/25/2010 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 04/28/2011 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 12/08/2010 |
| NOVA IC, INC.ORG | GOLDSBORO, NC | - | Psychologist | 05/26/2010 |
| NOVAK, DANIEL | WEST LINN, OR | PHD, LCSW, LICSW | Clinical Social Worker | 01/10/2006 |
| NOVAK, FOREST | SAN PABLO, CA | - | RBT | 12/17/2018 |
| NOVANT HEALTH NORTHERN REGIONAL MEDICAL CENTER, LLCORG | MOUNT AIRY, NC | - | Specialist | 09/23/2026 |
| NOVI COUNSELING SERVICES PLLCORG | PARK RIDGE, IL | - | Professional Counselor | 08/24/2023 |
| NOWAK, ZACHARY | VAN NUYS, CA | - | RBT | 09/22/2026 |
| NOWICKI, HEIDI | LAFAYETTE, LA | - | Counselor | 09/22/2026 |
| NSAMENKA, MARY-NIVES | UPPER MARLBORO, MD | - | Case Manager/Care Coordinator | 04/19/2012 |
| NU, ESTHER | FORT WAYNE, IN | - | RBT | 09/21/2026 |
| NUALLES, GRISELL | MIAMI, FL | - | Assistant Behavior Analyst | 11/08/2016 |
| NUESTRO, MICHAEL | CHULA VISTA, CA | - | RBT | 09/24/2026 |
| NUEVO DIA BEHAVIORAL HEALTH CARE LLCORG | LAS CRUCES, NM | - | Community/Behavioral Health Agency | 02/05/2020 |
| NUGENT, EMILY | WANTAGH, NY | MS SLP CCC TSSLD | Speech-Language Pathologist | 09/25/2026 |
| NUNEZ, BIANCA | SAN DIEGO, CA | - | Case Manager/Care Coordinator | 09/23/2026 |
| NUNEZ, GABRIELA | JEFFERSON VALLEY, NY | - | Speech-Language Pathologist | 09/25/2026 |
| NUNEZ, IVELISSE | BROOKLYN, NY | MS, CCC-SLP, NYS LIC | Speech-Language Pathologist | 09/26/2026 |
| NUNN, KARA | JOHNSON CITY, NY | M.S., CCC-SLP | Speech-Language Pathologist | 08/24/2011 |
| NURNBERG, DEBORAH | SPRINGFIELD, MO | PLPC | Professional Counselor | 09/25/2026 |
| NURTURED MINDS THERAPY LLCORG | NEWARK, NJ | - | Community/Behavioral Health Agency | 09/25/2026 |
| NURTURED PATH ACADEMY LLCORG | KETTERING, OH | - | BCBA | 09/22/2026 |
| NURTURING HEARTS THERAPEUTIC SERVICESORG | ST PETERSBURG, FL | - | Clinical Social Worker | 09/22/2026 |
| NUSS, OLIVIA | FREDERICK, MD | - | Mental Health Counselor | 06/09/2023 |
| NUZZI, EMMA | MELVILLE, NY | - | RBT | 09/23/2026 |
| NWAKUCHE, AMA-ECHI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| NWOSU, KELECHI | CYPRESS, TX | - | BCBA | 02/28/2018 |
| NYARKO, ERNESTINA | APOPKA, FL | - | BCBA | 05/03/2025 |
| O'BRIEN, ARIANNA | PITTSFIELD, MA | - | Counselor | 09/10/2024 |
| O'BRIEN, KATHLEEN | MINNEAPOLIS, MN | MSW, LICSW | Clinical Social Worker | 09/22/2026 |
| O'BRIEN, MICHELLE | LAKEWOOD, CO | RBT | RBT | 02/12/2021 |
| O'BRIEN, SHANNON | LANCASTER, CA | LCSW | Clinical Social Worker | 03/20/2021 |
| O'BRYAN, KELLY | OCEANSIDE, CA | PH.D. | Psychologist | 11/29/2006 |
| O'CAREY, JULIA | BENTON HARBOR, MI | LLMSW | Clinical Social Worker | 09/21/2026 |
| O'CLAIR, OLIVIA | WINSTON SALEM, NC | - | Mental Health Counselor | 11/26/2025 |
| O'CONNELL, AMANDA | GREENFIELD, WI | - | Mental Health Counselor | 09/23/2022 |
| O'CONNOR, ANDREW | UNION, NJ | - | BCBA | 05/04/2023 |
| O'CONNOR, BLAKE | BOULDER, CO | MED | Clinical Social Worker | 09/23/2026 |
| O'CONNOR, SEAN | WHITE PLAINS, NY | LMHC | Mental Health Counselor | 04/12/2023 |
| O'CUILINN, DIANA | CONCORD, CA | - | RBT | 09/29/2020 |
| O'DELL, JENNIFER | NORTHFIELD, VT | LCMHC | Mental Health Counselor | 09/21/2026 |
| O'DONOGHUE, HANNAH | LOMBARD, IL | - | BCBA | 11/26/2024 |
| O'GRADY, CAITRIONA | SAN FRANCISCO, CA | LICSW | Clinical Social Worker | 09/03/2019 |
| O'MEARA, CRYSTAL | HUBBARD, OH | LICDC | Mental Health Counselor | 07/18/2019 |
| O'MEARA, ISABELLA | LANSING, MI | - | RBT | 09/21/2026 |
| O'NEIL, MELINDA | PLEASANTON, CA | MA, APCC | Mental Health Counselor | 04/09/2024 |
| O'SHEA, CONNOR | EUGENE, OR | - | Clinical Social Worker | 08/19/2020 |
| O'SHEA, PHOENIX | SACRAMENTO, CA | MSW | Clinical Social Worker | 07/19/2017 |
| OAK & ARROW BEHAVIORAL SERVICES, LLCORG | GRISWOLD, CT | - | BCBA | 09/02/2026 |
| OAK PSYCHOLOGY CENTER, P.A.ORG | TAMPA, FL | - | Psychologist | 09/22/2026 |
| OAK STREET HEALTH OF NEW YORK MEDICAL GROUP PCORG | BROOKLYN, NY | - | Clinical Social Worker | 06/09/2020 |
| OAKES, AMAZING | AURORA, CO | BCBA | RBT | 02/25/2026 |
| OATES, ARNITRA | GASTONIA, NC | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| OBANGUALA, INCORG | HIALEAH, FL | - | BCBA | 09/13/2010 |
| OBAS, SANDRA | AVENTURA, FL | LCSW | Clinical Social Worker | 04/11/2017 |
| OBERG, LAURA | RENO, NV | RD | Clinical Social Worker | 02/15/2021 |
| OBERG, SARA | SAINT PAUL, MN | - | Speech-Language Pathologist | 09/21/2007 |
| OBNER, ROBERT | NEW SMYRNA BEACH, FL | - | BCBA | 09/21/2026 |
| OBOZNAYA, DARINA | SPOKANE, WA | - | Counselor | 01/10/2023 |
| OCAMPO, ALYSSA | ONTARIO, CA | - | RBT | 09/22/2026 |
| OCD AND ANXIETY OF THE WOODLANDS, PLLCORG | THE WOODLANDS, TX | - | Clinical Social Worker | 09/22/2026 |
| OCEAN WAVE ABA LLCORG | CENTENNIAL, CO | - | BCBA | 06/09/2026 |
| OCHOA QUEVEDO, YANAELI | WALNUT CREEK, CA | - | RBT | 09/21/2026 |
| OCHOA, GABRIELA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| OCHOA, NANCY | GARNER, NC | - | BCBA | 01/31/2020 |
| ODEGAARD, AMY | POLSON, MT | MSW, LCSW | Clinical Social Worker | 02/24/2016 |
| ODOM, HAILEY | WILMINGTON, NC | - | RBT | 09/23/2026 |
| ODOM, JOANNE | WASHINGTON, DC | LICSW, LCSW-C | Clinical Social Worker | 09/15/2006 |
| ODOU, CALEB | WILMINGTON, DE | - | RBT | 09/21/2026 |
| OGDEE, JASALYNN | BATON ROUGE, LA | - | RBT | 09/25/2026 |
| OGLE, LAUREN | OSWEGO, IL | - | Clinical Social Worker | 11/30/2021 |
| OGLESBY, YOLANDA | DAYTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| OJEDA, EMILY | SAN BERNARDINO, CA | - | RBT | 09/21/2026 |
| OK ELLA LLCORG | DURHAM, NC | - | Community/Behavioral Health Agency | 09/23/2026 |
| OKAMMOR, AMELIA | WINTER PARK, FL | - | Mental Health Counselor | 09/26/2026 |
| OKEKE, KAYLE | MIAMI, FL | LMHC | Mental Health Counselor | 09/26/2026 |
| OKEREKE, KATE | FOLSOM, PA | LCSW | Mental Health Counselor | 09/26/2026 |
| OKONSKY, ERIN | CYPRESS, TX | - | RBT | 09/21/2026 |
| OKORO, OPE | LANHAM, MD | BLS | RBT | 07/18/2022 |
| OKOYE, FAITH | ROUND ROCK, TX | - | RBT | 09/22/2026 |
| OKPERE, ROSSY | CHERRYLAND, CA | - | Day Training/Habilitation Specialist | 06/25/2026 |
| OKRASINSKI, AMY | COCOA, FL | - | Mental Health Counselor | 09/23/2026 |
| OLAYA, EVELYN | PLANO, TX | - | BCBA | 09/22/2026 |
| OLENCHEK, JULIA | MILWAUKEE, WI | - | Speech-Language Pathologist | 09/25/2026 |
| OLESKY, EMILY | KALAMAZOO, MI | - | RBT | 09/23/2026 |
| OLIVARES, BRIAN | SAN BRUNO, CA | - | RBT | 09/22/2026 |
| OLIVARES, ZOE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| OLIVE BRANCH BEHAVIORAL HEALTH NETWORK LLCORG | TOLEDO, OH | - | Community/Behavioral Health Agency | 09/22/2026 |
| OLIVE TREE MENTAL WELLNESS, PLLCORG | BRIDGEVIEW, IL | - | Psychologist | 08/17/2022 |
| OLIVER, MERCIANNA | ATLANTA, GA | LPC, LPCC | Counselor | 09/25/2017 |
| OLMOS, LESLIE | STOCKTON, CA | - | RBT | 09/26/2026 |
| OLNEY COMMUNITY COUNSELING CENTERORG | OLNEY, TX | - | Community/Behavioral Health Agency | 09/23/2026 |
| OLOWUDE, BRIAN | SANTA MARIA, CA | PHD | Psychologist | 08/15/2006 |
| OLSEN, SHAWNA | EUGENE, OR | LE | Specialist | 07/19/2025 |
| OLSEN, SUNNY | ALBUQUERQUE, NM | - | Psychologist | 10/18/2017 |
| OLSON, JENNA | WOODBURY, MN | MSW | Clinical Social Worker | 11/19/2025 |
| OLSON, REBECCA | KENOSHA, WI | SLP - CCC, MA | Speech-Language Pathologist | 09/24/2026 |
| OLSON, STEPHANIE | ROSEMOUNT, MN | MS, CCC-SLP | Speech-Language Pathologist | 07/08/2022 |
| OLVERA, ARIEL | EAGLE, ID | LCSQ | Clinical Social Worker | 02/25/2015 |
| OMAR, OMAR | BURNSVILLE, MN | - | RBT | 09/21/2026 |
| OMER, DANYA | SAN JOSE, CA | - | RBT | 09/25/2026 |
| OMITOGUN, YETUNDE | SANDY SPRING, MD | LGPC | Counselor | 09/24/2026 |
| OMOBUDE, MEAGHON | WASHINGTON, DC | - | Mental Health Counselor | 01/04/2023 |
| OMOHUNDRO, MADISON | SANDY, OR | BS | Counselor | 10/12/2018 |
| OMOTUYI, OLUSEMILOORE | KATY, TX | - | Mental Health Counselor | 05/20/2025 |
| ONAMUTI, AISHA | DORAVILLE, GA | LPN | Clinical Social Worker | 06/22/2018 |
| ONE HEART BEHAVIORAL HEALTHORG | RESEDA, CA | - | Clinical Social Worker | 01/22/2025 |
| ONE:12 COUNSELING PLLCORG | CHARLOTTE, NC | - | Counselor | 01/08/2020 |
| ONEAL, KAELYN | MELBOURNE, FL | - | RBT | 09/23/2026 |
| ONEIL, STEPHANIE | NEW LENOX, IL | LPC, NCC | Professional Counselor | 09/21/2026 |
| ONGOING PATHWAY TO EMPOWERMENT COUNSELING PLLCORG | EDMOND, OK | - | Clinical Social Worker | 09/22/2026 |
| ONHEALING THERAPYORG | SAN ANTONIO, TX | - | Professional Counselor | 05/24/2023 |
| ONTIVEROS, MICHELLE | MOORPARK, CA | - | RBT | 09/21/2026 |
| ONYX COLLECTIVEORG | ATLANTA, GA | - | Mental Health Counselor | 09/25/2026 |
| OPPEN, JACK | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| OQUENDO, DILIANYS | FORT LAUDERDALE, FL | BS | Case Manager/Care Coordinator | 08/19/2020 |
| ORBE, VICTORIA | KALAMAZOO, MI | LMSW | Counselor | 02/23/2016 |
| ORBIN, ANGELINA | NILES, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| ORCHARD SLOAN, SHERI | SPRINGFIELD, MO | LPC | Professional Counselor | 10/10/2011 |
| ORDONEZ, KATHERINE | CHICAGO, IL | - | Clinical Social Worker | 06/18/2025 |
| ORDWAY, JOHNATHAN | UNIVERSITY PLACE, WA | - | Mental Health Counselor | 09/21/2026 |
| ORELLANA FONSECA, RUBY | SAN DIEGO, CA | - | RBT | 09/24/2026 |
| OREN, JOSHUA | BAY CITY, MI | - | RBT | 09/24/2026 |
| ORENDAY, ADAM | LOS ANGELES, CA | - | RBT | 09/25/2026 |
| ORESKOVIC, TYLER | BROOKLYN, NY | MS, LCPC | Mental Health Counselor | 07/23/2021 |
| ORLANDO, TRACI | VANCOUVER, WA | LMHC | Mental Health Counselor | 10/03/2022 |
| OROSCO, KARI | BOWLING GREEN, KY | LCSW | Clinical Social Worker | 08/05/2019 |
| OROZCO, JOSE | UKIAH, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| OROZCO, KELLY | VANCOUVER, WA | - | Mental Health Counselor | 09/21/2026 |
| ORR, MADELINE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| ORSO, ARIANNA | KINGSTON, NY | MHC-LP | Mental Health Counselor | 07/31/2026 |
| ORTEGA ROJAS, JOCELYN | LAS VEGAS, NV | - | Mental Health Counselor | 09/26/2026 |
| ORTEGA, ASHANTY | ANAHEIM, CA | - | RBT | 09/22/2026 |
| ORTEGA, CONNIE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| ORTEGA, MICHELLE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| ORTEGA, PATRITICIA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ORTEGA, RACHEL | CYPRESS, TX | - | RBT | 09/21/2026 |
| ORTEGA, VALERIA | RIVERSIDE, CA | - | RBT | 09/25/2026 |
| ORTIZ GONZALEZ, JULIO | LAS VEGAS, NV | APRN-CNP, FNP-C | Counselor | 04/18/2016 |
| ORTIZ PROFESSIONAL SERVICES LLCORG | ORANGE PARK, FL | - | Counselor | 11/29/2023 |
| ORTIZ-LUIS, ISABELLE | CITRUS HEIGHTS, CA | - | RBT | 09/23/2026 |
| ORTIZ-MELO, CAROLINE | BOCA RATON, FL | - | BCBA | 12/13/2021 |
| ORTIZ, ALEJANDRA | SOMERSET, NJ | M.A., BCBA | RBT | 05/21/2021 |
| ORTIZ, ANA | ROSLINDALE, MA | PH.D. | Psychologist | 03/01/2007 |
| ORTIZ, ANNETTE | MIAMI, FL | - | Speech-Language Pathologist | 09/21/2026 |
| ORTIZ, CATALINA | ORANGE, CA | - | RBT | 09/22/2026 |
| ORTIZ, HOLLY | SANTA FE, NM | - | RBT | 09/23/2026 |
| ORTIZ, RAFAEL | NAPA, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| ORTIZ, VALERIA | NOTTINGHAM, MD | - | Mental Health Counselor | 09/21/2026 |
| ORTIZ, VICTORIA | NEW BRAUNFELS, TX | LCSW-S | Clinical Social Worker | 03/15/2022 |
| ORVEX MEDICAL LLCORG | HOUSTON, TX | - | Clinic/Center | 07/09/2026 |
| OSANAI, CASSANDRA MHAY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| OSBORN, ELIZABETH | BROOMFIELD, CO | - | Mental Health Counselor | 09/04/2024 |
| OSEBOR, JOEL | BOWIE, MD | - | Professional Counselor | 09/22/2026 |
| OSEGUERA, GINA | CHICAGO, IL | - | Mental Health Counselor | 09/21/2026 |
| OSGOOD, GRACE | KNOXVILLE, TN | - | Speech-Language Pathologist | 09/21/2026 |
| OSHILIM, ZAMIJAH | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| OSMAN, BASMA | HAYWARD, CA | - | RBT | 09/02/2025 |
| OSMAN, ELYAS | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| OSMAN, FARTUN | COSTA MESA, CA | - | RBT | 09/22/2026 |
| OSMAN, KATE | GREENWICH, CT | LCSW | Clinical Social Worker | 09/26/2026 |
| OSORIO, VALERIA | TORRANCE, CA | - | RBT | 09/21/2026 |
| OSTROLENCKI, HAILEY | PORTAGE, MI | - | RBT | 09/21/2026 |
| OSTROM, DUSTIN | CLARKSVILLE, TN | - | Mental Health Counselor | 09/23/2026 |
| OSWALD, MARISSA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| OTERO CABRERA, RAFAEL | CAROLINA, PR | LP | Psychologist | 07/10/2023 |
| OTERO, WILLIAM | BELEN, NM | - | RBT | 09/23/2026 |
| OTO, BRANDY | MAPLE VALLEY, WA | LMHC, CDP | Mental Health Counselor | 10/24/2017 |
| OTT, ELIZABETH | TOPEKA, KS | SLP | Speech-Language Pathologist | 02/27/2013 |
| OTTERLY RESILIENT COUNSELING, LLCORG | BOISE, ID | - | Counselor | 04/21/2025 |
| OTTONE, MARIANO | SALT LAKE CITY, UT | MS | Psychologist | 04/21/2025 |
| OUR CLIMB LLCORG | BUTLER, NJ | - | Community/Behavioral Health Agency | 09/21/2026 |
| OURHEALTH PROFESSIONAL PHYSICIAN GROUP, LLCORG | TOBACCOVILLE, NC | - | Clinic/Center | 11/27/2019 |
| OURHEALTH PROFESSIONAL PHYSICIAN GROUP, LLCORG | DOBSON, NC | - | Clinic/Center | 02/20/2020 |
| OURHEALTH PROFESSIONAL PHYSICIAN GROUP, LLCORG | WINSTON SALEM, NC | - | Clinic/Center | 11/25/2019 |
| OUT OF THE BLUE PRODUCTIONS INC.ORG | BROOKLYN, NY | - | Clinical Social Worker | 09/23/2026 |
| OUVRIER, KATELYNN | OXNARD, CA | - | Mental Health Counselor | 09/24/2026 |
| OVALLE MAHMOOD, AYESHAH | SOUTH BEND, IN | LMHC | Mental Health Counselor | 05/10/2023 |
| OVANTRA LLCORG | SANTA CLARA, CA | - | Clinic/Center | 09/18/2026 |
| OVERBAY, CURIOSITY | PLANO, TX | - | Clinical Social Worker | 06/27/2023 |
| OVERFLOW MENTAL HEALTH LLCORG | ROCKY RIVER, OH | - | Clinical Social Worker | 09/21/2026 |
| OVERHAGE, TAMARA | SUN CITY, AZ | - | RBT | 09/23/2026 |
| OVERSTREET, DIONTE | CLEVELAND, OH | - | Professional Counselor | 08/15/2025 |
| OWATE, JENNIFER | AKRON, OH | - | Counselor | 11/01/2023 |
| OWEN, ISABELLA | WOOSTER, OH | QMHS-BACH | RBT | 09/23/2026 |
| OWEN, KAYLEE | WEST JORDAN, UT | - | RBT | 09/22/2026 |
| OWEN, KELLY | CINNAMINSON, NJ | - | BCBA | 09/25/2026 |
| OWEN, ROBERT | FORT SAM HOUSTON, TX | LCSW | Clinical Social Worker | 11/04/2005 |
| OWENS-JURGENS, RUTH | EMPORIA, KS | LCP LCAC | Clinical Social Worker | 11/07/2018 |
| OWIMAST HEALTH LLCORG | JACKSONVILLE, FL | - | Mental Health Counselor | 01/19/2022 |
| OYEBODE, ELIZABETH | OAKLAND, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| OYOLA, GIANLIER | TAMPA, FL | - | RBT | 09/21/2026 |
| OZMORE, REBECCA | MIDLOTHIAN, VA | M.ED., LPC | Mental Health Counselor | 09/21/2026 |
| OZTURK, CAITLAIN | LOS ANGELES, CA | BII | BCBA | 09/21/2026 |
| P.I.N.C. PSYCHIATRIC SERVICES, PLLCORG | GUYMON, OK | - | Community/Behavioral Health Agency | 02/04/2025 |
| P37 IOMORG | EULESS, TX | - | Specialist | 09/05/2014 |
| PABISZ, SKYLAR | LANSING, MI | - | Speech-Language Pathologist | 09/24/2026 |
| PACAL, JASMINE | SAN DIEGO, CA | - | Mental Health Counselor | 03/09/2022 |
| PACE, BRITT | FRISCO, TX | - | RBT | 09/23/2026 |
| PACHAEVA, IULIIA | GLENVIEW, IL | - | RBT | 09/23/2026 |
| PACHECO-VASQUEZ, JAZMIN | VAN NUYS, CA | - | RBT | 09/25/2026 |
| PACHECO, ASHLEY | FAIRFIELD, CA | - | Day Training/Habilitation Specialist | 12/15/2021 |
| PACHECO, CIERRA | LODI, CA | M.S., CCC-SLP | Speech-Language Pathologist | 05/07/2018 |
| PACHECO, JENNIFER | NEW BEDFORD, MA | - | BCBA | 09/21/2026 |
| PACHECO, MINERVA | NEW BRITAIN, CT | - | BCBA | 09/23/2026 |
| PACIFIC NEPHROLOGY LLCORG | WAILUKU, HI | - | Specialist | 03/05/2008 |
| PACIFIC SPEECH AND NEUROLOGICAL REHABILITATION, PLLCORG | OLYMPIA, WA | - | Speech-Language Pathologist | 09/05/2026 |
| PACIFICO, KELLA ANN | BROOMALL, PA | LPC | Mental Health Counselor | 08/11/2026 |
| PADEN, BRITTANY | SIMI VALLEY, CA | - | RBT | 09/21/2026 |
| PADGETT, DEON | COLUMBUS, OH | - | Case Manager/Care Coordinator | 08/15/2026 |
| PADGETT, TERESA | ALEXANDRIA, VA | - | Mental Health Counselor | 04/11/2026 |
| PADILLA, KAIRI | SAINT JOHNS, FL | - | BCBA | 09/22/2026 |
| PADILLA, MIRANDA | ROBINSON, TX | LPC | Professional Counselor | 03/26/2026 |
| PADILLA, SAGE | TRACY, CA | CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| PADRINO, MARIA | MIAMI, FL | - | RBT | 03/06/2025 |
| PAEK, JOANNE | NORTH CHESTERFIELD, VA | M.S. | Mental Health Counselor | 09/21/2020 |
| PAGE, LOUISE | BLOOMINGTON, MN | L.P.C.C. | Professional Counselor | 11/14/2006 |
| PAGE, SYDNEY | MATTESON, IL | - | Case Manager/Care Coordinator | 09/21/2026 |
| PAGE, TAYVION | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| PAI, TIMOTHY | FAIR LAWN, NJ | - | Mental Health Counselor | 09/24/2026 |
| PAIGE, NANCY | MURRAY, UT | LMFT | Mental Health Counselor | 01/07/2021 |
| PAINTER, MELISSA | CROWDER, MS | LPC | Professional Counselor | 12/20/2023 |
| PAIZ, KAYLEY | HAYWARD, CA | - | RBT | 09/25/2026 |
| PAJARES, KIMI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| PALACIO GARCIA, PRISCILA | NAPA, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| PALACIOS HARNESS, LETICIA | REDMOND, OR | LSW | Mental Health Counselor | 09/01/2026 |
| PALACIOS, JASMINE | COSTA MESA, CA | - | RBT | 09/21/2026 |
| PALACIOS, KIMBERLY | EL PASO, TX | - | RBT | 09/21/2026 |
| PALAFOX, THERESA | SAN DIEGO, CA | - | Professional Counselor | 07/16/2018 |
| PALM SPEECH CONSULTING INC.ORG | LAKE WORTH, FL | - | Speech-Language Pathologist | 09/21/2026 |
| PALMER, CRISTINA | RIALTO, CA | - | Day Training/Habilitation Specialist | 09/21/2026 |
| PALMER, DIANN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| PALMER, DYLAN | MILILANI, HI | - | RBT | 09/24/2026 |
| PALMER, JULIE | FOREST, VA | - | Professional Counselor | 10/13/2025 |
| PALMER, LEANA | BOWIE, MD | - | RBT | 09/23/2026 |
| PALMER, MEIRE | FORT WALTON BEACH, FL | - | Mental Health Counselor | 09/21/2026 |
| PALOMBINI, LINDSAY | MC KEES ROCKS, PA | LCSW | Clinical Social Worker | 09/23/2026 |
| PALUMBO, PAUL | VILLA PARK, IL | LCSW | Clinical Social Worker | 09/21/2026 |
| PAN, MARY | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| PANDO, NUBIA | DEERFIELD BEACH, FL | - | RBT | 09/23/2026 |
| PANETO-CAMACHO, MAGALY | SABANA GRANDE, PR | LCSW | Clinical Social Worker | 06/26/2024 |
| PANGANIBAN, ALIANA | SACRAMENTO, CA | - | RBT | 09/21/2026 |
| PANGEA HOPE PROFESSIONAL CLINICAL COUNSELOR CORPORATIONORG | BAKERSFIELD, CA | - | Professional Counselor | 08/21/2026 |
| PANJATHIA, ARUN | CLEVELAND, OH | MD | Specialist | 09/22/2026 |
| PANNELL, BRESLYN | LAKEWOOD, OH | - | Speech-Language Pathologist | 09/23/2020 |
| PANNELL, SHANTA | DANVILLE, VA | MA., QMHP-C | Addiction (Substance Use Disorder) Counselor | 04/17/2025 |
| PANNELL, VANESSA | SOUTHLAKE, TX | LMSW | Mental Health Counselor | 09/24/2026 |
| PANSANO, ISABELLA | PHOENIX, AZ | - | RBT | 09/21/2026 |
| PANTER BEHAVIORAL CONSULTING PLLCORG | WICHITA FALLS, TX | - | BCBA | 05/18/2026 |
| PAPPAS, AIKATERINI | CITRUS HEIGHTS, CA | - | RBT | 09/23/2026 |
| PARA TI COUNSELING PLLCORG | WESLACO, TX | - | Mental Health Counselor | 09/25/2026 |
| PARADA PERDOMO, YANCY | CUTLER BAY, FL | - | RBT | 11/15/2021 |
| PARADA, JENADEY | LANCASTER, CA | - | RBT | 09/25/2026 |
| PARDI, HEATHER | BROCKTON, MA | - | Clinical Social Worker | 09/21/2026 |
| PARDO RODRIGUEZ, DANIELA | MIAMI, FL | - | RBT | 06/26/2024 |
| PAREKH, VIHAAN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| PARENTS ANONYMOUS INC.ORG | VAN NUYS, CA | - | Professional Counselor | 02/03/2025 |
| PARETTE, LINLEY | DELAND, FL | - | RBT | 09/21/2026 |
| PARIENTE, SAMANTHA | SAN FERNANDO, CA | - | RBT | 09/22/2026 |
| PARILLO, HANNAH | WARRENSVILLE HEIGHTS, OH | - | RBT | 09/22/2026 |
| PARISE, MICHELLE | WOODBURY, NY | - | Speech-Language Pathologist | 08/29/2022 |
| PARISH HEALTH AND WELLNESS, INC.ORG | RED BLUFF, CA | - | Counselor | 05/31/2023 |
| PARISH HEALTH AND WELLNESS, INC.ORG | RED BLUFF, CA | - | Mental Health Counselor | 12/23/2016 |
| PARKER, BAILEY | DIAMOND SPRINGS, CA | LPCC | Professional Counselor | 02/13/2024 |
| PARKER, CARLY | RALEIGH, NC | MSW, LCSW, LCAS | Clinical Social Worker | 08/27/2014 |
| PARKER, JAMAL | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| PARKER, JENNIFER | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| PARKER, KYLA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| PARKER, ROGENIA | GAITHERSBURG, MD | LCSW | Clinical Social Worker | 02/09/2015 |
| PARKER, SALLY | MORGANTOWN, WV | - | Case Manager/Care Coordinator | 03/19/2025 |
| PARKER, VICTORIA | BOWIE, MD | - | RBT | 09/23/2026 |
| PARKS, DESTINIE | BRIGHTON, TN | RBT | RBT | 09/25/2026 |
| PARR, ANDREA | BELOIT, WI | MS/CCC/SLP | Speech-Language Pathologist | 09/07/2017 |
| PARRA, AZUCENA | LOVINGTON, NM | - | RBT | 08/11/2026 |
| PARRA, FABIANA | DAVENPORT, FL | - | RBT | 09/25/2026 |
| PARRILLA BETANCOURT, DAPHNE | RIO GRANDE, PR | LCSW,MSW | Clinical Social Worker | 03/21/2023 |
| PARRISH, AMANDA | SAN DIEGO, CA | LCSW | Clinical Social Worker | 07/01/2022 |
| PARRISH, SARA | CINCINNATI, OH | - | Mental Health Counselor | 10/22/2025 |
| PARRISH, SHAMARI | JEFFERSONVILLE, IN | MA, LMHCA | Mental Health Counselor | 09/21/2026 |
| PARRISH, VANESSA | NEW ALBANY, IN | - | RBT | 04/03/2025 |
| PARROCHA, CYPRO CRAIG CYLER | RIVERBANK, CA | - | RBT | 09/21/2026 |
| PARROTT, ADRIANNA | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| PARSONS, LEXUS | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| PARTIN, SHELBY | KNIGHTDALE, NC | LCSWA, CPSS | Clinical Social Worker | 09/10/2024 |
| PASCUAL, MARIANA | OMAHA, NE | - | RBT | 09/24/2026 |
| PASQUALE, ALLISON | NIAGARA FALLS, NY | - | Speech-Language Pathologist | 06/20/2025 |
| PASS, BRIANA | BRONX, NY | - | Case Manager/Care Coordinator | 09/25/2026 |
| PATE, MICHAELA | AUSTIN, TX | - | RBT | 09/21/2026 |
| PATEK, MELISSA | VICTORIA, TX | SLP | Speech-Language Pathologist | 09/21/2026 |
| PATEL, ASHVI | CLEVELAND, OH | - | Case Manager/Care Coordinator | 06/15/2026 |
| PATEL, HIRAL | BASEHOR, KS | - | RBT | 09/25/2025 |
| PATEL, KAJAL | PHILADELPHIA, PA | LPC | Professional Counselor | 04/29/2026 |
| PATEL, MIRA | WATERFORD, CT | LCSW | Clinical Social Worker | 02/01/2023 |
| PATEL, NIKI | WEST BLOOMFIELD, MI | - | RBT | 09/22/2026 |
| PATEL, PARITABEN | CLEVELAND, OH | - | Case Manager/Care Coordinator | 07/13/2026 |
| PATEL, PRERNA | LAKELAND, FL | - | RBT | 09/21/2026 |
| PATEL, PURVA | HOUSTON, TX | LMFT, LPC | Professional Counselor | 04/23/2014 |
| PATEL, RUDRA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| PATEL, RUPA | CRANFORD, NJ | MD | Specialist | 08/16/2006 |
| PATEL, VAIDEHI | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| PATERSON, HEATHER | ALGONQUIN, IL | MA, LPC | Mental Health Counselor | 01/27/2021 |
| PATETSIOS, PETER | QUEENS VILLAGE, NY | M.D., F.A.C.S | Specialist | 01/28/2006 |
| PATH THERAPY SERVICES, LLCORG | YOUNGSTOWN, OH | - | Addiction (Substance Use Disorder) Counselor | 12/01/2025 |
| PATHWAYS OF OHIO COUNSELING SERVICES, LLCORG | POLAND, OH | - | Clinical Social Worker | 12/30/2008 |
| PATHWAZE RECOVERY CENTER, LLCORG | PALM SPRINGS, FL | - | Community/Behavioral Health Agency | 07/14/2025 |
| PATINO FLORES, BARBARA | SALEM, OR | - | RBT | 06/01/2020 |
| PATINO, MIGUEL | MCALLEN, TX | - | Assistant Behavior Analyst | 09/24/2026 |
| PATLAN, MARGARITA | CORPUS CHRISTI, TX | - | RBT | 09/25/2026 |
| PATRICIA DAVIS LCSW LLCORG | RED BANK, NJ | - | Clinical Social Worker | 09/22/2026 |
| PATRICK, ALEXA | DALLAS, TX | LPC | Professional Counselor | 06/21/2021 |
| PATRICK, ALYSSA | CLOVIS, NM | - | RBT | 09/23/2026 |
| PATRICK, CHANEL | CHARLOTTE, NC | - | Addiction (Substance Use Disorder) Counselor | 04/19/2022 |
| PATRICK, KIMBERLY | BRISTOL, VA | LCSW | Clinical Social Worker | 11/01/2019 |
| PATRONE, RINIYA | BROOMALL, PA | - | RBT | 09/21/2026 |
| PATTERSON, ANNA | POPLAR BLUFF, MO | CSACII | Addiction (Substance Use Disorder) Counselor | 11/20/2008 |
| PATTERSON, ASHLEY | CHATTANOOGA, TN | - | RBT | 09/22/2026 |
| PATTERSON, JADA | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| PATTERSON, MITCHELL | COLUMBUS, OH | - | Addiction (Substance Use Disorder) Counselor | 07/29/2020 |
| PATTON, DEVON | BURNSVILLE, MN | - | RBT | 01/18/2021 |
| PATTON, ELEANOR | PHILADELPHIA, PA | LSW | Clinical Social Worker | 09/24/2026 |
| PAUL, MEGAN | CAMBRIDGE, MN | LPCC | Professional Counselor | 09/06/2023 |
| PAULINO, HENESSYS | SECAUCUS, NJ | PSYD | Psychologist | 09/22/2026 |
| PAULS, DIANA | MODESTO, CA | - | Clinical Social Worker | 10/04/2022 |
| PAVENTY, MARILYN | RED BLUFF, CA | LCSW | Mental Health Counselor | 08/17/2009 |
| PAVLOVICH, LINDSAY | JOHNSTOWN, PA | M.S., CCC-SLP | Speech-Language Pathologist | 01/25/2017 |
| PAWLICKI, MARY | LAKE IN THE HILLS, IL | - | Speech-Language Pathologist | 09/25/2026 |
| PAYETTE, BRITTNEY | LAWTON, OK | - | Case Manager/Care Coordinator | 02/25/2026 |
| PAYNE, KIARRA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| PAYNE, TYJVANNA | LAWRENCEVILLE, GA | LPC | Professional Counselor | 04/14/2016 |
| PAZ, JAMILA | ROCKVILLE, MD | - | RBT | 09/25/2026 |
| PEACE AND BALANCE THERAPYORG | HARTFORD, CT | - | Clinical Social Worker | 03/16/2026 |
| PEACE IN STILL WATERS, LLCORG | EVANSVILLE, IN | - | Clinical Social Worker | 09/24/2026 |
| PEARSON, AARIANA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| PEARSON, BRITTANY | CORDOVA, TN | - | RBT | 09/21/2026 |
| PEARSON, MARSHA | ROME, GA | LMSW | Clinical Social Worker | 09/25/2026 |
| PEAVEY, KRISTIN | TORRANCE, CA | RBT | RBT | 09/21/2026 |
| PEAVEY, MEGAN | WINDSOR, VT | - | Mental Health Counselor | 09/22/2026 |
| PECK, ERICA | CONCORD, NH | MED | Counselor | 05/20/2009 |
| PECK, JENA | FARMINGTON HILLS, MI | - | RBT | 12/11/2025 |
| PECK, JOEL | ROCKY HILL, CT | - | Mental Health Counselor | 09/13/2018 |
| PECORA, PETER | BEND, OR | - | Case Manager/Care Coordinator | 09/23/2026 |
| PEDDER, FRANCIS | ENGLEWOOD, CO | - | Mental Health Counselor | 09/21/2026 |
| PEDIKIDZ OF PALM BEACH THERAPYORG | LAKE WORTH, FL | - | Clinic/Center | 08/17/2023 |
| PEEBLER, JENNIFER | SEATTLE, WA | - | Mental Health Counselor | 09/25/2026 |
| PEEVY, LYCIA | LITTLE ROCK, AR | - | RBT | 09/21/2026 |
| PEGGS, JORDYN | MEMPHIS, TN | - | RBT | 09/21/2026 |
| PEIRIS, REHANA | PALMDALE, CA | PSYD | Psychologist | 11/18/2013 |
| PELAYO, JUAN | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 07/05/2024 |
| PELCHER, MARK | GRAND RAPIDS, MI | - | Professional Counselor | 03/23/2007 |
| PELHAM, SIERRA | CELEBRATION, FL | LCSW | Clinical Social Worker | 12/17/2025 |
| PEMBERTON, AUSTIN | CHESAPEAKE, OH | - | Case Manager/Care Coordinator | 03/31/2023 |
| PEMBERTON, KELSEY | EUGENE, OR | - | Clinical Social Worker | 06/19/2013 |
| PEMBERTON, ROBERT | CHESAPEAKE, OH | - | Addiction (Substance Use Disorder) Counselor | 09/06/2023 |
| PEMBERTON, TAYLOR | LINCOLN, NE | - | Speech-Language Pathologist | 09/23/2026 |
| PENA, ANDY | MIAMI, FL | BCABA | RBT | 10/24/2023 |
| PENA, ERICK | BERRIEN SPRINGS, MI | - | Clinical Social Worker | 08/27/2021 |
| PENALOZA LUNA, AUGUST | MISHAWAKA, IN | - | RBT | 09/23/2026 |
| PENAREDONDO, BLANCHE | FORT WORTH, TX | LPC-ASSOCIATE | Mental Health Counselor | 11/03/2025 |
| PENCE, AUTUMN | TACOMA, WA | - | RBT | 09/22/2026 |
| PENDERGRASS, JANECE | OWASSO, OK | - | RBT | 08/18/2025 |
| PENKAL, JESSICA | MASON, OH | LISW | Clinical Social Worker | 09/19/2021 |
| PENN, JORDAN | FLOWER MOUND, TX | - | RBT | 09/25/2026 |
| PENNEY, ICE'SHAY | MILL CREEK, WA | - | Case Management Agency | 09/26/2026 |
| PENNY FOR YOUR THOUGHTS, LLCORG | SAINT ALBANS, WV | - | Clinical Social Worker | 09/21/2026 |
| PENSALFINI, KAYLEAH | MIDDLETOWN, RI | - | Mental Health Counselor | 08/07/2025 |
| PENUELAS, HELEN | TORRANCE, CA | - | RBT | 09/21/2026 |
| PEPLINSKI MARTINEZ, AVELINA | KEARNEY, NE | - | RBT | 09/24/2026 |
| PERALES, JAZMIN | DALTON, GA | - | RBT | 09/22/2026 |
| PERALTA, JUAN | PHILADELPHIA, PA | - | Mental Health Counselor | 12/26/2014 |
| PERDOMO, MARCELA | EL CENTRO, CA | BCBA, LMFT | BCBA | 03/31/2010 |
| PERDUE, CASSADY | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 01/22/2021 |
| PEREIRA DANGER, ADAN | JUPITER, FL | - | BCBA | 07/11/2023 |
| PEREIRA, MICHELLE | COEUR D ALENE, ID | - | RBT | 05/19/2026 |
| PEREZ ARES, LAZARO | HIALEAH, FL | - | RBT | 09/22/2026 |
| PEREZ CARDERO, IRMA | ORLANDO, FL | - | RBT | 08/10/2020 |
| PEREZ GONZALEZ, MIRLLEINS | MIAMI, FL | MS.- SLP. | Speech-Language Pathologist | 05/18/2011 |
| PEREZ HERNANDEZ, HELEN | MIAMI, FL | - | Assistant Behavior Analyst | 07/21/2021 |
| PEREZ-RAMOS, BRIANA | ONTARIO, CA | - | RBT | 09/21/2026 |
| PEREZ, ABRAHAM | POMONA, CA | - | RBT | 09/21/2026 |
| PEREZ, ADRIANNA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| PEREZ, ALEXANDRA | FT LAUDERDALE, FL | - | RBT | 09/25/2026 |
| PEREZ, ALYSSA | ALICE, TX | - | Counselor | 09/23/2026 |
| PEREZ, ELIZABET | MIAMI, FL | RBT | RBT | 09/22/2026 |
| PEREZ, HENRY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| PEREZ, IDANIS | CUTLER BAY, FL | - | RBT | 07/16/2019 |
| PEREZ, JENNIFER | NORTH BERGEN, NJ | - | BCBA | 09/22/2026 |
| PEREZ, JEZARAE | ALBUQUERQUE, NM | - | RBT | 09/21/2026 |
| PEREZ, JOSE | TRUJILLO ALTO, PR | M.A. | Psychologist | 01/09/2015 |
| PEREZ, SANDRA | VALENCIA, CA | - | RBT | 09/24/2026 |
| PEREZ, SAVANNAH | BOISE, ID | LCSW | Clinical Social Worker | 03/04/2021 |
| PEREZ, SELENA | BAYTOWN, TX | - | RBT | 09/22/2026 |
| PEREZ, SERGIO | TURLOCK, CA | - | Mental Health Counselor | 01/23/2023 |
| PEREZ, STAR | MIAMI, FL | - | RBT | 09/26/2026 |
| PEREZ, YULIANA | VALENCIA, CA | - | RBT | 09/25/2026 |
| PERKINS, MADELINE | NORTHGLENN, CO | CCC-SLP | Speech-Language Pathologist | 07/17/2025 |
| PERKINS, PAULA | PIKETON, OH | - | Case Manager/Care Coordinator | 05/09/2023 |
| PERNETT, CINDY | LEOMINSTER, MA | - | Counselor | 09/22/2026 |
| PERRELLO, VICTORIA | NEWARK, NY | SLP | Speech-Language Pathologist | 09/23/2026 |
| PERRIER, ERNEST | PHILADELPHIA, PA | - | BCBA | 09/21/2026 |
| PERRIN, CHARLOTTE | WALNUT CREEK, CA | - | RBT | 09/21/2026 |
| PERRIN, DANIELLE | ALVIN, TX | - | Mental Health Counselor | 09/23/2026 |
| PERRY, CARLIE | NEWBURGH, IN | - | RBT | 09/23/2026 |
| PERRY, JETTA | MORRILTON, AR | M.S. CCC-SLP | Speech-Language Pathologist | 09/24/2010 |
| PERRY, JORDYN | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| PERRY, JUANITA | HOUSTON, TX | LCSW | Clinical Social Worker | 02/18/2013 |
| PERRY, KATLYN | MOORESVILLE, NC | - | RBT | 09/21/2026 |
| PERRY, KIERA | PROVIDENCE, RI | - | RBT | 09/21/2026 |
| PERRY, MALLERY | SEATTLE, WA | - | Counselor | 09/21/2026 |
| PERRY, MELINDA | WARWICK, RI | LICSW | Clinical Social Worker | 03/07/2016 |
| PERSING, TAYLOR | BYRON, MN | - | RBT | 09/22/2026 |
| PERSON CENTERED CARE, LLCORG | GREENSBORO, NC | - | Community/Behavioral Health Agency | 09/21/2026 |
| PERSON, KENDRA | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| PERSPECTIVES BEHAVIOR CONSULTING LLCORG | DAYTON, OH | - | BCBA | 09/13/2023 |
| PETAS, ALEXIS | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 09/22/2026 |
| PETERS, BOBBI | FAIR OAKS, CA | - | Addiction (Substance Use Disorder) Counselor | 04/27/2023 |
| PETERS, ELIZABETH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| PETERS, KRISTINE | LAS VEGAS, NV | LPC, LCADC | Professional Counselor | 03/22/2019 |
| PETERS, THEODORE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| PETERSEN, AMANDA | MASSILLON, OH | CDCA | Addiction (Substance Use Disorder) Counselor | 09/10/2025 |
| PETERSEN, ANNIE | BRATTLEBORO, VT | LCMHC | Mental Health Counselor | 11/28/2023 |
| PETERSEN, MELISSA | SAINT HELENS, OR | - | Case Manager/Care Coordinator | 02/03/2025 |
| PETERSON, ADELYNN | ANACORTES, WA | - | Mental Health Counselor | 09/24/2026 |
| PETERSON, DESTINY | FARMINGTON HILLS, MI | LMT | Specialist | 01/15/2015 |
| PETERSON, JULIE | DWG, TX | LCSW | Clinical Social Worker | 03/09/2023 |
| PETERSON, KAIAH | EAU CLAIRE, WI | MS. CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| PETERSON, RYAN | SAINT PAUL, MN | LPCC | Mental Health Counselor | 02/06/2020 |
| PETRAK, LINDSEY | BRADENTON, FL | - | RBT | 09/22/2026 |
| PETRIE, JAMIE | EVANS, GA | - | RBT | 02/17/2025 |
| PETRISKY, SHANNON | CARBONDALE, PA | MS, LBS | BCBA | 09/23/2026 |
| PETROPOULOS, LARA | COLORADO SPRINGS, CO | - | Addiction (Substance Use Disorder) Counselor | 06/15/2026 |
| PETTIT, MEAGAN | GARDEN CITY, NY | LMHC | Mental Health Counselor | 01/09/2018 |
| PETTY, COLE | CHARLOTTE, NC | LCMHCA | Mental Health Counselor | 07/11/2025 |
| PETTY, HAYLEE | FAIRFIELD, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| PETTY, LAUREN | FARMINGTON HILLS, MI | - | Mental Health Counselor | 09/24/2026 |
| PFAU, DILLON | MIDDLEBURG HEIGHTS, OH | LISW | Clinical Social Worker | 06/15/2022 |
| PFEIFFER, DANA | PLEASANT PLAINS, IL | LCSW | Clinical Social Worker | 09/21/2026 |
| PFEIFFER, ELIZABETH | OAKLAND, CA | M.A. | Mental Health Counselor | 06/15/2020 |
| PHAM, JULIE | ALHAMBRA, CA | MD | Specialist | 04/06/2021 |
| PHAM, LASHAUNDA | CORAL GABLES, FL | - | RBT | 11/10/2023 |
| PHAM, LEE | SAN JOSE, CA | AMFT | Case Manager/Care Coordinator | 04/19/2022 |
| PHAN, KELLY | NEWARK, CA | - | RBT | 04/08/2024 |
| PHAN, TINA | SAN BRUNO, CA | - | BCBA | 05/29/2024 |
| PHAN, VAN | PORTLAND, OR | PH.D. | Psychologist | 08/03/2026 |
| PHELPS, MACKENZIE | MILWAUKIE, OR | LPC | Professional Counselor | 06/06/2024 |
| PHELPS, RUBY | HELOTES, TX | - | RBT | 09/23/2026 |
| PHEMISTER, MADALYNN | HERRIN, IL | - | RBT | 09/24/2026 |
| PHIFER, AVIS | TEXARKANA, AR | LCSW | Clinical Social Worker | 03/21/2014 |
| PHIFER, BRIAN | SAN RAFAEL, CA | - | Counselor | 01/21/2021 |
| PHILIP, SHARUN | KATY, TX | - | Professional Counselor | 09/25/2026 |
| PHILLIPS, BRIANA | PHILADELPHIA, PA | LPC | Professional Counselor | 07/12/2011 |
| PHILLIPS, FAITH | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| PHILLIPS, GREGORY | RAEFORD, NC | LCSWA, LCASA | Addiction (Substance Use Disorder) Counselor | 07/06/2017 |
| PHILLIPS, KATHERINE | WINTER PARK, FL | BCBA | BCBA | 09/25/2026 |
| PHILLIPS, KINSEY | CLIVE, IA | T-LMHC | Mental Health Counselor | 09/21/2026 |
| PHILLIPS, KIRSTEN | EVERETT, WA | - | Clinical Social Worker | 06/01/2017 |
| PHILLIPS, MCKENZIE | DECATUR, GA | - | Mental Health Counselor | 07/20/2022 |
| PHILLIPS, MIRANDAH | NEWARK, NJ | LCSW | Clinical Social Worker | 08/21/2023 |
| PHILLIPS, OPAL | EUGENE, OR | - | Counselor | 07/09/2026 |
| PHILLIPS, REBECCA | AUBURN, WA | MA | Mental Health Counselor | 11/10/2022 |
| PHILLIPS, REGINA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| PHILLIPS, TATYANA | SACRAMENTO, CA | - | RBT | 09/24/2026 |
| PHILLIPS, TENELLE | RATON, NM | LCSW | Clinical Social Worker | 05/17/2007 |
| PHIPPS, BRION | OAKLAND, CA | LCSW | Clinical Social Worker | 06/19/2008 |
| PHIPPS, CHARLENE | FAIRFIELD, CA | LCSW | Clinical Social Worker | 07/15/2010 |
| PHLEGM, RAYLIN | BROOKLYN, NY | - | RBT | 09/24/2026 |
| PHOENIX EARLY INTERVENTION LLCORG | ALBANY, NY | - | Case Management Agency | 01/16/2026 |
| PHOENIX RISING THERAPY SERVICES, PLLCORG | WINSTON SALEM, NC | - | Clinical Social Worker | 09/01/2023 |
| PHONGSAVATH, JOHNNY | FRESNO, CA | - | Counselor | 09/21/2026 |
| PHUNG, DIEP | VAN NUYS, CA | - | RBT | 09/25/2026 |
| PHUNG, PHUONG UYEN | SANTA ANA, CA | - | Day Training/Habilitation Specialist | 08/30/2023 |
| PICCHI, ANNABELLA | LISLE, IL | - | RBT | 09/21/2026 |
| PICHARDO, CALISTA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| PICKENS, SCOTT | MIDDLETOWN, OH | - | Professional Counselor | 01/13/2021 |
| PIEDMONT REGIONAL COMMUNITY SERVICES BOARDORG | MARTINSVILLE, VA | - | Community/Behavioral Health Agency | 01/13/2006 |
| PIERACCI, BRETT | KENNEWICK, WA | - | Clinical Social Worker | 08/14/2025 |
| PIERATT, KHIA | PORTLAND, OR | PSYD | Psychologist | 09/23/2026 |
| PIERCE, FRANCI | OAKLAND, CA | - | Addiction (Substance Use Disorder) Counselor | 05/20/2008 |
| PIERCE, NAOMI | ORANGE, CA | - | Psychologist | 11/02/2022 |
| PIERRE LOUIS, CHARLOTTE | WESTBURY, NY | - | Mental Health Counselor | 09/23/2026 |
| PIERRE, JASMINE | NEW ORLEANS, LA | - | RBT | 09/24/2026 |
| PIETRASZEWSKI, JOSHUA | ALBUQUERQUE, NM | - | RBT | 09/21/2026 |
| PIETROWSKI, SAMANTHA | KATY, TX | LPC - ASSOCIATE | Mental Health Counselor | 09/25/2026 |
| PIFER, STACY | FORT WAYNE, IN | - | RBT | 09/24/2026 |
| PIGGOTT, JADE | WESTPHALIA, MI | - | RBT | 08/03/2022 |
| PIGNATIELLO, KAITLIN | LEXINGTON PARK, MD | LCSW-C | Clinical Social Worker | 06/11/2025 |
| PILATOS, JOE WILBERTE | WINSTON SALEM, NC | LCMHC-A | Professional Counselor | 08/25/2025 |
| PILLAR ABA, LLCORG | PACIFIC PALISADES, CA | - | Counselor | 09/21/2026 |
| PINEDA, JOHNNY | BAYPORT, NY | - | RBT | 09/23/2026 |
| PINEDO, MADISON | FULLERTON, CA | - | BCBA | 10/15/2020 |
| PINKSTON, JOSEPH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| PINNACLE VIEW COUNSELING LLCORG | FORT COLLINS, CO | - | Professional Counselor | 09/21/2026 |
| PINNACLES OF LIFE COUNSELING AND COACHING, LLCORG | HISTORIC NEW CASTLE, DE | - | Clinical Social Worker | 09/09/2026 |
| PINNEY, JONATHAN | EL PASO, TX | MA, LPC, NCC | Mental Health Counselor | 08/12/2025 |
| PINNICK, KELLY | LAGRANGE, GA | M.A. | Mental Health Counselor | 11/02/2015 |
| PINTO, JONATHAN | JENKS, OK | - | Case Manager/Care Coordinator | 09/22/2026 |
| PINZON SANCHEZ, KAREN | SILVER SPRING, MD | - | RBT | 09/25/2026 |
| PIPER, EMMA | ROSEVILLE, CA | - | RBT | 09/22/2026 |
| PIRES, DELIZE | NORWELL, MA | - | Mental Health Counselor | 07/11/2025 |
| PISHORI, ALEFIYAH | MARTINEZ, CA | PHD | Psychologist | 05/30/2018 |
| PITMAN, JENNIFER | SAN ANTONIO, TX | LPC | Professional Counselor | 12/07/2006 |
| PITTMAN, LILLIAN | ELIZABETHTOWN, KY | BA | Counselor | 09/21/2026 |
| PITTMAN, MARGARET | DALLAS, TX | PT | Specialist | 07/17/2014 |
| PITTS, KATHERINE | SOUTHLAKE, TX | - | Mental Health Counselor | 09/24/2026 |
| PITTS, KEYLA | PROSPER, TX | - | RBT | 09/21/2026 |
| PIVARO, ANGELA | HOUSTON, TX | MA, CCC-SLP | Speech-Language Pathologist | 07/11/2018 |
| PIVOT POINT THERAPY PLLCORG | ROSCOE, IL | - | Clinical Social Worker | 09/26/2026 |
| PIZZATO, JULIANNA | SAN DIEGO, CA | - | Clinical Social Worker | 09/22/2026 |
| PLACE, LAURA | HIGH POINT, NC | - | Mental Health Counselor | 09/22/2026 |
| PLACKE, JENNIFER | WILLIAMSBURG, VA | - | Counselor | 09/22/2026 |
| PLAISANCE, TERESA | HASLET, TX | LPC | Counselor | 11/14/2008 |
| PLANTED THERAPY, LLCORG | PITTSBURGH, PA | - | Clinical Social Worker | 06/23/2026 |
| PLANTUS, VERONICA | SANDY SPRINGS, GA | MA, LAPC | Mental Health Counselor | 09/22/2026 |
| PLASCENCIA, SERINA | SANTA BARBARA, CA | - | BCBA | 09/25/2026 |
| PLAY PATH THERAPIES, PLLCORG | CHANDLER, AZ | - | BCBA | 03/19/2018 |
| PLAY THERAPY AND COUNSELING CENTER OF NORTH GEORGIA, LLCORG | BLAIRSVILLE, GA | - | Clinical Social Worker | 04/06/2009 |
| PLAYWISE ABA MO LLCORG | KANSAS CITY, MO | - | BCBA | 09/25/2026 |
| PLAZA-VELEZ, VASTI | PORTSMOUTH, VA | LCSW | Clinical Social Worker | 09/21/2026 |
| PLEASANT, TI'YANA | DURHAM, NC | - | RBT | 09/22/2026 |
| PLESCHA, JULIA | OVIEDO, FL | BCBA | BCBA | 09/18/2023 |
| PLUKAS, KATIE | QUEEN CREEK, AZ | LPC | Counselor | 01/06/2021 |
| PLUMMER, AMAYA | CHINO, CA | - | RBT | 09/22/2026 |
| PLUNKETT, JULIE | OLATHE, KS | LPC | Professional Counselor | 11/05/2006 |
| PM PEDIATRICS BH II, P.C.ORG | WAYNE, PA | - | Psychologist | 02/09/2022 |
| PMH CT PCORG | WINDSOR, CT | - | Clinical Social Worker | 08/14/2026 |
| PODELL, SHERI | WANTAGH, NY | - | Specialist | 09/22/2026 |
| PODRAZA, ALEXIS | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/25/2026 |
| PODSIADLIK, HANNAH | PLYMOUTH, MI | - | RBT | 09/24/2026 |
| POE, ALEXANDRIA | VACAVILLE, CA | BCBA | BCBA | 05/13/2021 |
| POFFENROTH, ALYSSA | SPOKANE, WA | LMHCA | Mental Health Counselor | 05/05/2021 |
| POILE, ANGELA | RAPID CITY, SD | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| POINDEXTER, MILDRED | COLUMBUS, OH | - | Psychologist | 09/22/2026 |
| POIS, MARIA | CRESTWOOD, KY | - | Clinical Social Worker | 09/23/2026 |
| POKALA, AKSHAR | WASHINGTON COURT HOUSE, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| POKHAREL, BIPANA | FAIRFAX, VA | LCSW | Clinical Social Worker | 09/15/2026 |
| POLANCO MERCADO, MIRLANDA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| POLASKI, KATHRYN | PITTSBURGH, PA | - | Mental Health Counselor | 07/25/2025 |
| POLEVOY, ARINA | ALGONQUIN, IL | PSY.D. | Psychologist | 12/12/2016 |
| POLICELLA, NATALIE | SEWELL, NJ | BCBA | BCBA | 09/24/2026 |
| POLIGNONI, JENNIFER | SPOKANE, WA | LMHCA | Clinical Social Worker | 01/14/2015 |
| POLISHUK ALLEYNE, ZAHAVA | BALDWIN, NY | BCBA | BCBA | 09/23/2026 |
| POLK, MONAE' | METAIRIE, LA | - | RBT | 09/24/2026 |
| POLLARD, DARLEANE | MAYFIELD HTS, OH | - | Case Manager/Care Coordinator | 12/13/2022 |
| POLLARD, ISABELLE | INDIANAPOLIS, IN | - | RBT | 09/25/2026 |
| POLSTON, ARIEL | MCCLELLAN, CA | LCSW | Clinical Social Worker | 07/22/2016 |
| POMEROY, JASON | PLANO, TX | MS, LPC-ASSOCIATE | Counselor | 09/26/2026 |
| POMPEY, CHANDRIA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| PONCE-RODRIGUEZ, ALEXIS | TORRANCE, CA | - | RBT | 09/21/2026 |
| PONCE, CARLOS | EDINBURG, TX | LPC | Professional Counselor | 09/16/2026 |
| PONCE, EMANUEL | MANSFIELD, TX | - | RBT | 09/21/2026 |
| PONCE, JENNIFER | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| PONTES DE LUCENA DOMINGUES, BEATRIZ | BRISTOL, CT | - | Counselor | 09/26/2026 |
| PONTIUS, KAITLYNN | COTTAGE GROVE, MN | LPCC | Mental Health Counselor | 05/01/2024 |
| POOL, TIMOTHY | HARKER HEIGHTS, TX | LCSW | Clinical Social Worker | 03/16/2026 |
| POPE-DUNLAP, DEONQUANIC | GRAND RAPIDS, MI | - | RBT | 07/13/2023 |
| POPE, REBECCA | UPLAND, CA | - | Speech-Language Pathologist | 09/21/2026 |
| POPE, REBEKAH | ST GEORGE, UT | RBT | RBT | 09/22/2026 |
| POPOVA, NATALIA | NEW YORK, NY | MHC-LP | Mental Health Counselor | 06/26/2025 |
| POPP, CASSIDY | CHICAGO, IL | - | Mental Health Counselor | 09/25/2026 |
| PORRAS, MARISSA | AUSTIN, TX | - | RBT | 09/25/2026 |
| PORRAS, XOCHILT | SAN BRUNO, CA | - | RBT | 09/22/2026 |
| PORTA, ANA | CHICAGO, IL | - | Professional Counselor | 09/25/2026 |
| PORTER, ASHLEE | MCALLEN, TX | - | RBT | 09/22/2026 |
| PORTER, BRANDI | PHOENIX, AZ | - | Speech-Language Pathologist | 09/08/2014 |
| PORTER, JESSICA | LAKE MARY, FL | LMHC | Mental Health Counselor | 11/30/2021 |
| PORTER, MICKAYLA | SALT LAKE CITY, UT | - | Clinical Social Worker | 09/10/2020 |
| PORTER, REONA | FOREST PARK, GA | BFS, PPN | Specialist | 09/21/2026 |
| PORTER, SARA | CINCINNATI, OH | - | Speech-Language Pathologist | 05/01/2015 |
| PORTILLO, JOSE | TULSA, OK | - | Case Manager/Care Coordinator | 04/24/2026 |
| PORTILLO, LESLIE | NEW BEDFORD, MA | - | RBT | 09/23/2026 |
| PORTILLO, SARA | TEMECULA, CA | - | RBT | 09/21/2026 |
| PORTO HARPER, CAMILA | ENTERPRISE, AL | ALC | Counselor | 09/25/2026 |
| POSADAS, CHLOE | ORLANDO, FL | - | Assistant Behavior Analyst | 09/22/2026 |
| POSEY, DESTINE | SNELLVILLE, GA | LPC | Professional Counselor | 09/02/2026 |
| POSITIVE BEHAVIOR SUPPORTSORG | STUART, FL | - | BCBA | 01/22/2009 |
| POSITIVE HORIZONS COUNSELING LLCORG | MALAD CITY, ID | - | Clinical Social Worker | 09/22/2026 |
| POSSER, ALEX | VINELAND, NJ | - | Clinical Social Worker | 09/24/2026 |
| POST, ABIGAIL | NEWNAN, GA | LPC | Professional Counselor | 02/09/2023 |
| POTELUNAS, ASHLEY | WALLINGFORD, CT | - | RBT | 09/25/2026 |
| POTOMAC CENTER INC.ORG | ROMNEY, WV | - | Case Management Agency | 09/22/2026 |
| POTRATZ, ASHLEY | CHICAGO, IL | - | BCBA | 10/28/2020 |
| POTTER, ABAGAIL | CONCORD, CA | - | RBT | 10/09/2025 |
| POTTER, CLARA | SHERMAN OAKS, CA | - | RBT | 09/21/2026 |
| POTTER, COLBY | MENIFEE, CA | BCBA | BCBA | 04/01/2025 |
| POTTER, HANNAH | KENSETT, AR | - | RBT | 09/25/2026 |
| POTTER, KEVIN | TEMPE, AZ | LASAC | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| POTTS, BELLA | SAINT GEORGE, UT | - | RBT | 09/21/2026 |
| POTTS, SAMANTHA | DALLAS, TX | - | RBT | 09/22/2026 |
| POTTS, SUZANNE | AUBURN, MI | - | RBT | 09/21/2026 |
| POUCHER, THERESA | NEWBURG, MO | - | RBT | 09/25/2026 |
| POUND, DEBORAH | JACKSONVILLE, FL | - | Mental Health Counselor | 09/21/2026 |
| POWELL, ALAN | WOOSTER, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| POWELL, ALEXANDER | SALEM, OR | - | Mental Health Counselor | 09/21/2026 |
| POWELL, ASHLEY | BOSTON, MA | L.I.C.S.W. | Clinical Social Worker | 06/18/2013 |
| POWELL, AVERY | CHICAGO, IL | LPC | Mental Health Counselor | 09/22/2026 |
| POWELL, JODI | NASHVILLE, TN | LCSW | Clinical Social Worker | 07/30/2021 |
| POWELL, KRISTA | CANONSBURG, PA | - | Mental Health Counselor | 09/09/2024 |
| POWELL, SHAREE | BRONX, NY | - | Clinical Social Worker | 09/23/2026 |
| POWERS, MEGAN | JONESBORO, AR | - | Speech-Language Pathologist | 01/05/2021 |
| POWERS, RAFAEL | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| POZDNYAKOVA, ANNA | BROOKLYN, NY | - | Case Manager/Care Coordinator | 09/25/2026 |
| POZO DAGER, ISABEL | MIAMI, FL | - | RBT | 11/17/2020 |
| PRADO GONZALEZ, SHANAYA | HOMESTEAD, FL | - | RBT | 09/26/2026 |
| PRADO, ALEXANDRA | LITTLETON, CO | - | Mental Health Counselor | 07/21/2023 |
| PRADO, CLARISSE | ELK GROVE, CA | - | RBT | 09/22/2026 |
| PRADO, GLENDY | FORT MYERS, FL | - | BCBA | 06/11/2024 |
| PRADO, XZAVIOR | RIVERBANK, CA | - | RBT | 09/21/2026 |
| PRAHL, LILY | LONG BEACH, CA | HIGH SCHOOL DIPLOMA | RBT | 09/24/2026 |
| PRAHL, MEGAN | DALLAS, TX | LCSW | Clinical Social Worker | 10/13/2025 |
| PRASAD, FATIMA | MODESTO, CA | - | Clinical Social Worker | 03/29/2024 |
| PRASAD, SHEETAL | SAN RAMON, CA | - | RBT | 09/23/2026 |
| PRATER, STARLASHA | KOKOMO, IN | - | RBT | 09/22/2026 |
| PRATT, PRECIOUS | BELTSVILLE, MD | - | RBT | 09/21/2026 |
| PRATT, SANDRA | MCALLEN, TX | - | RBT | 09/25/2026 |
| PRATT, THOMI | SNELLVILLE, GA | LPC | Mental Health Counselor | 01/13/2016 |
| PRAVEEN NAIR, KAMYA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| PRAY-HERORG | MAPLE HEIGHTS, OH | - | Case Management Agency | 09/25/2026 |
| PRECIADO, ABIGAIL | SAINT MARYS, GA | - | RBT | 08/18/2023 |
| PRECIOUS BEGINNINGS RESOURCE CENTER LLCORG | AURORA, CO | - | Case Management Agency | 09/22/2026 |
| PRECISION TRAUMA THERAPY CENTER LLCORG | STREETSBORO, OH | - | Mental Health Counselor | 02/17/2026 |
| PREDMORE, HANNAH | BIRMINGHAM, AL | - | RBT | 09/21/2026 |
| PREJEAN, DERRICK | DECATUR, GA | RBT | RBT | 05/12/2021 |
| PREMIER WELLNESS CENTER LLCORG | MEDIA, PA | - | Mental Health Counselor | 04/15/2025 |
| PREMO, SHURENE | CARDIFF, CA | LCSW | Mental Health Counselor | 10/05/2022 |
| PRENDERGAST, JERED | MAUMEE, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| PRENDES, ISABELLA | MIRAMAR, FL | - | RBT | 09/21/2026 |
| PREPETIT, MELANIE | MENTOR, OH | LISW-SUPV | Clinical Social Worker | 09/16/2010 |
| PRESSEY, JENNIFER | COLORADO SPRINGS, CO | - | Professional Counselor | 02/12/2026 |
| PRESSLEY-TROCHE, SHAYNA | BRONX, NY | - | Specialist | 09/21/2026 |
| PRESTIPINO, ASHLEY | BENNINGTON, VT | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| PRESTON, ALISHA | TERRYTOWN, LA | RPSS | Case Manager/Care Coordinator | 09/23/2026 |
| PRESTON, JULIA | NORTH SUTTON, NH | M.S., CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| PRESTON, KARINKA | RIVERSIDE, CA | - | Counselor | 09/19/2022 |
| PRESTON, MACKENZIE | IRVING, TX | CF-SLP | Speech-Language Pathologist | 09/21/2023 |
| PRICE, CHAZ | VANCOUVER, WA | SUDP/T | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| PRICE, CIARA | GARDEN CITY, MI | - | RBT | 09/25/2026 |
| PRICE, COLE | CHICAGO, IL | - | Professional Counselor | 09/22/2026 |
| PRICE, EMILY | MANKATO, MN | - | Speech-Language Pathologist | 09/22/2026 |
| PRICE, ETHAN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| PRICE, FALON | KALAMAZOO, MI | LPC | Counselor | 08/08/2018 |
| PRICE, OLIVIA | TROY, NY | - | Psychologist | 10/22/2021 |
| PRIDDY, DAPHNE | SAN JACINTO, CA | LMFT, LPCC | Mental Health Counselor | 10/09/2019 |
| PRIDE HEALING AND RECOVERY SERVICES, LLCORG | CARENCRO, LA | - | Professional Counselor | 04/30/2026 |
| PRIDGEN, DOMINQUE | NEW YORK, NY | LMSW | Clinical Social Worker | 09/23/2026 |
| PRIEBE, KALA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| PRIETO, MAIA | SAN FRANCISCO, CA | - | BCBA | 05/14/2025 |
| PRIETO, RAYMOND | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| PRINCE, ATTAIRA | TULSA, OK | - | Counselor | 09/22/2026 |
| PRINCE, OLIVIA | ALLENTOWN, PA | - | RBT | 08/24/2026 |
| PRISM THERAPY, A LICENSED CLINICAL SOCIAL WORKER P.C.ORG | LOS ANGELES, CA | - | Clinical Social Worker | 06/02/2026 |
| PRITCHARD, KHALEED | NORWALK, CT | - | RBT | 09/22/2026 |
| PRITCHARD, MIRANDA | LIVONIA, MI | - | RBT | 09/20/2024 |
| PRITCHARD, THERESA | LEBANON, OH | LISW-S | Clinical Social Worker | 08/04/2009 |
| PROFFITT, BRENDON | ALBUQUERQUE, NM | - | RBT | 09/24/2026 |
| PROGRAM FOR THE ADVANCEMENT OF TRAUMA HEALINGORG | EVERETT, WA | - | Psychologist | 01/24/2026 |
| PROJECT OPTIMISMORG | SIGNAL HILL, CA | - | Case Management Agency | 09/23/2026 |
| PROKOP, NATALIA | CLEVELAND, OH | LISW | Clinical Social Worker | 10/07/2021 |
| PROKOPOWICZ, KATIE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| PROLO, MARY | SANTA CLARA, CA | - | Mental Health Counselor | 03/29/2007 |
| PROMINENT THERAPY SERVICES, LLCORG | ELLENWOOD, GA | - | Speech-Language Pathologist | 05/08/2023 |
| PROMISE HAVEN ADULT CARE LLCORG | GREENSBORO, NC | - | Community/Behavioral Health Agency | 09/22/2026 |
| PROMISE HEALTH SERVICES LLCORG | WALDORF, MD | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| PROMSEEMAI, ALNA MAE | PUNTA GORDA, FL | LCSW | Clinical Social Worker | 09/14/2026 |
| PROPST, SYDNEY | LENOIR, NC | - | Mental Health Counselor | 09/23/2026 |
| PROSPECT NYC COUNSELING LCSW PLLCORG | NEW YORK, NY | - | Clinical Social Worker | 05/27/2024 |
| PROUD MOMENTS ABAORG | ALBUQUERQUE, NM | - | Community/Behavioral Health Agency | 09/22/2026 |
| PROVOST BODY & MIND, PLLCORG | HENDERSON, NV | - | Mental Health Counselor | 09/21/2026 |
| PRUDHOMME, CRYSTAL | CALHOUN, LA | - | Addiction (Substance Use Disorder) Counselor | 07/30/2026 |
| PRUE, MADELAINE | NASHVILLE, TN | - | Professional Counselor | 08/26/2022 |
| PRUNESCU, ANDREW | LAWRENCEVILLE, GA | - | RBT | 09/23/2026 |
| PRUSIECKI, JORDAN | BUFFALO, NY | - | Counselor | 09/22/2026 |
| PSYCHOLOGICAL ASSESSMENT SPECIALISTS OF NORTH ATLANTA, LLC.ORG | MARIETTA, GA | - | Psychologist | 09/22/2026 |
| PUCK, ADDISON | GRAND RAPIDS, MI | LLMSW | Clinical Social Worker | 09/23/2026 |
| PUCKETT, ALANI | NEW BERN, NC | - | RBT | 09/22/2026 |
| PUDDY, SARAH | LEDYARD, CT | LPC | Mental Health Counselor | 09/26/2026 |
| PUENTE, MARLON | MIAMI, FL | RBT | RBT | 09/23/2026 |
| PUENTES, DANIELLE | SAN ANTONIO, TX | BCBA | BCBA | 06/12/2025 |
| PUEYO, ENID | GUAYNABO, PR | - | Mental Health Counselor | 09/24/2026 |
| PUGLIESE, MICAELA | DESERT HOT SPRINGS, CA | - | RBT | 09/25/2026 |
| PULIDO-HERNANDEZ, ASHANTIE | SALINAS, CA | - | RBT | 09/21/2026 |
| PULLAKANDAM, ANUJ | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| PULLEY, JADA | VENTURA, CA | - | RBT | 09/26/2026 |
| PULMONARY AND SLEEP MEDICINE P CORG | DALTON, GA | - | Specialist | 07/02/2006 |
| PUNGRATZ, TODD | PITTSBURGH, PA | LCSW, CAADC | Clinical Social Worker | 10/24/2011 |
| PURCELL, NATHAN | GRAND HAVEN, MI | LMSW | Clinical Social Worker | 09/25/2026 |
| PURDY, ROBIN | CLEVELAND, OH | - | Mental Health Counselor | 09/22/2026 |
| PURNELL-JOE, JOHNATHAN | PHILLIPSBURG, NJ | - | RBT | 09/21/2026 |
| PYLANT, OCEANIA | DOTHAN, AL | - | RBT | 09/21/2026 |
| QAYYUM, UMAIMA | SACRAMENTO, CA | - | RBT | 09/25/2026 |
| QIU, YONGYING | NEW YORK, NY | - | Mental Health Counselor | 05/05/2025 |
| QUACKENBUSH, SAMANTHA | CHEVY CHASE, MD | LGPC | Professional Counselor | 02/25/2020 |
| QUAD CITIES INTEGRATIVE WELLNESSORG | DAVENPORT, IA | - | Clinical Social Worker | 02/06/2026 |
| QUALITY CARE PREFERENCE LLCORG | MILWAUKEE, WI | - | Addiction (Substance Use Disorder) Counselor | 05/30/2022 |
| QUARTERMUS, KELLIE | PHILADELPHIA, PA | LCSW | Clinical Social Worker | 09/09/2016 |
| QUEDADO, CARLO | SEATTLE, WA | LICSW | Mental Health Counselor | 03/20/2014 |
| QUEEN CITY EMPOWERMENT NETWORK LLCORG | HARRISBURG, NC | - | Community/Behavioral Health Agency | 08/29/2024 |
| QUEEN, SAMANTHA | SAGINAW, MI | - | RBT | 09/23/2026 |
| QUESENBERRY, LAUREN | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| QUEST PROVIDER SERVICES LLCORG | CHARLOTTE, NC | - | BCBA | 05/29/2008 |
| QUEZADA, ESMERALDA | ONTARIO, CA | - | Clinical Social Worker | 05/29/2023 |
| QUEZADA, MELISSA | FREMONT, CA | - | Counselor | 09/21/2026 |
| QUEZADA, VERONICA | PRESCOTT, AZ | LCSW | Clinical Social Worker | 10/08/2019 |
| QUIET MIND PSYCHOTHERAPY, PLLCORG | PITTSBORO, NC | - | Psychologist | 09/22/2026 |
| QUIJADA, KAELA | WALNUT CREEK, CA | - | RBT | 11/09/2018 |
| QUIJADA, MAURICIO | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 08/03/2026 |
| QUIMSON BEHAVIORAL HEALTHORG | PORTLAND, OR | - | Addiction (Substance Use Disorder) Counselor | 03/24/2022 |
| QUINN MCFALL THERAPY PLLCORG | CHAPEL HILL, NC | - | Mental Health Counselor | 09/21/2026 |
| QUINN, GINA | MYRTLE BEACH, SC | - | Mental Health Counselor | 05/10/2012 |
| QUINONES, DESTINY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| QUINTANA, JOHNIECE | MODESTO, CA | MSW | Professional Counselor | 05/30/2017 |
| QUINTERO, HENNESSY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| QUINTO, KRYSTAL | IRVINE, CA | - | RBT | 09/21/2026 |
| QUIROZ, ALONDRA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| QUIROZ, FERNANDA | GARDEN GROVE, CA | - | RBT | 03/11/2026 |
| QUIST, KATHERINE | MURRAY, UT | - | Case Manager/Care Coordinator | 09/25/2026 |
| RAAD, JENNA | COON RAPIDS, MN | - | BCBA | 05/11/2021 |
| RABAKALI SALVADORI, TSHIFHIWA | COLUMBIA, MD | - | RBT | 09/21/2026 |
| RABU, OBSITU | BLAINE, MN | - | RBT | 09/21/2026 |
| RACAN, MICHAEL | SANTA BARBARA, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| RACELIS, ALYSSA | TORRANCE, CA | - | RBT | 09/21/2026 |
| RACHEL DEBOER COUNSELING PLLCORG | SEATTLE, WA | - | Mental Health Counselor | 09/22/2026 |
| RACHEL KLING, PSYCHOTHERAPIST LLCORG | SOUTH BURLINGTON, VT | - | Psychologist | 09/22/2026 |
| RACINE, SAMANTHA | NEW BEDFORD, MA | - | Case Manager/Care Coordinator | 09/25/2026 |
| RADDING, TAYLOR | WATSONVILLE, CA | - | RBT | 09/22/2026 |
| RADMAN, ELIZABETH | FORT COLLINS, CO | - | Mental Health Counselor | 09/22/2026 |
| RADZINSKI, ALEXANDRA | KENAI, AK | - | Mental Health Counselor | 06/18/2026 |
| RAEL, NANCY | ALBUQUERQUE, NM | - | Community/Behavioral Health Agency | 08/24/2022 |
| RAFTER, KELLY | BRICK, NJ | LPC | Professional Counselor | 04/03/2020 |
| RAGE, AMIN | FARIBAULT, MN | - | RBT | 09/21/2026 |
| RAGHAVAN, GREESHMA | LOS ANGELES, CA | M.S., CCC-SLP | Speech-Language Pathologist | 09/24/2026 |
| RAGUINDIN, JADA | FREMONT, CA | - | RBT | 09/24/2026 |
| RAHM, JORDAN | CHICAGO, IL | LPC | Professional Counselor | 09/21/2026 |
| RAHMAN, JANNAH | SOUTHFIELD, MI | - | RBT | 09/25/2026 |
| RAI, RAMA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| RAINGE, DANA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| RAITT, SHYANNA | FREMONT, NE | - | Day Training/Habilitation Specialist | 09/21/2026 |
| RAJA, NOREEN | BRICK, NJ | - | Psychologist | 09/12/2025 |
| RAKE, SAMUEL | LANCASTER, OH | LPCC | Mental Health Counselor | 07/27/2009 |
| RAMA, SHELBY | SANTA FE, NM | N/A | RBT | 09/25/2026 |
| RAMACHANDRAN, ERIN | FULLERTON, CA | PSYD | Psychologist | 09/08/2026 |
| RAMIREZ ESCAMILLA, CHRIS | OXNARD, CA | BA | RBT | 05/06/2025 |
| RAMIREZ FLORES, AILED | CONCORD, CA | - | RBT | 09/21/2026 |
| RAMIREZ GARCIA, LESLIE | CONCORD, CA | - | RBT | 09/22/2026 |
| RAMIREZ VELAZQUEZ, JAYLENE | TACOMA, WA | - | Clinical Social Worker | 09/23/2026 |
| RAMIREZ, ANA | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| RAMIREZ, CHRISTIAN | SALINAS, CA | - | RBT | 09/21/2026 |
| RAMIREZ, CRISTEL | FRESNO, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| RAMIREZ, CRISTINA | PHOENIX, AZ | LCSW | Clinical Social Worker | 09/21/2026 |
| RAMIREZ, DANIELLE | CHICAGO, IL | PSYD | Psychologist | 09/09/2025 |
| RAMIREZ, ERICKA | SOUTH BEND, IN | - | BCBA | 09/21/2023 |
| RAMIREZ, GEORGIANA | EDMOND, OK | - | RBT | 09/21/2026 |
| RAMIREZ, GISELLE | CAMPO, CA | RADT | Addiction (Substance Use Disorder) Counselor | 02/16/2023 |
| RAMIREZ, JADA | LAWRENCEVILLE, GA | - | RBT | 09/23/2026 |
| RAMIREZ, JOHN | WEST OLIVE, MI | LCSW | Clinical Social Worker | 01/07/2019 |
| RAMIREZ, KATELYNN | THORNTON, CO | BS | Counselor | 09/24/2026 |
| RAMIREZ, LESLEY | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| RAMIREZ, LINDSAY | SAINT PAUL, MN | LICSW | Clinical Social Worker | 12/21/2015 |
| RAMIREZ, MARIA | SANTA MARIA, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| RAMIREZ, MAYERLI | TORRANCE, CA | - | RBT | 09/21/2026 |
| RAMIREZ, NATALIE | SHERMAN OAKS, CA | - | RBT | 09/26/2026 |
| RAMIREZ, REANNA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| RAMIREZ, ROSARIO | ANAHEIM, CA | - | Addiction (Substance Use Disorder) Counselor | 09/03/2026 |
| RAMIREZ, RUBI | MARCO ISLAND, FL | - | RBT | 09/22/2026 |
| RAMIREZ, SIERRA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| RAMIREZ, SOFIA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| RAMIREZ, SOPHIA | SAN ANTONIO, TX | - | Professional Counselor | 09/22/2026 |
| RAMIREZ, STEFANIE | TACOMA, WA | MA | RBT | 07/15/2021 |
| RAMJI, SHRUTHI | LEANDER, TX | - | RBT | 09/22/2026 |
| RAMKISSOON, ALENA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| RAMOS PEREZ, NAYELI | WHITESTONE, NY | - | RBT | 09/21/2026 |
| RAMOS PEREZ, SHALIM SHAEL | NEW PORT RICHEY, FL | LMHC | Mental Health Counselor | 12/20/2012 |
| RAMOS, ALYSSIA | LINCOLN, RI | LICSW, BCBA | Clinical Social Worker | 06/24/2010 |
| RAMOS, BRITTANY | WESTFIELD, IN | - | RBT | 09/22/2026 |
| RAMOS, FAITH | ST GEORGE, UT | - | RBT | 04/04/2025 |
| RAMOS, JADE | ONTARIO, CA | - | RBT | 09/22/2026 |
| RAMOS, JOHNNY | DORAL, FL | - | RBT | 09/23/2026 |
| RAMOS, MELANIE | CLINTON TOWNSHIP, MI | - | BCBA | 08/24/2021 |
| RAMOS, MOLLY | WINDERMERE, FL | - | RBT | 09/26/2026 |
| RAMOS, NATALIE | FRESNO, CA | - | Day Training/Habilitation Specialist | 08/24/2026 |
| RAMOS, NIXZALIZ | HOLYOKE, MA | - | Mental Health Counselor | 09/21/2026 |
| RAMOS, STEPHANIE | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| RAMOS, VINCENT | NEW YORK, NY | MA, LPC | Professional Counselor | 01/09/2019 |
| RAMOS, VITORINO | NORWELL, MA | - | RBT | 08/17/2024 |
| RAMOS, YAILIN | MIAMI, FL | - | RBT | 06/20/2024 |
| RAMOZ, MACAYLA | BATON ROUGE, LA | LBA | BCBA | 09/24/2026 |
| RAMPERSAUD, JAILYN | BRONX, NY | - | Case Management Agency | 09/22/2026 |
| RAMSAY, JENNA | NORFOLK, VA | BCBA | BCBA | 01/06/2026 |
| RAMSEY, LECHAI | CONCORD, CA | - | RBT | 09/24/2026 |
| RAMSEY, MITTA | CORONA, CA | - | RBT | 09/21/2026 |
| RAMUSEVIC, BUKURIJE | MANHASSET, NY | LMHC, LPC | Mental Health Counselor | 09/04/2020 |
| RANALLO, OLIVIA | MORGANTOWN, WV | - | Mental Health Counselor | 04/02/2026 |
| RANDALL, JESSECA | GAMBRILLS, MD | LCSW-C | Clinical Social Worker | 01/06/2022 |
| RANDALL, KAYLA | HERNDON, VA | - | Assistant Behavior Analyst | 07/12/2022 |
| RANDALL, SHELBY | PORTAGE, MI | - | RBT | 09/23/2026 |
| RANDALL, TRISTAN | BATON ROUGE, LA | CIT | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| RANDLE, TANYA | EAST HARTFORD, CT | - | Professional Counselor | 09/23/2026 |
| RANDLES, ELANNA | ONTARIO, CA | - | Assistant Behavior Analyst | 02/04/2021 |
| RANDOLPH, MICHAEL | ROSEBURG, OR | - | Clinical Social Worker | 05/08/2025 |
| RANGEL, VALERIA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| RANSOM, BRIANA | PROSPER, TX | - | RBT | 09/21/2026 |
| RANSOM, IZABELLE | BELOIT, WI | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| RAPE, ANTHONY | FARMINGTON HILLS, MI | BT | RBT | 09/24/2026 |
| RAPOZA, MICHAELA | BOYLSTON, MA | LCSW | Clinical Social Worker | 08/16/2021 |
| RAPP, JOHN | CLAYTON, MO | MSW, LCSW | Clinical Social Worker | 04/17/2011 |
| RAPP, MELANIE | FORT COLLINS, CO | - | Mental Health Counselor | 09/24/2026 |
| RASH, LAUREN | WEST BLOOMFIELD, MI | - | BCBA | 01/18/2023 |
| RASMUSSEN, LEIF | UNIVERSITY PLACE, WA | - | RBT | 09/24/2026 |
| RASMUSSEN, LILLY | BROOKLYN, NY | - | RBT | 09/23/2026 |
| RASNICK, ELIZABETH | PANAMA CITY, FL | M.S. CF-SLP | Speech-Language Pathologist | 08/25/2007 |
| RATH, MACKENZIE | RICHFIELD, MN | - | RBT | 09/21/2026 |
| RATH, MARY | CHEEKTOWAGA, NY | LCSW | Clinical Social Worker | 09/26/2026 |
| RATHBONE, LAUREN | CHAPEL HILL, NC | - | RBT | 09/22/2026 |
| RATHFON, EMILY | ANDERSON, SC | - | RBT | 09/24/2026 |
| RATHKE, MEGAN | COLLEGEVILLE, PA | - | RBT | 06/19/2023 |
| RATLIFF, HEATHER | BROWNSBURG, IN | RBT | RBT | 09/25/2026 |
| RATLIFF, MELISSA | JAYESS, MS | - | Counselor | 09/21/2026 |
| RATLIFF, PATRICIA | PRESTONSBURG, KY | - | Case Manager/Care Coordinator | 09/24/2026 |
| RATLIFF, SIMONNE | FAYETTEVILLE, NC | - | RBT | 09/22/2026 |
| RAULINS, KAILANI | ROSEVILLE, CA | - | RBT | 09/25/2026 |
| RAY, ALLISON | CAMILLUS, NY | MS, LMHC-D, NCC, ACS | Mental Health Counselor | 08/16/2022 |
| RAY, DIAMOND | VIENNA, VA | RBT-25-500763 | RBT | 12/22/2025 |
| RAY, EBONY | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| RAY, KAEYA | MILWAUKEE, WI | - | RBT | 07/10/2025 |
| RAY, REBECCA | LEAWOOD, KS | LSCSW | Clinical Social Worker | 12/31/2013 |
| RAY, THERESA | SILVERDALE, WA | - | RBT | 09/23/2026 |
| RAYFORD, BRITTNEY | VICTORVILLE, CA | - | RBT | 09/21/2026 |
| RAYFORD, SHAWNICE | COVINA, CA | - | RBT | 09/23/2026 |
| RAYGAN, LEILA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| RAYMOND FOLMAR M.D., INC.ORG | ANAHEIM, CA | - | Specialist | 04/09/2008 |
| RAYMOND, BLANCA | SCOTTSDALE, AZ | LCSW | Clinical Social Worker | 06/03/2025 |
| RAYMOND, KATHERINE | CEDAR PARK, TX | APRN | Professional Counselor | 09/25/2008 |
| RAYMOND, KYLA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| RAYMOND, LANIKA | HOUSTON, TX | - | RBT | 09/25/2026 |
| RAYO, JONATHAN | CONCORD, CA | - | RBT | 09/22/2026 |
| RE-SOURCE THERAPY PLLCORG | HOUSTON, TX | - | Professional Counselor | 09/23/2026 |
| REA, BROOKE | OVID, MI | - | Clinical Social Worker | 09/25/2026 |
| REA, LAUREN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| REACH, KATARINA | NORTH RICHLAND HILLS, TX | LPC-ASSOCIATE | Counselor | 11/05/2024 |
| READOUX, ERIKA | BREAUX BRIDGE, LA | - | Case Manager/Care Coordinator | 09/21/2026 |
| READY SET GO ABA LLCORG | VICTORVILLE, CA | - | BCBA | 09/24/2026 |
| READY, AYSLINN | CONCORD, NH | - | Specialist | 09/15/2026 |
| REAGAN, SARA | KENNETT, MO | - | Case Manager/Care Coordinator | 09/23/2026 |
| REAGH, STEPHINE | AYDEN, NC | LPC | Professional Counselor | 04/08/2013 |
| REAL LIFE COUNSELING, PLLCORG | CRYSTAL LAKE, IL | - | Professional Counselor | 05/20/2021 |
| REAL MENTAL HEALTH THERAPYORG | SAINT CHARLES, MI | - | Counselor | 04/13/2026 |
| REAL, DEVEN | WINDSOR, CT | - | RBT | 09/24/2026 |
| REAL, EVELETTE | GARDEN GROVE, CA | - | RBT | 09/26/2026 |
| REAPER, LAURA | NASHVILLE, TN | CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| REARDON, SYBELLA | EL PASO, TX | LCSW | Clinical Social Worker | 06/29/2010 |
| REBECCA PHILLIPS COUNSELING LLCORG | AUBURN, WA | - | Mental Health Counselor | 09/25/2026 |
| REBELLIOUS RECOVERY LLCORG | PADUCAH, KY | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| REBOLLAR, JENNIFER | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| RECIPROCAL GROWTH THERAPY PLLCORG | CHICAGO, IL | - | Counselor | 12/04/2025 |
| RECONCILIATION THERAPY AND CONSULTING, LLCORG | FLINTSTONE, GA | - | Professional Counselor | 09/23/2026 |
| RECOVERED HUMANS WELLNESS, LLCORG | LOVELAND, CO | - | Addiction (Substance Use Disorder) Counselor | 09/02/2026 |
| RECTOR, MAKAYLA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| RECTOR, STEFFANI | MARQUETTE, MI | - | Speech-Language Pathologist | 09/23/2026 |
| REDEEMED MIND COUNSELING GROUP PLLCORG | LONGVIEW, TX | - | Mental Health Counselor | 09/23/2026 |
| REDEEMED WAY CHRISTIAN COUNSELING, LLCORG | LEXINGTON, VA | - | Mental Health Counselor | 05/04/2022 |
| REDFERN, JESSICA | JACKSON, TN | RBT | BCBA | 12/19/2024 |
| REDITT, ANGELICA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| REDSTONE BEHAVIORAL HEALTH LLCORG | LEXINGTON, KY | - | Community/Behavioral Health Agency | 08/25/2026 |
| REED, AMANDA | FRESNO, CA | LMFT | Case Manager/Care Coordinator | 04/17/2008 |
| REED, CHELSEA | JACKSON, MI | LLPC | Mental Health Counselor | 01/06/2026 |
| REED, CONNOR | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| REED, DENISE | BATH, ME | LCPC | Professional Counselor | 05/01/2018 |
| REED, GRIFFIN | PORTLAND, ME | MD | Specialist | 06/22/2020 |
| REED, KIANA | QUINCY, IL | LCPC | Professional Counselor | 03/04/2025 |
| REED, KRISTA | SAN DIEGO, CA | MS, SLP | Speech-Language Pathologist | 09/22/2026 |
| REED, SHERRI | DALLAS, TX | M.ED, LPC | Professional Counselor | 09/24/2026 |
| REED, TRAVIS | ZANESVILLE, OH | - | Case Manager/Care Coordinator | 06/06/2018 |
| REED, TREVOR | PORTLAND, OR | - | Mental Health Counselor | 09/23/2026 |
| REELS, SHANNA | MYSTIC, CT | LCSW | Clinical Social Worker | 04/29/2016 |
| REES, AMY | PINEHURST, NC | BCBA | BCBA | 09/10/2019 |
| REESE, AURORA | ALTOONA, IA | MA, BCBA, LBA | BCBA | 09/23/2026 |
| REESE, JADA | KANSAS CITY, MO | PLPC | Professional Counselor | 04/26/2018 |
| REFUGE COUNSELING, LLCORG | ASHLAND, OH | - | Mental Health Counselor | 10/03/2020 |
| REGENERATION SCHOOLS - AVONDALEORG | CINCINNATI, OH | - | Speech-Language Pathologist | 09/23/2026 |
| REGENERATION SCHOOLS - BOND HILLORG | CINCINNATI, OH | - | Speech-Language Pathologist | 09/23/2026 |
| REGENERATION SCHOOLS - REGENERATION MIDDLE SCHOOLORG | CINCINNATI, OH | - | Speech-Language Pathologist | 09/23/2026 |
| REGETS WORKMAN, MARY | UPPER ST CLAIR, PA | - | Professional Counselor | 12/07/2016 |
| REGIMBAL, PATRICK | GREAT FALLS, MT | LAC | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| REGO, KRISTIN | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| REGUS, DIANA | FRAMINGHAM, MA | - | Mental Health Counselor | 09/21/2026 |
| REHOBOTH SUPPORTIVE SERVICES LLCORG | PHILADELPHIA, PA | - | Case Management Agency | 09/26/2026 |
| REICH, RIVKY | MONSEY, NY | - | Specialist | 06/11/2012 |
| REID, JAMIE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| REID, JUMOI-ANTONIO | BEVERLY HILLS, MI | LPC, LLMFT, MA, NCC | Professional Counselor | 10/31/2022 |
| REID, MALIYAH | SACRAMENTO, CA | - | RBT | 09/24/2026 |
| REID, ZACHARY | CLIVE, IA | CF SLP | Speech-Language Pathologist | 09/25/2026 |
| REIHL, ERICKA | MILL CREEK, WA | - | Professional Counselor | 05/05/2023 |
| REILLY, DYLAN | MIAMI BEACH, FL | - | Mental Health Counselor | 09/21/2026 |
| REIN, JENNIFER | CHESTERFIELD, MI | - | Mental Health Counselor | 09/11/2023 |
| REINHOLD CARE GROUP LLCORG | NEWARK, NJ | - | Community/Behavioral Health Agency | 08/19/2026 |
| REIS, TIA | MELBOURNE, FL | - | RBT | 09/06/2023 |
| REISMAN, ELAINE | LAKEWOOD, CO | - | Case Manager/Care Coordinator | 09/22/2026 |
| REISS, SADI | AUSTIN, TX | - | RBT | 09/21/2026 |
| REITZ, SAVANNAH | JOHNSTOWN, PA | MA | Mental Health Counselor | 09/22/2026 |
| REJI, KEERA | OLATHE, KS | - | RBT | 09/22/2026 |
| RELLA COUNSELING LLCORG | BOONTON, NJ | - | Clinical Social Worker | 09/01/2026 |
| RELLA, KATHERINE | PARSIPPANY, NJ | LCSW | Clinical Social Worker | 06/27/2022 |
| REMBERT, ANEISHA | AKRON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| REMIEN, REBECCA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| RENAUD, NICOLE | EGG HARBOR TOWNSHIP, NJ | - | RBT | 09/21/2026 |
| RENDER, ELYZA | BAY CITY, MI | - | RBT | 09/21/2026 |
| RENEAU, MIKAYLA | FLEMING ISLAND, FL | - | RBT | 09/25/2026 |
| RENEE R MOLZON COUNSELING, LLCORG | CHARDON, OH | - | Clinical Social Worker | 02/21/2018 |
| RENELLO, ANTHONY | SUN CITY WEST, AZ | MS LISAC | Addiction (Substance Use Disorder) Counselor | 05/31/2018 |
| RENEW AGAIN, LLCORG | RALEIGH, NC | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| RENEWED HOPE BEHAVIORAL HEALTHORG | WICHITA, KS | - | Case Manager/Care Coordinator | 06/02/2026 |
| RENEWED MINDS THERAPY & WELLNESS LLCORG | CHICAGO, IL | - | Psychologist | 02/04/2026 |
| RENEWED MINDS, LLCORG | BELLEVUE, NE | - | Mental Health Counselor | 10/30/2023 |
| RENNISON, DEEANNA | COLORADO SPRINGS, CO | QBHA | RBT | 08/22/2019 |
| RENO, MELISSA | ORANGE, TX | LPC | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| RENTERIA, FRANCISCO | CHANTILLY, VA | - | RBT | 05/15/2024 |
| RESENDIZ, BERENICE | VISTA, CA | - | Counselor | 09/22/2026 |
| RESENDIZ, LUIS | CHICAGO, IL | LCPC | Mental Health Counselor | 06/25/2024 |
| RESTORATION VILLAGEORG | WAYNE, NJ | - | Case Management Agency | 09/22/2026 |
| RESTORE THERAPY CENTERORG | FULLERTON, CA | - | Counselor | 04/20/2026 |
| RESTREPO, KELLIE | SAVANNAH, GA | - | RBT | 09/24/2026 |
| RESTUCCIA, JENNIE | WALLKILL, NY | LCSW | Clinical Social Worker | 07/28/2026 |
| RESUELLO, CHRISTINA | TRACY, CA | - | RBT | 10/09/2023 |
| RETUNDIE, LEANNE | LINCOLNTON, NC | LCMHCA | Professional Counselor | 10/31/2022 |
| REVE, SHAWNTAVIA | MIAMI, FL | LCSW-QS | Clinical Social Worker | 08/02/2017 |
| REVELS, DEANNA | LAKEWOOD, OH | LPCC | Professional Counselor | 10/28/2019 |
| REVELS, JONATHAN | MILFORD, DE | MS, LCDP, LPCMH | Mental Health Counselor | 06/21/2016 |
| REVERE, DYLAN | MARYSVILLE, WA | - | Speech-Language Pathologist | 10/10/2025 |
| REVIVE WOUND CARE PLLCORG | MCALLEN, TX | - | Clinic/Center | 10/02/2024 |
| REY-ALVAREZ, ELAHNI | PHILADELPHIA, PA | BCBA | BCBA | 09/22/2026 |
| REY, MARLENIS | MIAMI, FL | RBT | RBT | 04/19/2024 |
| REYES ARANA, KAREN | SAN DIEGO, CA | MSW | Clinical Social Worker | 11/08/2023 |
| REYES HERNANDEZ, DANNIELHYS | CLARKSVILLE, TN | - | RBT | 09/01/2026 |
| REYES MENDOZA, ALMELY | WYOMISSING, PA | - | RBT | 09/22/2026 |
| REYES SANSORES, JUAN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| REYES-ORTIZ, MARTHA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| REYES-TOVAR, ASHLEY | SAN FRANCISCO, CA | - | Clinical Social Worker | 12/12/2016 |
| REYES, ALEXANDER | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| REYES, ALEXZA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| REYES, ALYSSA | RAYMONDVILLE, TX | LPC-A | Mental Health Counselor | 09/24/2026 |
| REYES, AUBREY | MANCHESTER, CT | - | RBT | 09/23/2026 |
| REYES, ELIZABETH | SAN DIEGO, CA | - | Clinical Social Worker | 09/25/2026 |
| REYES, GISELLE | AUSTIN, TX | RBT | RBT | 09/21/2026 |
| REYES, OLIVIA | BROOKLYN, NY | - | RBT | 09/23/2026 |
| REYNOLDS PICHIAL, SCARLETTE | INKSTER, MI | - | RBT | 09/23/2026 |
| REYNOLDS, DANIELLE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| REYNOLDS, KATIE | BURLINGTON, VT | LICSW | Clinical Social Worker | 02/01/2016 |
| REYNOLDS, LAURA | TARBORO, NC | - | Counselor | 06/02/2008 |
| REYNOLDS, VICTORIA | PALATINE, IL | - | Professional Counselor | 12/07/2020 |
| REYNOSO, BRIANNA | SAN JOSE, CA | - | Speech-Language Pathologist | 09/22/2026 |
| REZA, BRIANNA | SURPRISE, AZ | - | RBT | 09/22/2026 |
| REZK, KYRILLOS | COVINA, CA | - | RBT | 09/23/2026 |
| RHODES-COURTER, ASHLEY | ST PETERSBURG, FL | LCSW, MSW, BC-TMH | BCBA | 07/30/2019 |
| RHODES, NYAH | BROCKTON, MA | - | RBT | 09/26/2026 |
| RHOMBERG, THOMAS | DUBUQUE, IA | TLMHC | Mental Health Counselor | 10/29/2025 |
| RHYNE, ERIN | SPINDALE, NC | LCSW | Clinical Social Worker | 03/13/2024 |
| RIBBEY, MELISSA | ROCHESTER, MI | LLPC | Professional Counselor | 05/31/2012 |
| RICCARDO, RACHEL | TAMPA, FL | - | BCBA | 01/10/2024 |
| RICE, ASHLYN | GREER, SC | - | RBT | 09/25/2026 |
| RICE, KIESHA | CINCINNATI, OH | - | Counselor | 09/24/2026 |
| RICE, SERENA | SEATTLE, WA | - | Counselor | 09/10/2026 |
| RICH, HALEY | IDAHO FALLS, ID | BS | Case Manager/Care Coordinator | 09/23/2026 |
| RICH, REBECCA | CHICAGO, IL | LCSW | Clinical Social Worker | 07/31/2023 |
| RICHARD, JAMAYA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| RICHARDS, AMBER | FARMINGTON HILLS, MI | - | RBT | 09/13/2022 |
| RICHARDS, AVINA | MILWAUKEE, WI | LPC-IT | Professional Counselor | 10/04/2019 |
| RICHARDS, KAITLIN | MINNETONKA, MN | MSW, LICSW | Clinical Social Worker | 04/13/2020 |
| RICHARDS, LEAH | INDIANAPOLIS, IN | - | RBT | 09/24/2026 |
| RICHARDS, NICOLLE | FRIENDSWOOD, TX | - | Speech-Language Pathologist | 09/21/2026 |
| RICHARDSON, GRACE | GROVE CITY, OH | - | Mental Health Counselor | 04/07/2021 |
| RICHARDSON, KIMBERLEY | BROOKLINE, MA | - | Clinical Social Worker | 09/06/2019 |
| RICHARDSON, LILY | OVERLAND PARK, KS | - | RBT | 09/22/2026 |
| RICHARDSON, LUCHUNA | FARMINGTON HILLS, MI | - | RBT | 05/01/2026 |
| RICHARDSON, SONYA | MONROVIA, CA | - | RBT | 09/23/2026 |
| RICHMOND-JOHNSON, KIA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| RICHMOND, ROBIN | EVERETT, WA | - | Mental Health Counselor | 11/08/2022 |
| RICHTER, CORA | STATEN ISLAND, NY | LCSW | Clinical Social Worker | 10/10/2019 |
| RICKETTS, TONYA | LOUISVILLE, KY | LPCC | Professional Counselor | 09/23/2026 |
| RICO HERNANDEZ, YARELIS | LOUISVILLE, KY | - | RBT | 09/24/2026 |
| RICO, JENNIFER | POMONA, CA | - | RBT | 09/21/2026 |
| RIDDICK, JETE' | RALEIGH, NC | - | RBT | 09/21/2026 |
| RIDEOUT, KENNETH | TARENTUM, PA | M. ED. | Addiction (Substance Use Disorder) Counselor | 10/03/2006 |
| RIDGELL, TAPANGA | ST GEORGE, UT | - | RBT | 09/23/2026 |
| RIDGEWAY, HORATIO | NORTH HIGHLANDS, CA | - | BCBA | 09/22/2026 |
| RIDGHAUS, UNKNOWN | SALEM, OR | ASSOCIATE LICENSED P | Mental Health Counselor | 12/23/2024 |
| RIESELBACH, MAYA | SEATTLE, WA | PHD | Psychologist | 05/25/2021 |
| RIFE, JACQUELINE | MORGANTOWN, WV | LICSW | Clinical Social Worker | 06/14/2022 |
| RIFE, JESSICA | ORIENT, OH | LISW | Clinical Social Worker | 08/06/2019 |
| RIGHT DIRECTION BEHAVIORAL SERVICESORG | BEACHWOOD, OH | - | Mental Health Counselor | 08/07/2020 |
| RIJO AMPARO, ROSA | FARMINGTON HILLS, MI | - | RBT | 09/24/2026 |
| RIKLON, MELINA | ELK GROVE, CA | - | RBT | 09/25/2026 |
| RILEY, GENOVIA | ROSEDALE, MD | LCSW-C | Clinical Social Worker | 01/04/2024 |
| RILEY, ISABELLA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| RILEY, MEGAN | BOISE, ID | BCBA | BCBA | 10/28/2020 |
| RILEY, NICOLLETTE | ORLANDO, FL | - | RBT | 09/22/2026 |
| RILEY, PRECIOUS | BETHLEHEM, PA | - | RBT | 09/25/2026 |
| RILEY, REBEKAH | SACO, ME | LCPC-C, NCC | Professional Counselor | 09/21/2026 |
| RINALDI, GIANNA | PASADENA, CA | - | Mental Health Counselor | 01/31/2025 |
| RINCON LABS, INC.ORG | VENICE, CA | - | Case Management Agency | 09/26/2026 |
| RINEY, CASSIDY | MUNCIE, IN | - | RBT | 09/24/2026 |
| RINGHAND, COLE | LONGMONT, CO | - | RBT | 09/25/2026 |
| RIOS, STEFANNI | SPRINGDALE, AR | - | RBT | 05/23/2023 |
| RIOS, YAHAIRA | FRESNO, TX | LCSW | Clinical Social Worker | 09/26/2026 |
| RIPLEY, JERAD | WILLIMANTIC, CT | LCSW | Clinical Social Worker | 12/08/2022 |
| RIPTOE, BARAKA | GOLDSBORO, NC | - | Clinical Social Worker | 09/23/2026 |
| RISE ABOVE RECOVERY, LLCORG | WASILLA, AK | - | Addiction (Substance Use Disorder) Counselor | 02/05/2026 |
| RISE BEHAVIOR THERAPY VIRGINIA LLCORG | HERNDON, VA | - | Community/Behavioral Health Agency | 09/22/2026 |
| RISE COUNSELING AND WELLNESS CENTERORG | HUNTSVILLE, TX | - | Counselor | 08/08/2018 |
| RISING VOICES SPEECH AND LANGUAGE LLCORG | OAKLAND PARK, FL | - | Clinic/Center | 09/09/2026 |
| RITTER, REILLY | TABERNACLE, NJ | LAC | Counselor | 09/26/2026 |
| RITTON, RACHEL | OMAHA, NE | LICSW | Clinical Social Worker | 09/21/2026 |
| RIVAS-GARCIA, LUCIA | BOWLING GREEN, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| RIVAS, ALEJANDRA | LAREDO, TX | M.A., LPC | Mental Health Counselor | 09/24/2026 |
| RIVAS, ANABELLA | SAN ANTONIO, TX | - | RBT | 09/22/2026 |
| RIVAS, EMELY | GARDENA, CA | - | BCBA | 04/18/2026 |
| RIVAS, GISELLE | LONG BEACH, CA | - | Addiction (Substance Use Disorder) Counselor | 06/16/2022 |
| RIVER CITY RECOVERY LLCORG | ALBUQUERQUE, NM | - | Addiction (Substance Use Disorder) Counselor | 11/09/2019 |
| RIVERA RAMIREZ, KAREN | REEDLEY, CA | - | Speech-Language Pathologist | 09/23/2026 |
| RIVERA-DOBSON, AIDA | FARMINGTON HILLS, MI | - | RBT | 05/30/2012 |
| RIVERA-PAINTER, ADRIANNA | GUNTERSVILLE, AL | ALC05682 | Mental Health Counselor | 09/22/2026 |
| RIVERA, ADRIANA | WALNUT CREEK, CA | - | RBT | 09/21/2026 |
| RIVERA, ANGELA | PASADENA, CA | - | Case Manager/Care Coordinator | 11/07/2023 |
| RIVERA, ASHLEY | WEST PALM BEACH, FL | - | Mental Health Counselor | 07/25/2023 |
| RIVERA, CAROLYN | PERRIS, CA | - | Speech-Language Pathologist | 11/22/2020 |
| RIVERA, DEJANISE | NORWALK, CT | - | RBT | 09/22/2026 |
| RIVERA, DIGNA | HIGHLAND PARK, IL | MSW | Counselor | 05/29/2007 |
| RIVERA, ENA | ORLANDO, FL | - | RBT | 11/24/2025 |
| RIVERA, JOSHELLE | FRESNO, CA | - | RBT | 09/24/2026 |
| RIVERA, KATYA | PALMDALE, CA | - | RBT | 09/21/2026 |
| RIVERA, LINSEY | LAS CRUCES, NM | - | RBT | 09/23/2026 |
| RIVERA, MARIA | EL PASO, TX | LPC | Professional Counselor | 10/07/2024 |
| RIVERA, RAYMOND | NORWALK, CA | - | Addiction (Substance Use Disorder) Counselor | 06/03/2024 |
| RIVERA, SHANNON | VAN NUYS, CA | - | RBT | 09/24/2026 |
| RIVERA, SHARLENE | RIVERSIDE, CA | - | BCBA | 09/24/2026 |
| RIVERO-ROMAN, DANIEL | PLANTATION, FL | - | RBT | 06/06/2019 |
| RIVERS, NICOLE | FRAMINGHAM, MA | LMHC | Mental Health Counselor | 09/22/2026 |
| RIVKY REICH APPLIED BEHAVIOR ANALYSIS PROFESSIONAL SERVICES PLLCORG | MONSEY, NY | - | Community/Behavioral Health Agency | 07/18/2024 |
| RIZZO, KAYCIE | WEXFORD, PA | SLP | Speech-Language Pathologist | 09/24/2026 |
| RJI AUDIOLOGY, APCORG | PALM SPRINGS, CA | - | Clinic/Center | 09/21/2026 |
| RMED LLCORG | JACKSONVILLE, FL | - | Clinical Social Worker | 05/09/2006 |
| ROA, JOCELYN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| ROACH, JESSICA | FARMINGTON HILLS, MI | - | RBT | 09/24/2026 |
| ROACH, JULIE | LAS VEGAS, NV | RBT | RBT | 09/25/2026 |
| ROACH, TRISTAN | FORT MYERS, FL | - | RBT | 09/23/2026 |
| ROAN, AMANDA | FT LAUDERDALE, FL | - | Clinical Social Worker | 09/22/2026 |
| ROANE, BRYNEZ | BALTIMORE, MD | LCSW-C | Clinical Social Worker | 11/17/2010 |
| ROARK, TAMMY | JOHNSON CITY, TN | LADAC II | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| ROBB, SUSAN | SEATTLE, WA | - | Mental Health Counselor | 09/24/2026 |
| ROBBINS, KELSEY | SPOKANE VALLEY, WA | - | RBT | 12/17/2024 |
| ROBBINS, LAURA | ROCK HILL, SC | AADC-P, CPSS-S | Addiction (Substance Use Disorder) Counselor | 07/06/2020 |
| ROBBINS, MONA | ARLINGTON, TX | PHD, ABPP | Psychologist | 01/12/2015 |
| ROBER, DIANA | RIVERVIEW, FL | M.A., BCBA | BCBA | 09/25/2018 |
| ROBERSON, BARELLA | BOWIE, MD | - | RBT | 09/25/2026 |
| ROBERSON, KEIONTE | SAN JOSE, CA | - | RBT | 09/21/2026 |
| ROBERSON, KENIETRA | GARDEN GROVE, CA | - | RBT | 09/23/2026 |
| ROBERSON, TA'QUAN | STATESVILLE, NC | - | RBT | 09/22/2026 |
| ROBERTS, BRYANT | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/22/2026 |
| ROBERTS, DEIONA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| ROBERTS, KILEY | RIVERVIEW, FL | - | BCBA | 09/25/2026 |
| ROBERTS, LACEY | DECATUR, AL | M.S., CCC-SLP | Speech-Language Pathologist | 05/05/2021 |
| ROBERTS, MICHAEL | MACON, GA | - | RBT | 09/26/2026 |
| ROBERTS, RACHEL | HOUSTON, TX | M.ED. | Professional Counselor | 05/31/2016 |
| ROBERTS, RENA | BRYANT, AR | - | RBT | 09/22/2026 |
| ROBERTS, TABITHA | JACKSON, MI | LLPC | Mental Health Counselor | 08/06/2025 |
| ROBERTSON, ALVIN | WEST PALM BEACH, FL | - | BCBA | 12/15/2014 |
| ROBERTSON, BRYN | LITTLETON, CO | MCJ | Mental Health Counselor | 09/25/2026 |
| ROBERTSON, DUSTY | BAKERSFIELD, CA | RN | Case Manager/Care Coordinator | 05/29/2013 |
| ROBERTSON, JAZMEN | IRWIN, PA | - | RBT | 09/22/2026 |
| ROBERTSON, JESSICA | SUMMERVILLE, GA | LCSW | Clinical Social Worker | 09/25/2026 |
| ROBERTSON, MELISSA | WOODSTOCK, GA | MFT | Professional Counselor | 09/21/2026 |
| ROBESON, MIKAYLA | RED OAK, TX | - | Professional Counselor | 09/25/2026 |
| ROBEY, SUSAN | LANCASTER, PA | LCSW | Mental Health Counselor | 02/16/2023 |
| ROBINS, KELSEY | BUFORD, GA | - | Professional Counselor | 09/21/2026 |
| ROBINSON-RIDGILL, KAREN | FLORENCE, SC | LPC | Counselor | 05/07/2026 |
| ROBINSON, ANGELO | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| ROBINSON, ASHTYN | COLUMBUS, IN | LMHCA, RBT | RBT | 12/09/2021 |
| ROBINSON, BERNADETTE | LAKEWOOD, CO | - | Case Manager/Care Coordinator | 09/22/2026 |
| ROBINSON, CHASON | LAS VEGAS, NV | M.S., BCBA, LBA | BCBA | 04/13/2021 |
| ROBINSON, DAWN | BROOKSVILLE, FL | LCSW | Clinical Social Worker | 07/04/2016 |
| ROBINSON, DENISE | STOCKBRIDGE, GA | - | RBT | 09/24/2026 |
| ROBINSON, DESTINY | VAN NUYS, CA | - | RBT | 09/24/2026 |
| ROBINSON, JANISSA | LAND O LAKES, FL | LSCW | Clinical Social Worker | 12/15/2021 |
| ROBINSON, JIMMY | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| ROBINSON, JUSTIN | EUGENE, OR | - | Case Manager/Care Coordinator | 09/23/2026 |
| ROBINSON, KYOKO | CAMPBELL, CA | AMFT / APCC | Professional Counselor | 03/29/2025 |
| ROBINSON, MARKEITA | RICHMOND, VA | - | RBT | 09/22/2026 |
| ROBINSON, MIRANDA | LAS VEGAS, NV | RBT | BCBA | 08/15/2023 |
| ROBINSON, ROMA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| ROBINSON, SAMANTHA | PORTSMOUTH, OH | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| ROBINSON, SHALIYAH | DURHAM, NC | - | RBT | 09/22/2026 |
| ROBINSON, SIRENA | JACKSON, OH | - | Clinical Social Worker | 03/20/2017 |
| ROBINSON, SOPHIA | HARTFORD, CT | - | RBT | 09/22/2026 |
| ROBINSON, SUSAN | BERWYN, PA | MA/CCC-SLP | Speech-Language Pathologist | 07/22/2019 |
| ROBINSON, TERI | LOS GATOS, CA | - | Mental Health Counselor | 10/04/2024 |
| ROBLE, IBRAAHIIM | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| ROBLES, EMYSHA | NORTHAMPTON, MA | - | Counselor | 09/21/2026 |
| ROBLES, GYPSY | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ROBLES, MALAKHI | RIVERSIDE, CA | - | RBT | 09/22/2026 |
| ROCHA, ISABELLE | SALINAS, CA | - | RBT | 09/21/2026 |
| ROCHA, SYDNEE | HAYWARD, CA | - | RBT | 10/20/2023 |
| ROCKY MOUNTAIN CLINICAL COUNSELING, LLCORG | DENVER, CO | - | Counselor | 09/25/2026 |
| ROCKY MOUNTAIN CLINICAL COUNSELING, LLCORG | DENVER, CO | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| RODGERS, RACHAEL | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| RODGERS, WYATT | PFLUGERVILLE, TX | BCBA | BCBA | 09/23/2026 |
| RODRIGUES, CRYSTAL | KELSEYVILLE, CA | - | Clinical Social Worker | 07/29/2014 |
| RODRIGUEZ AMEZCUA, BRENDA | WOODBURN, OR | - | Speech-Language Pathologist | 09/21/2026 |
| RODRIGUEZ BURNS, DEBBIE | FOLSOM, CA | - | Counselor | 09/24/2026 |
| RODRIGUEZ CARDENAS, NAHOMY | ROSWELL, NM | - | RBT | 09/25/2026 |
| RODRIGUEZ CASTILLO, LIANA | TAMPA, FL | - | RBT | 09/23/2026 |
| RODRIGUEZ LABRADA, IRINIA | BRADENTON, FL | - | RBT | 09/24/2026 |
| RODRIGUEZ MEDINA, ALEXIS | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| RODRIGUEZ PEREZ, ERIKA | VANCOUVER, WA | - | RBT | 09/21/2026 |
| RODRIGUEZ SVEHLA, OLIVIA | OMAHA, NE | - | Mental Health Counselor | 10/10/2024 |
| RODRIGUEZ TRUNK, EMILY | MINNEAPOLIS, MN | - | Clinical Social Worker | 06/26/2023 |
| RODRIGUEZ-HERRERA, JAYDIN | SAN MARCOS, CA | - | RBT | 09/22/2026 |
| RODRIGUEZ-MUNGUIA, YOSELIN | MODESTO, CA | - | RBT | 09/22/2026 |
| RODRIGUEZ, ALEXIS | FARMINGTON HILLS, MI | - | RBT | 09/23/2026 |
| RODRIGUEZ, AMARA | MODESTO, CA | - | RBT | 09/21/2026 |
| RODRIGUEZ, ANNALYSE | VIENNA, VA | - | RBT | 09/25/2026 |
| RODRIGUEZ, ANTHONY | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| RODRIGUEZ, ARACELLI | IDAHO FALLS, ID | B.A. | Case Manager/Care Coordinator | 12/04/2007 |
| RODRIGUEZ, ASHLEY | ORANGE, CA | - | RBT | 09/21/2026 |
| RODRIGUEZ, BELISA | IRVINE, CA | - | RBT | 09/20/2023 |
| RODRIGUEZ, BRIANDA | BROOKLYN, NY | - | RBT | 09/23/2026 |
| RODRIGUEZ, BRIDGETTE | JACKSONVILLE, FL | MS HUMAN SERVICES | RBT | 12/14/2020 |
| RODRIGUEZ, CARMEN | BROOMALL, PA | - | RBT | 09/22/2026 |
| RODRIGUEZ, CLENE | LEAWOOD, KS | - | RBT | 09/24/2026 |
| RODRIGUEZ, DANIELYS | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| RODRIGUEZ, DAVID | BRONX, NY | CASAC | Addiction (Substance Use Disorder) Counselor | 03/11/2016 |
| RODRIGUEZ, ELIZABETH | ONTARIO, CA | - | BCBA | 03/02/2023 |
| RODRIGUEZ, JOE | YONKERS, NY | LCSW | Clinical Social Worker | 05/17/2007 |
| RODRIGUEZ, JULIA | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| RODRIGUEZ, KAREN | ROXBURY, MA | M.S., CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| RODRIGUEZ, KATIANA | DORAL, FL | RBT-26-2851237 | Assistant Behavior Analyst | 09/23/2026 |
| RODRIGUEZ, KRIZIA | BAYAMON, PR | - | Psychologist | 09/21/2026 |
| RODRIGUEZ, LESLIE | PLANTATION, FL | RBT | BCBA | 08/09/2022 |
| RODRIGUEZ, MADELINE | REDWOOD CITY, CA | - | Mental Health Counselor | 09/24/2026 |
| RODRIGUEZ, MARIEL | BOERNE, TX | RBT | RBT | 09/22/2026 |
| RODRIGUEZ, MIALIZ | WYOMISSING, PA | - | RBT | 09/22/2026 |
| RODRIGUEZ, MICHAEL | BLOOMINGTON, CA | - | Addiction (Substance Use Disorder) Counselor | 06/27/2017 |
| RODRIGUEZ, MICHELLE | PURCHASE, NY | - | Speech-Language Pathologist | 11/03/2015 |
| RODRIGUEZ, NAIYA | ELKTON, MD | - | RBT | 09/22/2026 |
| RODRIGUEZ, NICOLE | MIAMI, FL | LMHC | Mental Health Counselor | 04/08/2025 |
| RODRIGUEZ, NICOLE | CLEVELAND, TX | - | RBT | 09/21/2026 |
| RODRIGUEZ, RAUL | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 04/06/2026 |
| RODRIGUEZ, REBECCA | AUSTIN, TX | - | BCBA | 03/05/2026 |
| RODRIGUEZ, SUMMER | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| RODRIGUEZ, THALIA | MAHOPAC, NY | CCC-SLP | Speech-Language Pathologist | 09/25/2026 |
| RODRIGUEZ, TIARA | SIERRA VISTA, AZ | LPC | Professional Counselor | 06/22/2026 |
| RODRIGUEZ, TONENET | NEWTON, MA | - | RBT | 09/23/2026 |
| RODRIGUEZ, TRACI | CLARKSVILLE, TN | RBT | RBT | 09/24/2026 |
| ROE, ALLISON | LOUISVILLE, KY | M.S. CCC/SLP | Speech-Language Pathologist | 07/15/2014 |
| ROE, ZOIE | BRIGHTON, TN | RBT | RBT | 09/25/2026 |
| ROESKE, DEREK | WALNUT CREEK, CA | - | RBT | 09/25/2026 |
| ROGERS, ADEN | SACRAMENTO, CA | LCSW | Clinical Social Worker | 09/17/2024 |
| ROGERS, ALEXIS | VIRGINIA BEACH, VA | QMHP | Mental Health Counselor | 09/23/2026 |
| ROGERS, DANETTA | YOUNGSVILLE, LA | - | RBT | 02/24/2025 |
| ROGERS, ERIN | AUSTIN, TX | - | Professional Counselor | 09/21/2026 |
| ROGERS, JAMES | TAMPA, FL | RBT | RBT | 09/25/2026 |
| ROGERS, KAMARI | PALM DESERT, CA | - | RBT | 09/22/2026 |
| ROGERS, KERRY | LUDINGTON, MI | - | RBT | 09/24/2026 |
| ROGERS, OLIVIA | NEWTON, MA | - | Speech-Language Pathologist | 03/08/2022 |
| ROGGER, TAYLOR | SAFETY HARBOR, FL | BCBA | BCBA | 01/30/2026 |
| ROHR, KELLY | STOW, OH | - | Counselor | 09/09/2025 |
| ROIS, MOLLY | SAINT LOUIS, MO | - | Mental Health Counselor | 09/25/2026 |
| ROJAS, ADRIANA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| ROJAS, LILIANA | SEATTLE, WA | - | RBT | 09/21/2026 |
| ROJO, YAMILET | MARCO ISLAND, FL | - | RBT | 09/24/2026 |
| ROLAND, JESSICA | MURRIETA, CA | - | RBT | 09/22/2026 |
| ROLDAN, CATHERINE | MELVILLE, NY | - | Case Manager/Care Coordinator | 09/21/2026 |
| ROLF, ANNALEE | DALLAS, TX | - | Speech-Language Pathologist | 04/04/2024 |
| ROMAN, ARACELYS | QUEBRADILLAS, PR | - | Psychologist | 01/24/2026 |
| ROMAN, ELIZABETH | BLOOMFIELD, CT | - | Professional Counselor | 09/22/2026 |
| ROMAN, JOSE | HOLYOKE, MA | - | Mental Health Counselor | 09/21/2026 |
| ROMAN, REGINA | SPRINGFIELD, OH | CDCA | Addiction (Substance Use Disorder) Counselor | 02/24/2022 |
| ROMAN, VIVIAN | SAN FRANCISCO, CA | CADC II-CA | Addiction (Substance Use Disorder) Counselor | 09/03/2015 |
| ROMANO, NATALIE | MODESTO, CA | - | RBT | 09/25/2026 |
| ROMEO, MELISSA | CLACKAMAS, OR | - | Mental Health Counselor | 10/09/2023 |
| ROMERO BAEZ, ISAURIS | TAMPA, FL | RBT | RBT | 04/06/2026 |
| ROMERO-PORTILLO, MICHAEL | LOS LUNAS, NM | - | RBT | 09/23/2026 |
| ROMERO, AMELIA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ROMERO, ANDREW | CULVER CITY, CA | - | RBT | 12/16/2020 |
| ROMERO, ANGELINA | BROCKTON, MA | M.S., CCC-SLP | Speech-Language Pathologist | 07/16/2018 |
| ROMERO, BRITTANY | SYRACUSE, UT | - | RBT | 09/22/2026 |
| ROMERO, HALLIE | LYNNWOOD, WA | - | RBT | 09/26/2026 |
| ROMERO, JALEENA | FRISCO, TX | - | RBT | 09/23/2026 |
| ROMERO, LEILANI | ELK GROVE, CA | - | RBT | 09/22/2026 |
| ROMERO, SABRINA | SPANISH FORK, UT | - | RBT | 09/22/2026 |
| ROMERO, YASMINA | SAN BERNARDINO, CA | - | RBT | 09/25/2026 |
| ROMLESKI, DALE | ORISKANY, NY | LCAT | Professional Counselor | 08/17/2021 |
| ROMOSCA, ABBY | OAK RIDGE, TN | - | RBT | 08/31/2022 |
| RONG, VINCENT | OSWEGO, NY | - | Mental Health Counselor | 07/23/2024 |
| ROOKS, APRIL | BEATTYVILLE, KY | LPCC | RBT | 05/19/2009 |
| ROOKS, MEGAN | BLOOMINGDALE, GA | - | Speech-Language Pathologist | 09/26/2026 |
| ROONEY, ELIZABETH | GRAND RAPIDS, MI | LLMFT | Professional Counselor | 09/04/2026 |
| ROONEY, KELLY | GREENFIELD, WI | LPC | Professional Counselor | 02/01/2022 |
| ROOT & RESTORE THERAPY CENTERORG | RIVERSIDE, CA | - | Clinical Social Worker | 09/23/2026 |
| ROOT TO RISE COUNSELING INCORG | ROCKDALE, IL | - | Counselor | 09/21/2026 |
| ROOTED COMMUNICATION CO.ORG | LODI, CA | - | Speech-Language Pathologist | 09/25/2026 |
| ROOTED IN GRACE THERAPY P.L.L.CORG | PORTSMOUTH, NH | - | Clinical Social Worker | 09/15/2026 |
| ROOTED SOULSONG, LLCORG | BOULDER, CO | - | Mental Health Counselor | 02/09/2023 |
| ROOTS & WINGS FAMILY FOUNDATIONORG | LAS VEGAS, NV | - | Case Manager/Care Coordinator | 09/25/2026 |
| ROOTS OF PURPOSE LLCORG | DERIDDER, LA | - | Community/Behavioral Health Agency | 09/16/2026 |
| ROPELATO, MELANIE | MARTINEZ, CA | PHD | Psychologist | 11/05/2013 |
| ROQUE CUEVAS, RAYMUNDO | ANCHORAGE, AK | - | RBT | 09/24/2026 |
| ROQUE, ISABELLA | BAY CITY, MI | - | RBT | 07/17/2023 |
| ROSA MOSES, DAYLEN | CHICAGO, IL | - | RBT | 09/22/2026 |
| ROSALES DIAZ, ANA | RICHMOND, CA | - | Mental Health Counselor | 08/26/2019 |
| ROSALES RODRIGUEZ, JACINTO | CAPE CORAL, FL | - | BCBA | 03/28/2023 |
| ROSALES, GUADALUPE | ROSEMEAD, CA | - | RBT | 09/23/2026 |
| ROSALES, IZABELLA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| ROSARIO VEGA, ISIS | IDAHO FALLS, ID | BS | Case Manager/Care Coordinator | 09/23/2026 |
| ROSARIO, IVELISS | CARY, NC | M.A., LCMHCA | Mental Health Counselor | 09/25/2026 |
| ROSAS GAONA, JENNIFER | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| ROSAS, ARACELI | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 09/25/2026 |
| ROSAS, DAVID | TUCSON, AZ | - | RBT | 09/21/2026 |
| ROSAS, MARISSA | COVINA, CA | - | RBT | 03/31/2025 |
| ROSE ROCK PSYCHIATRY & WELLNESS, LLCORG | SAPULPA, OK | - | Mental Health Counselor | 09/15/2026 |
| ROSE THERAPY COLLECTIVEORG | FLORENCE, AL | - | Mental Health Counselor | 09/25/2026 |
| ROSE, DANIELLE | SPRINGFIELD, MA | LICSW122118 | Clinical Social Worker | 06/17/2015 |
| ROSE, MARIA | VANCOUVER, WA | - | Mental Health Counselor | 04/16/2024 |
| ROSE, RACHEL | LA SALLE, IL | - | Mental Health Counselor | 02/21/2022 |
| ROSE, SAVANNAH | COLUMBIA, SC | - | RBT | 09/22/2026 |
| ROSE, TESSA | COOS BAY, OR | LE | Specialist | 09/22/2026 |
| ROSE, VICKI | GALESBURG, IL | BS,CADC | Professional Counselor | 03/19/2007 |
| ROSEANNA LANCE, LPC, LLCORG | LANCASTER, PA | - | Professional Counselor | 09/22/2026 |
| ROSEMAN, KELLY | COCOA, FL | - | Specialist | 09/25/2026 |
| ROSEMAN, TWANETTA | GASTONIA, NC | NCC, LPC, LCAS-A | Addiction (Substance Use Disorder) Counselor | 06/30/2017 |
| ROSEN, REBECCA | NEW YORK, NY | - | Mental Health Counselor | 09/25/2026 |
| ROSENBLATT, WHITNEY | ASHEVILLE, NC | LCSW | Clinical Social Worker | 07/21/2023 |
| ROSETE, DENISE | ESCONDIDO, CA | RBT | Addiction (Substance Use Disorder) Counselor | 06/30/2021 |
| ROSOW, ALISON | FLUSHING, NY | LCSW | Mental Health Counselor | 09/22/2026 |
| ROSS, COURTNEY | OREM, UT | - | RBT | 09/25/2026 |
| ROSS, EBONI | WIXOM, MI | - | Clinical Social Worker | 01/23/2023 |
| ROSS, ELLEN | SEATTLE, WA | LMHC | Professional Counselor | 01/08/2018 |
| ROSS, EMILY | ALLENTOWN, PA | - | RBT | 09/24/2026 |
| ROSS, GARRETT | PORTLAND, OR | - | Counselor | 07/21/2016 |
| ROSS, JALIL | ELYRIA, OH | - | RBT | 09/21/2026 |
| ROSS, LADEJA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| ROSS, MORGAN | KENNETT, MO | - | RBT | 09/23/2026 |
| ROSS, MOSHE | FAR ROCKAWAY, NY | LMHC | Mental Health Counselor | 08/01/2023 |
| ROSS, STEPHANIE | SANTA ROSA, CA | - | Day Training/Habilitation Specialist | 06/22/2026 |
| ROSSITTO, JULIANA | WILDOMAR, CA | - | RBT | 09/24/2026 |
| ROTH, DAVID | SAN DIEGO, CA | AMFT | Counselor | 09/22/2026 |
| ROTMAN, KAYLA | HOLLAND, MI | - | Clinical Social Worker | 10/18/2017 |
| ROTOLO, TAYLOR | JERSEY CITY, NJ | LCSW, ACHT | Clinical Social Worker | 05/07/2021 |
| ROTSIDES, KATE | PAOLI, PA | - | Speech-Language Pathologist | 09/23/2026 |
| ROUCH, BROOKE | OGDEN, UT | - | RBT | 09/24/2026 |
| ROULEAU, ALEXANDER | PALM CITY, FL | - | RBT | 09/21/2026 |
| ROULHAC, ADRIANNA | HOPE MILLS, NC | - | RBT | 09/22/2026 |
| ROUSH, MAKAYLA | LOGAN, OH | - | Case Manager/Care Coordinator | 01/12/2026 |
| ROVIRA, GENESIS | TORRANCE, CA | - | RBT | 09/21/2026 |
| ROVNAK, MARGARET | BARRE, VT | - | Case Manager/Care Coordinator | 09/22/2026 |
| ROW, PETER | ORANGE, CA | - | Clinical Social Worker | 08/21/2017 |
| ROWAN BEHAVIORAL HEALTH AND CONSULTING LLCORG | TUPELO, MS | - | Clinical Social Worker | 07/17/2026 |
| ROWAN, JENNIFER | DENVER, NC | LCSW | Clinical Social Worker | 06/27/2022 |
| ROWE, BRIANA | GARDEN GROVE, CA | - | BCBA | 09/25/2026 |
| ROWE, JORDAN | MARIETTA, GA | - | RBT | 09/21/2026 |
| ROWETON, CHASE | FAYETTEVILLE, AR | M.S., LAC | Mental Health Counselor | 02/12/2020 |
| ROWLAND-WALKER, DANA | LANCASTER, CA | - | Case Manager/Care Coordinator | 01/31/2018 |
| ROWLETT, BLAKE | MURFREESBORO, TN | LPC-MHSP | Mental Health Counselor | 04/27/2022 |
| ROWLETT, SAMANTHA | CINCINNATI, OH | - | Specialist | 09/24/2026 |
| ROY, AVA | PINEVILLE, LA | M.A., L-SLP, CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| ROY, NIGEL | HOUSTON, TX | - | RBT | 09/22/2026 |
| ROYALTY, JACEY | EVANSVILLE, IN | RBT | RBT | 09/21/2026 |
| ROYER, ISABEL | SOMERVILLE, MA | - | Speech-Language Pathologist | 09/21/2026 |
| ROYER, OLIVIA | GREENVILLE, SC | - | Clinical Social Worker | 03/15/2021 |
| RUBASH, ALICIA | RIVERBANK, CA | - | RBT | 09/23/2026 |
| RUBIN, DAISY | LONG BEACH, CA | - | RBT | 09/22/2026 |
| RUBIO ANDRADE, JOSEPH | NAPERVILLE, IL | - | RBT | 04/20/2026 |
| RUBIO ROSERO, DANA | DUNCAN, OK | - | RBT | 09/23/2026 |
| RUBIO, JESUS | FRESNO, CA | - | Counselor | 09/21/2026 |
| RUBIO, JULIETTE | SANTA CRUZ, CA | - | BCBA | 06/11/2018 |
| RUBY, ELIJAH | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| RUCKER, CAITLIN | MERRIMACK, NH | LCMHC | Counselor | 09/22/2026 |
| RUCKER, T'ERRA | WAUKEGAN, IL | - | Case Manager/Care Coordinator | 09/22/2026 |
| RUCKMAN, JENNIFER | TROY, MO | LCSW | Clinical Social Worker | 09/03/2024 |
| RUDULPH, MICHAEL | BIRMINGHAM, AL | - | Clinical Social Worker | 09/23/2026 |
| RUDY, DANIELLE | WYOMISSING, PA | - | RBT | 09/25/2026 |
| RUELAS, SAMANTHA | MONTEREY, CA | - | RBT | 04/26/2023 |
| RUF, LISA | MARIETTA, OH | - | Case Manager/Care Coordinator | 11/02/2016 |
| RUFFIN, JENNA | FARMINGTON HILLS, MI | LLMSW | Clinical Social Worker | 09/23/2026 |
| RUGGERA BRAUNREITER, JESSICA | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| RUGGERO, JESSICA | GRAND RAPIDS, MI | - | RBT | 09/24/2026 |
| RUIZ CASTRO, MARBELLA | MEDFORD, OR | QMHA | Mental Health Counselor | 09/11/2026 |
| RUIZ DEAL, MICHELLE | SAN ANTONIO, TX | LPC | Professional Counselor | 10/23/2018 |
| RUIZ-FERNANDEZ, ANA | ORLAND, CA | - | Day Training/Habilitation Specialist | 06/19/2019 |
| RUIZ-LUGO, JACQUELINE | WESLACO, TX | LCSW-S | Clinical Social Worker | 06/24/2022 |
| RUIZ-VERDUGO, DAISY | LOS ANGELES, CA | - | Clinical Social Worker | 03/25/2014 |
| RUIZ, ALEXIS | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| RUIZ, JACQUELLINE | NORMAN, OK | - | RBT | 09/24/2026 |
| RUIZ, JESSICA | VIENNA, VA | LCMHC, LPC, NCC | Mental Health Counselor | 07/14/2020 |
| RUIZ, VERONICA | CONCORD, CA | - | BCBA | 02/08/2021 |
| RULE, PAM | WAYNESBORO, VA | LPC | Professional Counselor | 04/24/2014 |
| RULLA, BENJAMIN | MCMINNVILLE, OR | - | Counselor | 09/23/2026 |
| RULLMAN, MARYANN | COLORADO SPRINGS, CO | - | Case Manager/Care Coordinator | 09/25/2026 |
| RUMBO, ANGEL | MARION, IA | - | RBT | 09/25/2026 |
| RUMLEY, RANASIA | DEERFIELD BEACH, FL | - | RBT | 05/16/2025 |
| RUMMEL, GRACE | DU BOIS, PA | LCSW | Clinical Social Worker | 03/05/2021 |
| RUNDIO, ERIN | COLUMBUS, OH | CCC-SLP | Speech-Language Pathologist | 07/16/2020 |
| RUNGE, HANNAH | ELYRIA, OH | LCDCIII | Addiction (Substance Use Disorder) Counselor | 06/06/2022 |
| RUNKLES, FLENIA | WESTMINSTER, MD | LCSWC | Clinical Social Worker | 09/09/2025 |
| RUNYON, CORI | TUCSON, AZ | - | Clinical Social Worker | 09/22/2026 |
| RUPARD, TABITHA | SEAGOVILLE, TX | LPC | Mental Health Counselor | 12/03/2017 |
| RURAL MOUNTAIN HEALTH SERVICES LLCORG | MOUNTAIN HOME, ID | - | BCBA | 08/17/2026 |
| RUSBOLDT, SHELBY | ORLAND PARK, IL | - | BCBA | 11/10/2020 |
| RUSH, PHILIP | GREENVILLE, SC | LMFT | Addiction (Substance Use Disorder) Counselor | 01/06/2022 |
| RUSS, JIHADA | OMAHA, NE | - | RBT | 07/13/2026 |
| RUSSELL, ABBEY | GALLIPOLIS, OH | P.C. | Professional Counselor | 01/16/2014 |
| RUSSELL, ALAINA | SALEM, OR | - | Mental Health Counselor | 03/05/2024 |
| RUSSELL, BRYON | NEWARK, DE | LPCMH | Counselor | 06/18/2024 |
| RUSSELL, CHRISTOPHER | JONESBORO, AR | LCSW | Clinical Social Worker | 08/10/2023 |
| RUSSELL, COURTNEY | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| RUSSELL, ELINAH | COLORADO SPRINGS, CO | LCSW | Clinical Social Worker | 01/20/2021 |
| RUSSELL, KERRY | ST CHARLES, IL | - | RBT | 09/21/2026 |
| RUSSELL, SIERRA | FRESNO, CA | - | RBT | 09/23/2026 |
| RUSSO, ALISHA | NEW ROCHELLE, NY | - | Mental Health Counselor | 09/22/2026 |
| RUTLEDGE, CADEE | WILLOW SPRINGS, MO | MSCF-SLP | Speech-Language Pathologist | 09/08/2026 |
| RUTTEN, KAELY | LEWISVILLE, TX | - | RBT | 10/09/2019 |
| RUVALCABA, JANELL | BRAWLEY, CA | - | Assistant Behavior Analyst | 09/24/2026 |
| RWEBOGORA, CARLOS | AKRON, OH | - | Mental Health Counselor | 08/12/2025 |
| RYAN-LEAP, SHANNON | ODESSA, MO | LPC | Professional Counselor | 12/06/2024 |
| RYAN, ALEXIS | CHICAGO, IL | LCPC | Professional Counselor | 03/11/2021 |
| RYAN, IMANI | CHICAGO, IL | LPC | Professional Counselor | 11/10/2023 |
| RYAN, JERI | OAKLAND, CA | - | Day Training/Habilitation Specialist | 07/27/2022 |
| RYAN, OLIVIANNE | SAN BERNARDINO, CA | - | RBT | 09/23/2026 |
| RYAN, TYLER | ANN ARBOR, MI | - | Psychologist | 12/20/2016 |
| RYDER, FELICIA | SHAWNEE, KS | - | RBT | 09/22/2026 |
| RYER, MELANIE | LITTLETON, CO | - | Mental Health Counselor | 09/25/2026 |
| S AND S SHAW AND SON COUNSELING LLCORG | ENTERPRISE, AL | - | Mental Health Counselor | 09/24/2026 |
| S&A CONSULTANT LLCORG | HOPEWELL, VA | - | Community/Behavioral Health Agency | 06/25/2025 |
| SA, CANDICE | CARSON CITY, NV | QMHA | Clinical Social Worker | 06/02/2021 |
| SAAD, SAMA | FARMINGTON HILLS, MI | - | RBT | 09/24/2026 |
| SAALAH, AMUUNI | COLUMBUS, OH | - | RBT | 09/23/2026 |
| SAAVEDRA, DAVID | TINLEY PARK, IL | - | Mental Health Counselor | 09/21/2026 |
| SABA INTEGRATED BEHAVIORAL HEALTH SERVICES, LLCORG | PHOENIX, AZ | - | Professional Counselor | 10/05/2022 |
| SABA INTEGRATED BEHAVIORAL HEALTH SERVICES, LLCORG | PHOENIX, AZ | - | Professional Counselor | 01/24/2022 |
| SABA INTEGRATED BEHAVIORAL HEALTH SERVICES, LLCORG | PHOENIX, AZ | - | Professional Counselor | 10/13/2023 |
| SABADO, WILLIAM | SOUTHFIELD, MI | MSW, JD | Case Manager/Care Coordinator | 06/29/2022 |
| SABATINO, LAURIE | PORTLAND, OR | MSW, LCSW | Clinical Social Worker | 09/21/2026 |
| SABIN-WHITE, TREVA | HANOVER, MA | LICSW | Clinical Social Worker | 09/26/2006 |
| SABIR, SADIYAH | BALTIMORE, MD | - | RBT | 09/25/2026 |
| SABRINA CRUZ, LCSW, PLLCORG | MIAMI, FL | - | Clinical Social Worker | 09/10/2026 |
| SADIGZADE, NIGAR | ALEXANDRIA, VA | - | RBT | 09/24/2026 |
| SADIQ, YUSMA | BALTIMORE, MD | - | Mental Health Counselor | 09/22/2026 |
| SADLER, SECOYIA | FARMINGTON HILLS, MI | - | RBT | 09/17/2026 |
| SAENZ, STEPHANIE | SPRING, TX | - | RBT | 09/21/2026 |
| SAFARI HEALTH SERVICESORG | BOISE, ID | - | Mental Health Counselor | 04/18/2024 |
| SAFARI, EMMA | THOUSAND OAKS, CA | - | Mental Health Counselor | 09/25/2026 |
| SAFE HARBOR WELLNESS COLLECTIVE, PLLCORG | BENNINGTON, VT | - | Mental Health Counselor | 03/25/2026 |
| SAFE HAVEN CONNECTION LLCORG | CHERRY HILL, NJ | - | Community/Behavioral Health Agency | 09/25/2026 |
| SAFE PLACE THERAPYORG | BRYAN, TX | - | Counselor | 09/25/2026 |
| SAHAY, NAINA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SAINT FRANCIS COMMUNITY SERVICES IN MISSISSIPPI INCORG | PICAYUNE, MS | - | Community/Behavioral Health Agency | 01/06/2012 |
| SAINT FRANCIS COMMUNITY SERVICES IN MISSISSIPPI INCORG | CARRIERE, MS | - | Community/Behavioral Health Agency | 11/20/2015 |
| SAINTE, VLADIMIR | KANSAS CITY, MO | LCSW | Clinical Social Worker | 10/05/2012 |
| SAJJAD, FATIMA | ROCKVILLE, MD | - | RBT | 09/25/2026 |
| SAK, THOMAS | ALGONQUIN, IL | PSYD | Psychologist | 07/20/2018 |
| SAKA, ROSEMARY | LOS ANGELES, CA | MA, CCC-SLP | Speech-Language Pathologist | 11/22/2017 |
| SAKHAWAT, TAUFIKA | MACEDONIA, OH | LISW | Clinical Social Worker | 08/12/2021 |
| SALAA, MELISSA | PHARR, TX | - | Professional Counselor | 09/24/2026 |
| SALAIS-ARENAS, YAILYN | TACOMA, WA | - | Clinical Social Worker | 09/22/2026 |
| SALAM5ORG | BROOKLYN, NY | - | Specialist | 09/25/2026 |
| SALAMAN BIRD, HARRY | SAINT CLOUD, FL | BCBA | BCBA | 11/07/2018 |
| SALAMONE, DAVID | BOSTON, MA | - | Clinical Social Worker | 09/22/2026 |
| SALAS, JESSENIA | OKLAHOMA CITY, OK | LCSW | Case Manager/Care Coordinator | 09/25/2026 |
| SALAT, RIDHWAN | TUKWILA, WA | - | RBT | 09/25/2026 |
| SALAZAR, ANALIESE | KYLE, TX | - | BCBA | 09/21/2026 |
| SALAZAR, ANAVEAH | RIVERBANK, CA | - | RBT | 09/21/2026 |
| SALAZAR, ANDREW | NORTH HOLLYWOOD, CA | - | Case Manager/Care Coordinator | 04/04/2019 |
| SALAZAR, ASHLEY | GARDENA, CA | - | RBT | 09/21/2026 |
| SALAZAR, JACKELINE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SALAZAR, MAGDALENA | LAUREL, MD | - | RBT | 09/24/2026 |
| SALAZAR, SADIE | CHICAGO, IL | LCSW | Clinical Social Worker | 01/23/2020 |
| SALAZAR, SARAH | LAS VEGAS, NV | - | Speech-Language Pathologist | 05/01/2019 |
| SALCIDO, LIZETTE | SAN ANTONIO, TX | - | Professional Counselor | 07/25/2017 |
| SALDANA, DEVIN | CORONA, CA | - | RBT | 09/22/2026 |
| SALDANA, MANUEL | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| SALEMI, LIBBY | ENCINO, CA | - | RBT | 09/22/2026 |
| SALES, KIERSTEN | SAN MATEO, CA | - | Counselor | 09/24/2026 |
| SALGADO HO, CYNTHIA | VAN NUYS, CA | - | BCBA | 03/23/2021 |
| SALGADO, JOCELYN | RIDGECREST, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| SALGADO, ROSALIE | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| SALINAS, QUETZALY | RANCHO CUCAMONGA, CA | - | RBT | 09/21/2026 |
| SALLOUM, ZARAGNNA | PORT SAINT LUCIE, FL | - | RBT | 09/21/2026 |
| SALT & LIGHTORG | RICHMOND, VA | - | Case Manager/Care Coordinator | 09/24/2026 |
| SALT & SHORE WELLNESS, PLLCORG | VIRGINIA BEACH, VA | - | Mental Health Counselor | 09/23/2026 |
| SALTMARSH, JENNIFER | QUINCY, MA | - | Clinical Social Worker | 07/20/2020 |
| SALUD WELLNESS LLCORG | LOS ANGELES, CA | - | Case Management Agency | 03/20/2026 |
| SALVANERA, JOAQUIN | HONOLULU, HI | - | RBT | 09/22/2026 |
| SAMARA, DANA | ORLAND PARK, IL | - | RBT | 09/25/2026 |
| SAMCHISEN, AUGUSTINE | PLANO, TX | RBT | RBT | 09/21/2026 |
| SAMMON, DIANE | NORTH ARLINGTON, NJ | LPC | Mental Health Counselor | 08/02/2021 |
| SAMPSON, LORI | SALEM, OR | LMFT, LCAS, CCS | Mental Health Counselor | 07/03/2024 |
| SAMUEL, ALICIA-ANN | TAMARAC, FL | EDD, LMHC,NCC | Counselor | 02/20/2019 |
| SAMUELS, TRISELLE | NARBERTH, PA | CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| SAN JUAN MACHIN, YUDELKYS | HIALEAH, FL | APRN | BCBA | 06/03/2016 |
| SAN JUAN-DUNFORD, GERALDINE | JACKSON, MI | MA LPC | Mental Health Counselor | 12/07/2020 |
| SAN JUAN, KAILEY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SAN MIGUEL, JESSICA | MCALLEN, TX | LPC | Professional Counselor | 05/21/2021 |
| SANABRIA-PAYNE, AALIYAH | CLEVELAND HEIGHTS, OH | - | RBT | 09/24/2026 |
| SANBORN, BRIANNA | PASADENA, TX | M.A. CF-SLP | Speech-Language Pathologist | 08/13/2025 |
| SANCHEZ-ANDERSON, ELLA | PHOENIX, AZ | - | RBT | 09/21/2026 |
| SANCHEZ, ALEJANDRA | NORTH HOLLYWOOD, CA | - | Mental Health Counselor | 06/27/2017 |
| SANCHEZ, ALEJANDRO | BROWNSVILLE, TX | LPC-A | Mental Health Counselor | 09/21/2026 |
| SANCHEZ, ANA | BRANDON, FL | MSW | Clinical Social Worker | 06/10/2013 |
| SANCHEZ, ANGELA | DALLAS, TX | - | Professional Counselor | 09/15/2026 |
| SANCHEZ, ANGELIQUE | PLYMOUTH, MI | - | Clinical Social Worker | 09/21/2026 |
| SANCHEZ, BETTY JEAN | SAN ANTONIO, TX | - | Clinical Social Worker | 09/22/2026 |
| SANCHEZ, ISABELA | SAN ANTONIO, TX | - | RBT | 09/21/2026 |
| SANCHEZ, JOSHUA | COATESVILLE, PA | - | Mental Health Counselor | 04/15/2025 |
| SANCHEZ, KAREN | COSTA MESA, CA | - | RBT | 09/25/2026 |
| SANCHEZ, MICHAEL | BELEN, NM | - | RBT | 01/08/2026 |
| SANCHEZ, RAFAEL | HOLYOKE, MA | - | Mental Health Counselor | 07/15/2020 |
| SANCHEZ, SAUL | ANAHEIM, CA | - | BCBA | 03/26/2019 |
| SANCHSZ, ALACIE | NEW YORK, NY | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| SAND, LAURETTA | BILLINGS, MT | LCPC | Professional Counselor | 12/11/2006 |
| SANDERS, DESTINY | HOBART, IN | - | RBT | 09/21/2026 |
| SANDERS, GABRYEL | HENDERSON, NV | - | RBT | 09/23/2026 |
| SANDERS, GEORGIA | ATLANTA, GA | LCSW | Clinical Social Worker | 09/22/2026 |
| SANDERS, KAYANA | LAS VEGAS, NV | M.S. | BCBA | 07/29/2015 |
| SANDERS, LAUREN | SPOKANE, WA | - | Mental Health Counselor | 11/09/2024 |
| SANDERS, MARLOS | PICKERINGTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| SANDERS, NORYA | INDEPENDENCE, MO | - | RBT | 09/23/2026 |
| SANDERS, PAUL | MIDDLETOWN, RI | LMHC, LCDP | Addiction (Substance Use Disorder) Counselor | 08/16/2008 |
| SANDERS, TYRELL | WESTFIELD, IN | - | RBT | 09/22/2026 |
| SANDERSON, AVERY | ALLEN, TX | - | BCBA | 09/22/2026 |
| SANDI, MUSA | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| SANDOVAL, CINDY | SOUTH PASADENA, CA | BCBA | BCBA | 04/19/2012 |
| SANDOVAL, JULIANA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| SANDOVAL, LILIJEWEL | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| SANDOVAL, SUTIWEYU | LOS ANGELES, CA | - | RBT | 07/22/2024 |
| SANFORD, TAYSIA | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| SANGUYU, MICAH | BROOKLYN, NY | - | Addiction (Substance Use Disorder) Counselor | 07/28/2022 |
| SANKOORIKAL, JENNIFER | TOPEKA, KS | - | Speech-Language Pathologist | 09/21/2026 |
| SANKS, NAZGUL | BILLINGS, MT | LCPC | Mental Health Counselor | 10/20/2021 |
| SANNEH, HADDY | PITTSBURGH, PA | - | RBT | 09/21/2026 |
| SANTEN, ALLISON | LIBERTY, MO | LCSW | Clinical Social Worker | 02/22/2022 |
| SANTIAGO ALMODOVAR, SAFIR | CHULA VISTA, CA | - | RBT | 09/25/2026 |
| SANTIAGO, AMANDA | ALBUQUERQUE, NM | B.S. PSYCHOLOGY | Mental Health Counselor | 10/10/2008 |
| SANTIAGO, JEANETTE | FOREST HILLS, NY | LCSW | Clinical Social Worker | 11/16/2022 |
| SANTIAGO, LUIS | MERIDEN, CT | - | Mental Health Counselor | 09/21/2015 |
| SANTOS AGUIRRE, PALOMA | SAN DIEGO, CA | - | Clinical Social Worker | 02/26/2007 |
| SANTOS ALVES GONCALVES, AUREA HELENA | BROCKTON, MA | - | Mental Health Counselor | 09/24/2026 |
| SANTOS RIVERA, MARIA | KISSIMMEE, FL | - | RBT | 09/21/2026 |
| SANTOS RODRIGUEZ, KIMBERLY | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| SANTOS, CHRISTIAN | BOSTON, MA | - | RBT | 09/24/2026 |
| SANTOS, JONATHAN | BROOKLYN, NY | - | RBT | 09/22/2026 |
| SANTOS, MARIO | HYDE PARK, MA | - | RBT | 09/24/2026 |
| SANTOS, PATRICK | HYDE PARK, MA | - | RBT | 09/24/2026 |
| SANTOYO, LETICIA | LOS ANGELES, CA | - | Clinical Social Worker | 09/22/2026 |
| SANZ, KATHERINE | MIAMI, FL | - | RBT | 09/21/2026 |
| SAPIRO, KENDALL | NEW YORK, NY | - | Clinical Social Worker | 04/22/2025 |
| SARA BOILEN PSY D PLLCORG | WHITEFISH, MT | - | Addiction (Substance Use Disorder) Counselor | 11/25/2020 |
| SARA BOILEN PSY D PLLCORG | WHITEFISH, MT | - | Professional Counselor | 08/28/2017 |
| SARAH H GARNER FOUNDATION INCORG | DOLTON, IL | - | Community/Behavioral Health Agency | 09/21/2026 |
| SARAMAGO, JESSICA | ROCHELLE PARK, NJ | - | Clinical Social Worker | 09/25/2026 |
| SARANGO, MARTIN | PLANTATION, FL | - | Mental Health Counselor | 04/04/2018 |
| SARANICH, KARA | HAMDEN, CT | LCSW | Clinical Social Worker | 09/26/2026 |
| SARGEE, JAIME | CLINTON TWP, MI | - | RBT | 09/22/2026 |
| SARGENT, SHAUNA | SPRINGFIELD, VA | - | Speech-Language Pathologist | 08/28/2012 |
| SARLO, JARED | NORTH CHESTERFIELD, VA | - | RBT | 09/21/2026 |
| SARMIENTO, JAMIELYN | COSTA MESA, CA | - | RBT | 09/16/2026 |
| SARRYN GROUP LLCORG | CONCORD, NC | - | Community/Behavioral Health Agency | 10/03/2024 |
| SARTIN, MEGAN | YUCCA VALLEY, CA | - | RBT | 09/25/2026 |
| SASHA, KEZIAH | WILMINGTON, MA | - | RBT | 09/23/2026 |
| SASIN, CHASE | LEBANON, IN | RBT | RBT | 09/25/2026 |
| SASSER, DIANE | FORT LAUDERDALE, FL | LMHC | Case Manager/Care Coordinator | 03/02/2007 |
| SASSER, EMILY | DAYTON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| SASSON, PRABHJOT | FREMONT, CA | - | RBT | 09/23/2026 |
| SAUCEDO, DAVID | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| SAUCEDO, NATHALY | KAUFMAN, TX | - | RBT | 09/21/2026 |
| SAUCEDO, VALERIA | SHERMAN OAKS, CA | - | RBT | 09/21/2026 |
| SAUCER, MADELYN | HOUSTON, TX | MS, CCC-SLP | Speech-Language Pathologist | 04/28/2025 |
| SAULSBY, ANGELA | JACKSONVILLE, FL | - | RBT | 08/17/2026 |
| SAUNDERS, TARA | EVERETT, WA | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| SAURIT, JULIETA | BOULDER, CO | - | Counselor | 09/22/2026 |
| SAUTTER, TAMARA | CARY, NC | MSW, LCSW, PMH-C | Clinical Social Worker | 01/07/2015 |
| SAVANNAH SLEEP CONSULTANTS LLCORG | SAVANNAH, GA | - | Psychologist | 01/02/2019 |
| SAVANUCK, HANNA | DENVER, CO | - | RBT | 09/21/2026 |
| SAVERESE-BURKITT, LISA | WORCESTER, MA | - | Counselor | 09/26/2026 |
| SAVILLO, SANDRA | SAINT CLOUD, FL | BCBA | BCBA | 02/26/2024 |
| SAWAYA, DOUNIA | BROOKLYN, NY | - | Speech-Language Pathologist | 09/22/2026 |
| SAWIERS, GEORGETTE | SACRAMENTO, CA | - | Clinical Social Worker | 02/02/2022 |
| SAYER, PAIGE | NARRAGANSETT, RI | - | Mental Health Counselor | 09/17/2026 |
| SAYGBAY, CELESTINE | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| SCAFATI, CAITLIN | NEW YORK, NY | LMSW | Clinical Social Worker | 04/02/2020 |
| SCALABRINI, CHRISTINA | MAHOPAC, NY | - | Speech-Language Pathologist | 09/25/2026 |
| SCALES, KELLESHA | TEXARKANA, TX | - | RBT | 09/24/2026 |
| SCALES, RANELDA | ATHENS, AL | - | Professional Counselor | 04/12/2007 |
| SCALES, TYRONE | SEATTLE, WA | - | Counselor | 09/21/2026 |
| SCALORA, JAMIE | STUART, FL | - | RBT | 05/01/2019 |
| SCAVARDA, AMY | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| SCEARSE, MELLISSA | MIDWEST CITY, OK | - | RBT | 09/22/2026 |
| SCHAAP, HEIDI | KEIZER, OR | - | Professional Counselor | 08/22/2025 |
| SCHACHT, JING | FORNEY, TX | LPC | Professional Counselor | 06/24/2026 |
| SCHADEWALD, NATASHA | ELKINS, WV | BCBA | RBT | 08/21/2020 |
| SCHAEFER, MARNI | DANVILLE, CA | - | BCBA | 07/14/2014 |
| SCHAEFLE, STEPHEN | ASHEVILLE, NC | LCSW, LCASA | Clinical Social Worker | 05/16/2023 |
| SCHAFFER, ANA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SCHARRER, MIKAYLA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SCHEIDIG, TIFFANY | HOLLY SPRINGS, NC | SLP | Speech-Language Pathologist | 02/17/2009 |
| SCHEIRER, JESSICA | BEND, OR | LCSW | Clinical Social Worker | 02/09/2021 |
| SCHELL, SAVANNAH | ALBANY, OR | - | RBT | 12/22/2025 |
| SCHELLENBERG, ALLISON | KETTERING, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| SCHELLER, ALEXANDRIA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| SCHERB, CAROLINE | INDIANAPOLIS, IN | - | Speech-Language Pathologist | 09/21/2026 |
| SCHERBARTH, ANDREW | HICKSVILLE, NY | PHD, BCBA-D | BCBA | 12/12/2010 |
| SCHEXNAYDER, SANAA | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| SCHIEFEN, KELSEY | OMAHA, NE | - | Assistant Behavior Analyst | 04/17/2018 |
| SCHIENVAR, SAMANTHA | TINTON FALLS, NJ | BCBA | BCBA | 09/22/2026 |
| SCHILL, EMILY | JUNEAU, WI | LPC | Mental Health Counselor | 10/23/2024 |
| SCHIMMING-WHITE, MARTHA | HAVERHILL, MA | - | Mental Health Counselor | 09/03/2014 |
| SCHIRO, KIMBERLY | LAKE CHARLES, LA | - | Mental Health Counselor | 09/21/2026 |
| SCHLEICHER, MARGARET | LONGMONT, CO | - | Mental Health Counselor | 07/09/2025 |
| SCHLETTY, KATE | ROSEMOUNT, MN | MA, CCC SLP | Speech-Language Pathologist | 09/23/2026 |
| SCHLICHTING, ANDREW | ROSEMOUNT, MN | M.A. CCC-SLP | Speech-Language Pathologist | 05/11/2017 |
| SCHLICHTING, RACHEL | ROSEMOUNT, MN | M.A. CCC-SLP | Speech-Language Pathologist | 07/17/2019 |
| SCHLORFF, ELAINE | URBANA, IL | LCSW | Clinical Social Worker | 12/15/2016 |
| SCHMAHL STEPS COUNSELINGORG | EUGENE, OR | - | Mental Health Counselor | 09/22/2026 |
| SCHMALTZ, LESLEY | NEW ALBANY, IN | LCSW | Clinical Social Worker | 12/11/2006 |
| SCHMECKPEPER, MATTHEW | COUNCIL BLUFFS, IA | MS | Mental Health Counselor | 03/12/2014 |
| SCHMIDT, JACK | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| SCHMIDT, JENNA | EVERETT, WA | LMHC | Mental Health Counselor | 07/15/2024 |
| SCHMIDT, ZACHARY | HOOVER, AL | - | RBT | 09/25/2026 |
| SCHNABEL, FREYA | NEW YORK, NY | M.D. | Specialist | 10/18/2006 |
| SCHNAPP, JONATHAN | NEW YORK, NY | LCSW | Clinical Social Worker | 10/06/2011 |
| SCHNEIDER, CHRISTINA | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| SCHNEIDER, VICTORIA | NORFOLK, NE | - | Mental Health Counselor | 09/22/2026 |
| SCHNELZER, PAULINE | RICHMOND, VA | - | Clinical Social Worker | 09/23/2026 |
| SCHNITT, RUTH | SALT LAKE CITY, UT | LCSW | Clinical Social Worker | 11/11/2024 |
| SCHNUR-FISHMAN, ANNA | BROOKLYN, NY | MHC-LP | Mental Health Counselor | 09/23/2026 |
| SCHOENROCK, MICHELLE | LINCOLN, NE | - | RBT | 03/13/2025 |
| SCHOLARSHIP PREPORG | SANTA ANA, CA | - | RBT | 09/23/2019 |
| SCHOLTEN, WENDI | LITTLETON, CO | - | Mental Health Counselor | 09/22/2026 |
| SCHOVANEC, ADAM | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| SCHRADER, MEGHAN | BUTLER, PA | LCSW | Clinical Social Worker | 01/18/2023 |
| SCHRECK, KERI | ATHENS, OH | - | Case Manager/Care Coordinator | 08/04/2025 |
| SCHRICK, KARLEIGH | WACO, TX | LCSW | Mental Health Counselor | 09/21/2026 |
| SCHROCK, WILLOW | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| SCHUBERT, JEFF | GLENDALE, CA | - | Case Manager/Care Coordinator | 05/05/2013 |
| SCHUELKE, CARRYN | GREEN BAY, WI | - | Counselor | 09/22/2026 |
| SCHUETTER, MIKE | DALLAS, TX | LPC | Mental Health Counselor | 04/25/2019 |
| SCHUH, ELIZABETH | TORRANCE, CA | - | Professional Counselor | 03/12/2024 |
| SCHULLER, MIKAYLA | GRAND RAPIDS, MI | - | Speech-Language Pathologist | 09/23/2026 |
| SCHULTZ, JACOB | MADISON, WI | - | Mental Health Counselor | 09/21/2026 |
| SCHULTZ, SIMONE | BROOKLYN, NY | LMHC,LMSW, LPC,CASAC | Professional Counselor | 03/29/2018 |
| SCHUMACHER, ZACHARY | ATHENS, OH | - | Case Manager/Care Coordinator | 08/24/2017 |
| SCHUMM, PAUL | FARGO, ND | - | Addiction (Substance Use Disorder) Counselor | 02/07/2017 |
| SCHURA, CHELSEY | SHAKER HEIGHTS, OH | LPCC-S | Mental Health Counselor | 03/06/2018 |
| SCHUSTER, JOHN | DU BOIS, PA | MSW/ LCSW | Clinical Social Worker | 06/12/2007 |
| SCHWARTZ, JAY | CEDARHURST, NY | LCSW | Clinical Social Worker | 09/21/2026 |
| SCHWARTZ, THERESA | WYANDOTTE, MI | LMSW | Clinical Social Worker | 07/22/2019 |
| SCHWARZ, LAUREN | MEMPHIS, TN | LMSW | Clinical Social Worker | 09/21/2026 |
| SCHWEIZER, LUKE | NORTH EASTON, MA | - | BCBA | 06/26/2024 |
| SCIAMBRA, VERONICA | LITTLETON, CO | LSW | Case Manager/Care Coordinator | 09/23/2026 |
| SCKIC, INC.ORG | DES MOINES, IA | - | Addiction (Substance Use Disorder) Counselor | 07/21/2025 |
| SCOGGINS-MARTZ, TRACY | SEARCY, AR | - | Day Training/Habilitation Specialist | 09/24/2026 |
| SCOTT, DESHA | BROOKLYN, NY | - | Specialist | 09/26/2026 |
| SCOTT, ELISABETH | SAN FRANCISCO, CA | MS | Speech-Language Pathologist | 07/13/2020 |
| SCOTT, ELIZABETH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SCOTT, IGGY | LOS ANGELES, CA | - | Clinical Social Worker | 09/21/2026 |
| SCOTT, JANSEY | ORANGE, CA | - | Counselor | 09/05/2025 |
| SCOTT, KENNISE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SCOTT, KRISTEN | FORT COLLINS, CO | - | Addiction (Substance Use Disorder) Counselor | 06/13/2024 |
| SCOTT, LAUREN | WAIPAHU, HI | - | RBT | 08/20/2024 |
| SCOTT, LORENA | BEAVERTON, OR | LCSW | Clinical Social Worker | 08/10/2010 |
| SCOTT, SHANNON | LADSON, SC | LPC | Addiction (Substance Use Disorder) Counselor | 11/21/2022 |
| SCOTT, TAYLOR | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| SCOTT, TESSA | FORT SMITH, AR | MHPP | Case Manager/Care Coordinator | 08/25/2016 |
| SCOTT, TYLER | EUGENE, OR | - | Mental Health Counselor | 06/12/2016 |
| SCOVILLE, GILLIAN | COEUR D ALENE, ID | LCSW | Clinical Social Worker | 11/13/2023 |
| SCURVY ELEPHANT THERAPY SERVICES, LLCORG | OIL CITY, PA | - | Clinical Social Worker | 09/20/2024 |
| SCZERBA, ADEANA | GILBERT, AZ | MED, BCBA, LBA | BCBA | 01/22/2019 |
| SEA THERAPY, INC.ORG | WINTHROP, MA | - | Specialist | 09/21/2026 |
| SEALY MENTAL HEALTH COUNSELING SERVICE INC.ORG | SANTA CLARITA, CA | - | Mental Health Counselor | 03/23/2013 |
| SEARLE, LAUREL | OMAHA, NE | - | Mental Health Counselor | 09/22/2026 |
| SEARLES, KYLE | YOUNGSTOWN, OH | - | Professional Counselor | 10/15/2025 |
| SEARS, NATHANIEL | PORTSMOUTH, NH | MD | Specialist | 04/12/2012 |
| SEARS, PENNI | TRUTH OR CONSEQUENCES, NM | - | Addiction (Substance Use Disorder) Counselor | 02/19/2007 |
| SEASONS PEDIATRIC DEVELOPMENT CTR - COLUMBIA LLCORG | COLUMBIA, MO | - | BCBA | 09/21/2026 |
| SEAWARD, REBECCA | FENTON, MI | LLPC | Counselor | 04/16/2015 |
| SEAY, ASHLEE | BOISE, ID | LCPC | Mental Health Counselor | 08/28/2015 |
| SEBEK, MATTHEW | LINCOLN, NE | MSW | Clinical Social Worker | 09/22/2026 |
| SECKLIN, KAYLA | RENO, NV | - | Clinical Social Worker | 08/16/2012 |
| SECOND LANE PLLCORG | GURNEE, IL | - | Mental Health Counselor | 03/30/2026 |
| SECOND SUNRISE THERAPY PLLCORG | OLATHE, CO | - | Professional Counselor | 12/14/2023 |
| SECRIST, CAITLIN | ASHEVILLE, NC | CCC-SLP | Speech-Language Pathologist | 08/03/2017 |
| SECURE CONNECTIONS LLCORG | JONESBORO, AR | - | Clinical Social Worker | 09/25/2026 |
| SEEDS FOR GROWTH AND DEVELOPMENT INCORG | BRONX, NY | - | Addiction (Substance Use Disorder) Counselor | 03/06/2023 |
| SEEFELT, JAMIE | LARGO, FL | - | Clinical Social Worker | 09/21/2026 |
| SEEKINS, BRANDI | LOS ALAMOS, NM | LMSW | Clinical Social Worker | 08/14/2023 |
| SEELY, ANDREW | SPOKANE, WA | MSW/LICSW | Clinical Social Worker | 01/21/2011 |
| SEEMS, KELLIE | BEND, OR | CRM | Addiction (Substance Use Disorder) Counselor | 09/22/2020 |
| SEGAL, RACHEL | FRISCO, CO | LPCC | Mental Health Counselor | 09/24/2026 |
| SEGALL, MATT | SAN FRANCISCO, CA | - | Case Manager/Care Coordinator | 08/24/2026 |
| SEGURA ALEGRIA, MARIA | VICTORVILLE, CA | - | BCBA | 02/29/2024 |
| SEGURA-LOPEZ, JACKELYN | FRESNO, CA | - | RBT | 01/06/2023 |
| SEGURA, ROXANNE | ALBUQUERQUE, NM | - | Addiction (Substance Use Disorder) Counselor | 06/09/2023 |
| SEHREMELIS, JOHNATHAN | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| SEIGNON, PAOLO | MILFORD, MA | - | RBT | 02/27/2026 |
| SEITZ, LINDY | TULSA, OK | LCSW | Clinical Social Worker | 08/03/2006 |
| SELAH COUNSELING & CONSULTING LLCORG | MONROE, LA | - | Professional Counselor | 09/23/2026 |
| SELAH THERAPEUTIC PRACTICE PLLCORG | PORTER, TX | - | Professional Counselor | 09/25/2026 |
| SELAH THERAPY COLLECTIVE, PLLCORG | CLAYTON, NC | - | Clinical Social Worker | 09/26/2026 |
| SELFE, CELIA | ROCKINGHAM, VA | LCSW | Clinical Social Worker | 03/11/2024 |
| SELLENRICK, ANNE | FRESNO, CA | ASW | Clinical Social Worker | 08/19/2026 |
| SELLERS, KRYSTIAN | VIRGINIA BEACH, VA | - | Assistant Behavior Analyst | 09/22/2026 |
| SENECA FAMILY OF AGENCIESORG | KING CITY, CA | - | Community/Behavioral Health Agency | 03/03/2014 |
| SENGELMANN, VICTORIA | BOISE, ID | SLP | Speech-Language Pathologist | 09/21/2026 |
| SENNETT, DONALD | CHARLOTTE, NC | B.S. | Mental Health Counselor | 06/07/2022 |
| SEPRINO, NATALIE | FORT COLLINS, CO | - | Counselor | 09/22/2026 |
| SEPULVEDA, BRENDA | MILFORD, CT | LPCA | Professional Counselor | 04/27/2026 |
| SERATI, JACQUELINE | SAN DIEGO, CA | - | Speech-Language Pathologist | 09/25/2026 |
| SERDA, EBENEZER | SAN ANTONIO, TX | LPC | Professional Counselor | 08/26/2025 |
| SEREMEDY, LLCORG | ATLANTA, GA | - | Mental Health Counselor | 09/25/2026 |
| SERENE COUNSELING SERVICES, LLCORG | FARMINGTON HILLS, MI | - | Mental Health Counselor | 07/26/2024 |
| SERENEPATHWAYS LLCORG | HAYMARKET, VA | - | BCBA | 06/05/2024 |
| SERENGETI WELLNESS, PLLCORG | CHICAGO, IL | - | Community/Behavioral Health Agency | 11/30/2022 |
| SERENITY NP IN PSYCHIATRY SERVICES PLLCORG | NEW YORK, NY | - | Clinic/Center | 11/25/2024 |
| SERENITY OUTPATIENT THERAPY ASSOCIATES, PLLCORG | RALEIGH, NC | - | Mental Health Counselor | 09/24/2026 |
| SERRANO GALLEGOS, REINA | HAYWARD, CA | - | RBT | 08/13/2026 |
| SERRANO, ISABEL | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| SERRANO, ISABELLA | TORRANCE, CA | - | RBT | 09/21/2026 |
| SERVANTEZ, SILVIA | TORRINGTON, WY | - | Day Training/Habilitation Specialist | 09/22/2026 |
| SERVICEBERRY CARE COLLECTIVEORG | FREDERICK, MD | - | Clinical Social Worker | 05/15/2026 |
| SERZAN, JOHN | CENTENNIAL, CO | LSW | Clinical Social Worker | 09/21/2026 |
| SESSIONGLANCE, LLCORG | DETROIT, MI | - | Counselor | 09/24/2026 |
| SESSUM, LEMIYAH | CORDOVA, TN | RBT | RBT | 09/21/2026 |
| SETTLE, DANIELLE | WINSTON SALEM, NC | - | RBT | 09/17/2026 |
| SETZER, KIERSTEN | CHARLOTTE, NC | LCMHCA | Professional Counselor | 07/28/2023 |
| SEVEN OAKS HEALTH SERVICES LLCORG | SILVER CITY, NM | - | Clinical Social Worker | 09/25/2026 |
| SEVIGNY, AMANDA | SALT LAKE CITY, UT | CSW | Clinical Social Worker | 09/22/2026 |
| SEVILLA, ISHMAEL | STUART, FL | - | RBT | 09/22/2026 |
| SEVILLA, SAHIRA | PASADENA, CA | - | Addiction (Substance Use Disorder) Counselor | 11/08/2022 |
| SEXTON, BRITTNI | KNOXVILLE, TN | - | RBT | 11/26/2025 |
| SEYMORE, TAMILA | PORT CHARLOTTE, FL | RMHCI | Mental Health Counselor | 09/24/2026 |
| SHABAZZ, KALIFA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| SHADIX, ANNA | ALLEN, TX | M. ED. | BCBA | 07/31/2020 |
| SHADOWS, SARA | TEHACHAPI, CA | - | Day Training/Habilitation Specialist | 05/20/2020 |
| SHADROOZ, DANIELA | LOS ANGELES, CA | - | Clinical Social Worker | 09/25/2026 |
| SHAFER, LAURA | MOUNTLAKE TERRACE, WA | - | Professional Counselor | 07/18/2024 |
| SHAFFER, ALLISON | ONTARIO, OH | - | RBT | 09/22/2026 |
| SHAFFER, CHANA | NEW YORK, NY | LMSW | Clinical Social Worker | 09/24/2026 |
| SHAFFER, MADELIENE | TALLAHASSEE, FL | - | BCBA | 04/25/2023 |
| SHAFFER, SAMANTHA | HUTTO, TX | BCBA | BCBA | 03/15/2022 |
| SHAFFER, SYDNEY | NEW WINDSOR, NY | - | Speech-Language Pathologist | 09/21/2026 |
| SHAH, AASTHA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| SHAH, RAHI | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| SHAHRYARY, MITRA | FALLS CHURCH, VA | LCSW | Clinical Social Worker | 04/06/2023 |
| SHAKIBA, ABBY | LAFAYETTE, CA | - | BCBA | 03/08/2022 |
| SHAKTI THERAPY & HEALING SERVICESORG | LOS ANGELES, CA | - | Mental Health Counselor | 06/29/2022 |
| SHAMA, ALI MOHAMED | WASHINGTON, DC | - | RBT | 12/13/2024 |
| SHAMALOV, EMILY | ELMHURST, NY | - | Speech-Language Pathologist | 09/23/2026 |
| SHAMIRIAN, DVIN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SHAMULUS, CADY | TEMECULA, CA | - | RBT | 09/25/2026 |
| SHANK, BECKY | IVA, SC | L.I.S.W | Clinical Social Worker | 08/21/2009 |
| SHANNON, SAMUEL | LAS VEGAS, NV | - | RBT | 09/21/2026 |
| SHAPIRO, GABRIEL | WAUKEGAN, IL | BA | Clinical Social Worker | 09/23/2026 |
| SHAPIRO, KIMBERLY | FARMINGTON, CT | - | Mental Health Counselor | 09/23/2026 |
| SHAPOURIAN, ROYA | LOS GATOS, CA | - | RBT | 09/25/2026 |
| SHARE SELF CARE LLCORG | WINSTON SALEM, NC | - | Community/Behavioral Health Agency | 06/06/2025 |
| SHARING SPACE THERAPY LLCORG | MOUNTAIN BRK, AL | - | Clinical Social Worker | 08/21/2026 |
| SHARMA, KHUSHI | ST CHARLES, IL | - | RBT | 09/22/2026 |
| SHARP, AUSTIN | MONROE, MI | - | Clinical Social Worker | 09/03/2026 |
| SHARPE, TREVOR | SPOKANE, WA | - | RBT | 09/23/2026 |
| SHAW, ANN | JACKSON, MI | LMSW | Clinical Social Worker | 09/22/2026 |
| SHAW, DANIELLE | DOWNERS GROVE, IL | - | Professional Counselor | 07/07/2020 |
| SHAW, ERIN | BOSTON, MA | - | Mental Health Counselor | 09/21/2026 |
| SHAW, GAVEN | LAS VEGAS, NV | - | RBT | 09/26/2026 |
| SHAW, JEREMIAH | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| SHEARON, HENRY | DENVER, CO | MBA, B.S. | Case Manager/Care Coordinator | 09/24/2026 |
| SHEEHAN, BEKAH | BOISE, ID | - | RBT | 09/22/2026 |
| SHEEN, JOANNE | KENOSHA, WI | - | Speech-Language Pathologist | 09/21/2026 |
| SHEETS, KRISTOPHER | GILBERT, AZ | LAC | Counselor | 09/21/2026 |
| SHEETS, MADELINE-ELAINE | LORIS, SC | - | Professional Counselor | 06/26/2023 |
| SHEFFIELD, TRISHANA | JACKSONVILLE, FL | LMHC | Mental Health Counselor | 08/21/2023 |
| SHEHY, KENDRA | DENVER, CO | SLP | Speech-Language Pathologist | 09/01/2021 |
| SHEIKH, ROZA | SEATTLE, WA | - | Counselor | 06/06/2024 |
| SHEIN, BRITTANY | SPRINGFIELD, PA | - | BCBA | 09/22/2026 |
| SHEKOUH COUNSELING LLCORG | YUKON, OK | - | Mental Health Counselor | 12/08/2025 |
| SHEKOUH, ALEXANDER | YUKON, OK | LPC-S | Mental Health Counselor | 07/26/2021 |
| SHELDON, BLAIR | MANCHESTER, MD | - | Mental Health Counselor | 09/23/2026 |
| SHELDON, JONATHAN | SHENANDOAH, TX | - | RBT | 09/21/2026 |
| SHELDON, NICOLE | ATTLEBORO, MA | - | Counselor | 10/02/2008 |
| SHELLEY, MADISON | KILLEEN, TX | RBT | RBT | 09/24/2026 |
| SHELTON, KELLY | TULSA, OK | - | Speech-Language Pathologist | 09/22/2015 |
| SHELTON, SHAWNA | BAKERSFIELD, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| SHENANDOAH VALLEY CENTER FOR CONCUSSION AND PAIN MANAGEMENT LLCORG | MARTINSBURG, WV | - | Specialist | 09/21/2026 |
| SHENELLE MICOLE FOSTER, A LICENSED CLINICAL SOCIAL WORKER CORPORATIONORG | OAKLAND, CA | - | Clinical Social Worker | 09/24/2026 |
| SHEPARD, EMMA | TACOMA, WA | - | Clinical Social Worker | 09/22/2026 |
| SHEPARD, MAKHIA | CHARLOTTE, NC | - | RBT | 07/16/2026 |
| SHEPARD, OWEN | OLYMPIA, WA | - | RBT | 08/08/2023 |
| SHEPARD, SIENA | BEND, OR | - | Mental Health Counselor | 09/24/2026 |
| SHEPPARD, JESSICA | WEST BRANCH, MI | - | RBT | 01/27/2017 |
| SHEPPARD, SANIA | JONESBORO, AR | - | RBT | 09/24/2026 |
| SHERIDAN, JESSICA | CUMMING, GA | LMSW | Clinical Social Worker | 09/02/2014 |
| SHERMAN, JUNE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 04/25/2024 |
| SHERMAN, KRYSTAL | AUGUSTA, GA | - | RBT | 01/12/2024 |
| SHERMAN, REGINA | JACKSONVILLE, FL | - | Case Management Agency | 09/11/2020 |
| SHERMAN, SAM | CHICAGO, IL | LCPC | Mental Health Counselor | 09/25/2026 |
| SHERRADEN, KAYLA | MAIZE, KS | LPC | Counselor | 05/25/2023 |
| SHETLER, DEMI | NORTH LIBERTY, IA | - | Mental Health Counselor | 09/21/2026 |
| SHIGEMOTO, RILEY | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SHIMADA, KATHERINE | SEATTLE, WA | MSW | Clinical Social Worker | 02/04/2014 |
| SHINAULT, EMILY | CLEMENTON, NJ | - | Counselor | 09/22/2026 |
| SHINE THE LIGHT COUNSELING, LLCORG | BOX ELDER, SD | - | Mental Health Counselor | 09/21/2026 |
| SHINING LIGHT THERAPY PLLCORG | LAS VEGAS, NV | - | Speech-Language Pathologist | 09/21/2026 |
| SHISLER, MARIA | GOSHEN, IN | RBT | RBT | 09/23/2026 |
| SHOAIB, RABIA | WENTZVILLE, MO | MED, LPC | Mental Health Counselor | 07/09/2024 |
| SHOEMAKER, ALEXANDRIA | UPPER CHICHESTER, PA | - | Professional Counselor | 09/26/2026 |
| SHOEMAKER, JAKEITHA | MANSFIELD, TX | - | Professional Counselor | 07/21/2025 |
| SHOEMAKER, KENNEDY | BREMERTON, WA | - | Counselor | 09/21/2026 |
| SHOEMAKER, TAMIKA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| SHOOK, MEGAN | BEXLEY, OH | RBT | RBT | 09/22/2026 |
| SHOOK, SOMER | ASHLAND, OR | QMHP | Counselor | 09/24/2026 |
| SHORES, SHEILA | FRESNO, CA | MS, BCBA | BCBA | 11/11/2021 |
| SHORROCK, SAMANTHA | ACTON, MA | LMHC | Mental Health Counselor | 09/25/2026 |
| SHORT STEINER, EMILY | CAMP HILL, PA | LMFT | Mental Health Counselor | 06/11/2018 |
| SHOSTAK, PAYTON | LAWRENCE, KS | - | RBT | 09/23/2026 |
| SHULL, TORI | CARLSBAD, NM | - | Case Manager/Care Coordinator | 09/24/2026 |
| SHULTZ, ZACHARY | FORT WAYNE, IN | - | RBT | 08/20/2020 |
| SHURTLEFF, LAURA | HORSE SHOE, NC | - | RBT | 09/24/2026 |
| SIBILIA, LYNNE | NORTH CALDWELL, NJ | MA, CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| SIDDIQ, RABIA | WILMINGTON, MA | - | RBT | 09/23/2026 |
| SIDDIQUI, MARYAM | HONOLULU, HI | RBT | RBT | 09/19/2026 |
| SIDERS, BRIANNA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SIDES, ARIANNA | LONG BEACH, CA | - | Clinical Social Worker | 11/28/2024 |
| SIEFKES, LISA | ROSEMOUNT, MN | MS CCC-SLP | Speech-Language Pathologist | 12/29/2006 |
| SIEGEL, ORLI | PHILADELPHIA, PA | MSW | Clinical Social Worker | 09/24/2026 |
| SIERRA, LUIS | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SIESENNOP, JANA | WAUKESHA, WI | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| SIEWART, ANNMICHAEL | PRESTONSBURG, KY | - | Mental Health Counselor | 09/21/2026 |
| SIGUA, MICHAEL | SACRAMENTO, CA | - | Specialist | 09/21/2026 |
| SIID, TALASA | AURORA, CO | - | RBT | 09/25/2026 |
| SILAS, MYLES | HAMILTON, OH | - | Case Manager/Care Coordinator | 05/09/2018 |
| SILER, TRACY | CHANDLER, AZ | - | Mental Health Counselor | 09/22/2026 |
| SILLAH, DAVIDE | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| SILLS, DANIELLE | JACKSONVILLE, NC | LCAS-A | Addiction (Substance Use Disorder) Counselor | 04/02/2019 |
| SILVA AREND, SARAH | PITTSBURGH, PA | LPC, MS | Mental Health Counselor | 06/02/2023 |
| SILVA MERINO, HESLEER | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| SILVA-IBARRA, MIRASOL | DEERFIELD BEACH, FL | - | RBT | 03/07/2022 |
| SILVA, ASHLEY | AKRON, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| SILVA, CINDY | BROOKLYN, NY | LMSW | Clinical Social Worker | 11/01/2019 |
| SILVA, EMILY | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| SILVAGNOLI, NINEL | CANTON, MA | - | Clinical Social Worker | 05/06/2026 |
| SILVEIRA, JULIA | NEW HAVEN, CT | - | Clinical Social Worker | 11/13/2018 |
| SILVER LINING COUNSELINGORG | CHARLOTTE, NC | - | Mental Health Counselor | 09/24/2020 |
| SILVERA, TYHONA | NEW BEDFORD, MA | - | RBT | 09/23/2026 |
| SILVERLEAF COUNSELING SERVICES LLCORG | APPLETON, WI | - | Mental Health Counselor | 09/26/2026 |
| SILVERMAN, DENA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| SILVERMAN, ROCHELLE | NAPA, CA | - | Clinical Social Worker | 03/20/2011 |
| SILVI, ARIANA | MEDFORD, OR | - | BCBA | 09/22/2026 |
| SIMAO, AMY | FOUNTAIN HILLS, AZ | MS, CCC-SLP | Speech-Language Pathologist | 05/12/2021 |
| SIMBLER, GRACE | SPOKANE VALLEY, WA | - | RBT | 10/27/2021 |
| SIMLEY, CIERA | FARMINGTON HILLS, MI | - | RBT | 09/23/2026 |
| SIMMER, HANNAH | MESA, AZ | SLP | Speech-Language Pathologist | 09/21/2026 |
| SIMMONS, ALEXIS | PASO ROBLES, CA | - | RBT | 09/22/2026 |
| SIMMONS, BRENT DIESEL | CHINO, CA | - | RBT | 09/21/2026 |
| SIMMONS, KELLY | HILLSDALE, MI | MA, LLPC | Mental Health Counselor | 09/24/2026 |
| SIMMONS, KORTNEY | SPRING, TX | LPC | Professional Counselor | 09/26/2024 |
| SIMMONS, MEKHI | SALISBURY, MD | - | RBT | 09/24/2026 |
| SIMMONS, NICOLETTE | FOREST PARK, IL | LPC | Professional Counselor | 06/09/2026 |
| SIMMS, ELLIE | PERU, IN | - | RBT | 09/23/2026 |
| SIMON SPEECH SOLUTIONS LLCORG | PLANTATION, FL | - | Speech-Language Pathologist | 06/02/2026 |
| SIMON, HEATHER | PLAINVIEW, NY | - | Speech-Language Pathologist | 05/08/2025 |
| SIMON, KIMBERLY | LOS ANGELES, CA | - | RBT | 09/21/2026 |
| SIMON, MARGARET | POOLER, GA | - | RBT | 09/23/2026 |
| SIMON, REBECCA | PLANTATION, FL | - | Speech-Language Pathologist | 05/05/2026 |
| SIMPLE SOLUTIONS FAMILY THERAPYORG | VICTORVILLE, CA | - | Community/Behavioral Health Agency | 09/25/2026 |
| SIMPLE SOLUTIONS FAMILY THERAPYORG | RANCHO CUCAMONGA, CA | - | Community/Behavioral Health Agency | 06/08/2020 |
| SIMPLY BEYOND BEHAVIOR LLCORG | HOMESTEAD, FL | - | Clinic/Center | 09/23/2026 |
| SIMPSON, BRYANNA | LIMA, OH | - | Case Manager/Care Coordinator | 10/21/2025 |
| SIMPSON, NADIA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/14/2026 |
| SIMS, JULIA | HARRISBURG, PA | - | Counselor | 09/22/2026 |
| SIMS, KAYLA | ATLANTA, GA | LPC | Professional Counselor | 08/20/2020 |
| SIMS, KENDALL | LA GRANGE, KY | CF-SLP | Speech-Language Pathologist | 09/23/2026 |
| SIMS, NOAH | HAYWARD, CA | - | RBT | 09/22/2026 |
| SIMS, SHAIANNE | NASHVILLE, TN | - | RBT | 09/24/2026 |
| SIMS, SUMMER | WATERTOWN, MA | - | Clinical Social Worker | 09/21/2026 |
| SIN, CALEB | OAKLAND, CA | - | Psychologist | 02/21/2024 |
| SINCLAIR, JADA | FAYETTEVILLE, NC | - | RBT | 09/21/2026 |
| SINCLAIR, MORGAN | DURHAM, NC | - | RBT | 09/23/2026 |
| SINGH, SONIA | CALABASAS, CA | - | RBT | 09/24/2026 |
| SINKEY, ANNE | CLACKAMAS, OR | LCSW | Clinical Social Worker | 06/09/2016 |
| SIPIN, GABRIELLE | REDWOOD CITY, CA | MT-BC | Day Training/Habilitation Specialist | 11/20/2025 |
| SIRINEK, HAYLEY | EAU CLAIRE, WI | - | Mental Health Counselor | 02/11/2026 |
| SIROTA, ALEXIS | NEOSHO FALLS, KS | - | RBT | 09/24/2026 |
| SITZMAN, CATHI | WASHINGTON, DC | PH.D. | Psychologist | 01/27/2014 |
| SIVIN-KACHALA, NADIYA | BRONX, NY | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| SIZEMORE, BRANDI | RICHMOND, IN | RBT | RBT | 05/31/2022 |
| SKAHAN, SARAH | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| SKILL CREATIONS, INC.ORG | GOLDSBORO, NC | - | Community/Behavioral Health Agency | 03/23/2007 |
| SKIN SOLUTIONSORG | KUNKLETOWN, PA | - | Clinic/Center | 05/11/2020 |
| SKINNER LEWIS, NATALIE | KISSIMMEE, FL | LCSW | Clinical Social Worker | 12/17/2009 |
| SKINNER, NATALIE | HANNIBAL, MO | PLPC | Professional Counselor | 09/21/2026 |
| SKINNION, NICOLE | CHICAGO, IL | - | Clinical Social Worker | 10/04/2021 |
| SKOGSETH, ALISON | HASTINGS, MI | - | Clinical Social Worker | 09/09/2026 |
| SKOMER, MINA | FORT COLLINS, CO | - | Counselor | 09/22/2026 |
| SLAGLE, IRENE | EVERETT, WA | AACC | Counselor | 09/25/2026 |
| SLAINTE CLINICORG | HARTLAND, WI | - | Mental Health Counselor | 01/04/2024 |
| SLAPE, GWEN | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| SLATER, CARLOTTA | MOUNT CLEMENS, MI | LPC CADC | Counselor | 03/25/2010 |
| SLATER, MADISON | FARMINGTON HILLS, MI | - | RBT | 12/04/2020 |
| SLATTERY, ALYSSA | MARQUETTE, MI | LMSW | Clinical Social Worker | 09/23/2026 |
| SLAYTON, SARA | RALEIGH, NC | - | Speech-Language Pathologist | 03/09/2026 |
| SLEEN, ISABELLA | ARDEN HILLS, MN | - | RBT | 09/21/2026 |
| SLETTA, CAMBRIA | BOZEMAN, MT | - | RBT | 09/23/2026 |
| SLIWINSKI, GRACE | WOOD DALE, IL | - | RBT | 09/21/2026 |
| SLOAN-STUBBS, KIASHIA | INDIANAPOLIS, IN | - | RBT | 01/31/2025 |
| SLOANE, OLIVIA | BOSTON, MA | - | Counselor | 09/24/2026 |
| SLOCOMBE, EMILY | PORTLAND, OR | - | Mental Health Counselor | 09/24/2026 |
| SLOOP, HAYLEE | LINCOLN, NE | - | Day Training/Habilitation Specialist | 09/25/2026 |
| SLP ONCALL PLLCORG | HOUSTON, TX | - | Speech-Language Pathologist | 10/30/2023 |
| SLPTELE LLCORG | KATY, TX | - | BCBA | 12/19/2019 |
| SLUSHER, STEPHANIE | SAN ANGELO, TX | LCSW | Clinical Social Worker | 09/21/2026 |
| SLUSSER, WILLIAM | DAYTON, OH | BCBA, COBA | Case Manager/Care Coordinator | 02/01/2017 |
| SMAIL, HEATHER | ORLAND PARK, IL | RBT | RBT | 09/24/2026 |
| SMALL TALK THERAPYORG | BIG STONE GAP, VA | - | Speech-Language Pathologist | 04/06/2026 |
| SMALL, BROOKLYNN | HACKENSACK, NJ | - | Assistant Behavior Analyst | 09/24/2026 |
| SMALLTALK SPEECH & LANGUAGE THERAPY, INCORG | BELLEVUE, WA | - | Speech-Language Pathologist | 09/20/2022 |
| SMALLWOOD, MARCHKETA | FAIRBURN, GA | LPC | Mental Health Counselor | 09/23/2026 |
| SMARTRUAMAORG | SPRINGFIELD, MA | - | Case Management Agency | 09/21/2026 |
| SMERKER, ELIZABETH | IRVINE, CA | - | RBT | 09/21/2026 |
| SMETHURST, EMILY | LOWELL, MA | - | RBT | 09/22/2026 |
| SMIDA, ERIN | PROSPECT PARK, PA | LPC | Professional Counselor | 09/22/2026 |
| SMIKLE, OSHEA | FARMINGTON HILLS, MI | - | RBT | 08/08/2023 |
| SMILEY, ERIN | INDIANAPOLIS, IN | LCSW | Clinical Social Worker | 07/17/2026 |
| SMITH TUBBS, AURIE | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| SMITH-MISJA, ANGELA | NORTH RIDGEVILLE, OH | LISW | Clinical Social Worker | 04/12/2022 |
| SMITH, ABBY | ST GEORGE, UT | - | RBT | 09/23/2026 |
| SMITH, AKILAH | PITTSBURGH, PA | - | RBT | 09/23/2026 |
| SMITH, AKILIA | SPRING, TX | - | RBT | 09/22/2026 |
| SMITH, ALIVIA | QUINCY, IL | - | Mental Health Counselor | 09/23/2026 |
| SMITH, ALLISON | ANN ARBOR, MI | - | Clinical Social Worker | 09/21/2026 |
| SMITH, ALLISON | BIDDEFORD, ME | - | Counselor | 09/23/2026 |
| SMITH, AMARA | SEGUIN, TX | - | Clinical Social Worker | 09/25/2026 |
| SMITH, AMBER | HAVERTOWN, PA | LCSW | Clinical Social Worker | 09/15/2021 |
| SMITH, ASHLEY | OMAHA, NE | - | Mental Health Counselor | 09/21/2026 |
| SMITH, ASHLYNN | PENSACOLA, FL | LCSW | Clinical Social Worker | 09/24/2026 |
| SMITH, BRANDEN | PERHAM, MN | - | Professional Counselor | 07/06/2021 |
| SMITH, BRIDGET | PLANO, TX | LCSW | Clinical Social Worker | 06/25/2026 |
| SMITH, BRYON | COLUMBUS, OH | - | Case Manager/Care Coordinator | 08/18/2026 |
| SMITH, CALISTA | CENTREVILLE, MI | - | Clinical Social Worker | 12/29/2021 |
| SMITH, CATHERINE | WASHINGTON, DC | - | Case Manager/Care Coordinator | 04/13/2012 |
| SMITH, CELES | BOWLING GREEN, KY | LCSW | Clinical Social Worker | 04/02/2021 |
| SMITH, CHERYL | HAMDEN, CT | LCSW | Clinical Social Worker | 11/07/2013 |
| SMITH, COLBY | DENVER, CO | - | Mental Health Counselor | 08/24/2026 |
| SMITH, COLTON | REDDING, CA | - | Addiction (Substance Use Disorder) Counselor | 06/05/2023 |
| SMITH, DEJA | METAIRIE, LA | - | BCBA | 08/26/2020 |
| SMITH, ELLA | LEAWOOD, KS | - | RBT | 09/23/2026 |
| SMITH, EMILY | ROSEVILLE, CA | - | Day Training/Habilitation Specialist | 09/15/2026 |
| SMITH, EMMA | WICHITA FALLS, TX | - | Professional Counselor | 09/24/2026 |
| SMITH, EMMA | XENIA, OH | - | Speech-Language Pathologist | 09/25/2026 |
| SMITH, ERICA | FAYETTEVILLE, AR | - | RBT | 09/25/2026 |
| SMITH, HARLEY | OWASSO, OK | - | RBT | 09/25/2026 |
| SMITH, HARMONY | AUSTIN, TX | LPC ASSOCIATE | Professional Counselor | 01/08/2025 |
| SMITH, HEAVEN | CHARLOTTE, NC | - | Clinical Social Worker | 09/22/2026 |
| SMITH, HOLLY | SAUGUS, CA | - | Counselor | 09/23/2026 |
| SMITH, JADE | COLUMBUS, GA | - | Mental Health Counselor | 09/23/2026 |
| SMITH, JANAY | AUSTELL, GA | - | RBT | 09/23/2026 |
| SMITH, JEDEDIAH | EASTHAMPTON, MA | - | Mental Health Counselor | 09/23/2026 |
| SMITH, JOHN | COLUMBUS, OH | - | Case Manager/Care Coordinator | 06/17/2022 |
| SMITH, JORDAN | TALLAHASSEE, FL | - | RBT | 10/13/2021 |
| SMITH, JOSIAH | BALTIMORE, MD | THERAPIST | Mental Health Counselor | 09/25/2026 |
| SMITH, JUDEA | PHILADELPHIA, PA | - | RBT | 09/03/2026 |
| SMITH, JULIE | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| SMITH, KENDRA | BROOKLYN, NY | - | Speech-Language Pathologist | 09/24/2026 |
| SMITH, KENDRA | FAYETTEVILLE, NC | - | RBT | 10/10/2018 |
| SMITH, KIMBERLY | WEST COLUMBIA, SC | ADC | Addiction (Substance Use Disorder) Counselor | 01/24/2020 |
| SMITH, KINDSEY | GLENDALE, AZ | BCBA | BCBA | 03/30/2020 |
| SMITH, KINSEY | CARMEL, IN | MA, LMHCA, NCC | Mental Health Counselor | 09/23/2026 |
| SMITH, KYLE | MILWAUKIE, OR | - | Case Manager/Care Coordinator | 07/09/2012 |
| SMITH, LATRIKA | SPRINGFIELD, LA | LCSW | Clinical Social Worker | 09/25/2026 |
| SMITH, LAUREN | PASADENA, CA | MA, LPCC | Professional Counselor | 10/08/2024 |
| SMITH, LONDYN | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| SMITH, LYNNE | PEACHTREE CORNERS, GA | LCSW | Clinical Social Worker | 02/03/2026 |
| SMITH, MACKENZIE | FARMINGTON HILLS, MI | - | RBT | 11/25/2024 |
| SMITH, MARIA | AUSTIN, TX | MA, LPC | Mental Health Counselor | 08/16/2011 |
| SMITH, MICHIAH | LEANDER, TX | - | RBT | 09/22/2026 |
| SMITH, MINDY | HAWKINSVILLE, GA | LMSW | Clinical Social Worker | 09/21/2026 |
| SMITH, MOLLY | BOSTON, MA | CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| SMITH, MONTRICIA | SOUTHFIELD, MI | - | RBT | 09/21/2026 |
| SMITH, NICOLE | SAN FRANCISCO, CA | LCSW | Specialist | 11/01/2021 |
| SMITH, OLIVIA | WILMINGTON, NC | - | RBT | 09/23/2026 |
| SMITH, RAJAIDA | GRAND RAPIDS, MI | - | RBT | 09/23/2026 |
| SMITH, REAGAN | OREM, UT | - | RBT | 09/21/2026 |
| SMITH, RONNY | MONROE, LA | LCSW | Clinical Social Worker | 03/10/2021 |
| SMITH, SADE | FRESNO, CA | - | Case Manager/Care Coordinator | 11/15/2023 |
| SMITH, SAMANTHA | OMAHA, NE | - | Speech-Language Pathologist | 08/26/2024 |
| SMITH, SARAH | VANCOUVER, WA | LMHC, MA | Mental Health Counselor | 08/19/2024 |
| SMITH, SHANNON | LAGRANGEVILLE, NY | - | Mental Health Counselor | 09/21/2026 |
| SMITH, SHELBY | SPRINGFIELD, MA | BS | Mental Health Counselor | 09/06/2023 |
| SMITH, TALEYSHA | AURORA, CO | LCSW, MSW | Clinical Social Worker | 09/04/2024 |
| SMITH, TARA | LAMAR, CO | - | Case Manager/Care Coordinator | 09/23/2026 |
| SMITH, TATIANA | RIDGEWOOD, NY | - | Clinical Social Worker | 09/24/2026 |
| SMITH, TEKOA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| SMITH, THERESE | LANSDOWNE, VA | LPC | Professional Counselor | 01/03/2022 |
| SMITH, TIFINI | HIRAM, GA | - | Professional Counselor | 08/05/2026 |
| SMITH, VERDIA | LITTLE ROCK, AR | - | RBT | 09/24/2026 |
| SMITHSON, AUSTIN | GAINESVILLE, FL | - | Mental Health Counselor | 09/21/2026 |
| SMJ LEARNING ACADEMYORG | CHICAGO, IL | - | BCBA | 08/08/2026 |
| SMOTHERGILL, CHEYENNE | EAST MORICHES, NY | - | Speech-Language Pathologist | 09/24/2026 |
| SMOTHERMAN, DEVON | MOUNT JULIET, TN | RBT | RBT | 09/24/2026 |
| SNAUFFER, STEPHANIE | KENT, OH | - | Case Manager/Care Coordinator | 04/10/2018 |
| SNELL, JESSICA | YORK, PA | - | Psychologist | 07/05/2024 |
| SNELLMAN, LYNDA | MILFORD, OH | - | Mental Health Counselor | 05/12/2006 |
| SNIDER, EMMA | KENNETT, MO | - | Case Manager/Care Coordinator | 09/23/2026 |
| SNIDER, SOPHIA | BROOKLYN, NY | - | Clinical Social Worker | 09/11/2024 |
| SNODGRASS, MEGAN | CHICAGO, IL | LPC | Professional Counselor | 11/10/2025 |
| SNOW, ATALIE | ELKVIEW, WV | MA, PLPC | Case Manager/Care Coordinator | 09/21/2026 |
| SNOW, KALY | WEST CHESTER, OH | SLP | Speech-Language Pathologist | 02/05/2024 |
| SNOW, OLIVIA | BROOKLYN, NY | LMHC | Mental Health Counselor | 01/20/2021 |
| SNOW, RACHEL | NATICK, MA | LICSW | Clinical Social Worker | 03/18/2022 |
| SNOW, THEOPHILUS | SPOTSYLVANIA, VA | LPC | Professional Counselor | 09/16/2026 |
| SNOWBALL, WILLIAM | WHITE BEAR LK, MN | - | Mental Health Counselor | 09/24/2026 |
| SNOWDEN, RIKKI | CENTRAL POINT, OR | CADC I, QMHA-R | Mental Health Counselor | 01/09/2023 |
| SOBALVARRO, EFRAIN | POMONA, CA | - | RBT | 09/22/2026 |
| SOBIECKI, MARLY | WILLIAMSVILLE, NY | MSW | Mental Health Counselor | 09/24/2026 |
| SOCIAL WORKERS ON DEMAND CONSULTANTSORG | HOUSTON, TX | - | Case Manager/Care Coordinator | 09/21/2026 |
| SOCIOLOGYWORKS AT LARGE, LLCORG | PHILADELPHIA, PA | - | Clinical Social Worker | 09/24/2026 |
| SOCKEY, TABITHA | LOVELL, WY | - | Case Manager/Care Coordinator | 01/20/2017 |
| SODANO, ROSE | HOWARD BEACH, NY | LMSW | Clinical Social Worker | 11/18/2008 |
| SOE, KAY | GILROY, CA | - | RBT | 09/21/2026 |
| SOEHNLIN, JEREMY | RED WING, MN | - | BCBA | 08/08/2024 |
| SOENS, SEAN | FORT LAUDERDALE, FL | MA | Psychologist | 06/05/2023 |
| SOFI RUBIN, EVELYN | HOLLYWOOD, FL | - | RBT | 09/23/2026 |
| SOFOLUKE, AYODEJI | WASHINGTON, DC | - | Case Manager/Care Coordinator | 06/28/2023 |
| SOHAM PULMONARY GROUP PAORG | SEBRING, FL | - | Specialist | 06/04/2007 |
| SOJKA, HEATHER | MELVILLE, NY | - | RBT | 09/25/2026 |
| SOLANO, KIMBERLY | CERRITOS, CA | ASW | Clinical Social Worker | 09/17/2026 |
| SOLANO, VIANEL | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| SOLAR, KIRSTY | GULFPORT, MS | - | RBT | 09/22/2026 |
| SOLIZ-CHAVEZ, ANDRES DE JESUS | MULESHOE, TX | MA, NCC, LMHC, LPC-A | Counselor | 10/07/2024 |
| SOLLER, BROOKE | MINNEAPOLIS, MN | - | Clinical Social Worker | 02/11/2021 |
| SOLO, MICHELLE | ROCHESTER HILLS, MI | LMSW | Clinical Social Worker | 12/14/2006 |
| SOLOMON, KELVIN | DAYTONA BEACH, FL | - | RBT | 09/21/2026 |
| SOLORIO, MARY | COALINGA, CA | - | Counselor | 09/21/2026 |
| SOLSTICE COUNSELING SERVICES, LLCORG | BOISE, ID | - | Mental Health Counselor | 01/05/2026 |
| SOM, ARNAB | SAN JOSE, CA | - | RBT | 09/22/2026 |
| SON, YEJIN | AUSTIN, TX | - | Assistant Behavior Analyst | 09/22/2026 |
| SONDERICKER, MICHAEL | DURHAM, NC | LCMHCA, LCASA | Addiction (Substance Use Disorder) Counselor | 08/06/2025 |
| SONI, DHRUV | TRENTON, NJ | - | RBT | 09/25/2026 |
| SOO HOO, HENRY | LONG BEACH, CA | - | RBT | 09/21/2026 |
| SORA PSYCHOTHERAPY, LLCORG | DENVILLE, NJ | - | Mental Health Counselor | 09/22/2026 |
| SORE, NEMATOU | BRONX, NY | - | BCBA | 09/23/2026 |
| SORENSEN, MARIA | MONTICELLO, MN | LICSW | Clinical Social Worker | 09/24/2026 |
| SORENSON, LYNN | MESA, AZ | LCSW | Clinical Social Worker | 07/09/2010 |
| SORIA MARQUEZ, YATZARY | MINNEAPOLIS, MN | - | RBT | 09/21/2026 |
| SORIANO, NATASHA | BRENTWOOD, CA | - | RBT | 09/22/2026 |
| SORKIN, MARY | EVERGREEN, CO | - | BCBA | 06/17/2026 |
| SOROKOVSKAYA, JESSICA | PUYALLUP, WA | - | Counselor | 09/22/2026 |
| SOSA, CHLOE | MARTINSBURG, WV | - | Mental Health Counselor | 10/03/2025 |
| SOTELO, MYRNA | WEBSTER, TX | - | RBT | 09/22/2026 |
| SOTO, DOLORES | TORRANCE, CA | - | RBT | 09/21/2026 |
| SOTO, ELENA | SOUTH BEND, IN | RBT | RBT | 09/21/2026 |
| SOTO, MADELYN | ALAMOGORDO, NM | - | RBT | 09/22/2026 |
| SOTO, MARICARMEN | CUTLER BAY, FL | LCSW | Clinical Social Worker | 04/05/2023 |
| SOTO, NINA | MADISON, WI | - | Mental Health Counselor | 09/24/2026 |
| SOTO, VICTORIA | STATEN ISLAND, NY | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| SOTOYE, TENIOLA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| SOUDERS, CARLEIGH | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| SOUKUP, TADIA | LINCOLN, NE | PLMHP | Mental Health Counselor | 09/23/2026 |
| SOUL DISCOVERY MENTAL HEALTH COUNSELING SERVICES PCORG | MALVERNE, NY | - | Mental Health Counselor | 07/24/2020 |
| SOUND DECISIONS LLCORG | SPRING, TX | - | Mental Health Counselor | 05/20/2025 |
| SOUND MIND THERAPY, LLCORG | AMHERST, MA | - | Clinical Social Worker | 09/24/2026 |
| SOUTHARD, HEIDI | STEVENSVILLE, MI | MA, CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| SOUTHEAST MISSOURI HEALTH NETWORKORG | BENTON, MO | - | Case Management Agency | 07/20/2005 |
| SOUTHERN BRIDGE COUNSELING, LLCORG | HAWKINSVILLE, GA | - | Community/Behavioral Health Agency | 03/18/2016 |
| SOUTHERN BRIDGE INCORG | WARNER ROBINS, GA | - | Mental Health Counselor | 07/20/2016 |
| SOUTHERN, REBEKAH | GALAX, VA | LPC | Professional Counselor | 09/22/2026 |
| SOUTHWEST MICHIGAN RECOVERY CENTERORG | KALAMAZOO, MI | - | Community/Behavioral Health Agency | 09/22/2026 |
| SOUTO PILOTOS, YENIA | HIALEAH, FL | - | RBT | 05/06/2020 |
| SOUZA, KAIA | TAUNTON, MA | - | Mental Health Counselor | 09/23/2026 |
| SOUZA, MONIQUE | CENTRAL ISLIP, NY | - | Mental Health Counselor | 05/04/2026 |
| SOUZA, VIISHA | EVERETT, WA | - | Counselor | 09/21/2026 |
| SOWERS-COLLISON, SARA | MIDDLETOWN, OH | M.S.W., L.I.S.W. | Clinical Social Worker | 09/11/2006 |
| SOWLES, MIKAYLAH | SAGINAW, MI | - | RBT | 09/24/2026 |
| SPAKOWSKI-LANE, TANYA | KELLER, TX | - | Professional Counselor | 09/22/2026 |
| SPANN, JIMMY | WEST COLUMBIA, SC | - | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| SPARK CHANGE WELLNESS CENTER, LLCORG | GAMBRILLS, MD | - | Mental Health Counselor | 09/22/2026 |
| SPARKLE INITIATIVEORG | KENNEWICK, WA | - | Community/Behavioral Health Agency | 09/21/2026 |
| SPARROW, SYLVIA | OREGON CITY, OR | - | Clinical Social Worker | 03/13/2018 |
| SPAULDING, ELANAH | BROOKLYN, NY | - | RBT | 09/23/2026 |
| SPEARMAN, DAMONTAY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| SPECHT, AMY | NORFOLK, NE | LIMHP | Mental Health Counselor | 01/09/2023 |
| SPECTHRIVE WELLNESS & BEHAVIORAL HEALTHORG | BROOKLYN PARK, MN | - | Professional Counselor | 11/29/2025 |
| SPECTRUM DISCOVERY CENTER INCORG | MIAMI, FL | - | Mental Health Counselor | 05/29/2025 |
| SPEECH WITH ZOE PLLCORG | CHICAGO, IL | - | Speech-Language Pathologist | 09/23/2026 |
| SPEER, BRINLEY | JACKSON, MI | - | RBT | 09/22/2026 |
| SPENCE, JOQUINA | FUQUAY VARINA, NC | - | RBT | 09/24/2026 |
| SPENCER, ANGELICA | FORT WAYNE, IN | - | RBT | 09/23/2026 |
| SPENCER, HEATHER | ERIE, PA | LCSW | Clinical Social Worker | 09/26/2026 |
| SPENCER, JOLINE | KENT, WA | - | RBT | 09/23/2026 |
| SPENCER, KEITH | RICHMOND, VA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| SPENCER, MAGEN | NENANA, AK | LCSW | Clinical Social Worker | 06/25/2020 |
| SPENSER, SHELBY | EL SEGUNDO, CA | - | BCBA | 09/21/2026 |
| SPERANZA RANCH LLCORG | WOODLAND PARK, CO | - | Addiction (Substance Use Disorder) Counselor | 04/02/2020 |
| SPERGIN, CARLEIGH | ATHENS, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| SPERTUS THERAPY PLLCORG | CHICAGO, IL | - | Clinical Social Worker | 09/18/2026 |
| SPERTUS, DEBORAH | CHICAGO, IL | LCSW | Clinical Social Worker | 08/22/2022 |
| SPINA, MARGARET | CLEVELAND, OH | CARE COORDINATOR/MH | Mental Health Counselor | 09/23/2026 |
| SPINNER, WILMA | NEW YORK, NY | - | Specialist | 12/29/2006 |
| SPIRAL TIDE THERAPY LLCORG | PORTLAND, OR | - | Clinical Social Worker | 08/12/2026 |
| SPLATTSTOESSER, SILVIA FRANCESCA | FARMINGTON, UT | CMHC | Mental Health Counselor | 04/01/2024 |
| SPOKUS, LEANN | EVERETT, WA | MSW, MHP, CMHS | Clinical Social Worker | 08/15/2016 |
| SPOONER, KALLIE | OMAHA, NE | - | Mental Health Counselor | 08/22/2020 |
| SPOUND, SARAH | BOSTON, MA | - | Clinical Social Worker | 03/16/2021 |
| SPREAD YOUR WINGSORG | CHESTER, VA | - | Community/Behavioral Health Agency | 04/19/2017 |
| SPRING EOP P.C.ORG | COLORADO SPRINGS, CO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| SPRING EOP P.C.ORG | COLORADO SPRINGS, CO | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| SPRING, HANNAH | FORT COLLINS, CO | - | Professional Counselor | 06/07/2024 |
| SPROUT COUNSELING AND CONSULTATIONS, PLLCORG | SPRINGFIELD, IL | - | Mental Health Counselor | 09/24/2026 |
| SPURGEON, BARBARA | MARION, IL | MSW | Clinical Social Worker | 09/11/2009 |
| SPYRES, LINDA | RED BLUFF, CA | L.C.S.W. AND C.A.T.S | Addiction (Substance Use Disorder) Counselor | 02/15/2008 |
| SQ1 SOLUTIONS LLCORG | FISHERS, IN | - | Community/Behavioral Health Agency | 09/24/2026 |
| SQUALLS, SELAH | ASHBURN, VA | - | Mental Health Counselor | 09/24/2026 |
| SQUARE ONE BEHAVIORAL SERVICES INC.ORG | ROYAL PALM BEACH, FL | - | BCBA | 05/22/2018 |
| ST LUKES ROOSEVELT HOSPITAL CENTERORG | NEW YORK, NY | - | Case Management Agency | 12/28/2006 |
| ST OF MT DOCORG | DEER LODGE, MT | - | Clinic/Center | 08/25/2025 |
| ST-PIERRE, MICKENSON | PLYMOUTH, MA | - | RBT | 09/24/2026 |
| ST. CHARLES COUNTY AMBULANCE DISTRICTORG | SAINT PETERS, MO | - | Community/Behavioral Health Agency | 09/22/2026 |
| ST. JOHN, BRITTANY | WILMINGTON, NC | MSW, LCSW | Clinical Social Worker | 03/22/2023 |
| ST. MARIE, AMBER | OKLAHOMA CITY, OK | M. ED. | Mental Health Counselor | 03/11/2015 |
| ST. PETER'S HEALTHORG | HELENA, MT | - | Case Management Agency | 04/20/2006 |
| STABILE, SHELBY | EAST LANSING, MI | - | RBT | 09/25/2026 |
| STABLE GAINS MENTAL HEALTH SERVICE LLCORG | PLYMOUTH, IN | - | Clinical Social Worker | 02/17/2025 |
| STACHOVIAK, JULIE | MADISON, WI | MSW, APSW | Clinical Social Worker | 09/24/2026 |
| STACK, MICHELLE | APO, AE | PH.D. | Psychologist | 01/06/2012 |
| STACY, VIVIANNA | DEKALB, IL | - | Mental Health Counselor | 09/21/2026 |
| STAFFORD, MICHAEL | GROVEPORT, OH | PRS | Addiction (Substance Use Disorder) Counselor | 01/23/2025 |
| STAFFORD, PAMELA | COLUMBUS, NE | - | RBT | 09/23/2026 |
| STAFFORD, ROLONDA | SOUTHFIELD, MI | - | RBT | 09/22/2026 |
| STAGG, JOANNA | SEATTLE, WA | MA, PSYD | Psychologist | 08/02/2010 |
| STAGGS, KATHERINE | INDIANAPOLIS, IN | - | RBT | 09/24/2026 |
| STALLINGS, JAMIE | SAN JACINTO, CA | LCSW | Clinical Social Worker | 04/26/2016 |
| STALLSMITH, ELIZABETH | KOKOMO, IN | BCBA | BCBA | 01/16/2025 |
| STANAGE, CHLOE | GRAND COULEE, WA | - | Mental Health Counselor | 08/23/2024 |
| STANEK LUCY, CAROLYN | SILVER SPRING, MD | LGPC | Professional Counselor | 07/22/2025 |
| STANINGER, ASHLEY | ROSEBURG, OR | - | Mental Health Counselor | 10/15/2024 |
| STANISLAUS COUNTY BEHAVIORAL HEALTH AND RECOVERY SERVICESORG | MODESTO, CA | - | Community/Behavioral Health Agency | 12/17/2018 |
| STAPLES, CHARITY | KILLEEN, TX | LCSW | Clinical Social Worker | 09/21/2026 |
| STAPLETON, RAVEN | LOVELAND, CO | LPC | Professional Counselor | 12/27/2023 |
| STARK RECOVERY ASSOCIATES, LLCORG | AKRON, OH | - | Community/Behavioral Health Agency | 04/21/2022 |
| STARKS, KAMIA | CHICAGO, IL | - | Clinical Social Worker | 06/06/2025 |
| STARR, GABRIELLE | MILFORD, DE | - | RBT | 09/23/2026 |
| STATEN, KIMBERLY | FORT WORTH, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/23/2026 |
| STAY 4 LIFEORG | GREENVILLE, NC | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| STAYROOK, LINDSAY | YORK, PA | - | Community/Behavioral Health Agency | 09/24/2026 |
| STEADHAM-WILLIAMS, EMILY | GULF SHORES, AL | - | BCBA | 04/12/2022 |
| STEAMBOAT HEALTHCARE LLCORG | GILLETTE, WY | - | Case Management Agency | 07/29/2025 |
| STEARNS, ALEAH | SAINT CLOUD, MN | - | RBT | 09/22/2026 |
| STEDMAN, THIDAR | SAN DIEGO, CA | LCSW | Clinical Social Worker | 03/22/2007 |
| STEELE, ASHLEY | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| STEEN, AMBER | OZARK, AL | LMSW | Clinical Social Worker | 09/21/2026 |
| STEFFEN, RYLEIGH | VESTAVIA, AL | - | RBT | 09/22/2026 |
| STEHLING, JOSEPH | PASADENA, CA | - | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| STEIN, HANNAH | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| STEINER, ANISTYN | NILES, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| STEINMETZ, HAYLEY | BLAND, MO | LPC | Counselor | 04/26/2018 |
| STEINMETZ, ILANA | NEW YORK, NY | MHC-LP | Mental Health Counselor | 09/22/2026 |
| STEKLOF, JESSICA | ROCHESTER, NY | - | Specialist | 09/22/2026 |
| STENDER, STACEY | MEDINA, OH | LPC | Professional Counselor | 09/01/2025 |
| STENSRUD, RACHAEL | GRINNELL, IA | - | Mental Health Counselor | 08/14/2015 |
| STEPHANIE VAUGHN COUNSELING PLLCORG | DECATUR, IL | - | Professional Counselor | 09/21/2026 |
| STEPHANO, ELIZABETH | HATFIELD, PA | LCSW | Mental Health Counselor | 02/18/2016 |
| STEPHANZ, GERALD | PROVO, UT | MD | Case Management Agency | 07/01/2006 |
| STEPHEN F. AUSTIN COMMUNITY HEALTH CENTER, INC.ORG | ALVIN, TX | - | BCBA | 05/15/2008 |
| STEPHENS, ANDALYN | DEERFIELD BEACH, FL | - | RBT | 09/24/2026 |
| STEPHENS, JILL | VAN NUYS, CA | - | BCBA | 09/24/2026 |
| STEPHENS, MAKEL | AUSTIN, TX | - | RBT | 09/25/2026 |
| STEPHENSON, HAYDEN | LAS VEGAS, NV | - | RBT | 09/25/2026 |
| STEPHENSON, SIAELYANNA | LIVERMORE FALLS, ME | LCPCC | Professional Counselor | 09/22/2026 |
| STEPHENSON, TIANNA | PLYMOUTH, MA | - | Speech-Language Pathologist | 03/19/2024 |
| STEPS, LLCORG | PIKESVILLE, MD | - | BCBA | 01/04/2016 |
| STERLING ABA LLCORG | MANCHESTER, NH | - | BCBA | 09/22/2026 |
| STERLING, BRITTANY | BARBOURSVILLE, WV | MSW | Counselor | 10/03/2022 |
| STERRY, NATHAN | LANCASTER, PA | LSW | Counselor | 09/21/2026 |
| STEVENS, HEATHER | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| STEVENS, JOSHUA | RIVERSIDE, CA | - | Mental Health Counselor | 09/22/2026 |
| STEVENS, MICHAEL | POCATELLO, ID | LCSW | Clinical Social Worker | 09/16/2006 |
| STEVENS, PATRICK | WESTAMPTON, NJ | - | Mental Health Counselor | 09/22/2026 |
| STEVENSON-ESTOCK, CAIRA | VIRGINIA BEACH, VA | - | RBT | 05/28/2026 |
| STEVENSON, ELIZABETH | JAMAICA PLAIN, MA | - | Clinical Social Worker | 09/22/2026 |
| STEVENSON, KRYSTAL | GREENSBORO, NC | MSW | Clinical Social Worker | 04/29/2026 |
| STEWARD, ANNA | AUSTELL, GA | - | RBT | 09/23/2026 |
| STEWART AGEE, LAYLA | OMAHA, NE | - | RBT | 08/18/2026 |
| STEWART, DEJA | PHOENIX, AZ | LCSW | Clinical Social Worker | 02/09/2026 |
| STEWART, ERICA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| STEWART, GALENA | LYNNWOOD, WA | - | RBT | 09/24/2026 |
| STEWART, HANNAH | WHEELING, IL | LCSW | Clinical Social Worker | 04/09/2025 |
| STEWART, LATICA | SOUTHFIELD, MI | - | RBT | 09/21/2026 |
| STEWART, LAURA | WILMINGTON, DE | - | RBT | 09/24/2026 |
| STEWART, SAMM | WOODINVILLE, WA | - | Counselor | 09/03/2025 |
| STEWART, THOMAS | CHARLESTON, WV | - | Case Manager/Care Coordinator | 09/21/2026 |
| STICH, DESE RAY | STERLING, CO | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| STIEFER, DARCY | TYLER, TX | - | Specialist | 09/21/2026 |
| STIGGINS, MARISSA | ST GEORGE, UT | M.S. CCC | Speech-Language Pathologist | 09/24/2026 |
| STILL, EMERSON | PLYMOUTH, MA | - | Mental Health Counselor | 09/22/2026 |
| STILLNESS POINT HEALING LLCORG | PHOENIX, AZ | - | Psychologist | 12/28/2020 |
| STILLWATERS RELATIONAL AND BEHAVIORAL HEALTHORG | WASHINGTON TOWNSHIP, OH | - | Mental Health Counselor | 07/08/2025 |
| STILLWELL, BARBARA | SALINAS, CA | - | Speech-Language Pathologist | 09/22/2026 |
| STITT, CLAUDIA | MESQUITE, TX | LPC | Professional Counselor | 09/21/2026 |
| STITT, JOHN | SKOKIE, IL | PSYD | Psychologist | 09/22/2026 |
| STITT, TEIRA | CARTERSVILLE, GA | - | Mental Health Counselor | 09/21/2026 |
| STOCKTON, NATALIE | CHICO, CA | LCSW | Clinical Social Worker | 02/16/2016 |
| STOFF, GEOFFREY | LUTZ, FL | - | RBT | 09/24/2026 |
| STOFLE, GARY | COLUMBUS, OH | LISW-S, LICDC | Addiction (Substance Use Disorder) Counselor | 11/07/2006 |
| STOGLIN, JAAMIKAH | WACO, TX | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| STOJANOV, LILIANA | MEDFORD, OR | - | Clinical Social Worker | 09/24/2026 |
| STOKER, LAURA | FAIRVIEW, UT | ACMHC | Mental Health Counselor | 09/24/2026 |
| STOKES, CHELSEA | OCALA, FL | - | RBT | 09/14/2026 |
| STOKES, MARIA | JEFFERSON CITY, MO | MED, LPC | Professional Counselor | 09/03/2008 |
| STOLTZFUS, TAYLOR | RALEIGH, NC | CCC SLP | Speech-Language Pathologist | 03/27/2023 |
| STOLZ, ALISSA | SCOTTSDALE, AZ | - | Speech-Language Pathologist | 06/21/2016 |
| STONE, CARLEY | FARMINGTON HILLS, MI | - | RBT | 02/06/2026 |
| STONE, JAMIE | FARMINGTON HILLS, MI | - | RBT | 09/26/2026 |
| STONE, JOHN | ST PETERSBURG, FL | MSW | Clinical Social Worker | 12/17/2015 |
| STONE, LYNN | ST PETERSBURG, FL | LCSW | Clinical Social Worker | 08/29/2007 |
| STONE, OLIVIA | VICTORVILLE, CA | LCSW | Clinical Social Worker | 09/05/2026 |
| STONEBRIDGE RECOVERY,LLCORG | GAHANNA, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| STORMBRINGER, BELLA | PLYMOUTH, MI | - | Psychologist | 08/20/2026 |
| STOUGH, KOREN | ST GEORGE, UT | - | RBT | 09/23/2026 |
| STOVALL, TIARA | HERRIN, IL | - | RBT | 09/24/2026 |
| STOVER, MADELEINE | COLUMBUS, OH | - | Mental Health Counselor | 09/21/2026 |
| STRADER, MELISSA | GROVE CITY, OH | LISW | Clinical Social Worker | 03/12/2022 |
| STRADINGER, TAYLOR | RAMSEY, MN | - | Speech-Language Pathologist | 09/21/2026 |
| STRAFACCI, BRUNO | HERRIMAN, UT | ACMHC | Mental Health Counselor | 05/28/2022 |
| STRAFFORD, OLIVIA | MONROVIA, CA | - | RBT | 09/22/2026 |
| STRAHLEY, MADELYNN | DUBLIN, OH | - | Case Manager/Care Coordinator | 06/02/2023 |
| STRAHORN, PATRICK | FRANKFORT, IL | - | Mental Health Counselor | 09/24/2026 |
| STRAND, MEGAN | BROOKFIELD, CT | - | BCBA | 09/25/2026 |
| STRATE, KELSEY | CHELSEA, MI | - | Psychologist | 09/24/2026 |
| STRATEGIC THERAPY ASSOCIATES, INC.ORG | WYTHEVILLE, VA | - | Community/Behavioral Health Agency | 09/24/2026 |
| STRATEGY TRANSITIONSORG | CORONA, CA | - | Mental Health Counselor | 09/22/2026 |
| STRAUGHN, KIANA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| STRAUSSNER, SARINA | NEW YORK, NY | LMSW | Clinical Social Worker | 09/21/2026 |
| STREET, ELIZABETH | ALTON, IL | MA,LPC | Professional Counselor | 01/21/2026 |
| STREETER, ALEXANDER | MANKATO, MN | - | RBT | 09/21/2026 |
| STREETT, LUCY | OAKLAND, CA | - | Mental Health Counselor | 09/21/2026 |
| STRIBLING, ASHLEY | AUSTIN, TX | LCSW-S, LCDC | Clinical Social Worker | 02/26/2019 |
| STRICKLAND, CINDIE | LITTLETON, CO | CPFS | Mental Health Counselor | 09/21/2026 |
| STRICKLAND, TRULI | MOUNTAIN BRK, AL | - | Mental Health Counselor | 09/21/2026 |
| STRITTMATTER, TESSA | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| STRIVING, HOPE | KENT, OH | LPC | Professional Counselor | 11/08/2017 |
| STROMBOM, WYATT | AMHERST, WI | - | Mental Health Counselor | 09/16/2026 |
| STRONG MYNDS ORG INCORG | GAITHERSBURG, MD | - | Mental Health Counselor | 04/07/2023 |
| STRONG START FAMILY SERVICESORG | MILWAUKEE, WI | - | Case Management Agency | 09/23/2026 |
| STRONG, ASHLEY | HUNTSVILLE, AL | LMSW | Professional Counselor | 09/22/2026 |
| STROPES, KAITLIN | SEATTLE, WA | - | Counselor | 09/21/2026 |
| STROUD, CARLEIGH | MONROE, NC | - | Mental Health Counselor | 09/23/2026 |
| STROUD, ELIZABETH | MECHANICSVILLE, VA | M.ED. CCC-SLP | Speech-Language Pathologist | 10/29/2008 |
| STRUBLE, REBECCA | ALLEGAN, MI | - | Speech-Language Pathologist | 09/24/2026 |
| STRUNK, RACHEL | CINCINNATI, OH | LISW-S, LICDC | Addiction (Substance Use Disorder) Counselor | 11/25/2015 |
| STRUTZ, ASHLEY | FRIDAY HARBOR, WA | LMHCA | Mental Health Counselor | 08/14/2018 |
| STRYJEWSKI, LIESL | TOWSON, MD | LCSW-C | Clinical Social Worker | 02/10/2020 |
| STRYKER, ELIZABETH | SEATTLE, WA | LMHCA | RBT | 02/04/2020 |
| STUART, ALANI | EUGENE, OR | - | Counselor | 09/17/2015 |
| STUART, ALYSSA | EAU CLAIRE, WI | - | Professional Counselor | 09/25/2024 |
| STUART, LEAH | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| STUART, TAYLOR | AKRON, OH | LPCC | Professional Counselor | 01/30/2023 |
| STUART, WILLIAM | OKLAHOMA CITY, OK | - | RBT | 07/14/2025 |
| STUBBE, CONNOR | VANCOUVER, WA | - | Counselor | 06/02/2025 |
| STUBBS, CAROLINE | BRADENTON, FL | - | Speech-Language Pathologist | 09/21/2026 |
| STUBBS, MARLYN | HAWKINSVILLE, GA | - | Mental Health Counselor | 04/10/2025 |
| STUCKEY, KYRSTEN | FARMINGTON HILLS, MI | LLMSW | Clinical Social Worker | 09/23/2026 |
| STULTZ, MEGAN | MARYSVILLE, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| STUMP, SAMANTHA | YOUNGSTOWN, OH | CPST-QMHS | Case Manager/Care Coordinator | 07/25/2023 |
| STURGILL, KATRINA | CLINTWOOD, VA | LPCC | Professional Counselor | 06/03/2015 |
| STURKEY, MACY | NEWTOWN, PA | LBS | BCBA | 09/22/2026 |
| STUVLAND, JANELLE | PORTLAND, OR | LPC | Mental Health Counselor | 04/08/2019 |
| SU, YA | RENO, NV | - | RBT | 09/25/2026 |
| SUASTE, DESTINY | POMONA, CA | - | RBT | 09/21/2026 |
| SUBIN, CAROLYN | BURLINGTON, VT | LCSWR | Clinical Social Worker | 01/24/2008 |
| SUDA, KOKORO | SAN FRANCISCO, CA | - | Counselor | 08/26/2024 |
| SUEIRAS, ANNABELLA | COLUMBIA, MD | - | RBT | 07/06/2026 |
| SULLIVAN-ROCHA, CORWIN | TRACY, CA | - | RBT | 09/22/2026 |
| SULLIVAN-STRAIN, LAUREN | GAHANNA, OH | - | Clinical Social Worker | 09/05/2019 |
| SULLIVAN, ASHLEY | POPLAR BLUFF, MO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| SULLIVAN, CHARLIE | LORAIN, OH | - | Case Manager/Care Coordinator | 09/24/2026 |
| SULLIVAN, CRISTINA | MEQUON, WI | PHD | Psychologist | 09/22/2020 |
| SULLIVAN, ELIZABETH | EAST LANSING, MI | - | Speech-Language Pathologist | 09/21/2026 |
| SULLIVAN, LISA | ANNAPOLIS, MD | LMSW | Mental Health Counselor | 09/26/2026 |
| SULLIVAN, MADELINE | FREDERICK, MD | - | BCBA | 07/23/2026 |
| SULLIVAN, MARLON | BALTIMORE, MD | - | RBT | 09/21/2026 |
| SULYA, CAMERON | CHAPEL HILL, NC | - | Clinical Social Worker | 09/12/2026 |
| SUME, SHARMIN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| SUMMERS, HANNAH | STATESVILLE, NC | MS, CCC-SLP | Speech-Language Pathologist | 06/09/2020 |
| SUMNER, ALLISON | LOUISVILLE, KY | M.S., BCBA, LBA | BCBA | 04/01/2015 |
| SUN BAY ABAORG | REDWOOD CITY, CA | - | BCBA | 09/23/2026 |
| SUNFLOWER DEVELOPMENTAL SERVICES LLCORG | MISSION HILLS, CA | - | BCBA | 09/22/2026 |
| SUNGA, MATT | PACHECO, CA | - | RBT | 09/24/2026 |
| SUNNYSIDE PSYCHOLOGY LLCORG | PHILADELPHIA, PA | - | Psychologist | 09/24/2026 |
| SUNRISE BEHAVIOR SERVICES OF ORANGE COUNTY, LLCORG | LADERA RANCH, CA | - | BCBA | 09/23/2026 |
| SUNRISE SPEECH THERAPY LLCORG | BRODHEAD, WI | - | Speech-Language Pathologist | 09/25/2026 |
| SUPPLE, MEGAN | CARLSBAD, CA | - | Mental Health Counselor | 03/01/2024 |
| SUPREME HOPE 4 KIDDOS CORPORG | MIAMI, FL | - | BCBA | 09/23/2026 |
| SURGICAL ASSISTING OF BROWARD LLCORG | NASHVILLE, TN | - | Clinic/Center | 09/21/2026 |
| SURVIVAL MODE THERAPY LLCORG | WOODSTOCK, GA | - | Clinical Social Worker | 09/22/2026 |
| SUSAETA, RACHEAL | WEST JORDAN, UT | - | Clinical Social Worker | 12/01/2022 |
| SUSCHENA, ALICIA | COLORADO SPRINGS, CO | CCC-SLP | Speech-Language Pathologist | 04/16/2024 |
| SUSK, CHRISTINE | DES MOINES, IA | - | BCBA | 09/22/2026 |
| SUTER, NICOLE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| SUTHERLAND, LINDSEY | BRIGHTON, CO | LPC | Professional Counselor | 06/15/2011 |
| SUTJIPTO, SARAH | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| SUTPHIN, CHRISTOPHER | YOUNGSTOWN, OH | - | RBT | 10/09/2024 |
| SUTTER, ANNE | DORR, MI | - | Speech-Language Pathologist | 08/20/2020 |
| SUTTLES, KATELYN | LAS CRUCES, NM | - | RBT | 11/05/2024 |
| SUTTON, ALISA | CONCORD, CA | - | BCBA | 09/23/2026 |
| SUTTON, JACQUELINE | COLUMBUS, OH | - | Counselor | 09/23/2026 |
| SUZUKI, ERINA | LOS ALTOS, CA | - | RBT | 09/21/2026 |
| SWANN, MADISON | CANTON, OH | - | Counselor | 09/22/2026 |
| SWANSON ANDRASIKOVA, KARINA | ASHEVILLE, NC | LCSWA | Clinical Social Worker | 02/05/2025 |
| SWANSON, CASEY | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| SWANSON, DANA | ROSEMOUNT, MN | M.S. | Speech-Language Pathologist | 08/22/2017 |
| SWANSON, RANDI | MINOT, ND | - | Case Manager/Care Coordinator | 09/23/2026 |
| SWARTZ, JUSTIN | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| SWARTZENTRUBER, JAMIE | SPRING HILL, TN | - | RBT | 10/12/2020 |
| SWEEN, EMILY | MANCHESTER, NH | LCMHC | Mental Health Counselor | 05/17/2016 |
| SWEET SERENITY COUNSELING SERVICESORG | MARMORA, NJ | - | Clinical Social Worker | 09/21/2026 |
| SWEETMAN, DANIELLE | OCALA, FL | - | RBT | 08/28/2026 |
| SWEETNAM, MEARA | MADISON, WI | - | Case Manager/Care Coordinator | 09/24/2026 |
| SWEETWATER AURORA OPCO LLCORG | AURORA, CO | - | Clinic/Center | 09/26/2017 |
| SWEITZER, NORAH | MIDDLEBURG, FL | - | RBT | 09/21/2026 |
| SWENSON, CYNDIE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| SWENSON, THOMAS | CHILTON, WI | - | Clinical Social Worker | 02/12/2007 |
| SWERDIN, SARAH | NEW YORK, NY | PSYD | Psychologist | 09/22/2026 |
| SWICK, ADRIANA | WESTFIELD, IN | - | RBT | 07/16/2025 |
| SWIECKI, KIMBERLY | CINCINNATI, OH | MSW, LISW | Clinical Social Worker | 01/15/2019 |
| SWIFT, STEFANIE | FORT MYERS, FL | LMHC | Professional Counselor | 08/07/2016 |
| SWINEY, ISABELLA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| SYED, UZMA | WILLOWBROOK, IL | M.D | Specialist | 02/26/2007 |
| SYKES, ABIGAIL | CHAMBERSBURG, PA | - | Speech-Language Pathologist | 01/25/2018 |
| SYKES, MARGARET | SACRAMENTO, CA | - | RBT | 09/24/2026 |
| SYLVESTER, MARSHAE | CHICAGO, IL | - | Professional Counselor | 09/24/2026 |
| SYMES, REBECCA | LA CROSSE, WI | - | BCBA | 06/02/2021 |
| SYMONS, MEGHAN | BURTON, MI | - | RBT | 09/23/2026 |
| SYNERGY COUNSELING SERVICES, LLCORG | SHALLOTTE, NC | - | Clinical Social Worker | 07/26/2011 |
| SYNERGY TRANSITIONAL HOUSING INC.ORG | MESA, AZ | - | Case Management Agency | 01/22/2026 |
| SYNOWIEC, EMILY | PITTSBURGH, PA | - | RBT | 09/22/2026 |
| SYPHER COUNSELING, PLLCORG | DENVER, CO | - | Clinical Social Worker | 09/21/2026 |
| SYVAK, DIANA | SOUTHFIELD, MI | - | RBT | 09/23/2026 |
| SZAFRAN, ARIELLE | BEDFORD, MA | - | Mental Health Counselor | 08/23/2021 |
| SZULC, JAMIE | BEXLEY, OH | - | Speech-Language Pathologist | 09/22/2026 |
| SZYKULA, AUSTIN | CONCORD, NC | - | RBT | 09/25/2026 |
| TACHET, SADIE | HENDERSON, NV | - | RBT | 09/21/2026 |
| TACKETT, AMANDA | PORTSMOUTH, OH | - | Case Manager/Care Coordinator | 07/29/2020 |
| TAFOYA-TORREZ, GABRIELLA | ALBUQUERQUE, NM | LPCC | Professional Counselor | 10/11/2019 |
| TAGGART, SCOTT | SAN DIEGO, CA | LMFT | Mental Health Counselor | 12/14/2006 |
| TAHAN, MARGARET | MARTINEZ, CA | LCSW | Clinical Social Worker | 03/16/2006 |
| TAHERI, JESSICA | SACRAMENTO, CA | - | RBT | 01/24/2023 |
| TAI, VERONICA | SAN FRANCISCO, CA | MSW, LCSW | Clinical Social Worker | 02/11/2016 |
| TAILORED FOR YOU BEHAVIORAL & MENTAL HEALTH SERVICES, LLCORG | OWINGS MILLS, MD | - | Clinical Social Worker | 06/29/2026 |
| TAISACAN-VILANTE, ALYSSA | VANCOUVER, WA | - | RBT | 09/24/2026 |
| TAIT, KEVIN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| TAKACE, MEGAN | VERMONTVILLE, MI | LMSW | Clinical Social Worker | 05/01/2023 |
| TAKAMORI, TYEISHA | MILILANI, HI | - | RBT | 09/26/2026 |
| TAKU, MIRANDA | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/26/2026 |
| TALAMANTES, ALANA | LAKE FOREST, CA | - | RBT | 09/23/2026 |
| TALAMANTES, ALLIYAH | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| TALAVERA, IVETH | LAS VEGAS, NV | - | RBT | 09/23/2026 |
| TALBERT-BRUST, ERIN | ONTARIO, CA | - | BCBA | 08/13/2026 |
| TALBOT, KATHRYN | ELLICOTT CITY, MD | M.ED., CCC-SLP | Speech-Language Pathologist | 10/29/2011 |
| TALLEY, BROOKELYN | PUEBLO, CO | - | RBT | 09/21/2026 |
| TALLEY, DAVID | BEACHWOOD, OH | - | Counselor | 09/23/2026 |
| TALU, IPEK | SHELTON, CT | MSED | Mental Health Counselor | 09/25/2026 |
| TALWAR, SHARVIKA | SAN JOSE, CA | - | Professional Counselor | 09/09/2026 |
| TAM, ARIEL | FREMONT, CA | - | RBT | 09/22/2026 |
| TAM, TANESHA | RANCHO CUCAMONGA, CA | - | RBT | 09/22/2026 |
| TAMAYO OCHOA, ALEXANDRA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| TAMAYO, JENNIFER | CHICAGO, IL | - | Case Manager/Care Coordinator | 09/22/2026 |
| TAMBWE, CHRISTVIE | KERNERSVILLE, NC | - | RBT | 09/25/2026 |
| TAMJIDI, FARNAZ | AGOURA HILLS, CA | - | RBT | 09/22/2026 |
| TAN, ANN RODETTE | CHULA VISTA, CA | - | RBT | 09/21/2026 |
| TAN, ISABEL | RIVERSIDE, CA | - | RBT | 09/24/2026 |
| TANDA, ELISSA | LOVELAND, CO | MA | Counselor | 09/19/2013 |
| TANG-CENTENO, JULIANNA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| TANGULI, SHEKINAH | MUSTANG, OK | - | RBT | 09/21/2026 |
| TANNER, KATHERINE | IRMO, SC | - | RBT | 09/25/2026 |
| TANNER, MACKENZIE | BRIGHTON, MI | PH.D. | Psychologist | 06/13/2022 |
| TANNER, MADISON | SPANISH FORK, UT | - | RBT | 09/22/2026 |
| TANNER, RHONDA | DACULA, GA | APC | Professional Counselor | 09/21/2026 |
| TANNER, RIKKI | JAMISON, PA | - | Counselor | 09/24/2026 |
| TANNER, VIVIAN | WASHINGTON, DC | - | Mental Health Counselor | 09/22/2026 |
| TANWAR, PRINCI | NEWTON, MA | - | RBT | 09/22/2026 |
| TANYA, ERNESTINE LAHZI | WASHINGTON, DC | - | Case Manager/Care Coordinator | 09/22/2026 |
| TAPAS YOGA SHALA INCORG | ROCK ISLAND, IL | - | Clinical Social Worker | 12/14/2017 |
| TAPER, ZOE | BREA, CA | - | RBT | 09/01/2026 |
| TAPIA VASQUEZ, EMILY | GRAPEVINE, TX | RBT-26-505871 | RBT | 09/22/2026 |
| TAPIA-ARRIAGA, EDUARDO | SANTA FE SPRINGS, CA | - | RBT | 09/21/2026 |
| TAPIA, DIANA | WHITE PLAINS, NY | LMHC | Mental Health Counselor | 06/04/2018 |
| TAPIA, ELYSSA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| TARIQ, DANYA | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| TARNOWSKI, JENA | EASLEY, SC | - | BCBA | 09/23/2026 |
| TARPLEY, ALANAH | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| TARRIO, NATASHA | FLOWOOD, MS | - | Mental Health Counselor | 01/06/2015 |
| TARVER, RUTH | LAREDO, TX | - | BCBA | 09/23/2026 |
| TATROE, TONYA | MANILA, AR | LPC | Professional Counselor | 04/25/2007 |
| TAUER, ANNA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| TAUGHER, ALYSSA | MOUNT CLEMENS, MI | - | Speech-Language Pathologist | 09/23/2026 |
| TAUKEIAHO, LEILANI | LEHI, UT | - | Case Manager/Care Coordinator | 01/06/2023 |
| TAVAREZ, CECILIA | OAKLAND, CA | - | Mental Health Counselor | 01/12/2026 |
| TAWIL, THERESA | BLOOMFIELD, NJ | M.A., CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| TAYE, ADDIS | RIVERBANK, CA | - | RBT | 09/21/2026 |
| TAYEH, YASIN | MAPLE HEIGHTS, OH | - | Speech-Language Pathologist | 09/21/2026 |
| TAYLHARDAT, REBECCA | MIAMI, FL | - | RBT | 09/23/2026 |
| TAYLOR-HUNTLEY, CAYLA | NEWNAN, GA | LPC | Mental Health Counselor | 06/15/2024 |
| TAYLOR-TUCKER, MELINDA | POPLAR BLUFF, MO | LCSW | Clinical Social Worker | 10/04/2015 |
| TAYLOR, AMY | BEREA, KY | M.A., CF-SLP | Speech-Language Pathologist | 09/24/2026 |
| TAYLOR, ANTONIETT | UPPER MARLBORO, MD | - | Case Manager/Care Coordinator | 09/23/2026 |
| TAYLOR, ASTGIK | BEACHWOOD, OH | QMHS-B, RN | Case Manager/Care Coordinator | 01/25/2023 |
| TAYLOR, BESARTA | HENRICO, VA | MSW | Case Manager/Care Coordinator | 09/21/2026 |
| TAYLOR, CORA | PUNTA GORDA, FL | PSY.S., LMHC | Mental Health Counselor | 04/04/2006 |
| TAYLOR, COURTNEY | RUSTON, LA | BCBA, LBA | BCBA | 01/22/2020 |
| TAYLOR, ELIZABETH | CORPUS CHRISTI, TX | - | RBT | 03/31/2026 |
| TAYLOR, HELENA | GAYLORD, MI | BCBA | BCBA | 10/03/2019 |
| TAYLOR, JEREMIAH | CONCORD, CA | - | RBT | 09/21/2026 |
| TAYLOR, JERROD | LANSING, IL | - | RBT | 09/21/2026 |
| TAYLOR, JONATHAN | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| TAYLOR, KATE | GRANBURY, TX | - | RBT | 09/21/2026 |
| TAYLOR, KAYDENCE | SPOKANE, WA | - | Assistant Behavior Analyst | 11/10/2021 |
| TAYLOR, KIMBERLY | COLUMBUS, GA | - | RBT | 09/22/2026 |
| TAYLOR, MALIK | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| TAYLOR, MARC | EUGENE, OR | PHD | Psychologist | 12/11/2006 |
| TAYLOR, MATTHEW | WAYNESBORO, VA | M.A., BCBA, LBA-V | BCBA | 11/22/2017 |
| TAYLOR, MAXINE | OWINGS MILLS, MD | PHD, LCSW-C | Clinical Social Worker | 02/10/2022 |
| TAYLOR, MICHAEL | BOLIVAR, MO | MSW, LMSW | Clinical Social Worker | 07/29/2024 |
| TAYLOR, NATALIE | TERRE HAUTE, IN | - | RBT | 09/21/2026 |
| TAYLOR, NIKAYLA | PICKERINGTON, OH | COTA | RBT | 11/22/2019 |
| TAYLOR, RACHEAL | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| TAYLOR, ROBERT | LAS VEGAS, NV | - | BCBA | 08/11/2017 |
| TAYLOR, TOREA | BOSSIER CITY, LA | CCC-SLP, CLC | Speech-Language Pathologist | 02/06/2025 |
| TAYLOR, TRINITY | JACKSONVILLE, NC | - | RBT | 09/22/2026 |
| TAYLOR, YOSHITA | GREENSBORO, NC | - | Clinic/Center | 06/16/2025 |
| TEAGUE, ALYSSA | RED BLUFF, CA | - | Mental Health Counselor | 09/24/2026 |
| TEELA, DARLENE | ELLENSBURG, WA | LMHC | Mental Health Counselor | 07/14/2023 |
| TEHRANI, NATASHA | FREMONT, CA | - | Mental Health Counselor | 02/23/2026 |
| TEIXEIRA, LILIANA | MERCED, CA | - | RBT | 09/23/2026 |
| TEJEDA, JENNA | ORMOND BEACH, FL | RBT | RBT | 09/24/2026 |
| TELLEZ, ABDIEL | LAKELAND, FL | BEHAVIOR TECHNICIAN | RBT | 09/21/2026 |
| TEMPLE, ALEC | FARMINGTON HILLS, MI | - | RBT | 09/24/2026 |
| TEMPLE, ANGELICA | OMAHA, NE | PLMHP, PCSW | Mental Health Counselor | 11/20/2024 |
| TEMPLE, NATASHA | MOUNTAIN VIEW, CA | - | RBT | 09/22/2026 |
| TENDER HEARTS AGENCY, LLCORG | HOUSTON, TX | - | Community/Behavioral Health Agency | 11/06/2025 |
| TENNESSEE LUNA CARE PHYSICAL THERAPY LLCORG | NASHVILLE, TN | - | Speech-Language Pathologist | 08/14/2020 |
| TENNIS, LINDSAY | ROUND ROCK, TX | - | RBT | 04/23/2026 |
| TEO, DAYANA | COSTA MESA, CA | - | RBT | 09/25/2026 |
| TEO, JONATHAN | TORRANCE, CA | - | RBT | 09/21/2026 |
| TERRAZAS, DAISY | ELMHURST, IL | - | RBT | 09/22/2026 |
| TERRAZAS, JOHNNY | CONCORD, CA | - | RBT | 09/21/2026 |
| TERROS INCORG | GLENDALE, AZ | - | Community/Behavioral Health Agency | 05/27/2025 |
| TERROS INCORG | GLENDALE, AZ | - | Community/Behavioral Health Agency | 05/27/2025 |
| TERROS, INC.ORG | MESA, AZ | - | Community/Behavioral Health Agency | 08/13/2024 |
| TERROS, INC.ORG | PHOENIX, AZ | - | Community/Behavioral Health Agency | 07/10/2007 |
| TERROS, INC.ORG | PHOENIX, AZ | - | Community/Behavioral Health Agency | 08/12/2024 |
| TERROS, INC.ORG | PHOENIX, AZ | - | Community/Behavioral Health Agency | 08/12/2024 |
| TERROS, INC.ORG | PHOENIX, AZ | - | Community/Behavioral Health Agency | 08/12/2024 |
| TERROS, INC.ORG | MESA, AZ | - | Community/Behavioral Health Agency | 02/29/2024 |
| TERRY, ANYA | PRESTONSBURG, KY | - | Professional Counselor | 08/25/2020 |
| TERRY, MARLO | EL CAJON, CA | - | Case Manager/Care Coordinator | 09/23/2026 |
| TERRY, REBECCA | GILLETTE, WY | LPC | Mental Health Counselor | 09/04/2023 |
| TESCH, CURTIS | LAYTON, UT | LCSW | Clinical Social Worker | 09/05/2012 |
| TESFAI, GENET | SAN FRANCISCO, CA | - | Clinical Social Worker | 09/23/2026 |
| TESSIER, RACHEL | CHARLOTTESVILLE, VA | MSW | Clinical Social Worker | 09/22/2026 |
| TESTA, ARIANNE | SAN DIEGO, CA | - | Speech-Language Pathologist | 09/26/2026 |
| TEUS, ROSAURA | MOORE, OK | - | Mental Health Counselor | 09/24/2026 |
| TEW, MEREDITH | STATESVILLE, NC | MA, CCC-SLP | Speech-Language Pathologist | 10/18/2012 |
| THACH, ETIENNE | SANTA BARBARA, CA | RBT | RBT | 03/08/2024 |
| THACKER, BRIEANNA | MIDLOTHIAN, VA | - | Assistant Behavior Analyst | 07/05/2023 |
| THAKAR, PUSHTI | PASADENA, CA | - | RBT | 09/23/2026 |
| THAO, JULIE | APPLETON, WI | APSW | Clinical Social Worker | 09/23/2026 |
| THAO, LEO | CONCORD, CA | - | RBT | 09/23/2026 |
| THARP, JERALYN | HUBER HEIGHTS, OH | LPCC-S LICDC | Mental Health Counselor | 10/13/2009 |
| THAXTON HOLISTIC WELLNESS CENTERORG | SCRANTON, PA | - | Mental Health Counselor | 08/24/2015 |
| THAYER, KATHERINE | ROSEBURG, OR | - | Counselor | 10/16/2019 |
| THE AFRICAN RESOURCE CENTER -THEARCORG | HOUSTON, TX | - | Case Management Agency | 09/22/2026 |
| THE BOARD OF TRUSTEES OF THE UNIVERSITY OF ILLINOISORG | CHICAGO, IL | - | Clinical Social Worker | 05/26/2006 |
| THE CARTER CONSORTIUM CORPORG | MECHANICSVILLE, VA | - | Counselor | 04/07/2022 |
| THE CELEBRATION HOUSE PLLCORG | CARY, NC | - | Speech-Language Pathologist | 09/21/2026 |
| THE CHILDRENS HOSPITAL OF PHILADELPHIAORG | PHILADELPHIA, PA | - | Clinic/Center | 04/02/2019 |
| THE CHILDRENS HOSPITAL OF PHILADELPHIA PRACTICE ASSOCIATIONORG | PHILADELPHIA, PA | - | Professional Counselor | 09/29/2006 |
| THE CORE COUNSELING AND CONSULTING PLLCORG | SUGAR LAND, TX | - | Mental Health Counselor | 09/23/2026 |
| THE COUNSELING CIRCLEORG | FLORENCE, AL | - | Mental Health Counselor | 09/25/2026 |
| THE DANIEL CLINIC, LLCORG | SEATTLE, WA | - | Counselor | 08/12/2020 |
| THE FAMILY RESOURCE NETWORKORG | E. WINDSOR, NJ | - | Community/Behavioral Health Agency | 03/19/2018 |
| THE FORGE AND THE VINE COUNSELING SERVICES PLLCORG | YAKIMA, WA | - | Mental Health Counselor | 09/25/2026 |
| THE FOUNDATION FOR COMMUNITY HEALTH AND WELLNESSORG | BEAUMONT, TX | - | Addiction (Substance Use Disorder) Counselor | 07/30/2025 |
| THE GARDENER SPIRITUAL COUNSELINGORG | ALBUQUERQUE, NM | - | Mental Health Counselor | 09/23/2026 |
| THE HEALING TREE COUNSELING AND THERAPEUTIC SERVICES LLCORG | HARTFORD, KY | - | Professional Counselor | 09/21/2026 |
| THE KEY WELLNESS & HEALING, PLLCORG | SACRAMENTO, CA | - | Professional Counselor | 07/18/2023 |
| THE MEDICAL SOCIAL WORKER THERAPY & CONSULTING LLCORG | TEXAS CITY, TX | - | Case Management Agency | 10/27/2023 |
| THE MENTAL SPACEORG | VESTAVIA HILLS, AL | - | Professional Counselor | 09/21/2026 |
| THE MOORE GROUP PSYCHOLOGY & CONSULTING PLLCORG | ROCHESTER HILLS, MI | - | Psychologist | 09/22/2026 |
| THE NEW PURPLE WELLNESS COUNSELING PLLCORG | WEST PEORIA, IL | - | Counselor | 09/24/2026 |
| THE NGUYEN HOLDING (DBA: BEAR SCHOOL)ORG | WESTMINSTER, CA | - | BCBA | 09/26/2026 |
| THE OFFICER HALL PROJECT, LLCORG | PITTSBURGH, PA | - | Case Management Agency | 02/02/2026 |
| THE POWER TO BE WHOLE COUNSELING THERAPY, LLCORG | LUCAS, TX | - | Professional Counselor | 09/24/2026 |
| THE SAFE AND SECURE COMMUNITY HEALTH CENTER LLCORG | PHOENIX, AZ | - | Clinic/Center | 09/24/2026 |
| THE SEE ME PLACE LLCORG | CLEVELAND, TN | - | BCBA | 09/14/2026 |
| THE SPEECH AGENCY CO.ORG | GONZALES, LA | - | Speech-Language Pathologist | 09/21/2026 |
| THE THERAPY OFFICE, LLCORG | SPRINGDALE, AR | - | Professional Counselor | 07/12/2023 |
| THELEN, RYN | CHICAGO, IL | LPC | Professional Counselor | 10/17/2025 |
| THEOPHILUS, REBECCA | SIOUX FALLS, SD | LPC | Mental Health Counselor | 09/10/2018 |
| THERACARE NORTH DALLASORG | CARROLLTON, TX | - | Mental Health Counselor | 09/21/2026 |
| THERAPEDIATRICS, LLCORG | VERNON HILLS, IL | - | Mental Health Counselor | 08/09/2006 |
| THERAPEDIATRICS, LLCORG | VERNON HILLS, IL | - | Professional Counselor | 04/06/2012 |
| THERAPEIA PLLCORG | TROY, MI | - | Professional Counselor | 05/18/2021 |
| THERAPENN COUNSELING & BEHAVIORAL HEALTHORG | SHAMOKIN, PA | - | Mental Health Counselor | 09/21/2026 |
| THERAPEUTIC BY NATURE, LLCORG | TOLEDO, OH | - | Mental Health Counselor | 12/17/2024 |
| THERAPIES & THERAPIES LLCORG | HOUSTON, TX | - | BCBA | 05/28/2021 |
| THERAPY WITH TIFFANY, PLLCORG | O FALLON, IL | - | Mental Health Counselor | 02/12/2026 |
| THERAPY WITH Z, LLCORG | TULSA, OK | - | Clinical Social Worker | 08/15/2026 |
| THERAPY, IT'S PERSONAL PLLCORG | CHESTERFIELD, MI | - | Professional Counselor | 08/17/2022 |
| THERAPYWALK LLCORG | NORTH MIAMI, FL | - | Mental Health Counselor | 09/19/2024 |
| THERESIA, KUM | BELTSVILLE, MD | - | Case Manager/Care Coordinator | 09/28/2023 |
| THIRAYATORN, ORAKORN | OAKLAND, CA | - | Day Training/Habilitation Specialist | 04/27/2020 |
| THIRD WAY THERAPY PLLCORG | WIMBERLEY, TX | - | Clinical Social Worker | 09/25/2026 |
| THIWAN SYED, SYED ISMAIL | NORFOLK, VA | MD | Specialist | 02/17/2006 |
| THOMA, KAITLYN | WEST COLUMBIA, SC | - | Mental Health Counselor | 09/23/2026 |
| THOMAS-JONES, ANGELA | BETHLEHEM, NH | LCMHC, MLADC | Mental Health Counselor | 01/09/2008 |
| THOMAS, ANGELA | KERNERSVILLE, NC | - | BCBA | 11/12/2012 |
| THOMAS, CALI | SAGINAW, MI | - | RBT | 09/24/2026 |
| THOMAS, CAMRYANA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| THOMAS, CATRINA | LAS VEGAS, NV | - | RBT | 07/05/2024 |
| THOMAS, DWAYNE | HOPEWELL, VA | - | Mental Health Counselor | 09/23/2026 |
| THOMAS, JACQUELINE | MOORE, OK | LMSW-P | Counselor | 07/22/2024 |
| THOMAS, JOSHUA | HOLLAND, MI | LMSW | Clinical Social Worker | 04/12/2017 |
| THOMAS, KALI | BOSTON, MA | - | Clinical Social Worker | 02/19/2025 |
| THOMAS, KOLEEN | EUCLID, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| THOMAS, KYLA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| THOMAS, LA'SHAY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| THOMAS, MARICIA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| THOMAS, MARIE | ORANGE, CA | - | Mental Health Counselor | 09/22/2026 |
| THOMAS, PHYLICIA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| THOMAS, SHAYLA | LOS LUNAS, NM | - | RBT | 09/22/2026 |
| THOMAS, ZACHARY | MARIETTA, GA | - | Professional Counselor | 09/23/2026 |
| THOMASON COUNSELING AND CONSULTING, PLLCORG | TEXARKANA, AR | - | Mental Health Counselor | 09/22/2026 |
| THOMASON, RANDY | TEXARKANA, TX | LCDC, LPC | Mental Health Counselor | 05/02/2013 |
| THOMPSON, ALEXUS | COLUMBIA, SC | - | RBT | 09/22/2026 |
| THOMPSON, AMBER | MAITLAND, FL | - | RBT | 06/04/2025 |
| THOMPSON, ANAIAH | DANVERS, MA | - | RBT | 09/21/2026 |
| THOMPSON, ANGELA | JACKSONVILLE, FL | - | Mental Health Counselor | 09/21/2026 |
| THOMPSON, BLAKE | MYRTLE BEACH, SC | ADC-IP | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| THOMPSON, COURTNEY | BONO, AR | - | RBT | 09/21/2026 |
| THOMPSON, DYLAN | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| THOMPSON, GEORGIA | VALLEJO, CA | - | RBT | 09/01/2026 |
| THOMPSON, JABARI | DAYTON, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| THOMPSON, JAMIE | ANNISTON, AL | LCSW | Clinical Social Worker | 09/13/2019 |
| THOMPSON, JENNA | WILMINGTON, MA | - | RBT | 09/23/2026 |
| THOMPSON, KAYLA | TORRANCE, CA | - | RBT | 09/21/2026 |
| THOMPSON, KELSEY | BETTENDORF, IA | - | Mental Health Counselor | 01/25/2019 |
| THOMPSON, MARYGRACE | WINCHESTER, CA | LVN | Mental Health Counselor | 03/03/2022 |
| THOMPSON, MAYA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| THOMPSON, NATHAN | BUENA, WA | - | Mental Health Counselor | 05/12/2025 |
| THOMPSON, STACY | DECATUR, IL | LPC | Professional Counselor | 09/21/2026 |
| THOMPSON, VASHTA | WASHINGTON, DC | - | Clinical Social Worker | 08/13/2018 |
| THORNBERG, MARA | DENVER, CO | LPC, LCPC, NCC | Mental Health Counselor | 01/03/2022 |
| THORNE, BRIAN | PETERSBURG, WV | - | Case Manager/Care Coordinator | 09/24/2026 |
| THORNE, CASSIDEE | APPLETON, WI | MS, LPC | Mental Health Counselor | 08/15/2022 |
| THORNTON, DEONDRA | BIRMINGHAM, AL | LPC | Mental Health Counselor | 11/26/2024 |
| THORNTON, TYSHA | SPRINGFIELD, MO | MS, LPC | Professional Counselor | 02/19/2007 |
| THORPE, MCKENNA | KNOXVILLE, TN | - | BCBA | 09/25/2026 |
| THRAILKILL, CHRISTOPHER | PORTLAND, OR | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| THREE RIVERS THERAPY LLCORG | MILWAUKEE, WI | - | Mental Health Counselor | 12/18/2015 |
| THREE RIVERS THERAPY, LLCORG | KENNEWICK, WA | - | Mental Health Counselor | 04/06/2016 |
| THRELKELD, KAREN | CORDOVA, TN | - | Mental Health Counselor | 09/21/2026 |
| THRIVE COUNSELING SERVICES, LLCORG | GILBERT, AZ | - | Professional Counselor | 09/03/2013 |
| THRIVE HEALTH LLCORG | GLENDALE, AZ | - | Professional Counselor | 07/16/2025 |
| THRIVE PSYCHOLOGICAL SOLUTIONS, PLLCORG | COLORADO SPRINGS, CO | - | Psychologist | 03/06/2025 |
| THRIVE THERAPYORG | PHILADELPHIA, PA | - | Case Management Agency | 09/21/2026 |
| THRIVELIGHT WELLNESS CORP.ORG | MISSOURI CITY, TX | - | Community/Behavioral Health Agency | 08/27/2025 |
| THROUGH THE PINES LLCORG | HATTIESBURG, MS | - | Mental Health Counselor | 09/21/2026 |
| THRYVEN HEALTH AND WELLNESS CENTER LLCORG | LIMA, OH | - | Community/Behavioral Health Agency | 09/21/2026 |
| THURMAN, MARCELLUS | OKLAHOMA CITY, OK | LCSW | Clinical Social Worker | 03/30/2022 |
| THURMES, MATTIE | ROSEMOUNT, MN | M.A. CCC-SLP | Speech-Language Pathologist | 06/29/2026 |
| TIAN, QIANYI | NEW YORK, NY | - | Mental Health Counselor | 09/24/2026 |
| TICEHURST, EMILY | CRANSTON, RI | - | Clinical Social Worker | 07/21/2023 |
| TIDWELL, MEGAN | SOUTH JORDAN, UT | - | Mental Health Counselor | 09/23/2026 |
| TIEFEL, MARK | GERMANTOWN, WI | - | Mental Health Counselor | 09/24/2026 |
| TIFFIANY CARES LLCORG | KANNAPOLIS, NC | - | Community/Behavioral Health Agency | 09/25/2026 |
| TIGER & BOLT MANAGED SERVICES, LLCORG | GREENWOOD VILLAGE, CO | - | Mental Health Counselor | 05/26/2022 |
| TIGER'S EYE COUNSELING AND CONSULTINGORG | PHOENIX, AZ | - | Clinical Social Worker | 08/26/2026 |
| TIJERINA, KOURTNEY | FARMINGTON HILLS, MI | - | RBT | 08/19/2026 |
| TILL, JEFFRY | POPLAR BLUFF, MO | LCSW | Clinical Social Worker | 01/04/2006 |
| TILLEY, NICHOLE | SACRAMENTO, CA | - | RBT | 09/24/2026 |
| TILLMAN, RACHEL | SAN JOSE, CA | M.A. | Professional Counselor | 03/21/2013 |
| TILLMANN, HEATHER | FAIRFIELD, OH | LISW | Clinical Social Worker | 05/09/2023 |
| TILMAN, JACI | GULFPORT, MS | - | RBT | 09/22/2026 |
| TIMESHERVEDRECOVERYLLCORG | WARREN, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| TIMM, HALLE | BRONX, NY | - | Speech-Language Pathologist | 09/21/2026 |
| TIMMERMANN, JESSE | LAKE MARY, FL | - | RBT | 09/21/2026 |
| TINDLE BEHAVIOR CONSULTING, LLCORG | DECATUR, GA | - | BCBA | 09/19/2026 |
| TINKER, ANNA | BEND, OR | - | Clinical Social Worker | 09/23/2026 |
| TINKLE, JAMIE | WOODINVILLE, WA | LICSW | Clinical Social Worker | 06/07/2018 |
| TINNELL, DANIEL | OMAHA, NE | - | Day Training/Habilitation Specialist | 11/24/2025 |
| TINORUA, MADONNA | HONOLULU, HI | LMHC | Mental Health Counselor | 10/19/2022 |
| TIONKO, KRISTEN | COLORADO SPRINGS, CO | - | RBT | 09/21/2026 |
| TIPPETT, ARIANA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| TIRADO CALDERON, NORMA | CAGUAS, PR | - | Clinical Social Worker | 09/24/2026 |
| TIRADO, CARLOS | VICTORVILLE, CA | - | RBT | 09/25/2026 |
| TIRONA-OBIAS, SHARON | FALLS CHURCH, VA | M.D. | Case Manager/Care Coordinator | 06/18/2007 |
| TIRONE, BROOKE | OAKLAND, NJ | LCSW | Clinical Social Worker | 09/23/2026 |
| TITA, KELLY | YORK, PA | LBS | BCBA | 09/23/2026 |
| TITOVA, NATALIA | DES MOINES, WA | - | Counselor | 09/18/2026 |
| TITUS, JERRICA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| TIWARI, PRISHA | MOUNTAIN VIEW, CA | - | RBT | 09/22/2026 |
| TJHAI, ROSELYNE | TORRANCE, CA | - | RBT | 09/24/2026 |
| TLC CHIROPRACTIC CENTER INCORG | DORAL, FL | - | Clinic/Center | 02/25/2008 |
| TOAL, LEAH | TROY, MI | - | BCBA | 10/01/2020 |
| TOBINUS, RACHAEL | MEDIA, PA | MS | Mental Health Counselor | 09/22/2026 |
| TOBLER, RACHEL | CHICAGO, IL | MA LPC | Professional Counselor | 09/24/2026 |
| TOGETHER WE CAN COMMUNITY ALLIANCE INCORG | WATERBURY, CT | - | Mental Health Counselor | 09/21/2026 |
| TOGNETTI, CALI | GRAND RAPIDS, MI | RBT | RBT | 09/22/2026 |
| TOIVOA, INC.ORG | NEWARK, DE | - | Community/Behavioral Health Agency | 04/15/2025 |
| TOJIMIRZAEVA, ADIBA | SAN BRUNO, CA | - | RBT | 09/22/2026 |
| TOLBERT, RAVEN | SMYRNA, GA | BCBA | BCBA | 09/17/2026 |
| TOLER, ADRIAN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| TOLIUSIS, LORETTA | VILLA PARK, IL | LCPC | Professional Counselor | 07/09/2012 |
| TOLLEY, MALEAH | LOUISVILLE, KY | - | RBT | 09/22/2026 |
| TOLLEY, STACEY | MC ARTHUR, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| TOLLISON, KIRA | TOLEDO, OH | BCBA | BCBA | 09/11/2019 |
| TOLLISON, MELODY | OKLAHOMA CITY, OK | - | Case Manager/Care Coordinator | 04/03/2018 |
| TOMBLIN, SOPHIA | SOUTHFIELD, MI | - | RBT | 09/24/2026 |
| TOMEH, SALAHEDDINE | PEORIA, AZ | MD | Specialist | 07/07/2006 |
| TOMER-LEWIS, ANDREA | CADIZ, OH | MSW, LISW-S | Clinical Social Worker | 09/27/2021 |
| TOMLINSON, SHELLY | CONROE, TX | - | Professional Counselor | 09/24/2026 |
| TONETTI, KARINA | CHARLOTTE, NC | - | Mental Health Counselor | 09/23/2026 |
| TONEY, JOSEPH | GARDEN CITY, ID | - | Clinical Social Worker | 05/17/2024 |
| TONEY, SYNTHIA | PORTLAND, OR | M.A., BCBA | BCBA | 06/07/2024 |
| TONEY, TANEKA | ATLANTA, GA | - | RBT | 09/25/2026 |
| TOOLE, JT | LITTLETON, CO | SWC | Mental Health Counselor | 09/21/2026 |
| TOOTHACKER, WILLIAM | COLUMBUS, OH | - | Case Manager/Care Coordinator | 09/21/2026 |
| TOPCUOGLU, SUZAN | EDGEWATER, MD | LCPC | Professional Counselor | 08/20/2009 |
| TOPPIN, CHANDLER | PHILADELPHIA, PA | - | RBT | 09/21/2026 |
| TORBERT, JORDYN | CLEVELAND, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| TORRES ARIAS, FRANSLY | LOS ANGELES, CA | - | Case Manager/Care Coordinator | 09/24/2026 |
| TORRES MUSEGUEZ, SUEDY | PEORIA, AZ | - | RBT | 09/25/2026 |
| TORRES, ALEX | TARRYTOWN, NY | - | Mental Health Counselor | 09/21/2026 |
| TORRES, ALEXIS | TORRANCE, CA | - | RBT | 05/08/2024 |
| TORRES, ANA | SAN PABLO, CA | - | Day Training/Habilitation Specialist | 03/20/2019 |
| TORRES, CHRISTINA | OKLAHOMA CITY, OK | SLP | Speech-Language Pathologist | 04/09/2018 |
| TORRES, FATIMA | PRESCOTT VALLEY, AZ | - | RBT | 09/21/2026 |
| TORRES, GABRIELA | TALLAHASSEE, FL | - | BCBA | 12/19/2023 |
| TORRES, HOPE | COLORADO SPRINGS, CO | - | RBT | 09/25/2026 |
| TORRES, ITZEL | COSTA MESA, CA | - | RBT | 09/22/2026 |
| TORRES, JESSIE | MENTOR, OH | CDCA, QMHS | Case Manager/Care Coordinator | 10/12/2021 |
| TORRES, JESUS | CORPUS CHRISTI, TX | LCDC | Addiction (Substance Use Disorder) Counselor | 09/21/2026 |
| TORRES, JONATHAN | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| TORRES, KRISTYN | HIALEAH, FL | SLP | Speech-Language Pathologist | 08/21/2024 |
| TORRES, LARISSA | GILROY, CA | - | Case Manager/Care Coordinator | 12/21/2015 |
| TORRES, MIGUEL | REDONDO BEACH, CA | LCSW | Clinical Social Worker | 10/24/2012 |
| TORRES, REBECCA | OXNARD, CA | - | Case Manager/Care Coordinator | 08/18/2021 |
| TORRES, SANDRA | OCOEE, FL | M.A. , LMHC | Mental Health Counselor | 03/05/2018 |
| TORRES, TREDUCE | EAST HARTFORD, CT | BT | RBT | 09/24/2026 |
| TORREZ, MINDI | LONG BEACH, CA | - | RBT | 09/21/2026 |
| TOTO MOTO ACADEMY LLCORG | ALEXANDRIA, VA | - | BCBA | 07/24/2026 |
| TOUCOVE ABA, LLCORG | DUNEDIN, FL | - | BCBA | 09/21/2026 |
| TOUKOLON, ALICE | MORRISVILLE, NC | - | BCBA | 03/15/2022 |
| TOURE, ROUGUIYATOU | FAIRFAX, VA | MSW | Clinical Social Worker | 12/07/2023 |
| TOUSAINT, BRIONA | FARMERVILLE, LA | - | Mental Health Counselor | 09/21/2026 |
| TOWNSELL, DAYSHA | TROY, OH | - | Day Training/Habilitation Specialist | 04/01/2024 |
| TOWNSEND, BRITTANY | SOUTH PRINCE GEORGE, VA | - | Addiction (Substance Use Disorder) Counselor | 11/22/2023 |
| TOWNSEND, DOMINIC | LOS GATOS, CA | - | Professional Counselor | 03/10/2020 |
| TRACI JO HAYSORG | SALEM, OH | - | Community/Behavioral Health Agency | 09/24/2026 |
| TRACY, KATLYN | CHICAGO, IL | LPC | Professional Counselor | 01/27/2020 |
| TRAHAN, SABREY | LITTLETON, CO | - | Mental Health Counselor | 09/21/2026 |
| TRAINING WHEELS, ABA, LLCORG | AUSTIN, TX | - | BCBA | 01/09/2020 |
| TRAN, APRIL | ORANGE, CA | - | RBT | 09/22/2026 |
| TRAN, KENNEDY | OAKLAND, CA | - | RBT | 09/25/2026 |
| TRANQUIL HEARTS HOME CARE LLCORG | DETROIT, MI | - | RBT | 11/20/2023 |
| TRANQUIL MINDS BEHAVIORAL HEALTH, LLCORG | EL PASO, TX | - | Mental Health Counselor | 06/29/2023 |
| TRANQUIL THERAPY CENTERORG | WOOD DALE, IL | - | Mental Health Counselor | 09/24/2026 |
| TRAPP, TIERA | COLUMBIA, SC | RBT | RBT | 09/21/2026 |
| TRAVERS, MADELINE | FOREST HILLS, NY | - | RBT | 09/21/2026 |
| TRAVIS, AALIYAH | MANILA, AR | PLMSW | Case Manager/Care Coordinator | 07/25/2023 |
| TREE FROG COUNSELING SERVICES PLLCORG | NEW BERN, NC | - | Counselor | 09/21/2026 |
| TREE OF LIFE COUNSELING, A LICENSED CLINICAL SOCIAL WORKER CORPORATIONORG | APPLE VALLEY, CA | - | Mental Health Counselor | 02/20/2025 |
| TREEGOOB, MARK | GLENDALE, AZ | PH.D. | Psychologist | 09/05/2005 |
| TREJO, KIMBERLY | TORRANCE, CA | - | RBT | 09/21/2026 |
| TRELLIS BEHAVIORAL HEALTH LLCORG | DENVER, CO | - | Counselor | 09/25/2026 |
| TRENT, MARIA | WILLIAMSBURG, VA | RESIDENT IN COUNSEL | Professional Counselor | 03/11/2022 |
| TRESALONI, CHLOE | ATHOL, MA | BA PSYCHOLOGY | Counselor | 09/23/2026 |
| TREVINO, ADRIANNE | SPRING, TX | - | Counselor | 09/22/2026 |
| TREVINO, MARYAH | CORAL GABLES, FL | BT, RBT | RBT | 09/22/2026 |
| TREVINO, SAMANTHA | HACIENDA HEIGHTS, CA | - | Case Manager/Care Coordinator | 09/21/2026 |
| TREVINO, VALERIE | SAN ANTONIO, TX | LPC | Professional Counselor | 12/13/2025 |
| TRIANO, JENNIFER | WESTMINSTER, MD | LCSW-C | Clinical Social Worker | 02/21/2023 |
| TRIECE, SKY | TACOMA, WA | - | Mental Health Counselor | 09/25/2026 |
| TRINISEWSKI, KATHERINE | PORTLAND, OR | - | Mental Health Counselor | 04/20/2026 |
| TRIUMPH, JAMES | KALAMAZOO, MI | - | Mental Health Counselor | 09/21/2026 |
| TRIUMPHCARE HEALTH LLCORG | GREER, SC | - | Clinic/Center | 11/25/2025 |
| TRIVITS, ANNA | SALISBURY, MD | - | Mental Health Counselor | 09/22/2026 |
| TROMSNESS, SIERRA | RUSSELLVILLE, KY | - | Clinical Social Worker | 08/25/2022 |
| TRONCOSO, DANIELA | HOFFMAN ESTATES, IL | - | RBT | 09/21/2026 |
| TROTCHIE, MIA | DENVER, CO | - | Case Manager/Care Coordinator | 09/24/2026 |
| TROTH, ANGELINA | STUART, FL | RBT | RBT | 09/26/2026 |
| TROTTO, DEBORAH | ROCHESTER, NY | - | Specialist | 09/24/2026 |
| TROXELL, ALYSSUM | MIDDLETOWN, OH | - | RBT | 09/23/2026 |
| TRUDEAU, GRACE | SAGINAW, MI | - | RBT | 09/24/2026 |
| TRUE HOPE COUNSELINGORG | MARKED TREE, AR | - | Community/Behavioral Health Agency | 02/03/2015 |
| TRUE LEVEL THERAPY LLCORG | KILAUEA, HI | - | Clinical Social Worker | 09/25/2026 |
| TRUE NORTH CLINICORG | KATY, TX | - | Mental Health Counselor | 09/23/2026 |
| TRUE PATH BEHAVIORAL HEALTH LLCORG | LAS VEGAS, NV | - | Community/Behavioral Health Agency | 09/21/2026 |
| TRUESDELL, CAROLINE | LAWRENCE, MA | - | BCBA | 09/03/2025 |
| TRUITT, COURTNEY | MADILL, OK | LPC | Counselor | 11/02/2011 |
| TRUJILLO, ASHLEIGH | AUSTIN, TX | - | RBT | 09/22/2026 |
| TRUJILLO, FAITH | DENVER, CO | - | RBT | 09/22/2026 |
| TRUJILLO, FELISA | SACRAMENTO, CA | - | Day Training/Habilitation Specialist | 09/23/2026 |
| TRUJILLO, KIRAH | COLORADO SPRINGS, CO | - | RBT | 09/26/2026 |
| TRUJILLO, REBECCA | ESPANOLA, NM | PSR | BCBA | 09/15/2026 |
| TRUJILLO, ROBERTO | FORT WAYNE, IN | - | RBT | 09/23/2026 |
| TRUJILLO, VANESSA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| TRUJILLO, VANESSA | BANNING, CA | LCSW | Mental Health Counselor | 09/20/2012 |
| TRULY KNOWN COUNSELING LLCORG | FORT WASHINGTON, PA | - | Professional Counselor | 09/03/2026 |
| TRUMP, CHELBEY | YOUNGSTOWN, OH | - | Mental Health Counselor | 07/31/2025 |
| TRUONG, MINHCHAU | HOUSTON, TX | LMSW | Clinical Social Worker | 09/25/2026 |
| TRUONG, VIVIAN | CHICAGO, IL | - | Mental Health Counselor | 09/25/2026 |
| TRUTTMAN, JENNIFER | YREKA, CA | - | Counselor | 09/22/2026 |
| TSAHIRIDIS, ELIZABETH | BRANSON, MO | MSMHC MSED LPC | Counselor | 04/13/2018 |
| TSAI, ANGELA | LAGUNA HILLS, CA | - | Mental Health Counselor | 08/06/2019 |
| TSUKANOVA, IRINA | SAN JOSE, CA | CADC I | Counselor | 10/03/2019 |
| TUBI, OLAJUMOKE | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| TUCKER, DANIELLE | KERNERSVILLE, NC | - | BCBA | 06/10/2022 |
| TUCKER, KELLY | ASHEVILLE, NC | LCMHC | Mental Health Counselor | 04/25/2018 |
| TUCKER, KELSEE | ROME, GA | LCSW | Clinical Social Worker | 10/02/2018 |
| TUCKER, ROSEANNE | WEST RUTLAND, VT | LCSW | Clinical Social Worker | 10/05/2020 |
| TUDELA, MEGAN | ANNAPOLIS, MD | LMSW | Clinical Social Worker | 09/23/2026 |
| TUDMAN, HAYVEN | GRAND PRAIRIE, TX | LCSW | Clinical Social Worker | 09/25/2026 |
| TUFTE, MEGHAN | RICHMOND, VA | - | RBT | 09/21/2026 |
| TULLIS, JAYCI | SPRINGFIELD, IL | - | BCBA | 09/30/2024 |
| TULLIS, KAITLYN | PEARLAND, TX | - | Speech-Language Pathologist | 09/22/2026 |
| TULLNER, HUGH | RALEIGH, NC | LCMHCA | Mental Health Counselor | 09/25/2026 |
| TULLY, SARAH | NASHVILLE, TN | - | BCBA | 03/16/2021 |
| TUNAI, KATELYN | ANCHORAGE, AK | - | RBT | 09/24/2026 |
| TUNLEY, MELISA | OKLAHOMA CITY, OK | - | Mental Health Counselor | 05/18/2021 |
| TURBE, MADELINE | CLARKSVILLE, TN | - | RBT | 09/21/2026 |
| TURGEON, KAREN | SOUTH PORTLAND, ME | LCSW | Clinical Social Worker | 09/21/2026 |
| TURK, DEREK | CONCORD, CA | - | RBT | 09/23/2026 |
| TURN KEY COUNSELING GROUP LLCORG | WESTWOOD, MA | - | Clinical Social Worker | 09/21/2026 |
| TURNER, ALYSHA | ALPHARETTA, GA | - | RBT | 11/26/2019 |
| TURNER, AMANDA | ATLANTA, GA | - | Clinical Social Worker | 09/25/2026 |
| TURNER, BRITTNEE | MONTROSE, CO | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| TURNER, CAROLYN | HURRICANE, UT | CMHC | Mental Health Counselor | 02/18/2019 |
| TURNER, CODY | SYLACAUGA, AL | - | BCBA | 09/21/2026 |
| TURNER, DIONYS | RIVERBANK, CA | - | RBT | 09/21/2026 |
| TURNER, EUGENE | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| TURNER, GAIL | AUSTIN, TX | DSW, LPC, NCC | Mental Health Counselor | 02/13/2019 |
| TURNER, JASMIN | WINDSOR MILL, MD | - | Professional Counselor | 12/19/2018 |
| TURNER, KAYLEE | LOS LUNAS, NM | - | RBT | 09/23/2026 |
| TURNER, KIWANDA | LA PLACE, LA | MS | Professional Counselor | 01/13/2016 |
| TURNER, LAUREN | INVERNESS, IL | M.A., LCPC, NCC | Professional Counselor | 01/31/2017 |
| TURNER, MAKAYLA | ONTARIO, CA | - | Assistant Behavior Analyst | 09/23/2026 |
| TURNER, MEGHAN | MANSFIELD, TX | CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| TURNER, MELISSA | SALEM, OH | LPCC | Mental Health Counselor | 09/27/2018 |
| TURNER, SYDNEY | DANVILLE, VA | - | Mental Health Counselor | 09/24/2026 |
| TURNING STONES COUNSELING AND WELLNESS LLCORG | UPPER ST CLAIR, PA | - | Mental Health Counselor | 06/15/2026 |
| TURNING TOWARD THERAPY, PLLCORG | INVERNESS, IL | - | Clinical Social Worker | 09/24/2026 |
| TURNWELL MENTAL HEALTH TENNESSEE, PCORG | NASHVILLE, TN | - | Counselor | 09/21/2026 |
| TURPEN, JORDAN | PLYMOUTH, MI | BCBA, LBA | BCBA | 04/08/2026 |
| TURPEN, KATHARINE | LAS CRUCES, NM | LMSW | Clinical Social Worker | 09/24/2026 |
| TUSSA, JALANE | COON RAPIDS, MN | - | RBT | 09/23/2026 |
| TUTHILL, TAYLOR | URBANDALE, IA | MSW | Mental Health Counselor | 09/25/2026 |
| TWEEDEL, JAKOB | STUART, FL | - | RBT | 04/13/2026 |
| TWEEDT, AMY | MOJAVE, CA | AAMFT | Case Manager/Care Coordinator | 12/21/2021 |
| TWIN BEARS THERAPY & PLAY LLCORG | WINTER HAVEN, FL | - | Speech-Language Pathologist | 09/24/2026 |
| TWITTY, CAL | NAPLES, FL | - | Mental Health Counselor | 09/24/2026 |
| TYH OPERATING CO., LLCORG | BLUE ASH, OH | - | BCBA | 07/20/2023 |
| TYLER, KAREN | BANGOR, ME | LCSW | Clinical Social Worker | 12/01/2009 |
| TYLER, LESLIE | COLUMBIA, SC | M.S.P., CCC - SLP | Speech-Language Pathologist | 05/01/2006 |
| TYRA, RYAN | WAIPAHU, HI | - | RBT | 09/24/2026 |
| TYREE, MALLORY | FORT WORTH, TX | LCSW | Clinical Social Worker | 12/09/2024 |
| TYSON, KIA | BIRMINGHAM, AL | BCBA | BCBA | 06/07/2016 |
| TZ THERAPY AND WELLNESS, LLCORG | MIDLAND, MI | - | Clinical Social Worker | 09/25/2026 |
| UCHISON, RACHAEL | LOOMIS, CA | - | Counselor | 02/25/2019 |
| UEDA, YOSHIMI | SAN DIEGO, CA | - | RBT | 09/25/2026 |
| UGBOR, MICHAEL | BROOKLYN, NY | PHD, MHC | Mental Health Counselor | 09/24/2026 |
| ULLERICH, ROBERT | CENTRALIA, WA | BS, R-AAC | RBT | 02/22/2021 |
| ULRICH, JAN | ANN ARBOR, MI | LMSW | Clinical Social Worker | 02/21/2007 |
| ULRICH, MICHAEL | BILLINGS, MT | LCSW | Clinical Social Worker | 02/08/2007 |
| UMI WELLNESS COUNSELING LLCORG | HONOLULU, HI | - | Clinical Social Worker | 09/24/2026 |
| UNC AT CHARLOTTEORG | CHARLOTTE, NC | - | Clinic/Center | 10/18/2006 |
| UNCOVERED ROADS PSYCHOTHERAPY PLLCORG | RALEIGH, NC | - | Clinical Social Worker | 09/22/2026 |
| UNDERSTORY THERAPY, PLLCORG | VASHON, WA | - | Counselor | 12/24/2025 |
| UNDERWOOD, DANELL | MANHATTAN, KS | LSCSW | Clinical Social Worker | 06/01/2006 |
| UNDERWOOD, SHERRI | FAYETTEVILLE, NC | - | RBT | 09/23/2026 |
| UNGER, MELISSA | CHERRY HILL, NJ | SLP | Speech-Language Pathologist | 09/25/2026 |
| UNITED HELPERS CARE INCORG | OGDENSBURG, NY | - | Case Management Agency | 09/21/2005 |
| UNITED HELPERS CARE INCORG | OGDENSBURG, NY | - | Case Management Agency | 09/20/2005 |
| UNITED MEDICAL CENTERSORG | EAGLE PASS, TX | - | Professional Counselor | 05/24/2005 |
| UNJADED CLINICALORG | SOUTH KINGSTOWN, RI | - | Clinical Social Worker | 09/23/2026 |
| UNLOCKED SELF COUNSELING PLLCORG | MESA, AZ | - | Mental Health Counselor | 09/15/2026 |
| UNLV MEDICINEORG | LAS VEGAS, NV | - | BCBA | 09/21/2026 |
| UPHAM, CATHERINE | JACKSON, MI | LLMSW | Clinical Social Worker | 07/16/2025 |
| UPSIDEHOM, INC.ORG | FORT LAUDERDALE, FL | - | Case Manager/Care Coordinator | 05/24/2024 |
| UPTHEGROVE, SYLVIA | DETROIT, MI | LLPC | Mental Health Counselor | 09/21/2026 |
| URBAN, TRACY | MILWAUKEE, WI | APSW | Clinical Social Worker | 09/21/2026 |
| URGENT PSYCH MEDPAORG | TAMARAC, FL | - | Mental Health Counselor | 09/25/2026 |
| URTEAGA, FRIDA | BROWNSVILLE, TX | - | RBT | 09/22/2026 |
| USATYNSKI, THEODORE | THORNTON, CO | LPCC | Mental Health Counselor | 09/24/2026 |
| USE, EVA | NOVATO, CA | - | Addiction (Substance Use Disorder) Counselor | 05/22/2024 |
| USERA, MARIA | SAN JUAN, PR | MS | Psychologist | 09/01/2026 |
| USSERY, RAE | DOTHAN, AL | - | RBT | 09/24/2026 |
| UTECHT, ALINA | FARWELL, MI | - | Speech-Language Pathologist | 09/24/2026 |
| UTRERA, DIRCE | LAKEHILLS, TX | LPC-ASSOCIATE | Professional Counselor | 09/21/2026 |
| UY-YOUKERD, RESSEKA | CHICAGO, IL | LCSW | Clinical Social Worker | 01/12/2023 |
| VACEK, ALISON | MANCHESTER, CT | LPC | Professional Counselor | 08/15/2023 |
| VAH, ASHLEE | COLUMBUS, OH | - | Case Manager/Care Coordinator | 06/05/2023 |
| VAHEY, REILLY | WALNUT CREEK, CA | - | RBT | 09/22/2026 |
| VAINER & VAINER NEPHROLOGY CONSULTANTS, INCORG | ROSWELL, GA | - | Specialist | 12/02/2008 |
| VAKHARIA, RICHA | CHICAGO, IL | PSYD | Psychologist | 06/11/2021 |
| VALADEZ SANCHEZ, CAROLINA | SAN BERNARDINO, CA | - | RBT | 09/24/2026 |
| VALADEZ, SARAH | ALHAMBRA, CA | - | RBT | 09/23/2026 |
| VALCIN, JESSICA | CONCORD, CA | - | BCBA | 09/01/2020 |
| VALDEMAR, GREGORY | AUSTIN, TX | - | RBT | 09/22/2026 |
| VALDEOSERA, KLAYNY | COVINA, CA | - | RBT | 01/21/2025 |
| VALDES, LUZ | CHICAGO, IL | - | Psychologist | 02/18/2026 |
| VALDEZ GUTIERREZ, DENISSE | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| VALDEZ, ALAHNA | OAKLAND, CA | - | RBT | 09/22/2026 |
| VALDEZ, ILENE | SAN BERNARDINO, CA | - | RBT | 09/25/2026 |
| VALDEZ, JAYLYN | SAN DIEGO, CA | - | RBT | 09/22/2026 |
| VALDEZ, JAZMIN | RIVERSIDE, CA | - | RBT | 09/25/2026 |
| VALDEZ, REGINA ANNE | VANCOUVER, WA | - | RBT | 09/22/2026 |
| VALDIBIA MARIN, BRENDA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| VALDIVIA, HECTOR | DOWNEY, CA | - | Addiction (Substance Use Disorder) Counselor | 03/09/2023 |
| VALDIVIA, LIZANDRA | CAPE CORAL, FL | - | BCBA | 11/06/2018 |
| VALDIVIA, MARISSA | TUCSON, AZ | SLP | Speech-Language Pathologist | 07/10/2024 |
| VALDIVIA, TANYA | LOS ANGELES, CA | - | RBT | 09/21/2026 |
| VALDOVINOS CARABEZ, JUDITH | SAN FRANCISCO, CA | - | Professional Counselor | 07/25/2022 |
| VALENCIA SANCHEZ, VERONICA | EL CAJON, CA | - | Mental Health Counselor | 05/15/2026 |
| VALENCIA, ELIZABETH | LOS ANGELES, CA | CLINICAL COUNSELING | Professional Counselor | 10/06/2022 |
| VALENCIA, SHANNON | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| VALENTE, GABRIELLA | WARWICK, RI | LCSW | Clinical Social Worker | 09/22/2026 |
| VALENTIN, ARLIN | DECATUR, AL | - | RBT | 09/21/2026 |
| VALENTIN, EMMANUELLA | CRANFORD, NJ | MISS | BCBA | 06/01/2021 |
| VALENTIN, LUPITA | MCALLEN, TX | - | Speech-Language Pathologist | 09/21/2026 |
| VALENTINE, MELISSA | CLEARWATER, FL | LCSW | Clinical Social Worker | 04/17/2018 |
| VALENTINO LOPEZ, DENENCY | FRESNO, CA | - | RBT | 09/22/2026 |
| VALEO MENTAL HEALTH LLCORG | LAS VEGAS, NV | - | Mental Health Counselor | 09/24/2026 |
| VALERIE MCMILLEN LCSW LLCORG | OAKHURST, NJ | - | Clinical Social Worker | 08/27/2014 |
| VALERIO, JANET | BRADENTON, FL | MA, LMHC | Case Manager/Care Coordinator | 07/13/2012 |
| VALERIO, MARY | SAN FRANCISCO, CA | - | Case Manager/Care Coordinator | 05/30/2024 |
| VALLADARES-KOSS, MALIKA | GWYNN OAK, MD | BT | BCBA | 09/23/2026 |
| VALLE OLIVARES, YUSDANIS | CAPE CORAL, FL | - | RBT | 01/08/2024 |
| VALLE, KIMBERLY | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| VALLE, LAURA | ANN ARBOR, MI | - | Speech-Language Pathologist | 09/24/2026 |
| VALLE, SARAY | MONROE, NY | - | BCBA | 09/21/2026 |
| VALLE, STEPHANIE | NASHVILLE, TN | - | RBT | 09/21/2026 |
| VALLEJOS LAZO, LEONEL | KENSINGTON, MD | - | RBT | 09/25/2026 |
| VALLES, CASSANDRA | LAS CRUCES, NM | - | RBT | 09/21/2026 |
| VALLES, CRYSTAL | LOS ANGELES, CA | - | BCBA | 07/20/2023 |
| VALLEY VIEW HOSPITAL ASSOCIATIONORG | GLENWOOD SPRINGS, CO | - | Clinical Social Worker | 09/22/2026 |
| VAN BRUGGEN, INGRID | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| VAN DEMARK, ALLISON | ISELIN, NJ | - | RBT | 09/22/2026 |
| VAN GORKUM, AUTUMN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| VAN HOOGENSTYN, ALEC | GARDEN GROVE, CA | - | RBT | 09/24/2026 |
| VAN HOUTEN, STEPHANIE | LAUDERDALE LAKES, FL | LCSW | Mental Health Counselor | 05/03/2022 |
| VAN JURA, CHRISTINA | ROSELAND, NJ | LCSW | Clinical Social Worker | 12/27/2010 |
| VAN LAANEN, OLIVIA | MILWAUKEE, WI | - | Mental Health Counselor | 09/22/2026 |
| VAN METER, JENNIFER | GAITHERSBURG, MD | LCPC | Mental Health Counselor | 09/12/2019 |
| VAN OTTERLOO, JOANNA | MINNETONKA, MN | - | Professional Counselor | 10/16/2013 |
| VAN RAVENHORST, CASSANDRA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 08/03/2016 |
| VAN SCHOONHOVEN, SHERILL | WOODINVILLE, WA | - | Mental Health Counselor | 10/01/2008 |
| VANCANT, LARRY | HIGHLAND HILLS, OH | LSW | Case Manager/Care Coordinator | 04/12/2017 |
| VANCE, HARLEE | LAKEWOOD, CO | - | RBT | 09/21/2026 |
| VANDENDRIES, ELIZABETH | ATHENS, OH | - | Addiction (Substance Use Disorder) Counselor | 06/18/2018 |
| VANDER VENNET, JULIA | SANTA ROSA, CA | - | Psychologist | 09/24/2026 |
| VANDERBERG, JESSICA | BETHANY, CT | LCSW | Clinical Social Worker | 06/30/2022 |
| VANDERLAAN, JOSHUA | HUDSONVILLE, MI | - | Mental Health Counselor | 08/20/2025 |
| VANDERZANDEN, SARAH | FORT CAVAZOS, TX | LCSW | Clinical Social Worker | 01/10/2018 |
| VANNICOLA, EMILY | CAMBRIDGE, MD | - | Clinical Social Worker | 09/25/2026 |
| VANOSDEL, ROWAN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| VANPELT, DARKITA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| VANWASHENOVA, JADE | NEWARK, OH | - | Case Manager/Care Coordinator | 02/16/2026 |
| VANWYK, HAILEY | DULUTH, MN | - | RBT | 09/24/2026 |
| VANZALEN, MALLORY | GRAND RAPIDS, MI | LMSW | Clinical Social Worker | 06/05/2024 |
| VARELA, NATALIE | GLENOLDEN, PA | - | Mental Health Counselor | 07/08/2024 |
| VARGAS, JENNIFER | POMONA, CA | - | Clinical Social Worker | 08/11/2016 |
| VARGAS, VIVIAN | HORIZON CITY, TX | - | BCBA | 12/20/2024 |
| VARNEY, CHELSEA | YPSILANTI, MI | LLMSW | Clinical Social Worker | 05/31/2018 |
| VARSAMIS, LAURA | MAGNOLIA, TX | LCSW | Clinical Social Worker | 04/08/2025 |
| VASA, ISLA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| VASA, KARIE | OMAHA, NE | LIMHP | Mental Health Counselor | 01/29/2018 |
| VASCONCELLOS PASSOS P, VICTORIA | CAMBRIDGE, MA | - | Mental Health Counselor | 08/18/2026 |
| VASKE, CYNTHIA | CORALVILLE, IA | LISW | Clinical Social Worker | 08/01/2005 |
| VASKO, DOMINICK | COLUMBUS, OH | - | RBT | 09/24/2026 |
| VASQUEZ, ALEXANDER | NAPA, CA | - | RBT | 09/23/2026 |
| VASQUEZ, BLANCA | ORANGE, CA | - | Clinical Social Worker | 10/07/2019 |
| VASQUEZ, GIOVANNY | VIEW PARK, CA | - | Case Manager/Care Coordinator | 09/24/2026 |
| VASQUEZ, JAMIE | IRVINE, CA | - | RBT | 09/22/2026 |
| VASQUEZ, KATRINA JACLYN | PASADENA, CA | - | RBT | 09/22/2026 |
| VASQUEZ, MICHELLE | OXNARD, CA | - | Clinical Social Worker | 01/11/2023 |
| VASQUEZ, SABRINA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| VASQUEZ, SANDRA | CYPRESS, TX | - | Speech-Language Pathologist | 08/01/2023 |
| VASQUEZ, SOFIA | CASTRO VALLEY, CA | - | Mental Health Counselor | 09/22/2026 |
| VASWANI, VRITTI | CHELSEA, MA | - | Mental Health Counselor | 09/23/2026 |
| VATMAN, ELAINA | EAST BRUNSWICK, NJ | - | Mental Health Counselor | 09/21/2026 |
| VAUGHAN, KAYLEIGH | MOUNTAIN HOME, AR | - | RBT | 09/23/2026 |
| VAUGHN, ANGELA | FORT WORTH, TX | - | BCBA | 09/15/2026 |
| VAUGHTERS, MOLLY | CHAPEL HILL, NC | LCSWA | Clinical Social Worker | 09/25/2026 |
| VAUX, ALEXANDRIA | SINKING SPRING, PA | SLP | Speech-Language Pathologist | 05/01/2018 |
| VAWTER, SPENCER | FITCHBURG, MA | - | RBT | 09/22/2026 |
| VAZQUEZ, ANDRES | TAMPA, FL | M.S. | Mental Health Counselor | 03/23/2020 |
| VAZQUEZ, JASMINE | PALM BAY, FL | - | RBT | 09/22/2026 |
| VAZQUEZ, MAYA | WOODSIDE, NY | - | Clinical Social Worker | 09/24/2026 |
| VAZQUEZ, NATALIE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| VAZQUEZ, SARAH | HARTFORD, CT | LMSW | Clinical Social Worker | 09/21/2026 |
| VECCHIO, VIRGINIA | SAN ANTONIO, TX | - | Assistant Behavior Analyst | 01/08/2018 |
| VEGA MELENDEZ, KEISHLA | CAGUAS, PR | - | Mental Health Counselor | 12/11/2025 |
| VEGA-BLANCO, VANESSA | MCKINNEY, TX | - | Professional Counselor | 09/24/2026 |
| VEGA, AHTZIRY | LOMBARD, IL | - | RBT | 09/22/2026 |
| VEGA, BROOKE | SURPRISE, AZ | - | RBT | 09/22/2026 |
| VEGA, CAMILA | ATWATER, CA | - | Speech-Language Pathologist | 09/23/2026 |
| VEGA, JACQUELINE | KNOXVILLE, TN | RBT | BCBA | 01/20/2021 |
| VEGA, JENNIFER | SAN ANTONIO, TX | LMSW | Clinical Social Worker | 05/06/2014 |
| VEGA, NAOMI | AUSTIN, TX | - | RBT | 09/22/2026 |
| VEGO, FRANK | RIVERSIDE, CA | - | Addiction (Substance Use Disorder) Counselor | 08/07/2020 |
| VEIGA, DAMAI | MIAMI, FL | - | RBT | 09/25/2026 |
| VEKHANDE, AISHWARYA | HAYWARD, CA | - | RBT | 09/25/2026 |
| VELA BEHAVIOR HEALTH, LLCORG | WESLEY CHAPEL, FL | - | BCBA | 09/26/2026 |
| VELASCO, AILEEN | TORRANCE, CA | - | RBT | 09/22/2026 |
| VELASCO, DENISE | BALDWIN PARK, CA | - | Speech-Language Pathologist | 09/24/2026 |
| VELASQUEZ, FERMIN | SAN DIEGO, CA | MSW, ASW | Clinical Social Worker | 04/07/2025 |
| VELASQUEZ, NAYELI | COLTON, CA | MS, BCBA | BCBA | 09/23/2026 |
| VELAZQUEZ, ALEXIS | MARION, IN | - | RBT | 09/23/2026 |
| VELAZQUEZ, ANGELICA | ORLAND, CA | - | Case Manager/Care Coordinator | 02/03/2025 |
| VELAZQUEZ, KEVIN | BREA, CA | - | RBT | 09/11/2026 |
| VELEZ MATIAS, JESSENIA | DENVER, CO | - | Clinical Social Worker | 02/08/2018 |
| VELEZ, AUDREY | COLORADO SPRINGS, CO | MSW CANDIDATE | Clinical Social Worker | 09/24/2026 |
| VELEZ, KAMANI | VANCOUVER, WA | MHCA | Mental Health Counselor | 09/21/2026 |
| VELLIQUETTE, ALYSSA | TOLEDO, OH | M.ED, BCBA, COBA | BCBA | 10/02/2023 |
| VELLUZZI, AVA | WHITE PLAINS, NY | - | RBT | 09/26/2026 |
| VELTRIX REVENUE PARTNER LLCORG | SAN JOSE, CA | - | Clinic/Center | 09/23/2026 |
| VENTURA-NIETO, ERIC | MURRIETA, CA | - | RBT | 09/21/2026 |
| VERA, CAROLYN | CARROLLTON, TX | SLP INTERN | Speech-Language Pathologist | 03/17/2022 |
| VERDANT MIND AND WELLNESSORG | GREAT FALLS, MT | - | Clinical Social Worker | 09/21/2026 |
| VERLANDER, LIA | SAN BRUNO, CA | - | BCBA | 08/21/2024 |
| VERMONT, ESTEPHANIE | YUMA, AZ | LPC | Professional Counselor | 08/17/2017 |
| VERMULM, DEANNA | PORT ANGELES, WA | - | Clinical Social Worker | 05/23/2016 |
| VERSHEY, ANGELA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| VERSI, GAVIN | EDMONDS, WA | - | Mental Health Counselor | 07/31/2024 |
| VERTICAL DEPTH MENTAL HEALTH, LLCORG | JANESVILLE, WI | - | Professional Counselor | 09/21/2024 |
| VEST, ITZEL | SANTA ANA, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| VESTER, MARGARET | WILMINGTON, NC | MSW, LCSW | Clinical Social Worker | 12/27/2019 |
| VETRANO, VIKI | HILLSBOROUGH, NC | - | Professional Counselor | 07/22/2009 |
| VIBRANT LIFE THERAPY LLCORG | EUGENE, OR | - | Clinical Social Worker | 09/21/2026 |
| VICK, TANYA | ENGLEWOOD, NJ | - | Professional Counselor | 02/27/2019 |
| VICKERS, BOBBI | BRYANT, AR | - | RBT | 09/23/2026 |
| VICKERS, CHRISTINA | YAKIMA, WA | - | Mental Health Counselor | 04/20/2026 |
| VICTORES, EMILY | MIAMI, FL | - | RBT | 09/21/2026 |
| VIDA COUNSELING, LLCORG | GERMANTOWN, TN | - | Mental Health Counselor | 09/21/2026 |
| VIDA REHABILITATION CENTER PLLCORG | MCALLEN, TX | - | Speech-Language Pathologist | 03/20/2026 |
| VIEIRA DA LUZ ALMEIDA, ESTHER | KENSINGTON, MD | - | RBT | 09/25/2026 |
| VIEIRA, BIANCA | TAMPA, FL | - | BCBA | 09/08/2023 |
| VIERA, ARIANA | MIAMI, FL | - | RBT | 03/11/2026 |
| VIERA, SIU | BROOKLYN, NY | LCSW | Clinical Social Worker | 10/25/2016 |
| VIEZCAS-VALDEZ, TANYA | LAKEWOOD, CO | - | RBT | 09/22/2026 |
| VIGO, LUIS JOEL | OPA LOCKA, FL | RBT | RBT | 09/25/2026 |
| VIGON, ASHLEY | CHARLOTTE, NC | - | RBT | 09/21/2026 |
| VILA SOLA, SYLVIA | CAGUAS, PR | - | Speech-Language Pathologist | 01/10/2019 |
| VILE, MORGAN | DAVIE, FL | - | RBT | 09/23/2026 |
| VILLA, ADRIANA | RIVERSIDE, CA | - | Mental Health Counselor | 08/31/2009 |
| VILLAGE LANE COMMUNITY COUNSELINGORG | CHICO, CA | - | Mental Health Counselor | 09/23/2026 |
| VILLAGOMEZ, EVELYN | PHOENIX, AZ | - | RBT | 09/21/2026 |
| VILLAGRAN, SOPHIA | WASCO, CA | - | Addiction (Substance Use Disorder) Counselor | 02/24/2025 |
| VILLALOBOS, GISELLE | DOWNEY, CA | - | Clinical Social Worker | 08/28/2024 |
| VILLALPANDO, SABREELYN | PFLUGERVILLE, TX | MS, LPC | Professional Counselor | 07/27/2026 |
| VILLANVEVA MARITZA, MAGANA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| VILLARREAL, HILARY | MONTEBELLO, CA | - | Clinical Social Worker | 09/21/2026 |
| VILLARREAL, MAYRA | COMMERCE, CA | - | Clinical Social Worker | 12/06/2012 |
| VILLATORO, YAYLY | FARMINGTON HILLS, MI | - | RBT | 09/25/2026 |
| VILLEGAS, DAISY | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| VILLEGAS, ETHAN | COSTA MESA, CA | - | RBT | 09/25/2026 |
| VILLERALDO, DIANA | LOS ANGELES, CA | - | Clinical Social Worker | 09/21/2026 |
| VILLORENTE, MARIA VICTORIA | LONG BEACH, CA | - | RBT | 09/21/2026 |
| VINCENT, CHANDRA | SPEARFISH, SD | - | Counselor | 03/17/2025 |
| VINCENT, ELIZABETH | RALEIGH, NC | PHD, LPC | Mental Health Counselor | 10/28/2019 |
| VINCENT, XENIAH | PIKESVILLE, MD | - | RBT | 09/25/2026 |
| VINCES-RODRIGUEZ, JOELLE | EGG HARBOR TOWNSHIP, NJ | MSW, LCSW | Clinical Social Worker | 06/25/2024 |
| VINEYARD, VALERIE | SAN ANTONIO, TX | L.P.C. | Addiction (Substance Use Disorder) Counselor | 02/15/2010 |
| VINSON, DAVID | RICHMOND, VA | LPC | Professional Counselor | 09/25/2026 |
| VIOLET HEALTH CORPORG | DORAL, FL | - | Case Management Agency | 11/15/2023 |
| VIRGINIA INTEGRATED CARE INCORG | VIRGINIA BEACH, VA | - | Professional Counselor | 08/11/2025 |
| VIRGINIA MEDICAL & THERAPEUTIC SERVICESORG | MIDLOTHIAN, VA | - | Mental Health Counselor | 11/24/2017 |
| VIRKUS, AIDAN | DENVER, CO | LCSW | Clinical Social Worker | 02/04/2021 |
| VITA BEHAVIORAL CENTER LLCORG | MIAMI, FL | - | BCBA | 09/24/2026 |
| VITAL MIND MENTAL HEALTH COUNSELING PLLCORG | LINDENHURST, NY | - | Mental Health Counselor | 09/21/2026 |
| VITTORIO, SAMANTHA | MOORESVILLE, NC | BCBA | BCBA | 10/21/2024 |
| VIZCAINO, JEYDEN | ROCKAWAY, NJ | - | RBT | 09/22/2026 |
| VLAJ, BRAE | FRANKLIN, WI | LPC | Professional Counselor | 06/12/2023 |
| VLHA, REBECCA | OCALA, FL | - | RBT | 10/18/2019 |
| VO, EMILY | WORCESTER, MA | - | Mental Health Counselor | 09/24/2026 |
| VOETBERG, HANNAH | MONMOUTH, OR | LCSW | Mental Health Counselor | 09/21/2006 |
| VOIGT, RIANA | CHICAGO, IL | - | Professional Counselor | 05/15/2019 |
| VOKES, MEGAN | MUSKEGON, MI | - | Speech-Language Pathologist | 09/21/2026 |
| VOLFSON, ELLEN | NEW YORK, NY | LMSW | Clinical Social Worker | 03/13/2023 |
| VON GEMMINGEN, MITCHELL | SAINT LOUIS, MO | MA LPC | Professional Counselor | 07/30/2006 |
| VONASEK, DENISE | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| VONDERHAAR, SABRINA | MAQUOKETA, IA | LMHC, IADC | Mental Health Counselor | 11/14/2024 |
| VONDOLLEN, MEGAN | RENSSELAER, NY | LMHC-D | Mental Health Counselor | 10/28/2019 |
| VOS VERITAS HOLISTIC COUNSELINGORG | EASLEY, SC | - | Clinical Social Worker | 09/21/2026 |
| VOYLES, CODY | MEMPHIS, TN | - | BCBA | 12/06/2024 |
| VPA OF TEXAS PLLCORG | SAN ANTONIO, TX | - | Clinical Social Worker | 06/04/2006 |
| VPA PCORG | TROY, MI | - | Clinical Social Worker | 07/28/2006 |
| VPA PCORG | VIRGINIA BEACH, VA | - | Clinical Social Worker | 01/18/2010 |
| VU, AMELY | BRIGHTON, CO | LCSW | Clinical Social Worker | 01/30/2023 |
| VU, THANHVAN | MINNEAPOLIS, MN | LADC, LPCC | Addiction (Substance Use Disorder) Counselor | 01/31/2012 |
| VYAS, NEELAM | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| VZAKEINUORG | BROOKLYN, NY | - | Community/Behavioral Health Agency | 09/24/2026 |
| WADE, ANNA | ROANOKE, VA | MS, LPC, NCC | Professional Counselor | 03/21/2023 |
| WADE, ELIZABETH | FLORENCE, MA | L.M.H.C. | Mental Health Counselor | 09/17/2009 |
| WADE, EMILY | THORNTON, CO | LCSW | Clinical Social Worker | 08/11/2020 |
| WADHWANI, RISHI | COSTA MESA, CA | - | RBT | 09/24/2026 |
| WADKOWSKI, HALEY | EL SEGUNDO, CA | - | RBT | 09/25/2026 |
| WAGAR, LAURA | CANTON, GA | LPC | Professional Counselor | 07/08/2020 |
| WAGLER, EMMA | WEST DES MOINES, IA | - | RBT | 09/22/2026 |
| WAGNER, KRISTI | MATHER, CA | PHD | Psychologist | 02/27/2008 |
| WAGNER, MADISON | MADISON, WI | - | RBT | 09/24/2026 |
| WAHID, AYESHA | DALLAS, TX | LPC | Professional Counselor | 11/07/2022 |
| WAHKINNEY, NOCONI | LAWTON, OK | - | Case Manager/Care Coordinator | 09/26/2026 |
| WAHLIG, NANCY | LA JOLLA, CA | LCSW | Clinical Social Worker | 01/10/2017 |
| WAI, KHIN PHONE | CONCORD, CA | - | RBT | 09/25/2026 |
| WAKEFIELD, VICTORIA | COLTON, CA | - | RBT | 09/22/2026 |
| WAKLEY, HANNAH | MADISON HEIGHTS, MI | - | Speech-Language Pathologist | 09/22/2026 |
| WALBLAY, BRIANNA | EAST LANSING, MI | - | RBT | 05/08/2023 |
| WALGREN, SARAH | SCOTTSBLUFF, NE | LIMHP, LMFT, CPC | Professional Counselor | 04/04/2013 |
| WALKER - WARNELL, GAVIN | TAMPA, FL | - | RBT | 09/23/2026 |
| WALKER-GREEN, BRENNAN | PAPILLION, NE | M.S., CF-SLP | Speech-Language Pathologist | 09/25/2026 |
| WALKER, AARIANA | WEST CHESTER, OH | - | RBT | 09/21/2026 |
| WALKER, AMANDA | SAINT PETERS, MO | - | Mental Health Counselor | 09/21/2026 |
| WALKER, ASHLEY | LAS VEGAS, NV | - | RBT | 09/21/2026 |
| WALKER, FAITH | WEST ROXBURY, MA | LMHC | Mental Health Counselor | 04/17/2022 |
| WALKER, FELICITY | SAINT LOUIS, MO | - | RBT | 09/22/2026 |
| WALKER, GIOVANNA | WALDORF, MD | - | Speech-Language Pathologist | 09/03/2021 |
| WALKER, JAMEYUH | NASHVILLE, TN | LCSW | Clinical Social Worker | 02/15/2016 |
| WALKER, JASMINE | POMONA, CA | - | RBT | 01/03/2025 |
| WALKER, JAYDEN | HERMOSA BEACH, CA | - | RBT | 09/21/2026 |
| WALKER, JORDAN | MOUNTAIN VIEW, CA | - | RBT | 05/06/2025 |
| WALKER, JOSHUA | TORRANCE, CA | - | RBT | 09/21/2026 |
| WALKER, JOURNEY | TEXARKANA, AR | LAC | Mental Health Counselor | 04/29/2022 |
| WALKER, MICHELE | TIFTON, GA | LCSW | Clinical Social Worker | 07/12/2006 |
| WALKER, NICOLE | CAMBRIDGE, MA | LICSW | Mental Health Counselor | 02/26/2007 |
| WALKER, RUNE | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| WALKER, SUMMER | ROCKWALL, TX | LPC | Mental Health Counselor | 06/19/2025 |
| WALKER, SYDNEE | GAITHERSBURG, MD | M.A.,LGPC,NCC | Mental Health Counselor | 09/23/2026 |
| WALKER, WHITNEY | HAMMOND, LA | - | Mental Health Counselor | 08/30/2016 |
| WALL, CIANNA | SAN FRANCISCO, CA | - | Day Training/Habilitation Specialist | 09/24/2026 |
| WALL, HEATHER | FLINTSTONE, GA | MDIV, MACMH, LPC | Professional Counselor | 04/19/2023 |
| WALLACE-WOOD, DEBORA | WHITEHALL, OH | LPCC-S | Addiction (Substance Use Disorder) Counselor | 08/17/2016 |
| WALLACE, ALEX | LUDLOW FALLS, OH | MA, LMHC, LPCC-S | Mental Health Counselor | 08/01/2018 |
| WALLACE, NIYA | METAIRIE, LA | - | RBT | 09/25/2026 |
| WALLACE, SHATAVEA | WESTAMPTON, NJ | - | Counselor | 10/11/2025 |
| WALLERICH, DELANEY | PORTLAND, OR | - | Counselor | 09/21/2026 |
| WALLES, AVRAHAM | CENTENNIAL, CO | - | RBT | 09/24/2026 |
| WALLS COUNSELING PCORG | COLORADO SPRINGS, CO | - | Mental Health Counselor | 09/23/2026 |
| WALLS, ASHLEY | SANTA ANA, CA | - | RBT | 09/25/2026 |
| WALLS, BILL | STOCKTON, CA | - | Mental Health Counselor | 10/06/2020 |
| WALLSTEADT, BRADLEY | GRAND RAPIDS, MI | LMSW | Clinical Social Worker | 09/30/2019 |
| WALSH, SAMIYAH | WESTBURY, NY | - | Psychologist | 09/23/2026 |
| WALSH, SARAH | NEWBURY, MA | M.A., | Mental Health Counselor | 08/08/2014 |
| WALTER, CORINA | FORT COLLINS, CO | - | Addiction (Substance Use Disorder) Counselor | 10/16/2019 |
| WALTERS, ANNIE | ENTERPRISE, OR | - | Case Manager/Care Coordinator | 09/21/2026 |
| WALTERS, MARLI | CLOVIS, CA | - | RBT | 09/21/2026 |
| WAMAITHA, KELVIN | OLYMPIA, WA | - | Mental Health Counselor | 09/21/2026 |
| WAMRE, SOPHIE | FARGO, ND | LPCC | Professional Counselor | 11/06/2023 |
| WANG, HONGJUN | RALEIGH, NC | - | Professional Counselor | 09/22/2026 |
| WANG, JESSICA | SUNNYVALE, CA | LMFT | Mental Health Counselor | 09/21/2026 |
| WANG, JINGYI | SAN JOSE, CA | - | Specialist | 08/01/2019 |
| WANG, QINGJIE | ROCHESTER, NY | - | Specialist | 02/06/2020 |
| WANG, SHIYU | SOUTH PASADENA, CA | - | Speech-Language Pathologist | 02/27/2026 |
| WANG, YING-CHEN | WALTHAM, MA | LMHC | Mental Health Counselor | 09/24/2026 |
| WANISH, ISABELLA | GILROY, CA | - | RBT | 09/23/2026 |
| WAPLES, DAVID | YUMA, AZ | LISAC | Addiction (Substance Use Disorder) Counselor | 09/19/2006 |
| WARD, BRITTNIE | RIVERBANK, CA | - | RBT | 09/21/2026 |
| WARD, CORDIJAH | GLENDALE, CA | - | RBT | 09/25/2026 |
| WARD, FREDRICK | SALT LAKE CITY, UT | CSW | Clinical Social Worker | 10/24/2013 |
| WARD, JANAY | THIBODAUX, LA | - | Counselor | 09/07/2024 |
| WARD, JENNA | COLORADO SPRINGS, CO | PHD | Psychologist | 04/26/2021 |
| WARD, JERISSA | JOHNSON CITY, TN | - | BCBA | 09/25/2026 |
| WARD, LAURIE | MARQUETTE, MI | - | Case Manager/Care Coordinator | 09/24/2026 |
| WARD, NATALIE | SAINT JOHNS, FL | - | Mental Health Counselor | 10/04/2022 |
| WARD, RAVEN | LANCASTER, CA | - | Professional Counselor | 11/09/2019 |
| WARD, SASHA | FARMINGTON HILLS, MI | - | RBT | 09/21/2026 |
| WARE, SABRINA | BETHLEHEM, PA | LPC | Mental Health Counselor | 09/21/2026 |
| WARE, SHAKAYLA | STATESBORO, GA | LPC | Professional Counselor | 01/09/2017 |
| WARENSKI, DIANA | EL SEGUNDO, CA | - | RBT | 09/24/2026 |
| WARKOCKI, ANA | DOWNERS GROVE, IL | - | Mental Health Counselor | 12/20/2023 |
| WARREN, RILEY | SAVANNAH, GA | - | RBT | 09/24/2026 |
| WASHACK, TAYLOR | WAUKESHA, WI | - | Case Manager/Care Coordinator | 09/23/2026 |
| WASHBURN, ABIGAIL | CANFIELD, OH | - | Speech-Language Pathologist | 01/06/2021 |
| WASHINGTON, AJANSE | CHESTERFIELD, MI | - | RBT | 10/06/2022 |
| WASHINGTON, EMILIE | YOUNGSVILLE, LA | - | RBT | 09/22/2026 |
| WASHINGTON, NYAIR | CAPITOL HEIGHTS, MD | LCPC | Mental Health Counselor | 10/30/2024 |
| WASHINGTON, STEPHANIE | LOS ANGELES, CA | - | Professional Counselor | 08/14/2020 |
| WASHINGTON, TOYIA | TINLEY PARK, IL | MSW | Mental Health Counselor | 09/24/2026 |
| WASLAND, MEGAN | DULUTH, MN | BCBA | RBT | 05/09/2018 |
| WATERS, JESSICA | LINTHICUM HEIGHTS, MD | LCPC, ACS | Professional Counselor | 09/14/2012 |
| WATERS, MADELEINE | BOSTON, MA | LMHC | Mental Health Counselor | 09/07/2022 |
| WATKINS-JOHNSON, ROYESHA | NORWALK, CT | LCSW | Clinical Social Worker | 08/06/2020 |
| WATKINS, AMY | SALEM, OR | - | Mental Health Counselor | 09/21/2026 |
| WATKINS, ANNA | LUMBERTON, NC | LCSW | Clinical Social Worker | 04/16/2015 |
| WATKINS, DIANNA | LEXINGTON, KY | LPCC | Mental Health Counselor | 05/19/2022 |
| WATKINS, HEATHER | SAN ANTONIO, TX | LPC | Professional Counselor | 11/08/2017 |
| WATKINS, JADA | STATE COLLEGE, PA | - | BCBA | 09/23/2026 |
| WATKINS, RENE | DORR, MI | - | Speech-Language Pathologist | 09/24/2026 |
| WATKINS, SHAQUILLE | STRUTHERS, OH | - | Community/Behavioral Health Agency | 09/24/2026 |
| WATRO, JAMIE | BALTIMORE, MD | - | BCBA | 09/24/2026 |
| WATSON, AKEEM | ALBUQUERQUE, NM | - | Professional Counselor | 09/22/2026 |
| WATSON, CASEY | KNOXVILLE, TN | PSYD | Psychologist | 08/15/2023 |
| WATSON, MELISSA | CAMBRIDGE, MA | LICSW, LCSW | Clinical Social Worker | 06/27/2024 |
| WATTS, ELAINE | GLEN ALLEN, VA | - | Clinical Social Worker | 09/24/2026 |
| WATTS, JOYCE | LAFAYETTE, CO | MA, LPC | Mental Health Counselor | 09/20/2021 |
| WAVES OF LIFE COUNSELING & CONSULTING, PLLC.ORG | MANSFIELD, TX | - | Professional Counselor | 04/07/2026 |
| WAVES OF WELLNESS PSYCHOTHERAPY PLLCORG | FORT COLLINS, CO | - | Counselor | 07/14/2026 |
| WAYE, LAUREN | PUEBLO, CO | - | Clinical Social Worker | 12/04/2024 |
| WE ROCK THE SPECTRUM - NORTH DAKOTAORG | FARGO, ND | - | Community/Behavioral Health Agency | 09/08/2026 |
| WEATHERED REINS THERAPY LLCORG | SIERRA VISTA, AZ | - | Professional Counselor | 09/22/2026 |
| WEAVER, MICHELLE | PIKESVILLE, MD | - | RBT | 09/23/2026 |
| WEAVER, RACHEL | VISALIA, CA | MA CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| WEBB, CHEYENNE | WICHITA, KS | - | RBT | 09/23/2026 |
| WEBB, DY'MAN | EVERETT, WA | - | Counselor | 10/14/2024 |
| WEBB, MARIAH | KNOXVILLE, TN | - | RBT | 08/31/2023 |
| WEBB, MONICA | LEXINGTON, KY | LCSW | Clinical Social Worker | 05/17/2024 |
| WEBB, TIFFANY | OMAHA, NE | LIMHP, LMHP, LADC | Addiction (Substance Use Disorder) Counselor | 03/20/2020 |
| WEBB, TRINITY | GAUTIER, MS | BCBA | BCBA | 09/08/2022 |
| WEBB, TRISTIAN | KERNERSVILLE, NC | - | Professional Counselor | 12/28/2020 |
| WEBBERMAN, JOLI | FRISCO, TX | - | BCBA | 02/17/2020 |
| WEBER, ALEXIS | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| WEBER, MATTHEW | METERIE, LA | - | Assistant Behavior Analyst | 09/23/2026 |
| WEBSTER, AMBERLEE | CHICAGO, IL | - | Mental Health Counselor | 09/21/2026 |
| WEBSTER, EMILY | MINNEAPOLIS, MN | MSW, LICSW | Clinical Social Worker | 12/11/2023 |
| WEBSTER, REBECCA | DURHAM, NC | LCMHCA | Mental Health Counselor | 09/22/2026 |
| WEBSTER, RILEY | SAN DIEGO, CA | - | RBT | 03/09/2026 |
| WEBSTER, SIMONE | WOODLAND HILLS, CA | LCSW | Clinical Social Worker | 09/30/2020 |
| WEDGE, JARROD | ORLAND PARK, IL | - | RBT | 09/23/2026 |
| WEEKS MEDICAL CENTERORG | COLEBROOK, NH | - | Addiction (Substance Use Disorder) Counselor | 04/18/2012 |
| WEEKS MEDICAL CENTERORG | LANCASTER, NH | - | Addiction (Substance Use Disorder) Counselor | 07/28/2006 |
| WEEKS, JESSICA | HENDERSONVILLE, TN | LMSW | Mental Health Counselor | 09/23/2026 |
| WEEKS, KRISTEN | TROY, MI | LLPC | Professional Counselor | 09/23/2026 |
| WEEKS, SHELBY | NASHUA, NH | MA | Counselor | 01/07/2025 |
| WEEMS, SHAWN | BAKERSFIELD, CA | - | Mental Health Counselor | 09/23/2026 |
| WEGKAMP, BRYNLEE | ST GEORGE, UT | - | RBT | 09/23/2026 |
| WEGLARZ, ALLYSON | ROCHESTER HILLS, MI | - | Professional Counselor | 09/22/2026 |
| WEGNER, MARY | BATAVIA, IL | - | Speech-Language Pathologist | 08/04/2023 |
| WEGROWSKI, OLIVIA | NEW YORK, NY | - | BCBA | 09/26/2026 |
| WEI, HANA | LOMA LINDA, CA | BA | RBT | 02/19/2026 |
| WEICKERT, KERRIE-ANNE | WOODSTOCK, NY | LMHC, LPC, NCC | Mental Health Counselor | 02/01/2024 |
| WEIMAN, CHRISTIAN | LOS ANGELES, CA | - | Clinical Social Worker | 09/02/2026 |
| WEINGART, BETHANY | MINNEAPOLIS, MN | - | Professional Counselor | 09/21/2026 |
| WEINSTEIN, GARETT | LOS ANGELES, CA | - | Mental Health Counselor | 09/22/2026 |
| WEISS, BRIANNA | AURORA, CO | PSYD | Mental Health Counselor | 08/14/2024 |
| WEISS, CATHERINE | SAN FRANCISCO, CA | - | Counselor | 09/16/2020 |
| WEISS, CYNTHIA | MISHAWAKA, IN | - | RBT | 06/26/2025 |
| WEISS, LISA | CHESAPEAKE BEACH, MD | SLP | Speech-Language Pathologist | 04/06/2007 |
| WEISWASSER, JACQUELINE | PHILADELPHIA, PA | LPC | Counselor | 09/24/2026 |
| WEISZ, CHAYA | MONROE, NY | BCBA | BCBA | 09/24/2026 |
| WELAGE, JILL | WILMINGTON, OH | CCC-SLP | Speech-Language Pathologist | 09/22/2026 |
| WELCH, HEATHER | WORCESTER, MA | LICSW | Clinical Social Worker | 03/05/2020 |
| WELCH, JE'SHARI | MOYOCK, NC | - | RBT | 09/22/2026 |
| WELCH, KATHERINE | WATERBURY, CT | LCSW | Clinical Social Worker | 08/19/2020 |
| WELLEN, DAMEN | HIGHLAND PARK, IL | LCSW | Clinical Social Worker | 02/08/2016 |
| WELLNESS PATHWAYSORG | AURORA, CO | - | Case Manager/Care Coordinator | 09/24/2026 |
| WELLS-TITUS, KAMASHA | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| WELLS, ALEXA | SAN DIEGO, CA | - | Day Training/Habilitation Specialist | 08/26/2026 |
| WELLS, COURTNEY | RALEIGH, NC | - | BCBA | 08/28/2020 |
| WELLS, DANIELLE | WASHINGTON, DC | LICSW | Clinical Social Worker | 09/21/2026 |
| WELLS, EMILY | DURANT, OK | - | Case Manager/Care Coordinator | 09/21/2026 |
| WELLS, MELANIE | TEMECULA, CA | ACSW#125971 | Clinical Social Worker | 03/02/2020 |
| WELLSPRING OF LIFE CENTER, PLLCORG | FLOWER MOUND, TX | - | Clinical Social Worker | 09/21/2026 |
| WELSER, AVA | PLYMOUTH, MI | - | RBT | 09/24/2026 |
| WELTIKOL, RITA | MINOT, ND | CM | Case Manager/Care Coordinator | 05/30/2025 |
| WENDY NADOLNY, LCSW, LLCORG | CRAIG, CO | - | Clinical Social Worker | 06/22/2018 |
| WENG, JACKSON | EL CAJON, CA | - | RBT | 09/21/2026 |
| WENGER, LAURA | PALM CITY, FL | - | Mental Health Counselor | 09/24/2026 |
| WESOCKES, LAUREN | VANCOUVER, WA | SUDP | Addiction (Substance Use Disorder) Counselor | 01/29/2024 |
| WESOLOWSKI, FAITHHAYLEY | BAY CITY, MI | - | RBT | 09/22/2026 |
| WEST CINCY KIDS OPERATING CO., LLCORG | CINCINNATI, OH | - | Community/Behavioral Health Agency | 12/21/2022 |
| WEST YAVAPAI GUIDANCE CLINIC INCORG | COTTONWOOD, AZ | - | Mental Health Counselor | 09/26/2025 |
| WEST-LAWSON, SHELBY | LAS VEGAS, NV | QMHA | Mental Health Counselor | 09/23/2026 |
| WEST, AMAYA | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| WEST, KRISTA | HIAWATHA, KS | - | Psychologist | 09/23/2026 |
| WEST, KRISTIANNA | LEBANON, PA | M.S., CCC-SLP | Speech-Language Pathologist | 09/21/2026 |
| WEST, LINDSAY | LOUISVILLE, OH | LPCC | Professional Counselor | 06/03/2020 |
| WESTBROOK, MADISON | TAMPA, FL | - | RBT | 09/24/2026 |
| WESTERBERG, HANNAH | BEAVERTON, OR | - | RBT | 09/22/2026 |
| WESTERFIELD, TIFFINEY | VIRGINIA, MN | - | RBT | 03/05/2026 |
| WESTERN KENTUCKY COUNSELING SERVICES LLCORG | LEITCHFIELD, KY | - | Mental Health Counselor | 09/23/2026 |
| WESTHOF, GRACE | UNIVERSITY PLACE, WA | LMFTA | Mental Health Counselor | 06/13/2023 |
| WESTHOFF, COLE | SPRINGFIELD, MO | MS, LPC | Professional Counselor | 08/14/2018 |
| WESTON CAILLIER, AMANDA | ALVARADO, MN | LPCC | Professional Counselor | 02/25/2022 |
| WESTON, LIBRA | CLEVELAND, OH | - | Counselor | 08/26/2026 |
| WESTSIDE INTERVENTION NETWORKORG | CHICAGO, IL | - | Case Management Agency | 03/28/2026 |
| WETMORE, GABRIELLE | LEANDER, TX | - | RBT | 09/21/2026 |
| WEYER, KATELYN | EVERETT, WA | - | Clinical Social Worker | 03/06/2024 |
| WEYNAND, MINDY | PANAMA CITY, FL | RICSW | Clinical Social Worker | 09/21/2026 |
| WHALEN, DEBORAH | SANTA FE, NM | LCSW | Clinical Social Worker | 02/27/2007 |
| WHALING, LOREN | DU BOIS, PA | LCSW | Clinical Social Worker | 10/29/2020 |
| WHAT ABOUT ME COMMUNITY SERVICES LLCORG | BOISE, ID | - | Case Manager/Care Coordinator | 09/25/2026 |
| WHEATON, KATEE | FRESNO, CA | - | Clinical Social Worker | 03/15/2023 |
| WHEATON, RHONDA | ELIZABETH CITY, NC | - | RBT | 09/23/2026 |
| WHEELEHON, ANGELA | PIEDMONT, MO | LCSW | Clinical Social Worker | 01/17/2014 |
| WHEELER, CASEY | POPLAR BLUFF, MO | LPC | Professional Counselor | 07/25/2024 |
| WHEELER, JUSTIN | HARTSVILLE, SC | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| WHIPPLE, WILLIAM | BERKELEY, CA | MS, CCC-SLP | Speech-Language Pathologist | 05/17/2007 |
| WHITAKER, ALICIA | GREENSBORO, NC | - | Mental Health Counselor | 04/17/2023 |
| WHITE, ANASTASHA | TOLEDO, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| WHITE, ANDREA | APO, AE | LCSW | Clinical Social Worker | 09/21/2026 |
| WHITE, ASHLEY | CASTLE ROCK, CO | - | BCBA | 08/04/2021 |
| WHITE, CHRISTOPHER | KALAMAZOO, MI | - | RBT | 09/23/2026 |
| WHITE, GRACE | COLUMBUS, OH | - | RBT | 09/23/2026 |
| WHITE, IMANI | FOREST HILL, MD | - | RBT | 09/22/2026 |
| WHITE, JESSE | MILWAUKIE, OR | QMHA | Case Management Agency | 03/19/2010 |
| WHITE, LAURA | TRENTON, MI | MA, LLC | Mental Health Counselor | 09/22/2026 |
| WHITE, LEIGHA | SAGINAW, MI | - | Clinical Social Worker | 09/23/2026 |
| WHITE, MYRA | LONG BEACH, CA | - | Day Training/Habilitation Specialist | 03/29/2007 |
| WHITE, RALENNA | COEUR D ALENE, ID | - | RBT | 09/23/2026 |
| WHITE, SWAE | COLORADO SPRINGS, CO | - | RBT | 09/24/2026 |
| WHITE, TANISHA | LONG BEACH, CA | - | Clinical Social Worker | 02/08/2017 |
| WHITE, TAYRELLE | NEWTON, MA | - | RBT | 09/23/2026 |
| WHITE, TEBISI | KENT, WA | - | RBT | 09/24/2026 |
| WHITEHEAD, ANJA | SCRANTON, PA | MS | Professional Counselor | 05/01/2024 |
| WHITEHEAD, PRECIOUS | FARMINGTON HILLS, MI | - | RBT | 06/10/2026 |
| WHITELY, MONICA | LAWTON, OK | MS, LMFT-S | Counselor | 05/24/2017 |
| WHITING, HALLIE | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| WHITINGER, NICOLE | GREENVILLE, SC | RBT | RBT | 09/24/2026 |
| WHITMER, GABRIELA | CENTENNIAL, CO | MA, LPC | Professional Counselor | 07/27/2020 |
| WHITMORE-GLOVER, KRISTINA | DALLAS, TX | - | Professional Counselor | 05/11/2023 |
| WHITNEY, ALEXA | COON RAPIDS, MN | - | RBT | 09/25/2026 |
| WHITNEY, TABAITHA | SAN DIEGO, CA | - | Mental Health Counselor | 09/24/2026 |
| WHITSON, JEAN | FULLERTON, CA | - | Speech-Language Pathologist | 09/21/2026 |
| WHITT, MICHAEL | RICHMOND, TX | PH.D, LPC | Professional Counselor | 03/12/2013 |
| WHITTEMORE, JOCELYN | FAIRFIELD, CA | - | Speech-Language Pathologist | 09/22/2026 |
| WHITTENBERG, MARCUS | GARDEN GROVE, CA | - | RBT | 07/14/2017 |
| WHITTINGHILL-ENGRAM, NATASHA | COOKEVILLE, TN | - | RBT | 09/21/2026 |
| WHITZELL, LUCIANA | ORANGE, CA | - | RBT | 09/21/2026 |
| WHOLISTIC HEALING MINISTRIES LLCORG | SOUTHFIELD, MI | - | Mental Health Counselor | 07/02/2026 |
| WIDMAN, BRIANNA | PALM SPRINGS, CA | MHW | Clinical Social Worker | 10/08/2020 |
| WIDNER, ABBY | RICHMOND, VA | - | Speech-Language Pathologist | 09/23/2026 |
| WIERNIK, PAYTON | BOYNTON BEACH, FL | BCBA | BCBA | 08/05/2025 |
| WIGGINS, BIANCA | STOCKBRIDGE, GA | - | RBT | 11/10/2025 |
| WIGGINS, ELAURIA | GARDENA, CA | - | RBT | 04/24/2023 |
| WIGGINS, JAVION | CONCORD, CA | - | RBT | 09/14/2026 |
| WIGGINTON, COURTNEY | AUSTIN, TX | BCBA, MS | BCBA | 09/21/2026 |
| WIGHT, MYLEIGH | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| WILCOXEN, HILARI | EGG HARBOR TOWNSHIP, NJ | - | RBT | 10/31/2025 |
| WILD CLARITY LLCORG | BREVARD, NC | - | Clinical Social Worker | 09/22/2026 |
| WILD PERENNIAL THERAPY LLCORG | PORTLAND, OR | - | Clinical Social Worker | 09/14/2026 |
| WILD, ALEXANDRA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| WILDFLOWER CONSULTING LLCORG | FORT COLLINS, CO | - | Clinical Social Worker | 09/23/2026 |
| WILDFLOWER COUNSELING, LLCORG | ALBUQUERQUE, NM | - | Community/Behavioral Health Agency | 08/04/2022 |
| WILDFLOWER TRAUMA AND WELLNESS LLCORG | BRISTOL, CT | - | Mental Health Counselor | 09/22/2026 |
| WILES, JACQUELYN | ENGLEWOOD, NJ | LPC | Mental Health Counselor | 02/23/2023 |
| WILES, SARAH | MILWAUKEE, WI | CCC-SLP | Speech-Language Pathologist | 07/23/2020 |
| WILEY, NICOLE | SAINT PAUL, MN | LISW | Clinical Social Worker | 05/15/2008 |
| WILFONG, AMBER | SAN ANTONIO, TX | - | RBT | 11/03/2017 |
| WILFORD, MARIA | APO, AE | - | RBT | 05/12/2022 |
| WILKERSON, MADELINE | OWENSBORO, KY | M.S, CFY/SLP | Speech-Language Pathologist | 09/24/2026 |
| WILKINS, MARQUITA | JACKSON, MS | LPC | Professional Counselor | 01/18/2013 |
| WILLA-MAE WELLNESS LLCORG | MAYS LANDING, NJ | - | Clinical Social Worker | 09/21/2026 |
| WILLAMETTE VALLEY PSYCHOLOGICAL SERVICES LLCORG | SALEM, OR | - | Mental Health Counselor | 12/09/2024 |
| WILLARD, NATALIE | WEST MONROE, LA | M.A., PLPC, PLMFT | Counselor | 09/23/2022 |
| WILLCOX, EMANI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| WILLETT, MARIA | SAVANNAH, GA | LPC | Professional Counselor | 08/15/2017 |
| WILLIAM CURTINORG | PHILADELPHIA, PA | - | Clinical Social Worker | 01/13/2026 |
| WILLIAMS JONES, JALYNN | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| WILLIAMS, ALEXIS | MACON, GA | - | RBT | 09/23/2026 |
| WILLIAMS, ANDREW | PENSACOLA, FL | RBT | BCBA | 09/22/2026 |
| WILLIAMS, ANIYA | SPARKS, MD | - | RBT | 09/22/2026 |
| WILLIAMS, AUBREY | CINCINNATI, OH | - | Psychologist | 06/29/2020 |
| WILLIAMS, BERRY | BLUE ASH, OH | LPCC | Professional Counselor | 01/24/2020 |
| WILLIAMS, BRANDON | LOS ANGELES, CA | - | Day Training/Habilitation Specialist | 08/07/2024 |
| WILLIAMS, BREEANN | CYPRESS, TX | - | RBT | 09/24/2026 |
| WILLIAMS, BRENNA | FRESNO, CA | - | RBT | 09/24/2026 |
| WILLIAMS, BRITTANY | GAINESVILLE, GA | LAPC | Mental Health Counselor | 09/24/2026 |
| WILLIAMS, BRITTNEY | KEYSER, WV | - | Mental Health Counselor | 09/23/2026 |
| WILLIAMS, CAMERON | MARION, IN | - | RBT | 09/23/2026 |
| WILLIAMS, CHEYENNE | IRVINE, CA | - | RBT | 01/06/2023 |
| WILLIAMS, CORINNE | MONROE, NC | - | Case Manager/Care Coordinator | 03/23/2026 |
| WILLIAMS, CORTNEY | FRESNO, CA | - | Day Training/Habilitation Specialist | 08/18/2022 |
| WILLIAMS, CYNTHIA | TUCSON, AZ | - | RBT | 09/23/2026 |
| WILLIAMS, DANIEL | TORRANCE, CA | - | RBT | 09/23/2026 |
| WILLIAMS, DESIRAE | FLORISSANT, MO | ED. D., LPC, NCC | Counselor | 09/23/2026 |
| WILLIAMS, DREMON | SMYRNA, TN | - | RBT | 09/23/2026 |
| WILLIAMS, EBONY | BROOKLYN, NY | LCSW | Clinical Social Worker | 01/22/2020 |
| WILLIAMS, ERINN | CHICAGO, IL | LCPC | Professional Counselor | 06/28/2016 |
| WILLIAMS, FATHIA | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| WILLIAMS, FELICIA | WAXAHACHIE, TX | LPC | Professional Counselor | 03/12/2026 |
| WILLIAMS, GARRETT | NORTHPORT, AL | - | Professional Counselor | 09/23/2026 |
| WILLIAMS, HEATHER | JONESBORO, GA | - | Professional Counselor | 08/19/2021 |
| WILLIAMS, HEIDI | MARSHALLTOWN, IA | - | Mental Health Counselor | 09/21/2026 |
| WILLIAMS, ISAIAH | LOS ANGELES, CA | - | Clinical Social Worker | 08/23/2024 |
| WILLIAMS, JACQUELINE | FOREST HILLS, NY | LCSW-R | Clinical Social Worker | 09/22/2026 |
| WILLIAMS, JAKIYN | FARMERVILLE, LA | - | Case Manager/Care Coordinator | 09/23/2026 |
| WILLIAMS, JAMESHA | ANGLETON, TX | - | RBT | 09/23/2026 |
| WILLIAMS, JASMINE | BROOKLYN, NY | - | Clinical Social Worker | 11/10/2016 |
| WILLIAMS, JASON | CHAPIN, SC | LPC | Counselor | 01/12/2022 |
| WILLIAMS, JENNIFER | KIRKSEY, KY | LCSW | Clinical Social Worker | 12/13/2016 |
| WILLIAMS, JODI | SPOKANE, WA | MSW, APSW, LCSW | Clinical Social Worker | 04/25/2023 |
| WILLIAMS, KATHERINA | DENVER, CO | - | Counselor | 09/25/2026 |
| WILLIAMS, KEITA | HENDERSON, NV | CPC-I | Mental Health Counselor | 09/21/2026 |
| WILLIAMS, KELSEY | AUSTIN, TX | LCSW | Clinical Social Worker | 09/21/2026 |
| WILLIAMS, KEVONNA | DEERFIELD BEACH, FL | - | RBT | 09/22/2026 |
| WILLIAMS, LAVITTA | SPOKANE, WA | - | Clinical Social Worker | 03/18/2021 |
| WILLIAMS, MARVA | KNOXVILLE, TN | M.DIV, MA, LPC | Professional Counselor | 07/12/2018 |
| WILLIAMS, MICHELE | REDDING, CA | RATC | Addiction (Substance Use Disorder) Counselor | 07/01/2021 |
| WILLIAMS, PARIS | COLUMBIA, MD | - | RBT | 09/26/2026 |
| WILLIAMS, SEMONE | AUGUSTA, GA | IBCLC | Specialist | 03/31/2022 |
| WILLIAMS, SHANICE | HUNTSVILLE, AL | - | RBT | 12/05/2024 |
| WILLIAMS, SHERRI | REIDSVILLE, GA | ED.S, LPC, ACS, NCC | Counselor | 09/25/2026 |
| WILLIAMS, SOPHIA | MARY ESTHER, FL | - | BCBA | 11/06/2019 |
| WILLIAMS, STEPHEN | WEST PLAINS, MO | - | RBT | 09/22/2026 |
| WILLIAMS, SUKITA | REYNOLDSBURG, OH | - | Case Manager/Care Coordinator | 09/23/2026 |
| WILLIAMS, TIAJUANA | ABILENE, TX | - | Clinical Social Worker | 09/25/2026 |
| WILLIAMS, TRISTINA | NORTH LITTLE ROCK, AR | LAC | Counselor | 04/03/2019 |
| WILLIAMSON, JILL | WEST COLUMBIA, SC | MA, CCC-SLP | Speech-Language Pathologist | 05/22/2008 |
| WILLIAMSON, NIKITA | MESA, AZ | M.S., SLP-CF | Speech-Language Pathologist | 09/22/2026 |
| WILLIS-CASH, EVENING | PORTLAND, OR | LCSW | Clinical Social Worker | 10/27/2014 |
| WILLIS, KAVORI | SHREVEPORT, LA | BS- PSYCHOLOGY | Case Manager/Care Coordinator | 09/22/2026 |
| WILLIS, PHYLLIS | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| WILLIS, SIERA | HOUSTON, TX | - | Professional Counselor | 09/26/2026 |
| WILLOW CREEK YOUTH PARTNERSHIPORG | WILLOW CREEK, CA | - | Community/Behavioral Health Agency | 09/25/2026 |
| WILLOW TREE COMMUNITY SERVICES LLCORG | SPARTA, NJ | - | Addiction (Substance Use Disorder) Counselor | 09/25/2026 |
| WILLS, PAULA | CENTENNIAL, CO | MA, LPC | Mental Health Counselor | 07/08/2024 |
| WILMOTH, KRISTI | ADA, OK | - | Case Manager/Care Coordinator | 09/22/2026 |
| WILSON GONZALEZ, STEPHANIE | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 10/17/2024 |
| WILSON-CASTEEL, GARA | LEXINGTON, KY | LPCC | Professional Counselor | 11/18/2014 |
| WILSON, AJONAY | SAN DIEGO, CA | - | RBT | 09/22/2026 |
| WILSON, ALEXIS | COAL GROVE, OH | CMS | Case Manager/Care Coordinator | 02/17/2021 |
| WILSON, CARLY | ISELIN, NJ | - | RBT | 09/22/2026 |
| WILSON, CAROLYN | DISTRICT HEIGHTS, MD | - | RBT | 07/11/2023 |
| WILSON, CRYSTAL | PALMER, AK | - | Addiction (Substance Use Disorder) Counselor | 09/23/2026 |
| WILSON, CRYSTAL | HOUSTON, TX | LPC-ASSOCIATE | Mental Health Counselor | 09/25/2026 |
| WILSON, EKISHA | NORTH LAS VEGAS, NV | - | Case Manager/Care Coordinator | 06/07/2023 |
| WILSON, FAITH | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| WILSON, JAMES | TAMPA, FL | - | RBT | 09/22/2026 |
| WILSON, JOCELINE | RIVERBANK, CA | - | RBT | 09/21/2026 |
| WILSON, KEHERA | AUBREY, TX | - | RBT | 09/22/2026 |
| WILSON, LISA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| WILSON, MAKILYA | FRISCO, TX | - | RBT | 09/23/2026 |
| WILSON, MELISSA | JEFFERSONVILLE, IN | LCSW | Clinical Social Worker | 11/20/2012 |
| WILSON, RACHEL | HICKORY, NC | - | RBT | 09/23/2026 |
| WILSON, SADIE | GREEN BAY, WI | LPC-IT | Professional Counselor | 05/26/2020 |
| WILSON, SAMARA | HARRISBURG, PA | MA, LBS, BCBA | BCBA | 09/21/2026 |
| WILSON, TATUM | SAINT LOUIS, MO | - | RBT | 06/02/2026 |
| WILSON, TOMEKA | FAYETTEVILLE, NC | - | Assistant Behavior Analyst | 06/03/2021 |
| WILSON, TONYIA | ADEL, GA | LPC | Professional Counselor | 09/06/2013 |
| WILT, MEGAN | NEW MARTINSVILLE, WV | - | Speech-Language Pathologist | 09/21/2026 |
| WILWOHL, LARYSSA | ALIQUIPPA, PA | - | Counselor | 11/18/2025 |
| WIMER, CHRISTIAN | SAN JOSE, CA | - | Professional Counselor | 05/25/2023 |
| WINDER, CRYSTAL | MARKHAM, IL | - | Mental Health Counselor | 09/23/2026 |
| WING, LESLIE | LYONS, NY | - | Mental Health Counselor | 09/19/2022 |
| WINGARD, ELIZABETH | ANN ARBOR, MI | MSW | Clinical Social Worker | 05/20/2024 |
| WINGER, SHAMICO | CORDOVA, TN | - | Addiction (Substance Use Disorder) Counselor | 09/22/2026 |
| WINGFIELD, JA'NEA | LIVE OAK, CA | - | Counselor | 09/22/2026 |
| WINKLER, TIMOTHY | PEORIA, IL | - | Mental Health Counselor | 09/21/2026 |
| WINN, DEBORAH | SAVOY, IL | LCPC | Professional Counselor | 01/22/2018 |
| WINSOME THERAPY CLINIC LLCORG | BILLINGS, MT | - | BCBA | 04/10/2023 |
| WINSTON, ASHANTI | DECATUR, GA | - | RBT | 09/25/2026 |
| WINSTON, DANIELLE | MILWAUKEE, WI | PSYD | Psychologist | 11/17/2017 |
| WINTER, AUSTIN | WOODBURY, MN | - | RBT | 09/23/2026 |
| WINTER, JAMIE | BURNSVILLE, MN | LAMFT | Mental Health Counselor | 09/25/2026 |
| WINTERS, MADALYNN | ROSEMOUNT, MN | - | Speech-Language Pathologist | 07/09/2026 |
| WINTLEND, MADILYNN | MADISON, WI | - | Mental Health Counselor | 09/22/2026 |
| WINTRINGHAM, ELIZABETH | TOLEDO, OH | - | Case Manager/Care Coordinator | 05/08/2018 |
| WIRTZ, NEVAEH | SAN BERNARDINO, CA | - | RBT | 09/23/2026 |
| WISE MIND BEHAVIORALORG | FREDERICK, MD | - | Mental Health Counselor | 08/21/2025 |
| WISEMAN, VICTORIA | WORTHINGTON, OH | - | Speech-Language Pathologist | 09/23/2026 |
| WISILOSKY, MACY | CORAL GABLES, FL | - | RBT | 09/21/2026 |
| WITT, MEGAN | FORT LIBERTY, NC | LCSW | Clinical Social Worker | 11/29/2023 |
| WITT, NATALIE | ELMIRA, NY | - | Counselor | 02/07/2025 |
| WITTE, AUDRA | WESTFIELD, NJ | - | RBT | 09/22/2026 |
| WITTE, BREANA | ROSEMOUNT, MN | CCC-SLP | Speech-Language Pathologist | 06/27/2014 |
| WITTMAN, CAROLINE | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/08/2022 |
| WITZANSKY, DENISE | SAPULPA, OK | LPC | Professional Counselor | 04/21/2013 |
| WLADYKA, ERIN | BRECKSVILLE, OH | M.S. CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| WOEHRLE, ELIANNA | DALY CITY, CA | - | RBT | 09/25/2026 |
| WOELFEL, TAYLOR | OVERLAND PARK, KS | RBT | RBT | 09/23/2026 |
| WOITEL, ASHLEY | DICKINSON, ND | - | Professional Counselor | 05/11/2026 |
| WOLEK, STEFFANI | GLENVILLE, NY | - | Speech-Language Pathologist | 09/01/2020 |
| WOLF KEENE, SYDNEY | SACO, ME | LCSW | Clinical Social Worker | 08/20/2026 |
| WOLFE, CAITLYN | TUCSON, AZ | MS, CCC-SLP | Speech-Language Pathologist | 08/28/2025 |
| WOLFE, JILIAN | REDMOND, OR | CADC 1 | Addiction (Substance Use Disorder) Counselor | 10/26/2021 |
| WOLFE, JORDAN | LEBANON, OH | - | Mental Health Counselor | 09/24/2026 |
| WOLFE, MARI | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| WOLFE, SAVANNAH | PLANO, TX | RBT | RBT | 09/21/2026 |
| WOLFORD, FAYTHE | RIPON, CA | - | RBT | 09/21/2026 |
| WOLLMAN, JORDYN | WYOMING, MI | - | RBT | 09/24/2026 |
| WOLSKI, NATALIE | CHARDON, OH | LISW | Clinical Social Worker | 03/04/2021 |
| WOLSKY PROCTOR, MARLA | HOUSTON, TX | LPC | Mental Health Counselor | 09/09/2021 |
| WOLZ, MACKENZIE | TAYLORSVILLE, KY | - | Clinical Social Worker | 07/24/2023 |
| WOMBOLD, DESTANIE | ATHENS, OH | LSW | Case Manager/Care Coordinator | 07/27/2026 |
| WONG, FRANCES | SAN ANTONIO, TX | LPC-S | Counselor | 04/17/2020 |
| WONG, MATTHEW | WANTAGH, NY | - | BCBA | 09/26/2026 |
| WONG, WAVERLY | SANTA BARBARA, CA | - | Day Training/Habilitation Specialist | 09/22/2026 |
| WOOD, ALEXIS | GRAND RAPIDS, MI | - | RBT | 09/22/2026 |
| WOOD, ASHLEY | GRAND RAPIDS, MI | LMSW | Clinical Social Worker | 03/24/2022 |
| WOOD, FELISHA | LITTLETON, CO | - | Case Manager/Care Coordinator | 09/21/2026 |
| WOOD, GRETCHEN | COLUMBUS, GA | MA, LMHC, NCC | Mental Health Counselor | 01/20/2023 |
| WOOD, KARLEKE | SOUTHAVEN, MS | LMSW | Clinical Social Worker | 08/25/2026 |
| WOOD, MATTHEW | SOUTH OGDEN, UT | - | RBT | 04/28/2023 |
| WOOD, SARAH | LINCOLNTON, NC | LCSWA | Clinical Social Worker | 08/19/2026 |
| WOOD, THOMAS | APPLETON, WI | LCSW | Clinical Social Worker | 05/18/2020 |
| WOOD, WENDY | WASHINGTON, DC | - | Counselor | 09/21/2026 |
| WOODARD, ZRYAIH | COLLEGE STATION, TX | - | RBT | 09/21/2026 |
| WOODCOCK, ERIN | CLYO, GA | LCSW | Clinical Social Worker | 09/24/2026 |
| WOODMAN, SANDRA | SOMERSWORTH, NH | MA, LCMHC | Mental Health Counselor | 07/09/2014 |
| WOODRICK, MADISON | GRAND RAPIDS, MI | LLPC | Professional Counselor | 11/15/2022 |
| WOODS, KHALIL | CINCINNATI, OH | - | Case Manager/Care Coordinator | 09/26/2026 |
| WOODS, KOJO | COLUMBIA, MD | - | RBT | 09/23/2026 |
| WOODS, PAULA | LA PLACE, LA | - | Case Manager/Care Coordinator | 05/12/2021 |
| WOODSON, APRIL | RALEIGH, NC | MSW, LCSW | Clinical Social Worker | 12/20/2020 |
| WOODWARD, KYRAH | WALNUT CREEK, CA | - | RBT | 09/25/2026 |
| WOODWARD, MATTHEW | HOMER, AK | - | Case Manager/Care Coordinator | 09/21/2026 |
| WOOLRIDGE, JERMISHA | RALEIGH, NC | LCSW | Clinical Social Worker | 09/25/2026 |
| WOOLSEY, JADE | WACO, TX | - | RBT | 09/23/2026 |
| WOOTEN, STEPHANIE | EVERETT, WA | MA, AAC-R | Mental Health Counselor | 02/24/2025 |
| WORDSWORTH, WILLIMINA | LESTER, PA | - | Mental Health Counselor | 09/22/2026 |
| WORK, JOANNA | JACKSON, MI | LLPC | Mental Health Counselor | 11/11/2025 |
| WORKERS COMP CONSULTING SERVICES LLCORG | ERIE, PA | - | Case Manager/Care Coordinator | 02/23/2018 |
| WORKLIFECO PLLCORG | RALEIGH, NC | - | Mental Health Counselor | 08/25/2026 |
| WORKS OF WONDERORG | ROME, GA | - | Clinical Social Worker | 02/18/2022 |
| WORLD MENTAL HEALTH ORGANIZATIONORG | DETROIT, MI | - | Case Management Agency | 09/21/2026 |
| WORLD MENTAL HEALTH ORGANIZATIONORG | DETROIT, MI | - | Case Management Agency | 01/07/2022 |
| WORLDS, MARY | HORN LAKE, MS | - | Clinical Social Worker | 11/24/2007 |
| WORLEY, SIMONE | MERIDEN, CT | LPC | Professional Counselor | 09/23/2026 |
| WORM, MELISSA | ROSEMOUNT, MN | - | Speech-Language Pathologist | 09/23/2026 |
| WORNER, LINDSEY | LEBANON, OH | - | Speech-Language Pathologist | 02/20/2026 |
| WORRELL, RODGANAE | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| WORSHIP, DANISHA | LOS ANGELES, CA | - | Addiction (Substance Use Disorder) Counselor | 09/10/2024 |
| WORTH, EMILY | TAMPA, FL | MS, CCC-SLP | Speech-Language Pathologist | 09/23/2026 |
| WORTHEN, ANGELA | SAINT LOUIS, MO | - | RBT | 09/23/2026 |
| WRAY, RALPH | NEWPORT, AR | LPC | Professional Counselor | 08/24/2009 |
| WRIGHT, ANUSARA | BOISE, ID | LCPC-6986 | Mental Health Counselor | 03/20/2012 |
| WRIGHT, BREANNA | AUSTIN, TX | LPC, NCC | Professional Counselor | 12/06/2022 |
| WRIGHT, CHAUNTE | SOUTHFIELD, MI | - | RBT | 09/24/2026 |
| WRIGHT, DEVAN | IRVING, TX | LPC | Professional Counselor | 09/24/2025 |
| WRIGHT, ELIZABETH | RIVERVIEW, FL | - | BCBA | 08/08/2020 |
| WRIGHT, KAYLA | UNION CITY, CA | - | Speech-Language Pathologist | 09/01/2017 |
| WRIGHT, KRISTOPHER | NORTH LITTLE ROCK, AR | - | RBT | 09/21/2026 |
| WRIGHT, MATTHEW | TOLEDO, OH | - | Counselor | 12/01/2022 |
| WRIGHT, MIKETA | PITTSBURGH, PA | - | RBT | 09/24/2026 |
| WRIGHT, PORTIA | LAKE ELSINORE, CA | - | BCBA | 09/23/2026 |
| WRIGHT, RASHEEDA | NEW BRITAIN, CT | LCSW | Clinical Social Worker | 09/22/2026 |
| WRIGHT, RENEE | NUTLEY, NJ | - | BCBA | 09/21/2026 |
| WRIGHT, SHELLYMARIE | BATAVIA, IL | - | Mental Health Counselor | 09/21/2026 |
| WRONA, KYRA | TOPEKA, KS | - | Professional Counselor | 06/15/2022 |
| WRONSKI, JENNA | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| WU, JENNA | SAN DIEGO, CA | - | Clinical Social Worker | 01/06/2020 |
| WU, MENG ZE | ALHAMBRA, CA | - | RBT | 09/25/2026 |
| WUERTZ, ADRIAN | ONTARIO, OH | - | RBT | 09/21/2026 |
| WYANT, MICHAEL | ELYRIA, OH | LICDC | Addiction (Substance Use Disorder) Counselor | 03/28/2017 |
| WYATT OKEEFE THERAPY LLCORG | SPOKANE, WA | - | Mental Health Counselor | 09/22/2026 |
| WYKOFF, LINSAY | JACKSON, MI | LPC | Mental Health Counselor | 02/20/2023 |
| WYNDMOOR MIND & WELLNESSORG | CHERRY HILL, NJ | - | Clinical Social Worker | 09/25/2026 |
| WYNN, ALEXIS | DAYTON, OH | - | Case Manager/Care Coordinator | 09/22/2026 |
| WYSE, JEREMY | OWOSSO, MI | - | RBT | 09/21/2026 |
| XIONG, KRISTA | MANTECA, CA | - | BCBA | 09/22/2026 |
| YAHYA, SAYDAH | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| YALUNG, CHARLOTTE | MARTINEZ, GA | - | RBT | 09/25/2026 |
| YAMANOUCHI, KIMIYO | HONOLULU, HI | - | RBT | 09/24/2026 |
| YAMAUCHI, BROOKE | GARDEN GROVE, CA | - | BCBA | 02/05/2019 |
| YAN, YE | FREMONT, CA | - | RBT | 09/22/2026 |
| YANEZ, JANET | EDEN PRAIRIE, MN | ADCT | Addiction (Substance Use Disorder) Counselor | 09/24/2026 |
| YANEZ, JOSE | ANTHONY, NM | MA | Case Manager/Care Coordinator | 09/26/2007 |
| YANG, ALVERY | BRIGHTON, CO | - | RBT | 09/21/2026 |
| YANG, BRIANNA | COSTA MESA, CA | - | RBT | 09/21/2026 |
| YANG, JUNWEN | FLUSHING, NY | - | Case Manager/Care Coordinator | 09/24/2026 |
| YANG, LEE | RIVERBANK, CA | - | RBT | 09/21/2026 |
| YANG, TERESA | LOS ANGELES, CA | - | Clinical Social Worker | 03/04/2024 |
| YANG, YIWEN | NEW YORK, NY | - | Mental Health Counselor | 12/26/2023 |
| YAO, LIEZEL JOY | CORONA, CA | - | RBT | 09/26/2026 |
| YAP, JUSTIN | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| YAP, ZACHARY | HILLSDALE, MI | - | Speech-Language Pathologist | 01/11/2019 |
| YARBROUGH, ANGEL | OLYMPIA, WA | - | Case Manager/Care Coordinator | 09/23/2026 |
| YARWOOD, SARAH | BOWLING GREEN, KY | - | Speech-Language Pathologist | 05/06/2024 |
| YASGAR, ASHLEY | SIOUX FALLS, SD | - | Clinical Social Worker | 10/27/2025 |
| YASMIN TAMAYO PCORG | LAS VEGAS, NV | - | Clinical Social Worker | 01/08/2026 |
| YATES, ASHLEY | LOS ANGELES, CA | - | Clinical Social Worker | 09/23/2026 |
| YATES, MELISSA | CHASKA, MN | MSW, LICSW | Clinical Social Worker | 12/02/2024 |
| YATESMITH, LILLIAN | KINGSPORT, TN | LCSW | Clinical Social Worker | 02/02/2022 |
| YCO, SIENA | SAN JOSE, CA | - | Day Training/Habilitation Specialist | 09/10/2026 |
| YEAGER, EMMA | NACOGDOCHES, TX | LCSW | Clinical Social Worker | 09/22/2026 |
| YEAGER, KIM | INDIANAPOLIS, IN | LCSW | Clinical Social Worker | 03/23/2007 |
| YEAGER, TRISTAN | FARMINGTON HILLS, MI | - | RBT | 09/22/2026 |
| YERKE, ERICA | MOUNT POCONO, PA | LCSW | Clinical Social Worker | 05/08/2023 |
| YES AND THERAPY, PLLCORG | INDIAN HEAD PARK, IL | - | Clinical Social Worker | 09/22/2026 |
| YEUNG, ANGELES | NEW YORK, NY | - | Mental Health Counselor | 09/24/2026 |
| YI, LAUREN | HUTTO, TX | - | Mental Health Counselor | 09/24/2026 |
| YOFFIE, ERIN | DES PERES, MO | PA-C | Specialist | 05/16/2008 |
| YOGA4CHANGEORG | NEW HAVEN, CT | - | Clinical Social Worker | 09/22/2026 |
| YOGGERST, LAUREN | SPRINGFIELD, IL | LCPC | Professional Counselor | 09/23/2026 |
| YOO, ESTHER | PLACENTIA, CA | - | Speech-Language Pathologist | 09/23/2026 |
| YOPP WELLNESS AND THERAPYORG | MIDDLETOWN, CT | - | Professional Counselor | 09/22/2026 |
| YORK, ALLISSA | ALLEN, TX | BCBA | BCBA | 05/09/2019 |
| YOSSEF, EMEY | TUSTIN, CA | - | RBT | 03/04/2022 |
| YOU CAN DO IT, LLCORG | ALBUQUERQUE, NM | - | Community/Behavioral Health Agency | 09/22/2026 |
| YOU GOT THIS, LLCORG | DELAND, FL | - | Clinical Social Worker | 09/21/2026 |
| YOU, XINGXUE | PALO ALTO, CA | - | RBT | 09/23/2026 |
| YOUNCE, MARY | LENOIR, NC | - | Speech-Language Pathologist | 09/23/2026 |
| YOUNG BRIDGE SUPPORT SERVICE INC.ORG | GREENSBORO, NC | - | Community/Behavioral Health Agency | 09/25/2026 |
| YOUNG-ELIGON, LACHELLE | RIVERVIEW, FL | - | Mental Health Counselor | 09/21/2026 |
| YOUNG, CAMERON | VENICE, CA | - | Clinical Social Worker | 01/12/2021 |
| YOUNG, DIANNA | BATON ROUGE, LA | - | Case Manager/Care Coordinator | 09/24/2026 |
| YOUNG, HANN LI | ANAHEIM, CA | - | RBT | 03/19/2024 |
| YOUNG, KARI | FESTUS, MO | LPC | Professional Counselor | 12/06/2022 |
| YOUNG, KATHERINE | SUMMERSVILLE, WV | - | Counselor | 09/24/2026 |
| YOUNG, KATIE | RUSH, KY | LCSW | Clinical Social Worker | 01/30/2023 |
| YOUNG, KENDALL | RONKONKOMA, NY | - | BCBA | 09/24/2026 |
| YOUNG, KIMBERLY | CONCORD, CA | - | RBT | 09/02/2026 |
| YOUNG, LAUREN | SUMMERVILLE, SC | LMSW | Clinical Social Worker | 12/30/2019 |
| YOUNG, MIRANDA | EL SEGUNDO, CA | - | RBT | 09/23/2026 |
| YOUNG, RAYNEE | INDIANAPOLIS, IN | - | RBT | 05/29/2025 |
| YOUNG, SHAKAYLA | EL SEGUNDO, CA | - | RBT | 07/24/2024 |
| YOUNG, SHARI | MESA, AZ | MS, CCC-SLP | Speech-Language Pathologist | 02/14/2024 |
| YOUNG, SHELBY | GLENDALE, AZ | LCSW | Clinical Social Worker | 11/14/2022 |
| YOUNG, TERESA | COLUMBUS, OH | PH.D. | Psychologist | 07/26/2010 |
| YOUNG, VESLA | VESTAVIA HILLS, AL | - | RBT | 09/21/2026 |
| YOUNGBLOOD, MELISSA | TROY, MI | L.P.C. | Professional Counselor | 12/17/2007 |
| YOUNGER, ARABEL | SOMERVILLE, MA | - | Counselor | 01/26/2022 |
| YOUNGER, TABITHA | CONYERS, GA | LCSW | Clinical Social Worker | 09/21/2026 |
| YOUNGREN, MACKENZIE | EVERETT, WA | - | RBT | 05/01/2023 |
| YOUR DIVINE JOURNEY, LLCORG | WINDSOR, PA | - | Community/Behavioral Health Agency | 02/25/2022 |
| YOUSEF, AHLAM | ORLAND PARK, IL | - | RBT | 09/24/2026 |
| YOUSSEF, AYAT | OVERLAND PARK, KS | - | Mental Health Counselor | 09/23/2026 |
| YOW FLETCHER, NAYSA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| YU, ALINA | RANCHO CUCAMONGA, CA | - | RBT | 09/24/2026 |
| YUAN, CONNIE | FRESH MEADOWS, NY | RDN, CDN | Mental Health Counselor | 09/22/2026 |
| YUAN, XIN | FLUSHING, NY | - | Mental Health Counselor | 08/26/2026 |
| YUSUF, SUMAYO | BURNSVILLE, MN | - | RBT | 09/25/2026 |
| YUSUFF, OLAOLUWA | FARMINGTON HILLS, MI | - | RBT | 09/23/2026 |
| YUSUPOVA, ARIELLA | ELMHURST, NY | - | Speech-Language Pathologist | 09/21/2026 |
| Z HOLISTIC CONNECTIONS PLLCORG | LAKE FOREST, IL | - | Professional Counselor | 03/07/2024 |
| ZABRISKIE, SAMANTHA | OREM, UT | - | RBT | 09/21/2026 |
| ZACARIAS, ESMERALDA | STILLWATER, MN | - | RBT | 09/21/2026 |
| ZACKS, DANA | PORTLAND, OR | LCSW, MPH | Clinical Social Worker | 09/22/2026 |
| ZAGABE, ARIANNAH | WORCESTER, MA | - | Mental Health Counselor | 09/21/2026 |
| ZALDIVAR, DANIELA | ALLENTOWN, PA | - | RBT | 09/25/2026 |
| ZALDO ABREU, GIOVANNA | PLANTATION, FL | - | RBT | 01/26/2026 |
| ZAMARRIPA, JAYCEE | OKLAHOMA CITY, OK | - | RBT | 09/24/2026 |
| ZAMORA, DANIELA | SOUTH JORDAN, UT | LCSW | Clinical Social Worker | 08/07/2025 |
| ZAMORA, ERICA | MISSION, TX | SLP-ASSISTANT | Addiction (Substance Use Disorder) Counselor | 08/31/2018 |
| ZAMORA, JOHN | TIGARD, OR | - | Mental Health Counselor | 09/25/2026 |
| ZAPATA, WINONA | PENSACOLA, FL | - | Clinical Social Worker | 09/21/2026 |
| ZAPPIA, MEREDITH | ASBURY PARK, NJ | LCSW, LCADC,CCS, ACS | Addiction (Substance Use Disorder) Counselor | 10/13/2021 |
| ZARAGOZA, ARIANA | EL SEGUNDO, CA | - | RBT | 09/22/2026 |
| ZARATE, MARISOL | MODESTO, CA | - | RBT | 09/24/2026 |
| ZARIVIA CLAIMS LLCORG | GREENWOOD, IN | - | Clinic/Center | 09/08/2026 |
| ZARLENGA, SABINA | STREETSBORO, OH | LPCC | Mental Health Counselor | 10/09/2013 |
| ZASSO, KALLISTA | SOUTH LAKE TAHOE, CA | - | Case Manager/Care Coordinator | 09/22/2026 |
| ZAVALA-PEREZ, BRISEYDA | MODESTO, CA | - | RBT | 09/25/2026 |
| ZAVALA, LUCINA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ZAVALA, PAMELA | EL SEGUNDO, CA | - | RBT | 09/21/2026 |
| ZEENAT CARE INCORG | SYRACUSE, NY | - | Case Management Agency | 09/23/2026 |
| ZEIS, EVA | SAN DIEGO, CA | - | RBT | 09/21/2026 |
| ZEITER, CARSON | EAST LANSING, MI | - | Mental Health Counselor | 09/24/2026 |
| ZELAYA CUETO, MIRNA | MIAMI, FL | - | Mental Health Counselor | 10/27/2021 |
| ZELEM, AMBER | CHICAGO, IL | - | Professional Counselor | 06/15/2024 |
| ZELENY, JENNIFER | KLAMATH FALLS, OR | - | RBT | 04/08/2026 |
| ZENTZ, SARAH | FORT COLLINS, CO | - | Addiction (Substance Use Disorder) Counselor | 06/28/2022 |
| ZEPEDA, CAREN | FRISCO, TX | - | Mental Health Counselor | 09/25/2026 |
| ZEQUEIRA, YESSICA | MIAMI, FL | BCABA | Assistant Behavior Analyst | 03/13/2024 |
| ZERFOSS, KELLY | HARRISONBURG, VA | LCSW | Clinical Social Worker | 04/27/2012 |
| ZERGER MEYER, ARIELLE | INDIANAPOLIS, IN | - | Clinical Social Worker | 03/21/2021 |
| ZERTUCHE, VICTORIA | TORRANCE, CA | - | RBT | 09/25/2026 |
| ZETINA MARTINEZ, BRENDA | SACRAMENTO, CA | B.A. | RBT | 08/22/2022 |
| ZEWDE, RAHEL | FARMINGTON HILLS, MI | - | RBT | 09/26/2026 |
| ZHAKET, ANAR | LOS ANGELES, CA | - | RBT | 09/22/2026 |
| ZHONG, XINTONG | VENTURA, CA | - | RBT | 09/22/2026 |
| ZIEGENBEIN, AMANDA | LINCOLN, NE | - | RBT | 03/11/2024 |
| ZIEGLER, SUSAN | ORLANDO, FL | LMHC | Mental Health Counselor | 04/17/2007 |
| ZIEMANN, KATLYN | WOODBURY, MN | - | BCBA | 10/06/2020 |
| ZIEMER, HAILEY | ROSEMOUNT, MN | - | RBT | 12/10/2018 |
| ZIMERMAN BEN-YOSEPH, NOGA | BOCA RATON, FL | - | Mental Health Counselor | 09/23/2026 |
| ZIMMER, COLLYN | WORTHINGTON, OH | - | Case Manager/Care Coordinator | 09/25/2026 |
| ZIMMER, MELISSA | WEAVERVILLE, NC | LCSW, LCAS, CCS | Addiction (Substance Use Disorder) Counselor | 02/12/2016 |
| ZIMMER, SARAH | AHWAHNEE, CA | - | Speech-Language Pathologist | 09/22/2026 |
| ZIMMERMAN, MICHAEL | MONROEVILLE, PA | LCSW | Clinical Social Worker | 11/27/2013 |
| ZISKA, MADELYN | DERBY, KS | LPC | Mental Health Counselor | 10/18/2024 |
| ZISSIMOS, KATELYN | TEMECULA, CA | BCBA | RBT | 09/28/2018 |
| ZLIMEN, KAITLYN | DULUTH, MN | - | RBT | 09/24/2026 |
| ZOLNIEREK, GINA | SAN MARCOS, CA | LPCC | Professional Counselor | 04/02/2019 |
| ZONA BLOOM THERAPY SOLUTIONSORG | GILBERT, AZ | - | Speech-Language Pathologist | 09/25/2026 |
| ZOOK, JENNIFER | LOGAN, UT | - | Clinical Social Worker | 09/22/2026 |
| ZORY, ALICE | CRANSTON, RI | LICSW | Clinical Social Worker | 07/17/2006 |
| ZOTECH CARE LLCORG | GREENWOOD, IN | - | Clinic/Center | 09/01/2026 |
| ZUK, ELIZABETH | AURORA, CO | MS, LPC | Professional Counselor | 08/06/2020 |
| ZUKAUSKAS, EMILY | LOUISVILLE, KY | CCC-SLP | Speech-Language Pathologist | 07/29/2025 |
| ZULLO, VALENTINO | CLEVELAND HEIGHTS, OH | LISW-S | Clinical Social Worker | 06/12/2018 |
| ZULUAGA, LIZ | LOS GATOS, CA | - | Mental Health Counselor | 08/10/2015 |
| ZUNO, SAMANTHA | YAKIMA, WA | - | RBT | 09/24/2026 |
| ZUREK, ANNA | DENTON, TX | MS, CCC-SLP | Speech-Language Pathologist | 08/29/2018 |
| ZUREK, ERIN | WESTMONT, IL | - | Speech-Language Pathologist | 05/08/2023 |